Birth & the Newborn
After roughly forty weeks of quiet growth, a fetus becomes a person you can hold. Birth is the single most dramatic transition of the entire lifespan — in a matter of hours the developing human leaves a warm, dark, weightless, fully provisioned world and must, within seconds of arrival, breathe air, regulate its own temperature, and take in food through its mouth for the first time. This chapter follows that passage from the inside out: the stages of labor, the settings and interventions that shape modern birth, the complications that can threaten a newborn, and the tools we use to check that a baby has arrived safely. It ends with a surprise — the newborn who looks so helpless is, in fact, already seeing, hearing, smelling, and preferring the people who love it.
By the end of this chapter you can
- Describe the three stages of labor — dilation, delivery, and afterbirth — and what happens in each.
- Explain the role of oxytocin and positive feedback in driving labor forward.
- Compare common birth settings and attendants and weigh medicated against natural (prepared) childbirth.
- State the main reasons for a cesarean delivery and its trade-offs.
- Define anoxia, prematurity, and low birth weight, and explain why each threatens development.
- Score a newborn on the Apgar scale and interpret the result.
- Identify the major newborn reflexes and explain what they reveal about the nervous system.
- Summarize the surprising sensory and perceptual abilities a newborn already possesses.
Section 1The stages of labor
What sets labor in motion
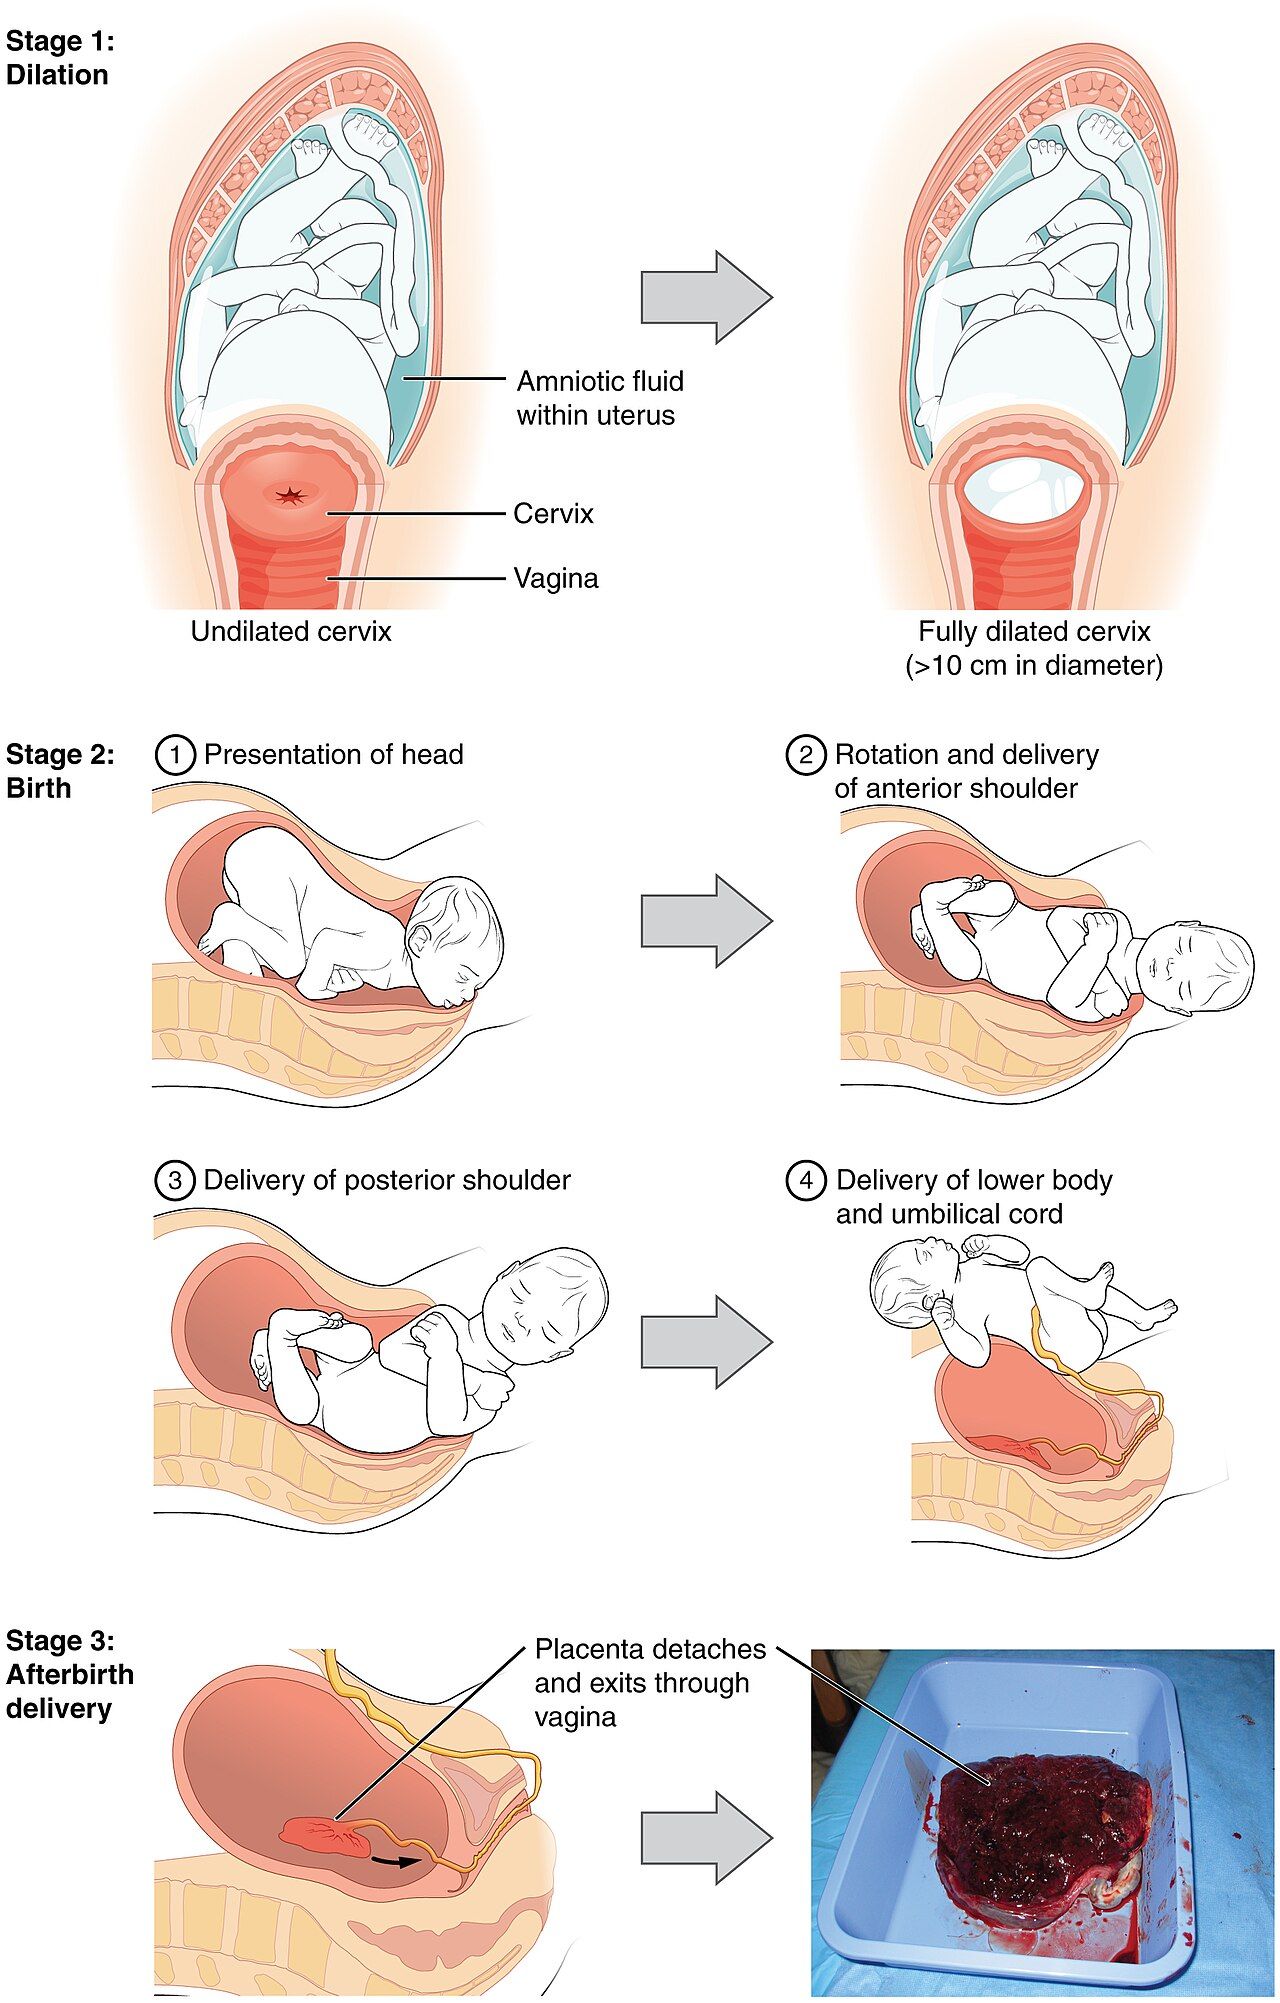
For most of pregnancy the uterus practices with irregular, painless tightenings called Braxton Hicks contractions, but true labor is a different event with its own chemistry. As the fetus reaches term, a rising tide of hormones — estrogen, prostaglandins, and above all oxytocin — brings the uterine muscle to the edge of coordinated contraction. Oxytocin is the engine of labor, and it works through a positive feedback loop: contractions push the baby's head against the cervix, stretch receptors there signal the brain to release more oxytocin, and more oxytocin produces stronger contractions. Unlike the negative feedback that keeps most of the body steady, this loop is designed to build and build until it resolves in only one way — birth.
Three stages, one passage
Obstetricians divide labor into three stages. The first stage — dilation — is by far the longest, often twelve to fourteen hours for a first birth and shorter thereafter. During it the cervix must do two things: efface (thin out) and dilate (open) from closed to a full ten centimeters. Early contractions are mild and widely spaced; by the end of the first stage, in the intense phase called transition, they come every couple of minutes and last a minute each. The second stage — delivery — begins once the cervix is fully open and the mother feels the urge to push. It usually lasts minutes to a couple of hours and ends when the baby is born: the head appears at the vaginal opening (crowning), then the head and shoulders emerge, and the newborn takes its first breath. The third stage — afterbirth — is the briefest, five to thirty minutes, in which continued contractions detach and expel the placenta and umbilical cord. Delivering the whole placenta matters: a fragment left behind can cause dangerous bleeding.
| Stage | What happens | Typical length (first birth) |
|---|---|---|
| 1 — Dilation | Cervix effaces and dilates from 0 to 10 cm; contractions strengthen and quicken, peaking in transition | 12–14 hours (very variable) |
| 2 — Delivery | Mother pushes; the baby crowns, the head and body emerge, first breath is taken | Minutes to ~2 hours |
| 3 — Afterbirth | Contractions detach and expel the placenta and cord | 5–30 minutes |
- Labor has three stages: dilation (longest), delivery of the baby, and afterbirth (the placenta).
- Oxytocin drives labor through a positive feedback loop that builds until birth.
- In the first stage the cervix must efface and dilate to 10 cm; transition is its most intense phase.
- The placenta must be delivered completely, or retained fragments can cause hemorrhage.
Section 2Birth settings and interventions
Where babies are born, and with whom
In most industrialized countries the great majority of births happen in a hospital, attended by an obstetrician or a certified nurse-midwife, because a hospital can respond instantly if something goes wrong. But the setting is not one-size-fits-all. Some families choose a freestanding birth center, a home-like facility staffed by midwives for low-risk pregnancies, or a planned home birth. A growing number are also accompanied by a doula — a trained companion who offers continuous emotional and physical support but does not deliver the baby. Research consistently finds that continuous support from a doula is associated with shorter labors and fewer interventions, a reminder that birth is a psychological event as much as a medical one.
Medicated versus natural birth
A medicated birth uses drugs to manage pain and, sometimes, to control the timing of labor. The most common is the epidural, a regional anesthetic injected near the spinal cord that numbs the lower body while leaving the mother awake and alert. Labor may be started or sped up with synthetic oxytocin (induction and augmentation), the baby's heart rate tracked by electronic fetal monitoring, and delivery assisted by forceps or a vacuum extractor if the second stage stalls. A natural or prepared childbirth, by contrast, aims to minimize or avoid drugs, relying instead on education, breathing and relaxation techniques, movement, and support. The best-known approaches are the Lamaze method (patterned breathing and conditioning) and the Bradley method (partner-coached, drug-free birth). Neither path is simply “better”: an epidural can turn an overwhelming labor into a manageable one, while an unmedicated birth avoids drug side effects and keeps the mother fully mobile. The developmentally important point is that the choice belongs to an informed family.
Cesarean delivery
A cesarean section (C-section) delivers the baby surgically through incisions in the abdomen and uterus rather than through the birth canal. It is the most common major surgery in the world, and it can be lifesaving. Clear indications include a baby positioned feet- or bottom-first (breech), signs of fetal distress on the monitor, a labor that fails to progress, a placenta covering the cervix (placenta previa), and certain prior cesareans. But a C-section is still major surgery, with a longer recovery, higher infection risk, and implications for future pregnancies — which is why the high cesarean rates in many countries (roughly one birth in three in the United States) have prompted efforts to reserve the operation for cases that genuinely need it.
| Approach | What it involves | Trade-off to weigh |
|---|---|---|
| Medicated (epidural) | Regional anesthesia numbs the lower body; mother stays awake | Powerful pain relief; may slow labor or limit mobility |
| Natural / prepared | Breathing, relaxation, movement, support (Lamaze, Bradley) | No drug effects; requires preparation and pain tolerance |
| Induction / augmentation | Synthetic oxytocin starts or strengthens labor | Useful when labor stalls or must begin; contractions can be intense |
| Cesarean section | Surgical delivery through the abdomen and uterus | Lifesaving when needed; major surgery with longer recovery |
- Births occur in hospitals, birth centers, or at home; a doula gives support but does not deliver.
- A medicated birth (commonly an epidural) manages pain with drugs; natural/prepared birth (Lamaze, Bradley) minimizes them.
- A cesarean delivers surgically and is indicated for breech, fetal distress, failure to progress, or placenta previa.
- Every intervention carries benefits and costs; the aim is the right choice for a given birth.
Section 3Birth complications
Anoxia: when oxygen is cut off
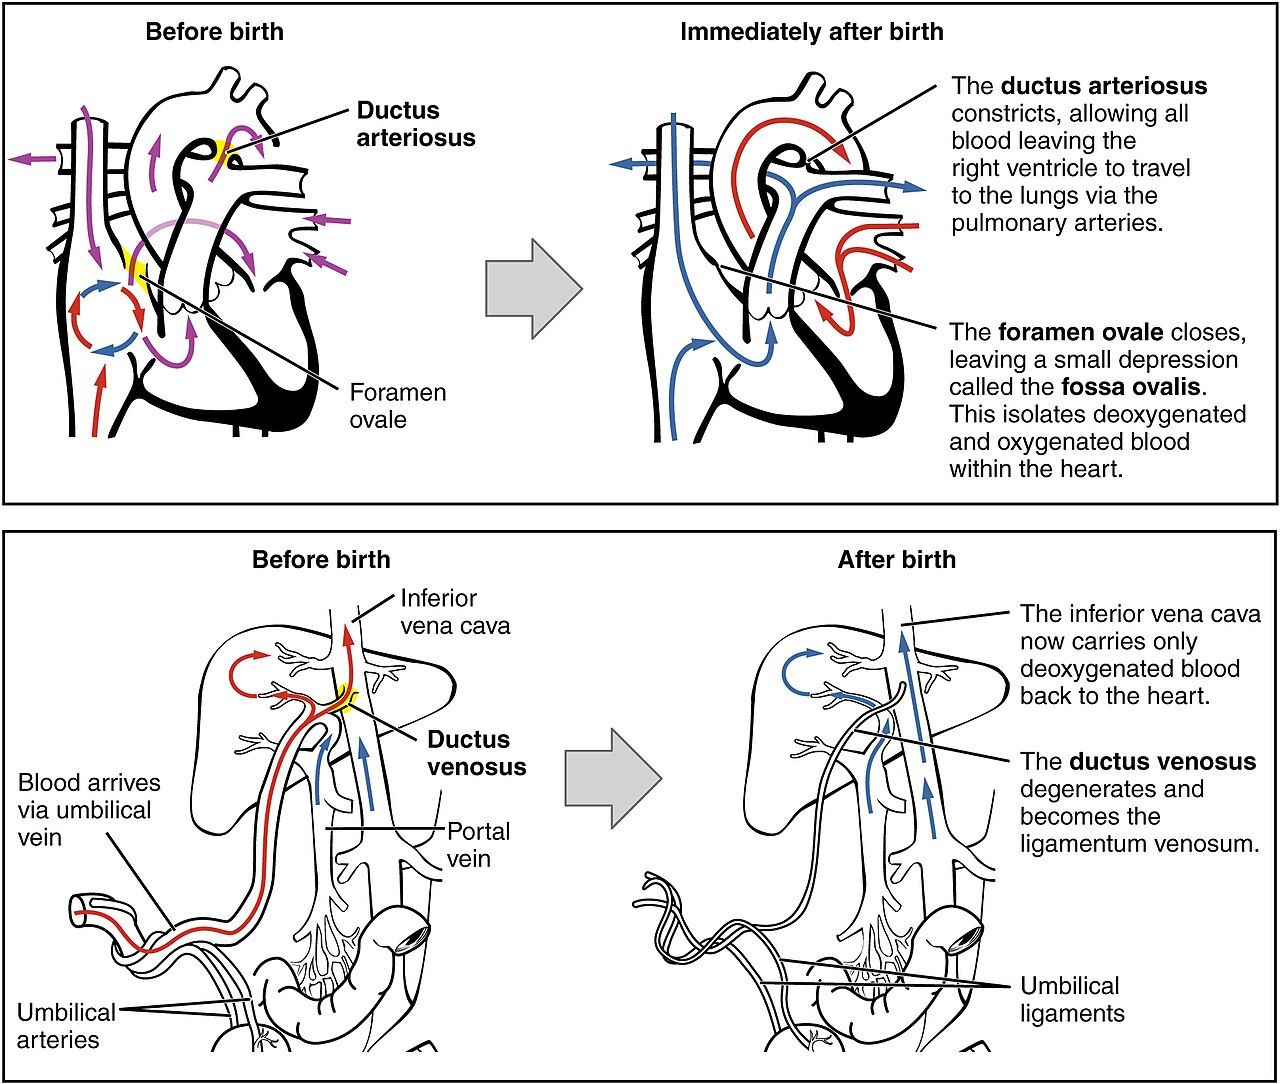
Throughout pregnancy the fetus receives oxygen through the placenta and umbilical cord; at birth that supply is severed and the lungs must take over within seconds. Anything that interrupts oxygen during this transition causes anoxia (a total lack of oxygen) or the milder hypoxia (a reduced supply). Common causes include a cord that becomes pinched or wrapped around the neck, a labor so prolonged that the placenta begins to fail, or a delayed first breath. Brief, mild oxygen loss is usually harmless, but prolonged anoxia can injure the brain, and it is one recognized cause of cerebral palsy, a disorder of movement and posture. Because the brain is so vulnerable, the whole apparatus of fetal monitoring exists mainly to catch falling oxygen early enough to act.
Prematurity and low birth weight
Two overlapping problems account for most newborn difficulty, and it is worth keeping them distinct. A preterm (premature) baby is one born before 37 weeks of gestation; a low-birth-weight (LBW) baby is one weighing less than 2,500 grams (about 5½ pounds), regardless of when it was born. A baby can be both, but not always: some low-weight babies are full-term but small for gestational age (SGA), having grown slowly in the womb. The thresholds sharpen as weight falls — very low birth weight under 1,500 g and extremely low birth weight under 1,000 g — because survival and long-term outcome track closely with size and maturity.
The preterm newborn's central problem is that its organs are unfinished. The lungs may lack surfactant, the soapy film that keeps air sacs from collapsing, producing respiratory distress syndrome; temperature control, feeding, and immune defenses are all immature. Modern neonatal intensive care has transformed the odds, and one of its gentlest tools is kangaroo care — holding the baby skin-to-skin against a parent's chest, which stabilizes heart rate, temperature, and breathing and supports the parent–infant bond.
| Complication | Definition | Why it threatens development |
|---|---|---|
| Anoxia / hypoxia | Total loss / reduction of oxygen around birth | The brain is highly vulnerable; prolonged loss can cause cerebral palsy or brain injury |
| Preterm (premature) | Born before 37 weeks gestation | Immature lungs (lack surfactant), poor temperature control, weak immunity |
| Low birth weight (LBW) | Under 2,500 g (~5½ lb) at birth | Higher risk of infection, feeding difficulty, and developmental delay |
| Small for gestational age | Underweight for gestational age, even if full-term | Signals restricted growth in the womb; distinct from prematurity |
- Anoxia (oxygen loss at birth) can injure the brain and is one cause of cerebral palsy.
- Preterm = born before 37 weeks; low birth weight = under 2,500 g — related but not identical.
- Preterm lungs may lack surfactant, causing respiratory distress syndrome.
- Kangaroo (skin-to-skin) care stabilizes fragile newborns and strengthens bonding.
Section 4Assessing the newborn

The Apgar score
Within the first minute of life, and again at five minutes, the newborn is given an Apgar score — the quick, standardized checkup devised in 1952 by anesthesiologist Virginia Apgar. It rates five signs, each from 0 to 2, for a total of 0 to 10. The five conveniently spell her name: Appearance (skin color), Pulse (heart rate), Grimace (reflex response to stimulation), Activity (muscle tone), and Respiration (breathing effort). A score of 7 to 10 means the baby is doing well; 4 to 6 signals that the newborn needs help, such as suctioning or oxygen; and below 4 is an emergency requiring immediate resuscitation. The Apgar is not a prediction of a child's future — it is a snapshot of how well the baby is making the transition to life outside the womb, and how urgently the team must act.
| Sign | Score 0 | Score 1 | Score 2 |
|---|---|---|---|
| Appearance (color) | Blue / pale | Body pink, limbs blue | Fully pink |
| Pulse (heart rate) | Absent | Below 100 bpm | Above 100 bpm |
| Grimace (reflex) | No response | Grimace | Cry, cough, or pull away |
| Activity (tone) | Limp | Some flexion | Active movement |
| Respiration | Absent | Slow, irregular | Strong cry |
Newborn reflexes
A newborn arrives with a repertoire of automatic, unlearned responses called reflexes, and checking them is a second window on the nervous system. Some are plainly for survival: rooting (stroke the cheek and the baby turns toward it, mouth open) and sucking work together to feed, and swallowing completes the chain. Others are primitive reflexes whose original purpose is less obvious — the Moro (startle) reflex flings the arms out and back at a sudden loss of support; the palmar grasp clamps tiny fingers around anything that touches the palm; the Babinski fans the toes when the sole is stroked; the stepping reflex makes walking motions when the baby is held upright; and the tonic neck reflex throws one arm out in a fencer's pose when the head turns. What makes these reflexes so useful clinically is that they follow a timetable: each should appear at birth and then disappear on schedule as the cerebral cortex matures. A reflex that is missing when it should be present, or one that lingers long past its time, can be an early sign of a neurological problem.
| Reflex | How to elicit it | Fades by (about) |
|---|---|---|
| Rooting | Stroke the cheek → head turns, mouth opens | 4 months (survival) |
| Sucking | Object in the mouth → rhythmic sucking | Persists / becomes voluntary |
| Moro (startle) | Sudden movement or noise → arms fling out, then embrace | 4–6 months |
| Palmar grasp | Press the palm → fingers curl and grip | 3–4 months |
| Babinski | Stroke the sole → toes fan outward | 8–12 months |
| Stepping | Hold upright, feet on a surface → stepping motions | 2 months |
- The Apgar score (0–10) rates Appearance, Pulse, Grimace, Activity, and Respiration at 1 and 5 minutes.
- A score of 7–10 is reassuring; 4–6 needs help; below 4 is an emergency.
- Newborn reflexes include survival reflexes (rooting, sucking) and primitive ones (Moro, grasp, Babinski, stepping, tonic neck).
- Reflexes should appear and then disappear on schedule; deviations can flag neurological concerns.
Section 5What newborns can do

Seeing, hearing, and the rest
The newborn who seems to do nothing but eat, sleep, and cry is in fact a busy perceiver, and researchers have found ingenious ways to ask a baby what it notices. Two tricks unlock the newborn mind. In the preference method, pioneered by Robert Fantz, a baby is shown two things at once and researchers time how long it looks at each — longer looking reveals a preference. In habituation, a baby is shown one stimulus until its interest wanes, then a new one; renewed attention proves the baby can tell the two apart. Using these methods, we have learned that vision is the least mature sense at birth: a newborn sees roughly 20/400, blurry beyond a short range, and focuses best at about 8 to 12 inches — not coincidentally the distance to a caregiver's face during feeding. Yet even this fuzzy vision is choosy: newborns prefer faces, high contrast, and curves, and within days come to prefer their own mother's face.
The other senses are further along. Hearing is nearly mature, having been working for months in the womb: newborns turn toward sounds, prefer the higher pitch of speech, and — in a classic demonstration by DeCasper and Fifer — will suck in a special pattern to hear their own mother's voice over a stranger's. Smell is keen enough that a breastfed newborn will turn toward a pad worn against its own mother's breast rather than another woman's. Taste shows clear preferences too — newborns relax and suck to sweet, and grimace at bitter and sour. And touch, the most mature sense of all, is the channel through which comfort, warmth, and bonding first flow. Far from a blank slate, the newborn is primed from the first hour to find, and prefer, the people who will care for it.
| Sense | Maturity at birth | What the newborn prefers |
|---|---|---|
| Vision | Least mature; ~20/400; clear at 8–12 in | Faces, contrast, curves; the mother's face within days |
| Hearing | Nearly mature; working before birth | Speech sounds; the mother's voice; the native language's rhythm |
| Smell | Well developed | The mother's scent; turns from noxious odors |
| Taste | Well developed | Sweet; rejects bitter and sour |
| Touch | Most mature | Warmth and gentle contact; central to bonding |
- The preference method (looking time) and habituation (renewed interest) let researchers read a newborn's mind.
- Vision is least mature (~20/400, clearest at 8–12 in) but already prefers faces and the mother's face.
- Hearing, smell, and taste are well developed; newborns prefer the mother's voice and scent and the taste of sweet.
- The senses are calibrated toward the caregiver, seeding early attachment.
The chapter in one breath
- Labor has three stages — dilation of the cervix, delivery of the baby, and afterbirth (the placenta) — driven by an oxytocin positive feedback loop.
- Births happen in hospitals, birth centers, or at home, with obstetricians, midwives, and supportive doulas.
- Medicated birth (commonly an epidural) manages pain with drugs; natural/prepared birth (Lamaze, Bradley) minimizes them; a cesarean delivers surgically when needed.
- Anoxia can injure the newborn brain (a cause of cerebral palsy); prematurity and low birth weight are related but distinct threats.
- The Apgar score (0–10) checks color, pulse, reflex, tone, and breathing at 1 and 5 minutes.
- Newborn reflexes — rooting, sucking, Moro, grasp, Babinski, stepping, tonic neck — should appear and fade on schedule, revealing the maturing brain.
- Newborns are surprisingly capable perceivers: vision is least mature, but hearing, smell, and taste are strong, and every sense leans toward the caregiver.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Afterbirth (third stage)
- The final stage of labor, in which the placenta and umbilical cord are expelled after the baby is born.
- Anoxia
- A total lack of oxygen around the time of birth; prolonged anoxia can damage the brain (hypoxia is a partial reduction).
- Apgar score
- A 0–10 rating of a newborn's Appearance, Pulse, Grimace, Activity, and Respiration, taken at 1 and 5 minutes.
- Babinski reflex
- A newborn reflex in which the toes fan outward when the sole of the foot is stroked; normally fades by 8–12 months.
- Cesarean section
- Surgical delivery of a baby through incisions in the abdomen and uterus rather than through the birth canal.
- Crowning
- The moment during delivery when the widest part of the baby's head appears at the vaginal opening.
- Dilation
- The opening of the cervix (to a full 10 cm) during the first stage of labor; paired with effacement, its thinning.
- Doula
- A trained companion who provides continuous emotional and physical support during birth but does not deliver the baby.
- Epidural
- A regional anesthetic injected near the spinal cord that numbs the lower body while the mother stays awake.
- Habituation
- The waning of attention to a repeated stimulus; used to test whether a newborn can tell two stimuli apart.
- Kangaroo care
- Holding a newborn skin-to-skin against a parent's chest to stabilize its vital signs and support bonding.
- Low birth weight (LBW)
- A birth weight under 2,500 g (~5½ lb), regardless of gestational age; below 1,500 g is very low birth weight.
- Moro reflex
- The newborn startle reflex — arms fling out and then embrace — in response to a sudden loss of support; fades by 4–6 months.
- Neonate
- A newborn infant, generally in the first four weeks after birth.
- Oxytocin
- The hormone that drives uterine contractions through a positive feedback loop; also used synthetically to induce labor.
- Placenta
- The organ that supplies the fetus with oxygen and nutrients during pregnancy and is delivered as the afterbirth.
- Preference method
- A technique that infers what a newborn notices from how long it looks at one stimulus versus another.
- Preterm (premature)
- Born before 37 completed weeks of gestation; often, but not always, also low in birth weight.
- Reflex
- An automatic, unlearned response to a specific stimulus; newborn reflexes appear and then disappear on a developmental timetable.
- Rooting reflex
- A survival reflex in which a stroked cheek prompts the newborn to turn its head and open its mouth to feed.
- Surfactant
- A film that keeps the lungs' air sacs from collapsing; when it is lacking in preterm babies, respiratory distress syndrome results.
- Transition
- The intense final phase of the first stage of labor, as the cervix reaches full dilation.