Shock, Trauma and Emergency Care
Every disorder in the preceding thirteen chapters can end in the same place: cells that are not getting enough oxygen to make enough ATP. That is shock, and it does not care whether the insult began in the heart, the gut, the bloodstream or the roadway. What makes shock frightening to a new graduate is that the patient often looks acceptable right up until the moment they do not — because the young, healthy body compensates brilliantly and then fails all at once. What makes it learnable is that the compensations are predictable, the haemodynamic fingerprints of each shock type are distinct, and the interventions are protocolised. This chapter teaches the common pathway and the four stages, then the low-flow shocks, then the distributive shocks and the sepsis Hour-1 bundle, then the trauma primary and secondary survey, and finally the triage and resuscitation logic that governs an emergency department or a rapid response call on your floor. Learn the mechanism and the manifestations follow.
By the end of this chapter you can
- Explain the cellular basis of shock and differentiate the initial, compensatory, progressive and refractory stages by assessment findings rather than by memorised lists.
- Compare the haemodynamic profiles — preload, cardiac output, systemic vascular resistance and venous oxygen saturation — of hypovolaemic, cardiogenic, obstructive and distributive shock.
- Prioritise nursing care for hypovolaemic, cardiogenic and obstructive shock, including fluid resuscitation limits, massive transfusion protocol and the emergencies that require immediate decompression.
- Execute the Surviving Sepsis Hour-1 bundle and recognise septic shock by the Sepsis-3 criteria, including a lactate greater than 2 mmol/L and a vasopressor requirement.
- Distinguish anaphylactic and neurogenic shock from septic shock and administer intramuscular epinephrine without delay.
- Perform the trauma primary survey (ABCDE) and secondary survey (AMPLE, head-to-toe), and identify the lethal triad of hypothermia, acidosis and coagulopathy.
- Apply emergency severity index and START mass-casualty triage, and state what changes when resources are scarce.
- Describe how shock, sepsis and trauma present differently in the older adult and why baseline vital signs mislead.
- Delegate appropriately to the LPN/LVN and UAP during a resuscitation and escalate using SBAR.
Section 1Shock: One Common Pathway, Four Stages
The cellular event that defines shock
Shock is inadequate tissue perfusion relative to metabolic demand. The blood pressure is a downstream number; the actual event is that a cell somewhere is not receiving enough oxygen to run oxidative phosphorylation. When mitochondria cannot use oxygen as the terminal electron acceptor, the cell switches to anaerobic glycolysis, which yields two molecules of ATP per glucose instead of roughly thirty-two. Lactate accumulates as the by-product. That is why serum lactate is the single most useful laboratory marker of shock, and why a rising lactate in a patient whose blood pressure looks fine should worry you more than a normal lactate in a patient who is hypotensive.
With ATP scarce, the sodium-potassium ATPase pump fails. Sodium and water move into the cell, the cell swells, the lysosomal membranes leak, and calcium floods the cytosol. Cell membranes lose integrity and intracellular contents spill into the interstitium, which drives capillary leak, interstitial oedema and further impairment of oxygen diffusion. This is why shock is self-perpetuating: the tissue damage caused by hypoperfusion worsens the hypoperfusion. Every hour of untreated shock makes the next hour harder, which is the entire justification for time-based bundles.
Oxygen delivery to the tissues is the product of cardiac output and arterial oxygen content. Cardiac output is heart rate times stroke volume, and stroke volume depends on preload, afterload and contractility. Arterial oxygen content depends overwhelmingly on haemoglobin and its saturation. Any shock state is a failure of one of those terms: not enough volume returning (preload), not enough pump (contractility), not enough vessel tone or too much (afterload and maldistribution), or not enough haemoglobin to carry the oxygen. Once you can name which term has failed, the treatment is nearly self-evident.
The four stages, read off the patient
In the initial stage, cardiac output has fallen, cells have gone anaerobic, and lactate has begun to rise, but there are no reliable clinical signs. The vital signs are normal. You detect this stage only by a laboratory value or by knowing the mechanism — the patient who has just vomited two litres of blood is in shock whether or not the monitor agrees.
The compensatory stage is where nursing assessment earns its keep. Baroreceptors in the carotid sinus and aortic arch sense the fall in mean arterial pressure and unleash the sympathetic nervous system. Heart rate and contractility rise. Peripheral arterioles constrict, shunting blood from skin, gut and kidney to heart and brain. The renin-angiotensin-aldosterone system and antidiuretic hormone conserve sodium and water. The result is a patient with a normal or even elevated blood pressure, a narrowed pulse pressure (the diastolic rises as vasoconstriction increases), tachycardia, cool and clammy skin, delayed capillary refill, a urine output falling below 0.5 mL/kg/hr, hypoactive bowel sounds and — the finding students consistently undervalue — restlessness, anxiety or confusion from cerebral hypoxia. Hyperventilation blows off carbon dioxide and produces an early respiratory alkalosis. In the compensatory stage the patient is fully salvageable, and this is where the diagnosis should be made.
In the progressive stage, compensation is exhausted. The mean arterial pressure falls below the level that autoregulates cerebral and coronary flow. Prolonged vasoconstriction has ischaemised the capillary beds; the precapillary sphincters relax while the postcapillary ones remain constricted, so fluid pools and leaks into the interstitium. Lactic acidosis overtakes the earlier respiratory alkalosis. Organs begin to declare themselves: crackles and hypoxaemia as acute respiratory distress syndrome develops, oliguria progressing to anuria with a rising creatinine, ileus and possible translocation of gut bacteria, hepatic dysfunction with rising bilirubin and ammonia, and disseminated intravascular coagulation with simultaneous bleeding and clotting. The patient becomes lethargic. This stage requires intensive care.
The refractory or irreversible stage is defined by unresponsiveness — the blood pressure no longer responds to escalating vasopressors and fluids, multiple organ dysfunction syndrome is established, and mortality approaches certainty. Recognising this stage matters clinically for goals-of-care conversations, not for further escalation.
| Stage | What is happening | What you see | Nursing focus |
|---|---|---|---|
| Initial | Anaerobic metabolism begins; lactate rises | Normal vital signs; lactate may exceed 2 mmol/L | Suspect based on mechanism; draw a lactate |
| Compensatory | Sympathetic surge, RAAS, ADH | Tachycardia, narrowed pulse pressure, cool clammy skin, urine output less than 0.5 mL/kg/hr, restlessness, respiratory alkalosis | Recognise and escalate now; this is the reversible window |
| Progressive | Compensation fails; capillary leak, third spacing | Hypotension, metabolic acidosis, crackles and hypoxaemia, anuria, ileus, DIC, lethargy | ICU transfer, vasoactive support, organ-specific care |
| Refractory | Multiple organ dysfunction syndrome | No response to fluids or pressors; profound acidosis | Comfort, family support, goals of care |
The haemodynamic fingerprints
There are four functional categories of shock, and they are separated by three questions: is there enough volume in the tank (preload), is the pump working (cardiac output), and are the pipes appropriately constricted (systemic vascular resistance)? Central venous pressure of 2 to 8 mmHg and pulmonary artery wedge pressure of 6 to 12 mmHg estimate preload. Cardiac output of 4 to 8 L/min and cardiac index of 2.5 to 4.0 L/min/m² describe the pump. Systemic vascular resistance of 800 to 1200 dynes·s·cm⁻⁵ describes the pipes. Mixed venous oxygen saturation of 60 to 80 percent (or central venous saturation around 70 percent) tells you how much oxygen the tissues are extracting.
Three of the four categories look alike at the bedside — cold, clamped-down, tachycardic — because the body compensates for low flow the same way regardless of cause. Distributive shock is the odd one out: the problem is vasodilatation, so the patient may be warm, flushed and bounding early on, with a high cardiac output and a paradoxically high venous oxygen saturation because the cells cannot extract the oxygen being delivered. If you remember only one distinction, remember warm versus cold.
| Type | Preload (CVP/PAWP) | Cardiac output | SVR | SvO₂ | Skin |
|---|---|---|---|---|---|
| Hypovolaemic | Low | Low | High | Low | Cool, pale, clammy |
| Cardiogenic | High | Low | High | Low | Cool, mottled, with crackles and JVD |
| Obstructive | High (tamponade, tension pneumothorax, PE) | Low | High | Low | Cool, JVD, often with a mechanical clue |
| Distributive — septic (early) | Low to normal | Normal to high | Very low | High (extraction failure) | Warm, flushed, bounding |
| Distributive — anaphylactic | Low | Variable | Very low | Variable | Urticaria, angio-oedema, wheeze |
| Distributive — neurogenic | Low | Low | Very low | Variable | Warm, dry, flushed — with bradycardia |
General principles that apply to every shock state
Regardless of type, the goals are the same: restore oxygen delivery, support the failing organ systems and treat the cause. Give supplemental oxygen and secure the airway if the patient cannot protect it or cannot maintain oxygenation. Establish two large-bore intravenous lines — 18 gauge or wider, and 16 gauge or wider in trauma, remembering that a lower gauge number means a wider catheter — because flow through a catheter increases with the fourth power of the radius and falls with length; a short fat peripheral line delivers volume faster than a long central line. Position the patient supine with legs elevated only if it does not compromise breathing; the old Trendelenburg position is no longer recommended because it impairs diaphragmatic excursion and does not reliably improve cardiac output.
The mean arterial pressure target for most adults is at least 65 mmHg, calculated as the systolic plus twice the diastolic, divided by three. Track urine output hourly — below 0.5 mL/kg/hr (roughly 30 mL/hr in an average adult) is renal hypoperfusion until proven otherwise. Trend lactate: a lactate that clears by 10 to 20 percent over the first several hours of resuscitation predicts survival better than any single blood pressure reading. Keep the patient warm, because hypothermia impairs coagulation and shifts the oxyhaemoglobin curve. And treat pain and anxiety, but with the smallest effective doses, because sedatives and opioids blunt the very sympathetic tone that is holding the pressure up.
Shock is cellular oxygen failure, and the compensatory stage — tachycardia, narrowed pulse pressure, cool skin, falling urine output and new restlessness with a still-normal blood pressure — is the window in which the nurse can change the outcome.
Section 2Hypovolaemic, Cardiogenic and Obstructive Shock
Hypovolaemic shock: not enough in the tank
Hypovolaemic shock follows loss of intravascular volume, either as whole blood (haemorrhagic) or as plasma and water (non-haemorrhagic: vomiting, diarrhoea, diuresis in diabetic ketoacidosis, burns, third spacing in pancreatitis or bowel obstruction). Roughly 15 percent of circulating volume can be lost with minimal signs. Beyond that, the sympathetic response becomes visible, and the ATLS haemorrhage classes give a useful mental model, provided you remember that they are a teaching framework rather than a bedside calculator and that older adults, athletes, pregnant patients and anyone on a beta-blocker will violate them.
| Class | Blood loss | Heart rate | Blood pressure | Respiratory rate | Urine output | Mental status |
|---|---|---|---|---|---|---|
| I | Up to 15 percent (750 mL) | Under 100 | Normal | 14 to 20 | Over 30 mL/hr | Slightly anxious |
| II | 15 to 30 percent (750 to 1500 mL) | 100 to 120 | Normal systolic, narrowed pulse pressure | 20 to 30 | 20 to 30 mL/hr | Mildly anxious |
| III | 30 to 40 percent (1500 to 2000 mL) | 120 to 140 | Hypotensive | 30 to 40 | 5 to 15 mL/hr | Anxious, confused |
| IV | Over 40 percent (over 2000 mL) | Over 140 | Markedly hypotensive | Over 35 | Negligible | Confused, lethargic |
Diagnostics are less about confirming shock than about finding the bleeding. An initial haemoglobin and haematocrit are often deceptively normal in acute haemorrhage because the patient loses whole blood — the concentration does not change until dilution occurs, so a normal haemoglobin of 14 to 18 g/dL in a man or 12 to 16 g/dL in a woman never excludes major bleeding. More useful are the lactate (normal under 2 mmol/L) and the base deficit from an arterial blood gas: a base deficit worse than negative 6 mEq/L signals significant tissue hypoperfusion. Type and crossmatch immediately. A focused assessment with sonography for trauma (FAST) finds free fluid in the abdomen or pericardium in minutes; computed tomography is for the patient stable enough to travel.
Management is control the source and replace the volume. Warmed isotonic crystalloid — balanced solutions such as lactated Ringer’s are preferred over large volumes of 0.9 percent sodium chloride, which produces a hyperchloraemic metabolic acidosis — is given as an initial bolus of about one litre in adults, but the patient who does not respond, or who responds and then deteriorates, needs blood, not more saline. Transfuse packed red blood cells with fresh frozen plasma and platelets in a balanced ratio approaching 1:1:1 under a massive transfusion protocol. Give tranexamic acid within three hours of traumatic injury — 1 g intravenously over 10 minutes followed by 1 g over 8 hours — because after three hours it may increase harm. In penetrating trauma without head injury, permissive hypotension (a systolic around 80 to 90 mmHg) until surgical control is deliberate, since raising the pressure pops fresh clot. That rule reverses in traumatic brain injury, where a single episode of hypotension doubles mortality and systolic pressure should be kept at or above 100 to 110 mmHg.
Nursing priorities: two large-bore lines and a fluid warmer, blood products through a filtered set with normal saline only (never lactated Ringer’s in the same line as blood, and never dextrose), vital signs every 5 to 15 minutes, hourly urine output, continuous cardiac monitoring for the hypocalcaemia and hyperkalaemia of massive transfusion, and active warming. Watch the ionised calcium: citrate in banked blood chelates calcium, and an ionised calcium below 4.5 mg/dL prolongs coagulation and depresses contractility.
Cardiogenic shock: the pump has failed
Cardiogenic shock is the failure of the heart to eject enough blood despite adequate filling. The commonest cause is extensive anterior myocardial infarction with loss of more than 40 percent of the left ventricle, but it also follows acute valvular rupture, ventricular septal rupture, myocarditis, end-stage cardiomyopathy, drug toxicity and sustained dysrhythmia. Physiologically it is a vicious circle: reduced cardiac output lowers coronary perfusion pressure, which worsens myocardial ischaemia, which further reduces output. Diagnostic criteria are a systolic pressure under 90 mmHg for at least 30 minutes or the need for support to maintain it, a cardiac index under 2.2 L/min/m², and a pulmonary artery wedge pressure above 15 mmHg.
The findings are those of forward failure plus backward congestion: cool mottled extremities, weak thready pulses, altered mentation, oliguria, and simultaneously jugular venous distension, an S3 gallop, bilateral crackles and frothy pink sputum. Troponin I is elevated (normal under 0.04 ng/mL), B-type natriuretic peptide is high, the electrocardiogram shows the infarct, and the echocardiogram gives you the ejection fraction and the mechanical complication. Chest radiograph shows pulmonary oedema.
Management is emergent revascularisation — percutaneous coronary intervention is the definitive therapy and door-to-balloon time drives survival. Pharmacologically, the balance is delicate. Inotropes such as dobutamine (a beta-1 agonist, 2 to 20 mcg/kg/min) increase contractility but also myocardial oxygen demand and can cause tachydysrhythmias and hypotension through beta-2 vasodilatation. Milrinone, a phosphodiesterase-3 inhibitor, is an inodilator that is renally cleared and accumulates in kidney injury. Norepinephrine is the preferred vasopressor because it raises coronary perfusion pressure with fewer dysrhythmias than dopamine. Diuretics reduce preload only once perfusion is adequate. Mechanical circulatory support — intra-aortic balloon pump or a percutaneous ventricular assist device — bridges the patient to revascularisation or recovery.
The nursing trap in cardiogenic shock is the fluid bolus. A hypotensive patient triggers the reflex to hang fluid, but this ventricle is already overfilled; a bolus will produce flash pulmonary oedema. Assess for crackles, jugular venous distension and an S3 before giving volume to any hypotensive patient. Keep the head of the bed elevated, cluster care to reduce myocardial oxygen demand, monitor titrated drips through a central line with a dedicated lumen, and check the balloon pump insertion site limb for pulse, colour, temperature and sensation every hour.
Obstructive shock: a mechanical block
In obstructive shock, the heart and the volume are adequate but something physically impedes filling or ejection. Three diagnoses matter most, and all three are fixed by relieving the obstruction — a needle, a tube, a drain or clot-dissolving therapy — never by another fluid bolus.
Cardiac tamponade is blood or fluid in the pericardial sac compressing the ventricles. Beck’s triad is hypotension, jugular venous distension and muffled heart sounds; add pulsus paradoxus (a fall in systolic pressure of more than 10 mmHg on inspiration), a narrow pulse pressure and electrical alternans on the electrocardiogram. Bedside echocardiography confirms it. Treatment is pericardiocentesis or a surgical pericardial window. Tension pneumothorax is air trapped under pressure that collapses the lung and shifts the mediastinum, kinking the great vessels. Findings are absent breath sounds and hyperresonance on the affected side, tracheal deviation away from the affected side (a late sign), jugular venous distension, severe respiratory distress and hypotension. This is a clinical diagnosis — do not wait for a radiograph. Treatment is immediate needle decompression with a large-bore catheter in the fifth intercostal space just anterior to the midaxillary line (or the traditional second intercostal space at the midclavicular line), followed by chest tube thoracostomy. Massive pulmonary embolism obstructs the pulmonary arterial circulation, so right ventricular afterload rises abruptly, the right ventricle dilates and fails, and left ventricular filling collapses — producing sudden dyspnoea, pleuritic chest pain, hypoxaemia, jugular venous distension and right heart strain; management is systemic thrombolysis or catheter-directed therapy plus anticoagulation.
Low-flow shock always presents cold and clamped down, but the fix depends on which term failed — volume for the empty tank, revascularisation and inotropes for the failed pump, and a needle, tube or thrombolytic for the mechanical obstruction.
Section 3Distributive Shock: Sepsis, Anaphylaxis and Neurogenic Injury
Sepsis and septic shock
Sepsis is life-threatening organ dysfunction caused by a dysregulated host response to infection. The insult is usually a bacterial cell wall component — endotoxin from gram-negative organisms, peptidoglycan from gram-positive — that triggers a massive release of inflammatory mediators including tumour necrosis factor, interleukin-1 and nitric oxide. Nitric oxide causes profound arteriolar vasodilatation, which drops systemic vascular resistance. Endothelial injury causes capillary leak, so intravascular volume moves into the interstitium and the patient becomes relatively hypovolaemic despite total body fluid overload. Simultaneously the coagulation cascade activates, generating microthrombi that plug capillaries, while consumption of clotting factors produces bleeding — disseminated intravascular coagulation. Mitochondrial dysfunction means the cells cannot use the oxygen even where it arrives, which is why the mixed venous oxygen saturation runs high.
Septic shock is the subset of sepsis in which circulatory and cellular abnormalities are profound enough to substantially increase mortality: clinically, a patient who requires vasopressors to maintain a mean arterial pressure of at least 65 mmHg and has a serum lactate above 2 mmol/L despite adequate fluid resuscitation. Hospital mortality exceeds 40 percent.
Early findings are the warm phase: fever above 38.3°C or hypothermia below 36°C, tachycardia, tachypnoea, warm flushed skin, bounding pulses, a widened pulse pressure and confusion. Late findings are the cold phase, indistinguishable from other shock. Screen with an early warning score, and remember that new confusion, a respiratory rate of 22 or higher, or a systolic pressure of 100 mmHg or less in a patient with suspected infection is a red flag. Laboratory findings include a white cell count above 12,000/mm³ or below 4000/mm³ or more than 10 percent immature bands (normal 5000 to 10,000/mm³), a procalcitonin above 0.5 ng/mL, a platelet count falling below 150,000/mm³, a rising creatinine above 0.6 to 1.2 mg/dL baseline, a bilirubin above 1.2 mg/dL, an INR above 1.5 (normal 0.8 to 1.1) and a lactate above 2 mmol/L.
| Hour-1 bundle element | What it means at the bedside | Why it matters |
|---|---|---|
| Measure lactate; remeasure if above 2 mmol/L | Draw with the initial labs; repeat in 2 to 4 hours | Quantifies tissue hypoperfusion and tracks response |
| Obtain blood cultures before antibiotics | Two sets from two sites, plus urine, sputum, wound as indicated | One dose of antibiotic can sterilise the culture and cost the patient targeted therapy |
| Administer broad-spectrum antibiotics | Within one hour of recognition | Every hour of delay in septic shock increases mortality measurably |
| Begin 30 mL/kg crystalloid | For hypotension or lactate of 4 mmol/L or more; roughly 2 L in a 70 kg adult | Refills the dilated, leaking vascular space |
| Start vasopressors | If hypotensive during or after fluids, to keep MAP at 65 mmHg or above | Restores perfusion pressure while the antibiotics work |
Do not let the cultures delay the antibiotics beyond a few minutes — draw the cultures while the pharmacy mixes the drug, and if access is the problem, get the antibiotic in. Norepinephrine is the first-line vasopressor. Vasopressin at a fixed 0.03 units/min is added second to spare norepinephrine dose. Epinephrine is third. Dobutamine is added if cardiac output remains inadequate after volume and pressors. Intravenous hydrocortisone, 200 mg per day, is considered when vasopressors are still required after adequate fluid; monitor glucose, since it will rise. Transfuse red cells for a haemoglobin under 7 g/dL in most patients. Source control — drain the abscess, remove the infected line, debride the wound — is as important as the antibiotic and is often the step that is delayed.
Nursing priorities: recognise early and activate the sepsis protocol, obtain cultures and administer antibiotics on time, monitor mean arterial pressure and urine output continuously, titrate vasopressors through a central line whenever possible, and inspect the infusion site for extravasation. Norepinephrine extravasation causes tissue necrosis; the antidote is phentolamine infiltrated locally. Assess mentation every hour — encephalopathy is often the first organ to fail and the first to recover.
Anaphylactic shock
Anaphylaxis is an IgE-mediated type I hypersensitivity reaction in which mast cells and basophils degranulate en masse, releasing histamine, tryptase, leukotrienes and prostaglandins. Histamine produces vasodilatation (hypotension), increased capillary permeability (angio-oedema and up to 35 percent of intravascular volume shifting into tissue within minutes), bronchoconstriction (wheeze, stridor) and increased gut motility (cramping, vomiting, diarrhoea). Common triggers are foods (peanuts, tree nuts, shellfish), medications (penicillins, sulfonamides, NSAIDs, contrast media), insect stings and latex.
The clinical picture develops in minutes: pruritus and urticaria, flushing, a sensation of throat tightness or of impending doom, hoarseness, stridor, wheeze, hypotension and tachycardia. Airway compromise from laryngeal oedema is the leading cause of death, which is why anaphylaxis is an airway emergency before it is a circulatory one.
Epinephrine intramuscularly is the first and only first-line drug: 0.3 to 0.5 mg of the 1 mg/mL (1:1000) concentration into the anterolateral thigh (vastus lateralis), repeated every 5 to 15 minutes as needed. Intramuscular thigh administration produces higher and faster peak levels than subcutaneous or deltoid injection. Alpha-1 stimulation reverses the vasodilatation and the angio-oedema; beta-2 stimulation bronchodilates; beta-1 supports the heart. Everything else is adjunctive: an H1 blocker such as diphenhydramine 25 to 50 mg, an H2 blocker such as famotidine, a corticosteroid to blunt the late phase, nebulised albuterol for persistent bronchospasm, aggressive isotonic fluids, and oxygen. Never delay epinephrine to give an antihistamine. Anticipate a biphasic reaction — a recurrence 1 to 72 hours (typically 4 to 12) after the initial event — and observe the patient for at least 4 to 8 hours. Patients on beta-blockers may be refractory to epinephrine; glucagon is the rescue. Discharge teaching centres on the epinephrine autoinjector: carry two, check the expiry date, inject through clothing into the outer thigh, hold for the counted seconds specified by the device, and call emergency services and go to hospital every single time, even if you feel better.
Neurogenic shock
Neurogenic shock follows injury at or above the sixth thoracic vertebra that interrupts sympathetic outflow from the thoracolumbar cord. Without sympathetic tone, arterioles and venules dilate massively and the cardiac accelerator fibres (T1 to T4) are lost, leaving unopposed vagal tone. The result is the one shock state with hypotension and bradycardia together, plus warm, dry, flushed skin below the level of injury and the inability to shiver or sweat, so the patient becomes poikilothermic and takes on the temperature of the room. Other causes include spinal anaesthesia extending too high and severe brainstem injury.
Distinguish neurogenic shock, a haemodynamic problem, from spinal shock, a neurological one: spinal shock is the transient flaccid paralysis, areflexia and loss of bulbocavernosus reflex below the injury that resolves over days to weeks. They may coexist. Management is cautious isotonic fluid (these patients are not volume-depleted; over-resuscitation causes pulmonary oedema), a vasopressor — norepinephrine is preferred over phenylephrine, because a pure alpha agonist worsens the reflex bradycardia — and atropine 1 mg intravenously, repeated every 3 to 5 minutes to a maximum of 3 mg, for symptomatic bradycardia. Current spinal cord injury care targets a mean arterial pressure of 85 to 90 mmHg for the first seven days to maximise cord perfusion. Maintain spinal immobilisation, log roll with adequate staff, monitor for neurogenic bladder and ileus, apply sequential compression devices and start prophylactic anticoagulation, and warm actively.
Distributive shock is a pipe problem: fill the dilated space, then constrict it — 30 mL/kg of crystalloid then norepinephrine in sepsis, intramuscular epinephrine first in anaphylaxis, and fluid plus a pressor plus atropine for the bradycardic patient in neurogenic shock.
Section 4The Trauma Patient: Primary and Secondary Survey
The primary survey: find and fix what kills in minutes
The primary survey is a rapid, ordered search for immediately life-threatening injuries, and each letter is treated before moving to the next. It takes about two minutes and it is repeated any time the patient deteriorates.
| Step | Assess | Intervene |
|---|---|---|
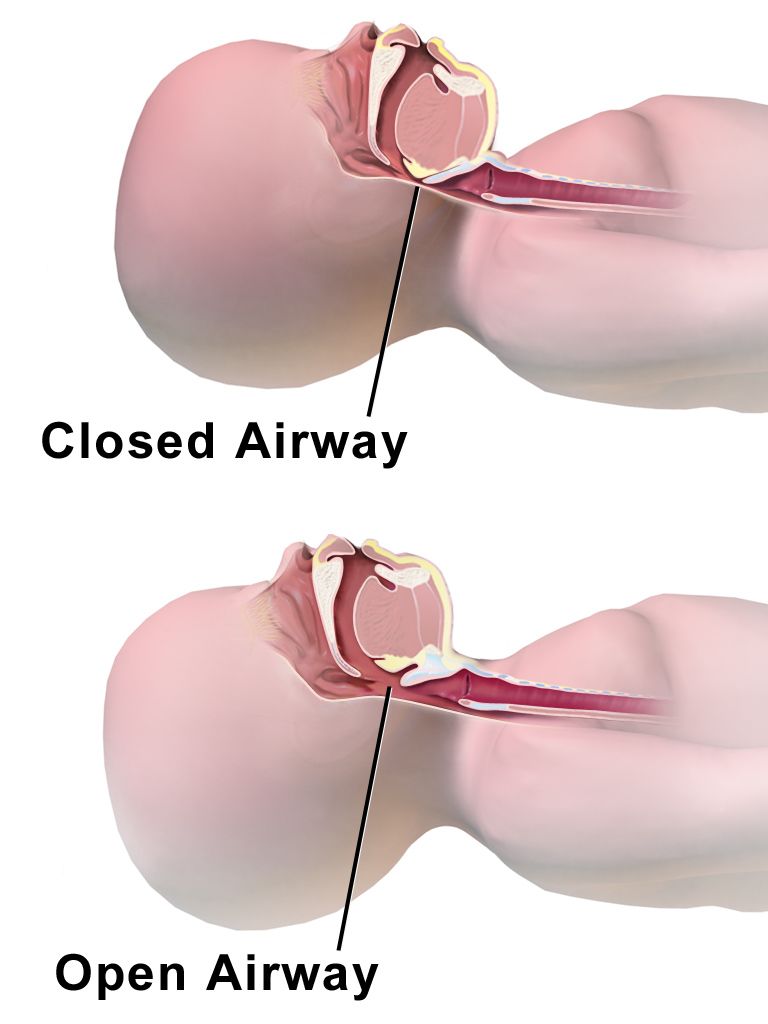
| A — Airway with cervical spine protection | Can the patient speak? Stridor, gurgling, blood, teeth, facial fractures, expanding neck haematoma | Jaw thrust (not head-tilt), suction, oral airway, definitive airway if GCS 8 or less; maintain manual in-line stabilisation and a rigid collar |
| B — Breathing and ventilation | Rate, effort, symmetry of chest rise, breath sounds, tracheal position, oxygen saturation, open wounds, flail segment | High-flow oxygen; needle decompression for tension pneumothorax; three-sided occlusive dressing for an open (sucking) chest wound; bag-mask or intubation |
| C — Circulation with haemorrhage control | Pulse quality and rate, blood pressure, skin colour and temperature, capillary refill, obvious external bleeding, pelvic stability, FAST | Direct pressure, tourniquet for extremity exsanguination, pelvic binder, two large-bore IVs, warmed fluid then blood, tranexamic acid |
| D — Disability | Glasgow Coma Scale, pupil size and reactivity, gross motor movement in all four limbs, blood glucose | Treat hypoglycaemia; manage raised intracranial pressure; recheck after every intervention |
| E — Exposure and environmental control | Undress completely, log roll and inspect the back, axillae, perineum and skin folds | Then cover immediately: warm blankets, warmed fluids, raised room temperature — hypothermia kills trauma patients |
Many trauma systems now place catastrophic external haemorrhage before the airway, because a patient can exsanguinate from a femoral artery faster than they can obstruct. If you can see arterial bleeding, stop it and then start at A. Adjuncts to the primary survey are continuous monitoring, pulse oximetry, capnography, a twelve-lead electrocardiogram, an arterial blood gas with lactate and base deficit, chest and pelvic radiographs, the FAST examination, a gastric tube (orogastric rather than nasogastric if there is midface trauma or a suspected basilar skull fracture) and a urinary catheter (withheld if blood is at the urethral meatus, there is a scrotal haematoma or a high-riding prostate, which suggest urethral injury).
Trauma nursing extends the sequence: F for full set of vital signs and family presence, G for monitoring devices and comfort measures, H for head-to-toe examination and history, and I for inspection of the posterior surfaces. The point of the extension is that the nurse owns the resuscitation adjuncts and the family, and that families who are supported at the bedside during resuscitation cope better afterwards.
The Glasgow Coma Scale and neurological deterioration
The Glasgow Coma Scale scores eye opening out of 4, verbal response out of 5 and best motor response out of 6, for a total of 3 to 15. A score of 13 to 15 is mild, 9 to 12 moderate and 8 or less severe traumatic brain injury. A GCS of 8 or less means intubate — the patient cannot protect the airway. Score the best response, note when a component is untestable (intubated, swollen eyes), and always trend the score rather than reading it once. A two-point drop is an emergency.
Raised intracranial pressure declares itself through a widening gap between systolic and diastolic pressure. Cushing’s triad — hypertension with a widened pulse pressure, bradycardia and irregular or Cheyne-Stokes respirations — is a late, ominous sign of impending herniation, along with a unilaterally dilated non-reactive pupil and decerebrate posturing. Management includes elevating the head of the bed 30 degrees with the head midline to promote venous drainage, avoiding hypoxia and hypotension, maintaining normocapnia (PaCO₂ 35 to 45 mmHg, with brief hyperventilation only for acute herniation), hypertonic saline or mannitol, and neurosurgical consultation. Cerebral perfusion pressure equals mean arterial pressure minus intracranial pressure and should be kept at 60 to 70 mmHg.
The secondary survey and the lethal triad
The secondary survey begins only after the primary survey is complete and the patient is being resuscitated. It is a complete head-to-toe examination plus a history, remembered as AMPLE: Allergies, Medications (anticoagulants and antiplatelets change everything), Past medical history and Pregnancy status, Last meal, and Events and Environment surrounding the injury. Mechanism of injury predicts the injuries you must look for — a fall of more than 20 feet in an adult (about two storeys, or more than two to three times the child’s height in paediatrics), ejection from a vehicle, death of another occupant, an unrestrained driver, or a steering wheel deformity all raise suspicion for occult injury even when the examination is benign.
Examine the head and face for depressed fractures, raccoon eyes and Battle sign, and any clear rhinorrhoea or otorrhoea suggesting a cerebrospinal fluid leak. Palpate the cervical spine. Reassess the chest for rib fractures, flail segments and pulmonary contusion. Palpate the abdomen for tenderness, distension and seat-belt marks. Assess the pelvis once and gently — repeated springing disrupts clot. Log roll to inspect the back and assess rectal tone. Check every extremity for deformity, pulses, motor function and sensation, and document neurovascular status before and after every splint. Give tetanus prophylaxis if the last dose was more than five years ago for a dirty wound.
The lethal triad of trauma is hypothermia, metabolic acidosis and coagulopathy, and each feeds the other two. Hypothermia slows enzymatic clotting reactions and platelet function; acidosis further impairs the clotting cascade and depresses myocardial contractility; the resulting coagulopathy causes more bleeding, which causes more hypoperfusion and more cold resuscitation fluid. Nursing interrupts this cycle: warm every fluid and blood product, use forced-air warming, remove wet clothing at once, raise the ambient temperature, and monitor core temperature continuously. This is why damage control surgery exists — the surgeon controls haemorrhage and contamination, packs the abdomen, and returns the patient to the ICU for rewarming and correction before definitive repair.
Complications to anticipate: compartment syndrome, in which pain out of proportion to injury and pain on passive stretch are the earliest reliable signs (a compartment pressure above 30 mmHg or a delta pressure under 30 mmHg mandates fasciotomy — do not elevate the limb above the heart and do not apply ice, both of which reduce arterial inflow); rhabdomyolysis after crush injury, with tea-coloured urine, a creatine kinase above 5000 units/L, hyperkalaemia and acute kidney injury, treated with aggressive isotonic fluid; fat embolism syndrome 24 to 72 hours after long bone fracture, with hypoxaemia, confusion and a petechial rash over the chest and axillae; venous thromboembolism; and acute respiratory distress syndrome.
Do the primary survey in order every time — airway with C-spine, breathing, circulation with haemorrhage control, disability, exposure — and fix each problem before moving on, then keep the patient warm, because hypothermia, acidosis and coagulopathy kill the trauma patient the surgeon has already saved.
Section 5Emergency and Disaster Care: Triage, Resuscitation and Priorities

Two kinds of triage
Day-to-day emergency department triage uses the five-level Emergency Severity Index and asks two questions in sequence: does this patient need a life-saving intervention right now, and if not, how many resources will they consume? Level 1 is the patient who needs immediate intervention — apnoeic, pulseless, unresponsive, severe respiratory distress, hypotensive with altered mentation. Level 2 is the high-risk patient who cannot wait: new confusion, lethargy or disorientation, severe pain or distress, or danger-zone vital signs; chest pain, stroke symptoms, suspected sepsis and suicidal ideation all live here. Levels 3, 4 and 5 are sorted by anticipated resource use. In routine triage the sickest patient is seen first.
In a mass casualty incident, when needs exceed resources, that principle inverts to the greatest good for the greatest number. START triage sorts adults in under 60 seconds per patient using respirations, perfusion and mental status. Anyone who can walk is tagged green (minor) and directed away. Of the remaining patients: no respirations after a single airway opening manoeuvre is black (expectant); a respiratory rate above 30, a capillary refill over 2 seconds or an absent radial pulse, or an inability to follow simple commands is red (immediate); everyone else is yellow (delayed). The emotionally hard part is the black tag — a patient in profound shock who would consume an entire surgical team is tagged expectant so that four salvageable patients can be treated. Students should understand this as a deliberate ethical framework, not abandonment, and expect NCLEX to test it.
| Tag | Meaning | Typical findings | Action |
|---|---|---|---|
| Red | Immediate | RR above 30, capillary refill over 2 s or no radial pulse, cannot follow commands; airway obstruction, tension pneumothorax, uncontrolled haemorrhage | Treat first; survivable with prompt intervention |
| Yellow | Delayed | Stable vital signs with significant injury — open fractures, large soft tissue wounds, stable abdominal injury | Can wait 30 to 60 minutes |
| Green | Minor | Ambulatory — sprains, minor lacerations, anxiety | Move away from the scene; may assist |
| Black | Expectant or deceased | Apnoeic after airway repositioning; injuries incompatible with survival given available resources | Comfort measures only |
Cardiac arrest and the deteriorating floor patient
Most in-hospital arrests are preceded by hours of documented abnormal vital signs, which means the real skill is not running the code but preventing it. Call the rapid response team for a respiratory rate under 8 or over 28, a heart rate under 40 or over 130, a systolic pressure under 90 or a fall of more than 40 mmHg from baseline, an oxygen saturation under 90 percent on supplemental oxygen, a urine output under 50 mL over 4 hours, new chest pain, a seizure, an acute change in mentation, or your own worry that something is wrong. That last criterion is legitimate and should be used.
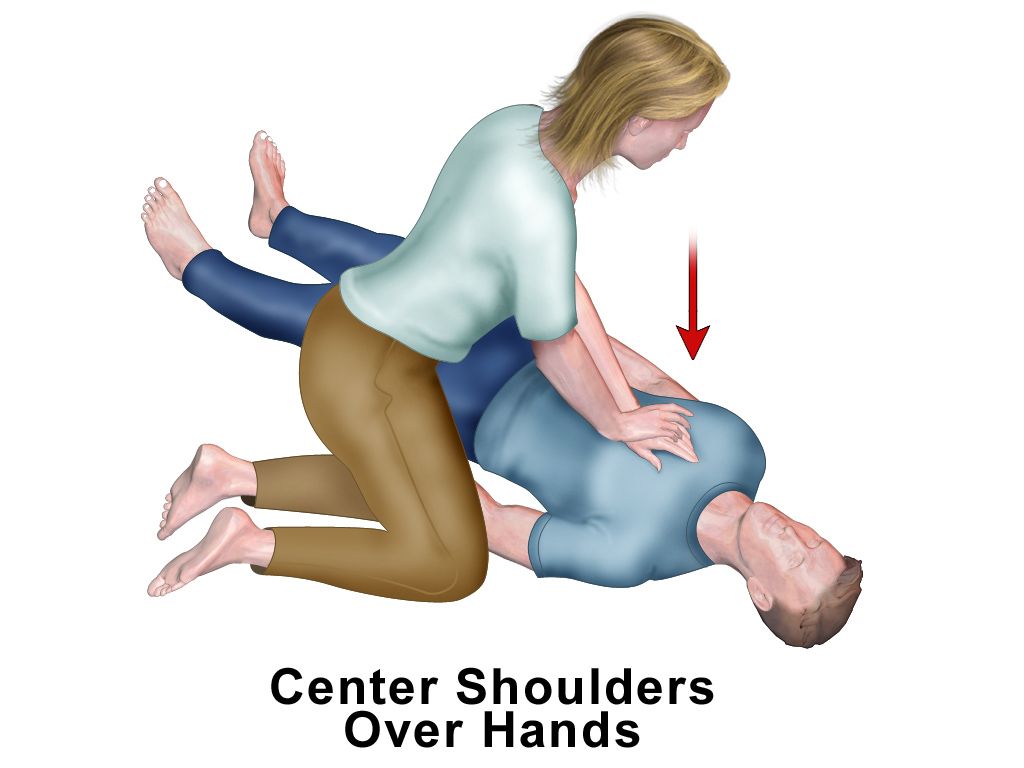
If the patient is pulseless, begin high-quality compressions: 100 to 120 per minute, at least 5 cm (2 inches) but no more than 6 cm (2.4 inches) deep, allowing full chest recoil, with interruptions under 10 seconds and a compressor change every two minutes. Ratio is 30:2 until an advanced airway is placed, then continuous compressions with one breath every 6 seconds. Attach the defibrillator as soon as it arrives. Ventricular fibrillation and pulseless ventricular tachycardia are shockable — defibrillate immediately (120 to 200 J biphasic) and resume compressions without a pulse check. Asystole and pulseless electrical activity are not shockable; give epinephrine 1 mg intravenously as soon as possible and every 3 to 5 minutes, and hunt the reversible causes (hypovolaemia, hypoxia, hydrogen ion excess, hypo- and hyperkalaemia, hypothermia, tension pneumothorax, tamponade, toxins, and thrombosis coronary or pulmonary). Amiodarone 300 mg then 150 mg, or lidocaine, is given for refractory shockable rhythms. End-tidal carbon dioxide below 10 mmHg means compressions are inadequate; an abrupt rise above 40 mmHg suggests return of spontaneous circulation. After ROSC, treat the cause, avoid hyperoxia and hypotension, obtain a twelve-lead electrocardiogram and consider targeted temperature management between 32 and 37.5°C for at least 24 hours.
Environmental emergencies and poisoning
Heat stroke is a core temperature above 40°C (104°F) with central nervous system dysfunction; classic heat stroke in older adults is often accompanied by hot dry skin, while exertional heat stroke in athletes may still be sweating. Cool aggressively — cold water immersion is the fastest method — and stop at about 38.9°C (102°F) to avoid overshoot. Do not give antipyretics; the hypothalamic set point is normal. Monitor for rhabdomyolysis and DIC. Hypothermia is mild at 32 to 35°C, moderate at 28 to 32°C and severe below 28°C. Handle the patient gently, because a cold myocardium fibrillates easily, and remember that resuscitation continues until the patient is rewarmed — a patient is not dead until warm and dead.
In poisoning, support the ABCs first and identify the agent second. Activated charcoal 1 g/kg is useful within about an hour of ingestion of many substances but is contraindicated in an unprotected airway, ileus and corrosive or hydrocarbon ingestion. Syrup of ipecac is obsolete. Naloxone 0.4 to 2 mg reverses opioid respiratory depression; titrate to respirations rather than to full alertness, and anticipate that its half-life is shorter than that of many opioids, so the patient may re-sedate. Flumazenil for benzodiazepine overdose is used with great caution because it can precipitate seizures in the chronically dependent. For acetaminophen, obtain a four-hour post-ingestion level and plot it on the Rumack-Matthew nomogram; N-acetylcysteine is highly effective when started within 8 hours of ingestion. Always contact the poison control centre.
Older adults, delegation and escalating with SBAR
Older adults present atypically in every category in this chapter. Baseline hypertension means a systolic of 110 mmHg may represent profound shock in someone who normally runs 165. Beta-blockers and calcium channel blockers blunt the compensatory tachycardia, so the heart rate may stay at 78 while the patient exsanguinates; in geriatric trauma a heart rate above 90 and a systolic below 110 mmHg are already abnormal. Reduced cardiac reserve, stiff ventricles and impaired renal concentrating ability mean less tolerance for both under- and over-resuscitation. Blunted thermoregulation and immunosenescence produce afebrile sepsis. Myocardial infarction presents as dyspnoea, fatigue, syncope or confusion rather than crushing chest pain. And delirium is frequently the first and only sign of infection, hypoxaemia, hypoglycaemia or hypoperfusion — treat acute confusion as an emergency, not as expected ageing. Ground-level falls are a major trauma mechanism in this group, rib fractures carry high mortality because of splinting and pneumonia, and polypharmacy with anticoagulants converts minor head trauma into intracranial haemorrhage.
Delegation during a resuscitation follows the same law as everywhere else: the registered nurse retains assessment, evaluation, teaching, triage, unstable patients and anything requiring nursing judgement. Unlicensed assistive personnel may take and report vital signs on stable patients, apply oxygen by nasal cannula per order, record intake and output, obtain a point-of-care glucose where policy permits, apply cooling or warming blankets, perform chest compressions if trained, run specimens and support the family. Licensed practical or vocational nurses may monitor a stable patient, administer many routine medications, perform wound and tracheostomy care and reinforce teaching. What may not be delegated: the initial and ongoing assessment of an unstable patient, triage decisions, titration of vasoactive drips, initiation of blood transfusion, intravenous push medications in most jurisdictions, and patient or family education.
Escalate with SBAR. Situation: “Dr. Rivera, this is Anika, RN on 4 West. I am calling about Mr. Cole in 412, post-op day two from a sigmoid colectomy. His blood pressure is 84 over 48 and he is newly confused.” Background: “He has been febrile to 38.6 since this morning and his heart rate has climbed from 88 to 124 over four hours.” Assessment: “His skin is warm and flushed, urine output has been 15 mL an hour for three hours, and his lactate just resulted at 4.2. I believe he is in septic shock, likely from an anastomotic leak.” Recommendation: “I have two large-bore IVs and cultures drawn. I need orders for broad-spectrum antibiotics now, a 30 mL/kg crystalloid bolus, a repeat lactate, urgent imaging and ICU evaluation.” Red flags that require an immediate call regardless of the hour: a systolic under 90 or a mean arterial pressure under 65, a lactate of 4 mmol/L or higher, a new oxygen requirement or saturation under 90 percent, urine output under 0.5 mL/kg/hr for two consecutive hours, a two-point drop in the Glasgow Coma Scale, new unilateral pupil dilation, absent pulses distal to an injury, and any patient who tells you something is very wrong.
Emergency care is applied prioritisation: routine triage treats the sickest first, disaster triage treats the most salvageable first, deterioration is usually visible in the vital signs for hours before an arrest, and in the older adult the first sign of catastrophe is often nothing more than new confusion.
The chapter in one breath
Shock is a failure of oxygen delivery at the cell, and its stages — initial, compensatory, progressive, refractory — describe how long the sympathetic nervous system can hide that failure. The compensatory stage, with tachycardia, a narrowed pulse pressure, cool clammy skin, falling urine output and a new restlessness while the blood pressure still reads normal, is where the nurse changes the outcome. The four functional categories separate by preload, cardiac output and systemic vascular resistance: hypovolaemic and cardiogenic and obstructive shock all run cold with a high resistance and a low output, while distributive shock runs warm with a low resistance. That distinction sets the treatment — volume for the empty tank, revascularisation and inotropes for the failed pump, a needle or a tube or a thrombolytic for the mechanical block, and fluid then norepinephrine for the dilated one. Sepsis has an Hour-1 bundle: lactate, cultures before antibiotics, antibiotics, 30 mL/kg of crystalloid, vasopressors to a mean arterial pressure of 65. Anaphylaxis has one first-line drug given intramuscularly in the thigh. Trauma has an order — ABCDE, then AMPLE and head to toe — and one enemy triad: cold, acid and clot failure. Everything else is prioritisation.
Words worth knowing
| Term | What it means |
|---|---|
| Shock | Inadequate tissue perfusion relative to metabolic demand, producing anaerobic metabolism and cellular injury. |
| Mean arterial pressure (MAP) | Average pressure driving organ perfusion, roughly (systolic plus twice diastolic) divided by three; target at least 65 mmHg. |
| Pulse pressure | Systolic minus diastolic pressure; narrowing is an early sign of compensated hypovolaemia. |
| Lactate | By-product of anaerobic metabolism; normal under 2 mmol/L, and 4 mmol/L or above signals severe tissue hypoperfusion. |
| Base deficit | Amount of base needed to normalise pH; worse than negative 6 mEq/L suggests significant shock. |
| Systemic vascular resistance (SVR) | Afterload of the left ventricle; normal 800 to 1200 dynes·s·cm⁻⁵, very low in distributive shock. |
| Preload | Ventricular filling volume, estimated by CVP (2 to 8 mmHg) or pulmonary artery wedge pressure (6 to 12 mmHg). |
| Cardiac index | Cardiac output adjusted for body surface area; normal 2.5 to 4.0 L/min/m², under 2.2 in cardiogenic shock. |
| Septic shock | Sepsis requiring vasopressors for a MAP of 65 mmHg or more with a lactate above 2 mmol/L despite adequate fluid. |
| Hour-1 bundle | Lactate, blood cultures before antibiotics, broad-spectrum antibiotics, 30 mL/kg crystalloid, vasopressors for persistent hypotension. |
| Disseminated intravascular coagulation | Simultaneous widespread microthrombosis and bleeding from consumption of clotting factors and platelets. |
| Beck’s triad | Hypotension, jugular venous distension and muffled heart sounds — cardiac tamponade. |
| Tension pneumothorax | Trapped intrapleural air that collapses the lung and shifts the mediastinum; a clinical diagnosis needing immediate needle decompression. |
| Neurogenic shock | Loss of sympathetic tone from injury at or above T6, causing hypotension with bradycardia and warm dry skin. |
| Spinal shock | Transient flaccid paralysis and areflexia below a cord injury; a neurological, not haemodynamic, phenomenon. |
| Biphasic reaction | Recurrence of anaphylaxis 1 to 72 hours after the initial event, justifying prolonged observation. |
| Lethal triad | Hypothermia, metabolic acidosis and coagulopathy, each worsening the other two in major trauma. |
| Massive transfusion protocol | Balanced replacement of packed red cells, plasma and platelets in a ratio approaching 1:1:1. |
| Permissive hypotension | Deliberately accepting a systolic of about 80 to 90 mmHg in uncontrolled penetrating haemorrhage until surgical control. |
| START triage | Mass-casualty sort by respirations, perfusion and mental status into immediate, delayed, minor and expectant. |