The Microbial World & Why It Matters to Nursing
You are outnumbered. For every human cell you carry, there is roughly one bacterial cell living on or inside you — and the vast majority are harmless, even helpful. Microbiology is the study of that invisible world: the bacteria, viruses, fungi, and parasites that share your body and, occasionally, make your patients sick. This chapter introduces the cast of characters, explains the difference between a microbe that lives with you and one that harms you, tells the story of how we figured out that germs cause disease, and shows you how those germs are named. Everything else in this course — and much of what you will do at the bedside to keep patients safe — grows out of these first ideas.
By the end of this chapter you can
- Define microbiology and identify the major groups of microorganisms.
- Distinguish cellular from acellular microbes, and prokaryotic from eukaryotic cells.
- Explain the human microbiome and contrast normal flora, opportunistic pathogens, and true pathogens.
- Distinguish colonization, infection, and disease, and explain why infection prevention is central to nursing.
- Summarize the germ theory of disease and the contributions of Semmelweis, Pasteur, and Koch.
- State Koch's postulates and what they are for.
- Correctly write and read a microbe's binomial name and place organisms in the three-domain system.
Section 1Meet the microbes
What counts as a microbe
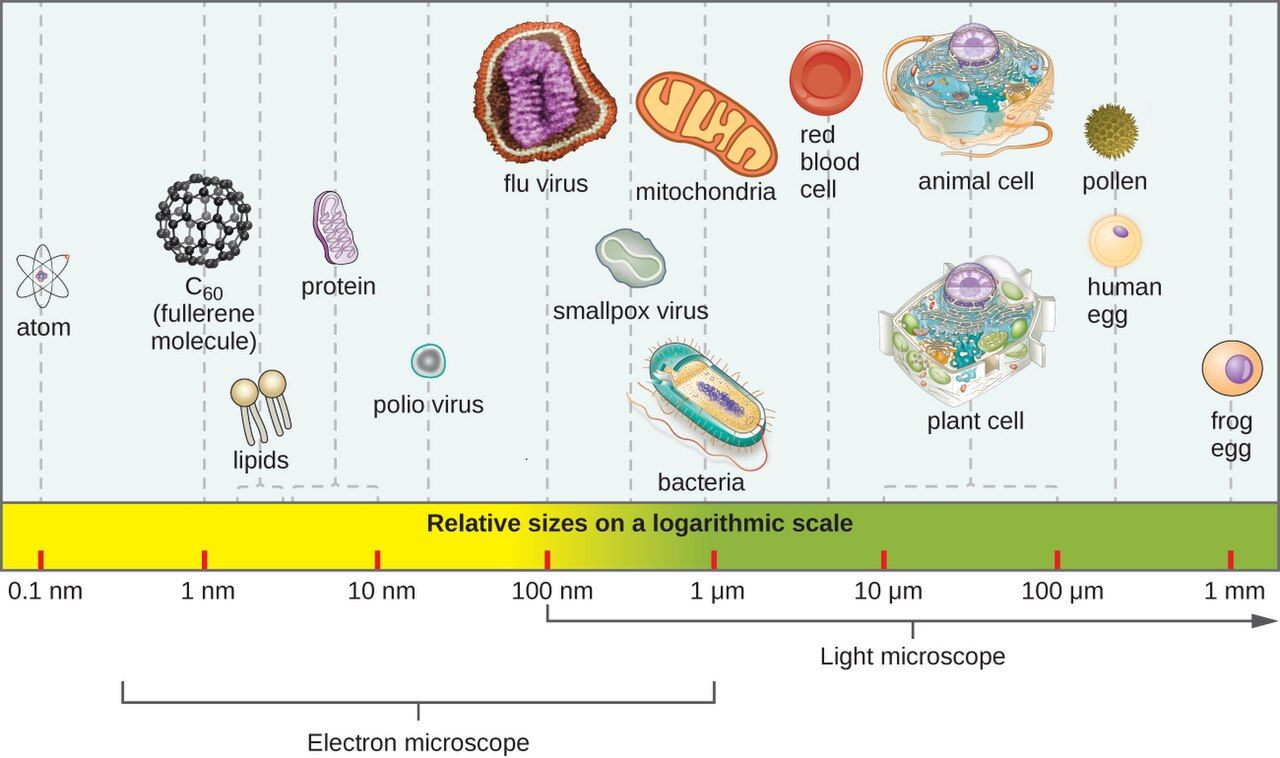
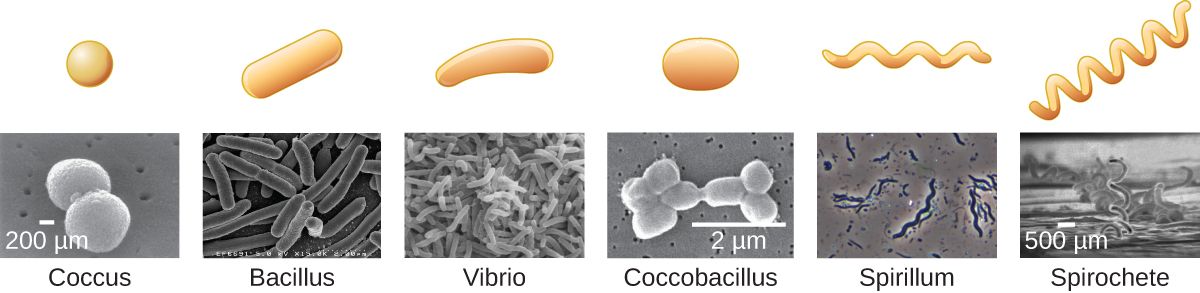
A microorganism (or microbe) is simply a living thing too small to see with the naked eye — you need a microscope. That single size rule sweeps together a wildly diverse group of organisms that are otherwise unrelated. Learning microbiology begins with sorting that group into a handful of families, because the family a microbe belongs to tells you almost everything that matters clinically: how it is built, how it grows, what disease it causes, and — crucially — which drugs will kill it.
The main groups
Microbes split first into cellular organisms (made of one or more true cells) and acellular agents (not cells at all). Among the cellular microbes, the deepest divide is between prokaryotes — small, simple cells with no nucleus — and eukaryotes, larger cells that keep their DNA in a membrane-bound nucleus, just like your own cells do.
| Group | Cell type | Key features | Example disease |
|---|---|---|---|
| Bacteria | Prokaryote | Single-celled, no nucleus; enormous variety; many are our normal flora | Strep throat, UTIs, TB |
| Archaea | Prokaryote | Prokaryotes of extreme environments; none are known to cause human disease | — |
| Fungi | Eukaryote | Yeasts (single-celled) and molds (filamentous) | Thrush (Candida), ringworm |
| Protozoa | Eukaryote | Single-celled eukaryotic microorganisms (protists); often motile; many are parasites | Malaria, giardiasis |
| Helminths | Eukaryote (animal) | Parasitic worms — not micro, but their eggs/larvae are, and they're studied here | Pinworm, tapeworm |
| Viruses | Acellular | Genetic material in a protein coat; must hijack a host cell to replicate | Influenza, COVID-19, HIV |
Keep the prokaryote–eukaryote line firmly in mind, because it is the reason many drugs are safe to give: an antibiotic that attacks a structure found only in bacterial (prokaryotic) cells — a cell wall, a bacterial ribosome — can wipe out the infection while leaving your patient's eukaryotic cells untouched. That principle, called selective toxicity, is the whole reason antimicrobial therapy is possible.
Tap through the six groups of microbes below.
- A microbe is any organism too small to see unaided.
- Cellular microbes are bacteria, archaea, fungi, protozoa (plus helminths by tradition); viruses are acellular.
- Prokaryotes (bacteria, archaea) have no nucleus; eukaryotes (fungi, protozoa) do.
- Selective toxicity — hitting a microbial-only target — is why antimicrobial drugs can cure without poisoning the patient.
Section 2Microbes on and in us
The microbiome: your resident microbes
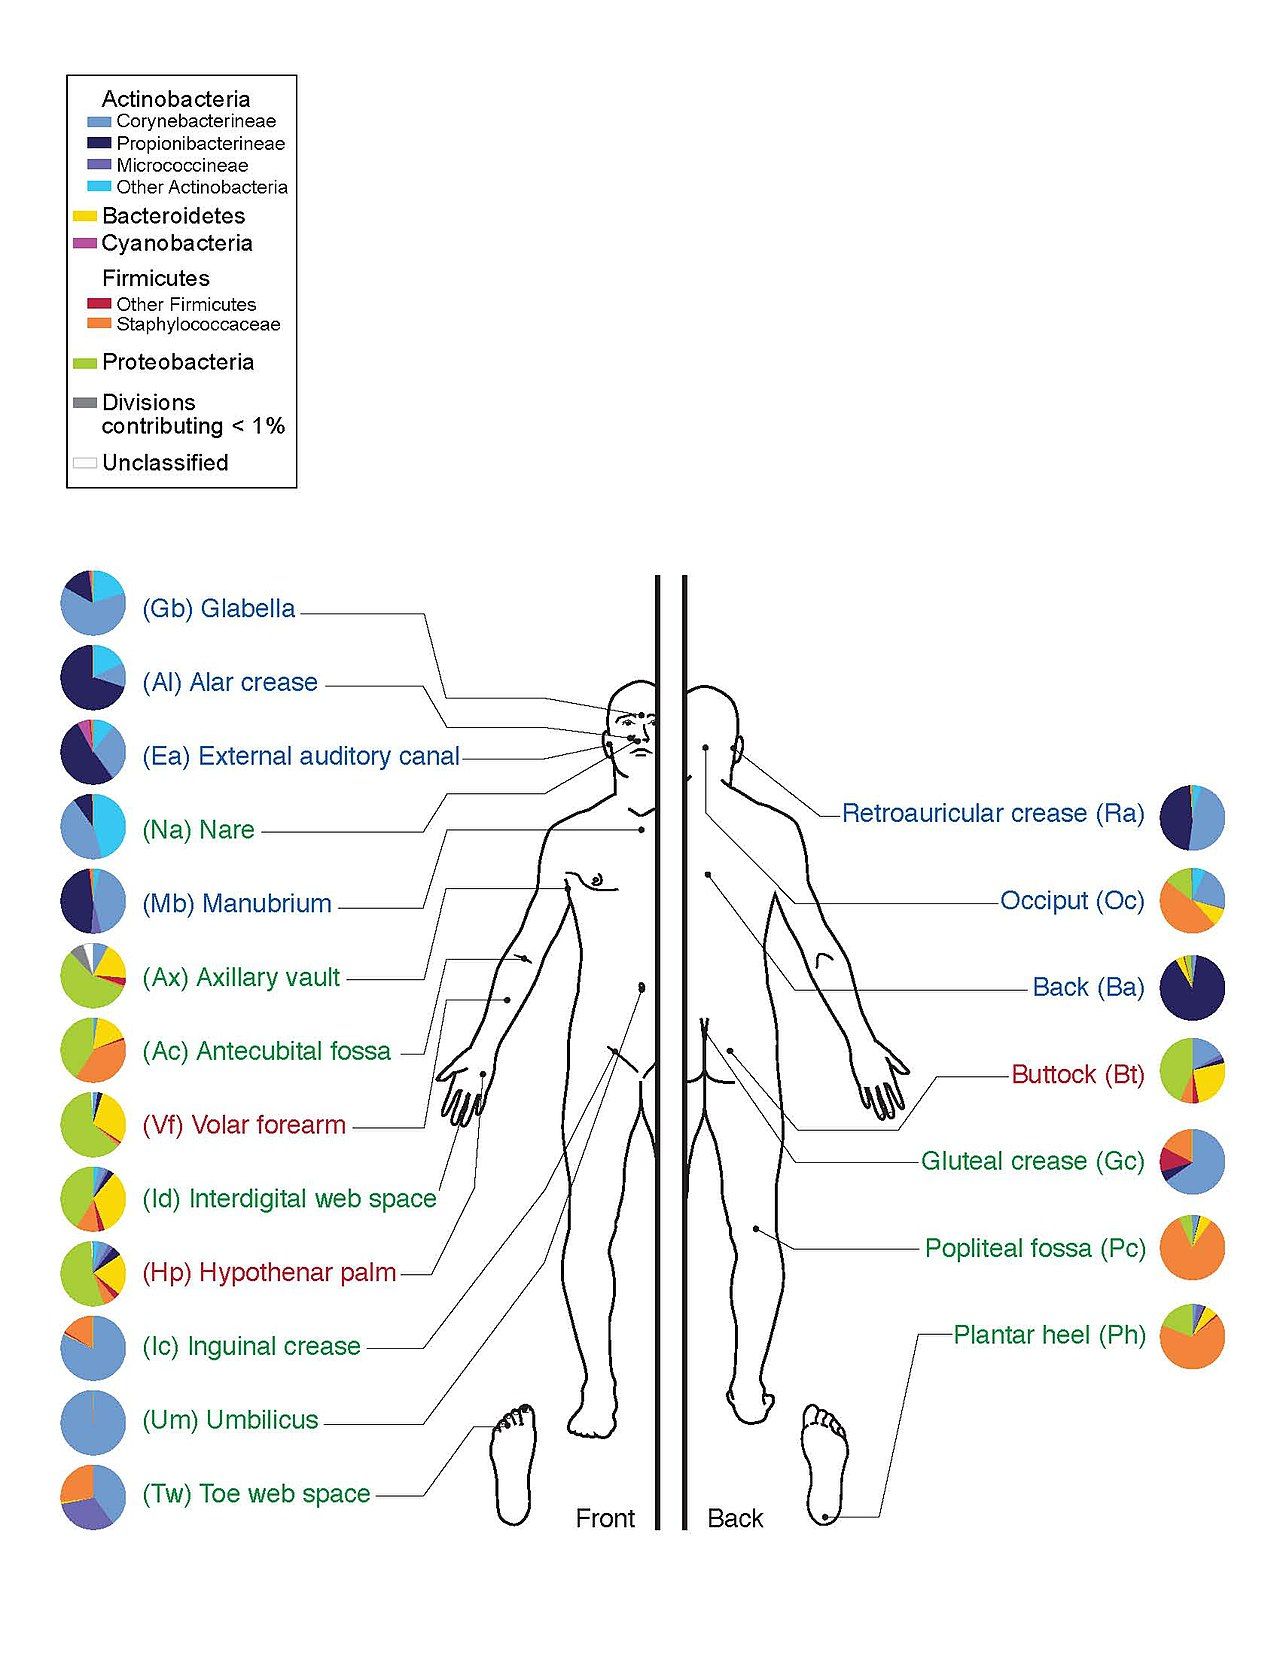
You are not sterile, and you were never meant to be. Trillions of microbes — collectively the microbiota, and together with their genes the microbiome — colonize your skin, mouth, gut, and other surfaces from the moment you are born. These normal flora are not freeloaders. They earn their keep: gut bacteria synthesize vitamin K and some B vitamins, they crowd out invaders by occupying space and consuming nutrients (competitive exclusion), and they help train the developing immune system to tell friend from foe.
Flora come in two flavors. Resident flora live with you long-term and re-establish themselves if disturbed. Transient flora are just passing through — picked up from a doorknob or a patient's bedrail — and this is precisely the population that hand hygiene is designed to remove before it moves from one patient to the next.
When a good microbe goes bad
Many of the organisms that cause healthcare infections are not exotic invaders at all — they are the patient's own normal flora, turned dangerous by opportunity. An opportunistic pathogen causes no trouble in its usual home but causes disease when it is moved somewhere new, when the normal flora are wiped out, or when the host's defenses fall. Escherichia coli is harmless in the colon but causes a urinary tract infection if it reaches the bladder; Candida overgrows into thrush when antibiotics clear its bacterial competitors; and Clostridioides difficile blooms into severe colitis after antibiotics flatten the gut's normal community.
| What normal flora do | Why it matters |
|---|---|
| Make vitamin K & some B vitamins | Nutrition; K is needed for clotting |
| Competitive exclusion of pathogens | They physically and chemically crowd out invaders |
| Train the immune system | Early exposure calibrates immune responses |
| Maintain low pH / hostile niches | e.g., vaginal lactobacilli keep pH low, blocking pathogens |
Explore where your normal flora live.
- The microbiome is the community of microbes that normally live on and in the body.
- Normal flora are mostly beneficial — nutrients, competitive exclusion, immune training.
- Opportunistic pathogens are normal flora that cause disease when displaced, unopposed, or the host is weakened.
- Removing transient flora is the entire point of hand hygiene.
Section 3When microbes cause disease
Colonization, infection, disease
These three words are often used loosely in conversation, but in the clinical world they mean different things, and confusing them leads to over-treatment. Colonization means a microbe is simply present and multiplying on a body surface without causing harm — the patient has no symptoms. Infection means a microbe has invaded and the body is now responding to it. Disease is the step further, when that infection produces recognizable signs and symptoms and impairs function.
The distinction is intensely practical. A wound swab growing bacteria in a patient with no redness, warmth, or fever usually reflects colonization, not infection — treating it with antibiotics does harm without benefit. A pathogen, meanwhile, is any microbe capable of causing disease, and its virulence is the degree of harm it can do (we unpack the machinery of virulence in Chapter 10).
| State | Microbe present? | Host responding? | Symptoms? |
|---|---|---|---|
| Colonization | Yes (multiplying) | No | No |
| Infection | Yes (invading) | Yes | Not necessarily |
| Disease | Yes | Yes | Yes — signs & symptoms |
Why this is a nursing problem
Infections are among the most common and most preventable threats a hospitalized patient faces. Healthcare-associated infections (HAIs) — catheter-associated UTIs, central-line bloodstream infections, surgical-site infections, ventilator-associated pneumonia — affect roughly one in every thirty-one hospital patients on any given day. The nurse is the person at the bedside most often, which makes the nurse the single most important line of defense: every hand wash, every sterile field, every catheter removed a day earlier prevents an infection that would otherwise have happened.
Step through the three clinical states below.
- Colonization (present, no harm) ≠ infection (invading, host responding) ≠ disease (symptoms & impairment).
- A pathogen can cause disease; virulence is how much harm it does.
- HAIs are common and largely preventable, and the nurse is the front line of prevention.
Section 4How we found out microbes cause disease

From bad air to germ theory
For most of history, disease was blamed on miasma — bad air — or on spontaneous generation, the idea that life simply arose from non-living matter. The germ theory of disease, the recognition that specific microbes cause specific diseases, is only about 150 years old, and it is the intellectual foundation of everything nurses do to prevent infection.
Three people worth knowing
Ignaz Semmelweis, a Viennese obstetrician in the 1840s, noticed that mothers died of childbed fever far more often on the ward staffed by doctors (who came straight from autopsies) than on the ward staffed by midwives. He ordered handwashing with a chlorine solution, and the death rate plummeted. He could not explain why it worked — germ theory did not yet exist — and his colleagues ridiculed and rejected him. He is now remembered as the father of hand hygiene.
Louis Pasteur disproved spontaneous generation with his elegant swan-neck flask experiments, showing that broth stayed sterile until microbes from the air reached it. He gave us pasteurization and helped establish that microbes drive fermentation and spoilage. Robert Koch then supplied the rigor: a systematic way to prove that one particular microbe causes one particular disease, now called Koch's postulates.
| Koch's postulate | In plain English |
|---|---|
| 1 | The microbe is found in every case of the disease, and absent in healthy hosts |
| 2 | It can be isolated from a sick host and grown in pure culture |
| 3 | The cultured microbe causes the same disease when introduced into a healthy host |
| 4 | The same microbe can be re-isolated from that newly diseased host |
Walk through Koch's four-step proof below.
- Germ theory — specific microbes cause specific diseases — is the basis of all infection control.
- Semmelweis = hand hygiene; Pasteur = disproved spontaneous generation, pasteurization; Koch = postulates linking microbe to disease.
- Koch's postulates are the logical test for proving a given microbe causes a given disease.
Section 5Naming and classifying microbes
The three domains
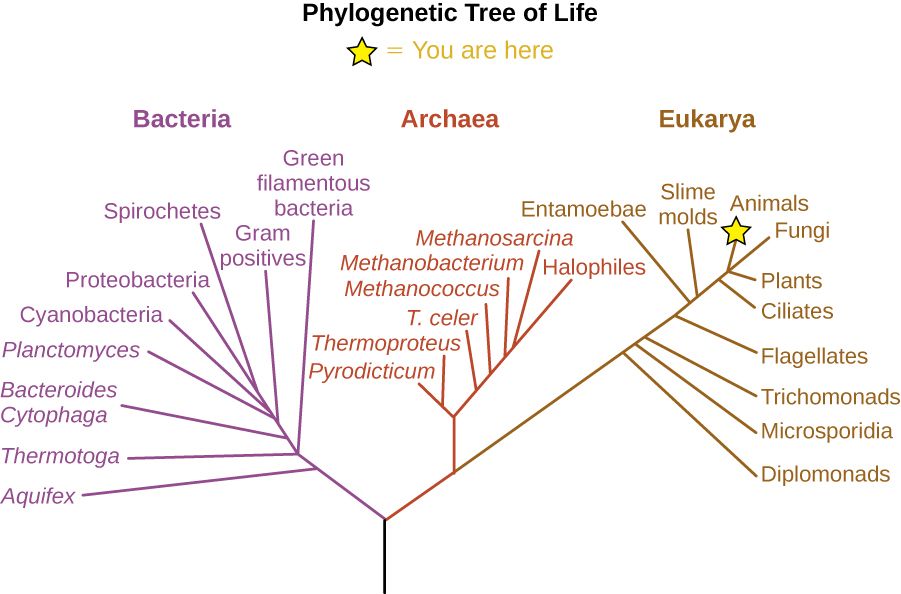
Every living organism belongs to one of three great domains, a scheme worked out by Carl Woese from differences in ribosomal RNA. Two domains, Bacteria and Archaea, are prokaryotes. The third, Eukarya, holds everything with a nucleus — protozoa, fungi, plants, animals, and you. Notice where the microbes land: bacteria are their own domain, archaea are a second, and the microbial eukaryotes (fungi and protozoa) sit alongside us in the third. Viruses, being acellular, are not placed on this tree of life at all.
Binomial names, and how to read them
Every organism gets a two-part Latin name — binomial nomenclature, a system from Carl Linnaeus. The first word is the genus (capitalized), the second is the species (lowercase), and the whole name is italicized: Staphylococcus aureus, Escherichia coli, Clostridioides difficile. After the full name is written once, it is abbreviated to the genus initial: S. aureus, E. coli, C. difficile (or the familiar "C. diff"). Getting this right matters at the bedside, because a chart, a culture result, and a handoff report all assume you can read these names fluently.
| Domain | Cell type | Members | Human disease? |
|---|---|---|---|
| Bacteria | Prokaryote | True bacteria | Yes — most bacterial pathogens |
| Archaea | Prokaryote | Extremophiles & others | No known pathogens |
| Eukarya | Eukaryote | Protozoa, fungi, plants, animals | Yes — fungi, protozoa, helminths |
Decode a few real microbe names below.
- All life falls into three domains: Bacteria, Archaea (both prokaryotic), and Eukarya.
- Viruses are acellular and are not on the tree of life.
- Binomial names are Genus species, italicized, abbreviated to G. species after first use.
The chapter in one breath
- Microbes are organisms too small to see: bacteria, archaea, fungi, protozoa, helminths, and (acellular) viruses.
- The prokaryote/eukaryote divide underlies selective toxicity — why antimicrobials can cure without harming the patient — and antibiotics do nothing to viruses.
- The microbiome of normal flora is mostly beneficial; opportunistic pathogens are normal flora that harm when displaced or unopposed.
- Colonization ≠ infection ≠ disease; a pathogen causes disease and virulence is how much harm it does.
- HAIs are common and preventable, and the nurse's hand hygiene is the most powerful infection-control tool there is.
- Germ theory (Semmelweis, Pasteur, Koch) grounds all infection control; Koch's postulates prove a microbe causes a disease.
- Life sorts into three domains; microbes are named with italic binomial names abbreviated after first use.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Acellular
- Not composed of cells; describes viruses, viroids, and prions.
- Archaea
- A domain of prokaryotes distinct from bacteria; none are known to cause human disease.
- Bacteria
- A domain of single-celled prokaryotes; the source of most bacterial infections and much of our normal flora.
- Binomial nomenclature
- The two-part naming system (italic Genus species) used for every organism.
- Colonization
- The presence and multiplication of a microbe on a body surface without harm or symptoms.
- Domain
- The highest level of classification: Bacteria, Archaea, or Eukarya.
- Disease
- An infection that produces recognizable signs and symptoms and impairs function.
- Eukaryote
- A cell (or organism) whose DNA is enclosed in a membrane-bound nucleus; includes fungi and protozoa.
- Germ theory of disease
- The principle that specific microorganisms cause specific diseases.
- Healthcare-associated infection (HAI)
- An infection a patient acquires while receiving care, e.g., CAUTI, CLABSI, or surgical-site infection.
- Infection
- Invasion of body tissues by a microbe and the host's response to it.
- Koch's postulates
- Four criteria used to establish that a particular microbe causes a particular disease.
- Microbiome
- The community of microbes normally living on and in the body, together with their genes.
- Microorganism (microbe)
- Any living organism too small to see without a microscope.
- Normal flora (microbiota)
- The resident microbes that normally inhabit a healthy body, mostly beneficial.
- Opportunistic pathogen
- A normally harmless microbe that causes disease when displaced, unopposed, or the host is weakened.
- Pathogen
- A microbe capable of causing disease.
- Prokaryote
- A cell (or organism) with no membrane-bound nucleus; bacteria and archaea.
- Selective toxicity
- Harming a microbe while sparing the host by targeting a structure the microbe has and the host lacks.
- Virulence
- The degree of harm (pathogenicity) a microbe is capable of causing.