Innate Immunity
Long before your body knows the name of an invader, it is already fighting back. Innate immunity is the defense you were born with — a set of barriers, cells, and chemical alarms that respond within seconds to minutes, the same way every time, to almost anything that doesn't belong. It doesn't need to have met the microbe before, and it doesn't remember it afterward. From the skin that keeps microbes out, to the neutrophils that swarm a wound, to the fever that makes your patient miserable at 3 a.m., innate immunity is the fast, blunt, always-on first responder of the immune system. This chapter walks through its layers in the order the body meets an invader — and shows you why so much of nursing is really the art of protecting, and reading, these defenses.
By the end of this chapter you can
- Contrast innate and adaptive immunity by speed, specificity, and memory.
- Describe the first-line defenses — skin, mucous membranes, and normal flora — and how each keeps microbes out.
- Identify the major phagocytic cells and walk through the steps of phagocytosis.
- Explain the inflammatory response and relate the four cardinal signs to what is happening in the tissue.
- Describe how pyrogens reset the hypothalamic thermostat to produce a fever, and weigh its benefits and dangers.
- Summarize the outcomes of the complement cascade — opsonization, inflammation, and cytolysis.
- Explain how interferons protect cells from viral infection.
- Connect each of these defenses to concrete nursing assessments at the bedside.
Section 1First line: barriers
Two immune systems, one goal
Your body defends itself with two overlapping systems. Innate immunity is present from birth, responds within seconds to minutes, and treats all invaders with the same non-specific weapons — it has no memory, so the tenth exposure gets the same response as the first. Adaptive immunity (the subject of the next chapter) is slower to start, exquisitely specific to one particular microbe, and it remembers, which is why a second exposure is met faster and harder. Innate immunity buys the days that adaptive immunity needs to gear up. In practice they work as one team, but learning them separately makes each far easier to understand.
The immune system is often taught as three lines of defense, and innate immunity supplies the first two. The first line is the set of physical, chemical, and biological barriers that stop microbes from ever entering — the focus of this section. The second line is the internal response that kicks in once something breaches a barrier: phagocytes, inflammation, fever, and antimicrobial proteins (Sections 2–5). Adaptive immunity is the third line.
Skin and mucous membranes
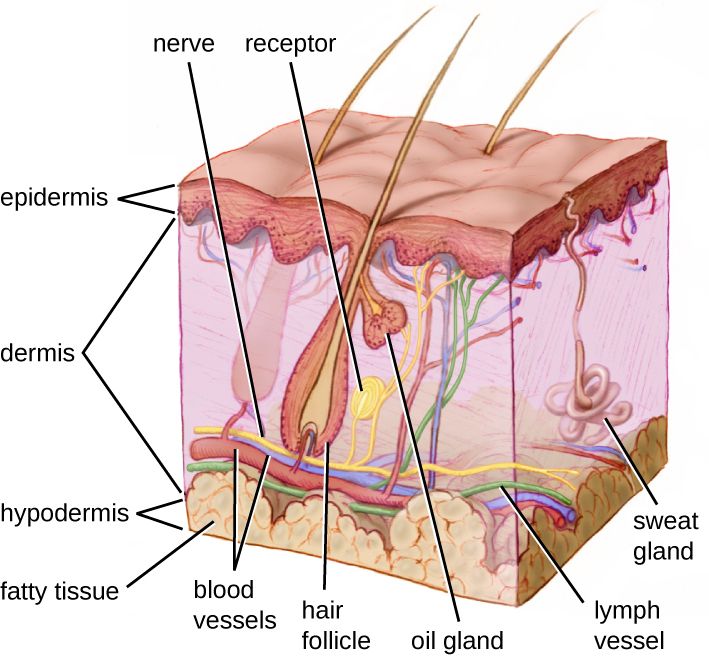
The skin is the single largest organ of the body and the most important physical barrier there is. Its outer layer, the epidermis, is built of tightly packed cells stuffed with keratin and stacked into dead, shingled sheets that are constantly shed — taking any attached microbes with them. Most bacteria simply cannot penetrate intact skin. This is exactly why every break in the skin matters clinically: an IV site, a surgical incision, a pressure injury, or a simple scratch is a door in the wall, and the nurse's job of keeping that door clean and dressed is frontline infection control.
Where the body opens to the outside — the respiratory, digestive, urinary, and reproductive tracts — the barrier is not dry skin but a mucous membrane. These surfaces are kept moist and coated with mucus, a sticky gel that traps microbes before they can reach the cells beneath. In the airway, cells carrying tiny hair-like cilia beat in waves to sweep the trapped debris up and out of the lungs — the so-called mucociliary escalator. Tears, saliva, and the flushing action of urine physically wash microbes away. Understanding this tells you why an intubated patient, whose tube bypasses the mucociliary escalator, is at such high risk for pneumonia, and why we encourage coughing, deep breathing, and adequate hydration.
Chemical and microbial reinforcements
Barriers are not just walls; they are hostile chemical environments. The skin secretes sebum (oily, acidic) and sweat, keeping the surface at a low, unfriendly pH. Lysozyme, an enzyme found in tears, saliva, and mucus, chews apart bacterial cell walls. Stomach acid is brutally low in pH, and the vagina is kept acidic by resident lactobacilli. On top of all this sits the normal flora — the harmless microbes that already occupy the skin and mucosal surfaces. By taking up space and consuming nutrients, they crowd out would-be pathogens, a protection called competitive exclusion. Wipe out that flora — with broad-spectrum antibiotics, for instance — and opportunists like Candida or Clostridioides difficile move into the vacancy.
| First-line defense | Type | How it stops microbes |
|---|---|---|
| Skin (epidermis) | Physical | Keratinized, dry, shedding cell layers block entry |
| Mucous membranes | Physical | Trap microbes in mucus; cilia and flushing remove them |
| Sebum & sweat | Chemical | Low pH and fatty acids inhibit growth |
| Lysozyme | Chemical | Enzyme that digests bacterial cell walls |
| Stomach acid / vaginal acidity | Chemical | Low pH kills or inhibits many microbes |
| Normal flora | Biological | Competitive exclusion — crowd out pathogens |
- Innate immunity is fast, non-specific, and has no memory; adaptive is slow, specific, and remembers.
- The first line is physical, chemical, and microbial barriers that keep invaders out.
- Skin and mucous membranes are the physical walls; lysozyme, acid, and sebum are the chemical defenses.
- Normal flora protect by competitive exclusion; any break in the skin is a breach that nursing care must cover.
Section 2Second line: cells
The white blood cell responders
Once a microbe slips past the barriers, it meets the cellular second line — the white blood cells, or leukocytes. These are made in the bone marrow and patrol the blood and tissues. Two of them do most of the eating, and they are the cells you must know. Neutrophils are the most numerous white cell and the first to arrive at an infection — fast, aggressive, short-lived front-line soldiers. Macrophages (from circulating monocytes that mature after leaving the blood) are the larger, longer-lived cleanup crew; they patrol the tissues, engulf microbes and debris, and help kick off other immune responses. A microbe-eating cell of either kind is called a phagocyte, and the act of eating is phagocytosis (Greek for "cell eating").
These cells don't reach a wound by accident. Chemical signals released at the site of infection — from damaged cells, from the microbes themselves, and from complement (Section 5) — draw phagocytes toward the trouble, a directed migration called chemotaxis. To get out of the bloodstream, circulating white cells first stick to the vessel wall (margination) and then squeeze between the cells of the vessel lining into the tissue, a maneuver called diapedesis (or extravasation).
How a phagocyte recognizes an enemy
How does a phagocyte tell "self" from "invader"? It carries pattern-recognition receptors (PRRs) — sensors that latch onto molecular signatures shared by whole classes of microbes but absent from human cells, called pathogen-associated molecular patterns (PAMPs). A classic PAMP is the lipopolysaccharide (LPS) in the outer membrane of Gram-negative bacteria. Because these patterns are broad, one receptor recognizes many microbes — the hallmark of innate, non-specific immunity. Recognition is made even easier when a microbe is coated with tags called opsonins (antibodies or the complement protein C3b); this coating, opsonization, is like painting a target "eat me" and dramatically speeds engulfment.
Phagocytosis, step by step
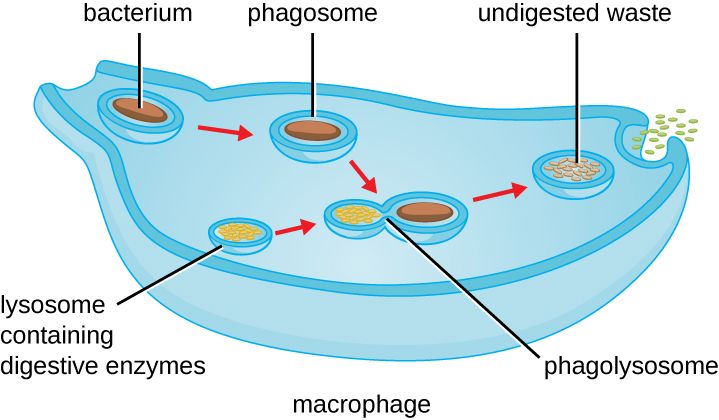
The killing sequence is worth memorizing because it recurs throughout immunology. (1) Chemotaxis — the phagocyte migrates toward the microbe. (2) Adherence — it binds the microbe, helped by opsonins. (3) Ingestion — the cell membrane wraps around the microbe and pinches off an internal bubble called a phagosome. (4) Fusion — the phagosome merges with a lysosome (full of digestive enzymes) to form a phagolysosome. (5) Killing and digestion — enzymes, reactive oxygen (the "respiratory burst"), and low pH destroy the microbe. (6) Exocytosis — the indigestible remains are dumped back out. The spent neutrophils, dead microbes, and tissue fluid left behind are what we recognize as pus.
| Cell | Comes from | Role |
|---|---|---|
| Neutrophil | Bone marrow (granulocyte) | First responder; most abundant WBC; fast, short-lived phagocyte |
| Monocyte → macrophage | Bone marrow; matures in tissue | Large, long-lived phagocyte; cleanup and immune signaling |
| Dendritic cell | Bone marrow | Phagocyte that alerts adaptive immunity |
| Natural killer (NK) cell | Lymphoid line | Kills virus-infected and tumor cells (not classic phagocytosis) |
| Eosinophil | Bone marrow (granulocyte) | Attacks parasites; role in allergy |
- Neutrophils are the first, most numerous phagocytes; macrophages (from monocytes) are the long-lived cleanup phagocytes.
- Phagocytes reach infection by chemotaxis, margination, and diapedesis.
- They recognize microbes by PRRs binding PAMPs, and engulf opsonized microbes fastest.
- Phagocytosis: chemotaxis → adherence → ingestion (phagosome) → fusion (phagolysosome) → digestion → exocytosis; leftover debris is pus.
Section 3Inflammation
The four cardinal signs
Inflammation is the tissue's coordinated reaction to injury or infection, and it produces four classic signs that have been recognized since antiquity: redness, heat, swelling, and pain (in Latin, rubor, calor, tumor, dolor). A fifth is often added: loss of function (functio laesa). Far from being the enemy, these signs are the visible proof that the second line has arrived and is working. When you assess a wound, an IV site, or a joint, you are reading the four cardinal signs directly — they are the everyday language of infection assessment.
What is actually happening in the tissue
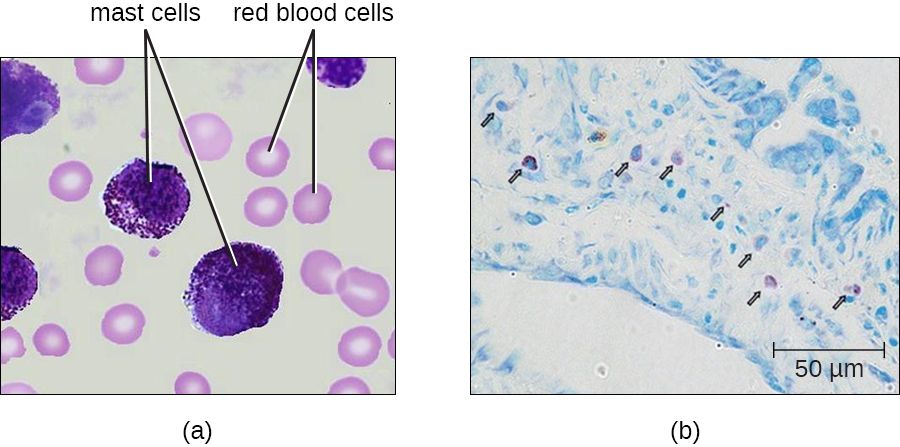
Each sign has a mechanism. When cells are injured or microbes are detected, resident mast cells and damaged tissue release chemical mediators — above all histamine, along with prostaglandins, bradykinin, and cytokines. These do two things. First, they cause vasodilation, widening the blood vessels so more blood floods the area — that extra warm blood is the redness and the heat. Second, they increase vascular permeability, making the vessel walls leaky so fluid, proteins, and cells pour out into the tissue — that accumulation of fluid (edema) is the swelling. The pressure of that swelling on nerve endings, along with mediators like prostaglandins and bradykinin that sensitize those nerves, produces the pain. The whole point is to deliver phagocytes and clotting proteins to the site and to wall the infection off with a mesh of fibrin so it cannot spread.
| Cardinal sign | Latin | What causes it |
|---|---|---|
| Redness | rubor | Vasodilation — more blood flowing in |
| Heat | calor | Warmth of that increased blood flow |
| Swelling | tumor | Fluid leaking from leaky vessels (edema) |
| Pain | dolor | Pressure on nerves plus pain-sensitizing mediators |
| Loss of function | functio laesa | Swelling and pain limit use of the part |
Acute, chronic, and when inflammation turns dangerous
Acute inflammation is short-lived and resolves as the threat is cleared. When a threat can't be cleared, inflammation becomes chronic: macrophages persist and may wall off the invader in a ball of immune cells called a granuloma (classically in tuberculosis). Localized inflammation is protective — but when the same mediators spill into the bloodstream system-wide, the result can be catastrophic. In sepsis, a body-wide inflammatory response to infection causes widespread vasodilation and leaky vessels, dropping the blood pressure and starving organs of oxygen. The very tools that heal a local wound, unleashed everywhere at once, can kill.
- The four cardinal signs are redness, heat, swelling, and pain (plus loss of function).
- Mast cells and injured tissue release histamine and other mediators that cause vasodilation and increased vascular permeability.
- Inflammation delivers phagocytes and walls off infection with fibrin.
- Localized inflammation heals; systemic inflammation (sepsis) is life-threatening.
Section 4Fever
Resetting the thermostat
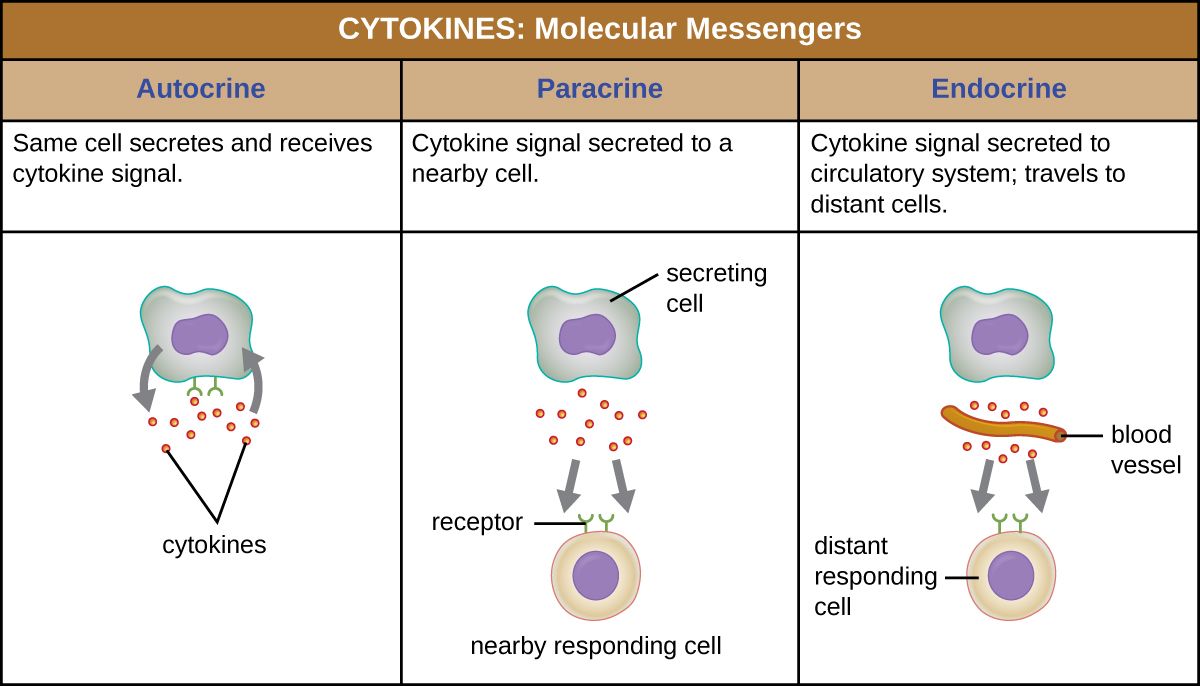
Fever (pyrexia) is an abnormally high core body temperature, and it is not the infection getting the upper hand — it is a deliberate, regulated defense. Your temperature is controlled by a "thermostat" in the hypothalamus, which normally holds the body near 37°C (98.6°F). Fever happens when substances called pyrogens raise the hypothalamic set-point. There are two kinds. Exogenous pyrogens come from outside the body — most famously the LPS of Gram-negative bacteria (also called endotoxin). Endogenous pyrogens are made by the patient's own immune cells: the cytokines interleukin-1 (IL-1), IL-6, and tumor necrosis factor (TNF), released by macrophages when they meet a microbe. These pyrogens drive the production of prostaglandin E₂ in the hypothalamus, which is what actually pushes the set-point up.
Here is the key idea: once the set-point is raised, the body isn't "overheating" — it now believes 39°C is the correct temperature and works to reach it. That is why the onset of a fever brings shivering and a feeling of cold: muscles contract to generate heat and blood vessels constrict to conserve it, all to climb toward the new, higher target.
The three phases of a fever
A fever runs a predictable course, and recognizing the phase changes what you do. In the onset (chill phase), the set-point jumps; the patient feels cold, shivers, and has cool, pale skin as the body drives its temperature up. In the plateau (stadium), the body has reached the new set-point — the patient feels warm, flushed, and dry, and the temperature holds steady at its elevated level. In defervescence (the flush or crisis), pyrogens fall and the set-point drops back to normal; now the body is "too hot," so it sweats and flushes to shed the excess heat. Reading these phases is practical. A shivering patient is climbing toward a set-point the hypothalamus has already chosen, and external warmth will not push the temperature past it — so cover the patient, add blankets, and cut the drafts to stop the shivering, because shivering thermogenesis sharply raises oxygen consumption, metabolic rate, and cardiac workload in exactly the cardiac, respiratory, and septic patients who can least afford it. What you must not do in the chill phase is apply cooling: tepid sponging or a cooling blanket while the patient is still shivering fights the set-point and makes the shivering worse. Cooling measures belong to the plateau and defervescence phases; antipyretics work differently, by lowering the set-point itself.
| Phase | Set-point | What you see | Nursing note |
|---|---|---|---|
| Onset (chill) | Rising | Shivering, cold, pale, "goosebumps" | Temp is climbing; warm the patient and add blankets to stop the shivering — do not cool now |
| Plateau (stadium) | Reached (high) | Warm, flushed, dry skin | Watch hydration; temp is holding high |
| Defervescence (flush) | Falling | Sweating, flushed, feels hot | Replace fluids lost in sweat |
Friend or foe?
A moderate fever helps: higher temperatures slow the growth of many pathogens, speed up the enzymes of the immune response, and enhance the activity of phagocytes and other defenders. That is why routinely erasing every low fever with antipyretics is not always wise — the fever is doing work. But fever also has costs and limits. It raises metabolic demand, the heart rate, and fluid loss; in young children a rapid rise can trigger a febrile seizure; and a very high temperature — roughly above 40–41°C (104–106°F) — begins to denature the body's own proteins and becomes a medical emergency. Antipyretics such as acetaminophen and NSAIDs work by blocking prostaglandin production, lowering the set-point back down.
- Fever is a regulated rise in the hypothalamic set-point, not loss of control.
- Exogenous pyrogens (e.g., LPS) and endogenous pyrogens (cytokines IL-1, IL-6, TNF) act via prostaglandin E₂.
- Phases: onset (chills, climbing) → plateau (steady, high) → defervescence (sweating, falling).
- Moderate fever aids defense; very high fever (>40°C) is dangerous, and some patients can't mount one at all.
Section 5Complement & interferons
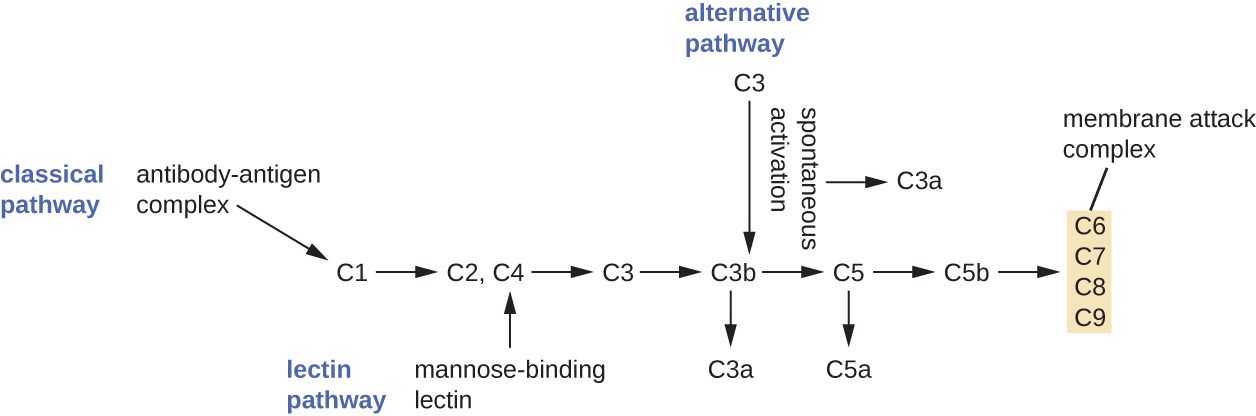
Complement: a cascade of ready-made proteins
Complement is a set of about 30 blood proteins, made mostly by the liver, that circulate in an inactive form and wait. When triggered, they activate one another in sequence — a cascade, where each activated protein cuts and activates the next, amplifying the signal at every step. Three pathways can set it off: the classical pathway (triggered by antibodies bound to a microbe), the alternative pathway (triggered directly by microbial surfaces), and the lectin pathway (triggered by carbohydrates on microbes). All three converge on the central protein, C3, which is split into C3a and C3b — the hinge of the whole system.
From there, complement produces three life-saving outcomes. Opsonization: C3b coats the microbe as an opsonin, tagging it so phagocytes grab it far more easily (linking this section straight back to phagocytosis). Inflammation: the fragments C3a and C5a are anaphylatoxins and chemotactic factors — they trigger mast cells to release histamine and they call phagocytes to the scene. Cytolysis: the terminal proteins assemble into a ring called the membrane attack complex (MAC), which punches a hole in the microbe's membrane so its contents leak out and it bursts. Together, these are sometimes remembered as the three jobs of complement: tag, recruit, and destroy.
| Complement outcome | Key players | What it does |
|---|---|---|
| Opsonization | C3b | Coats the microbe so phagocytes engulf it faster |
| Inflammation | C3a, C5a | Anaphylatoxins — trigger histamine release and attract phagocytes |
| Cytolysis | MAC (C5b–C9) | Forms pores that lyse the microbe |
Interferons: the antiviral alarm
Barriers, phagocytes, and complement are formidable against bacteria — but a virus hides inside a host cell, where those defenses can't reach. For viruses, innate immunity has a different tool: interferons (IFNs), a family of cytokines named because they "interfere" with viral replication. When a cell is infected by a virus, it releases type I interferons (IFN-α and IFN-β). These don't save the dying cell that made them; instead they act as a warning to neighboring cells. A neighbor that receives the interferon signal switches on an antiviral state — it produces enzymes that degrade viral genetic material and shut down protein synthesis if a virus enters — so the virus finds no factory to hijack. A separate interferon, IFN-γ, mainly activates macrophages and bridges to adaptive immunity.
This matters clinically in two directions. The malaise, muscle aches, and fever of a viral illness like influenza are largely the effects of your own interferons working, not the virus directly. And because interferons are natural antivirals and immune modulators, purified versions are used as medications — for certain viral hepatitis infections, some cancers, and multiple sclerosis.
- Complement is a cascade of ~30 proteins; three pathways (classical, alternative, lectin) converge on C3.
- Its three outcomes are opsonization (C3b), inflammation (C3a/C5a), and cytolysis (the MAC).
- Interferons are antiviral cytokines: a virus-infected cell releases type I IFN to put neighboring cells into an antiviral state.
- Interferons cause much of the "sick" feeling of viral illness and are used as drugs.
The chapter in one breath
- Innate immunity is the fast, non-specific, memory-free defense you are born with; it buys time for adaptive immunity.
- The first line keeps microbes out: skin and mucous membranes, chemical defenses (lysozyme, acid, sebum), and normal flora.
- When barriers fail, phagocytes — neutrophils first, then macrophages — find microbes by chemotaxis and destroy them by phagocytosis.
- Inflammation (redness, heat, swelling, pain) comes from histamine-driven vasodilation and leaky vessels; systemic, it becomes sepsis.
- Fever is a raised hypothalamic set-point driven by pyrogens (LPS; cytokines IL-1/IL-6/TNF) via prostaglandin E₂ — helpful in moderation, dangerous when very high.
- Complement tags (opsonization), recruits (inflammation), and destroys (MAC); interferons warn neighboring cells to resist viruses.
- Nearly every innate defense maps onto a bedside assessment — skin integrity, the WBC differential, wound signs, temperature phase, and sepsis recognition.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Antipyretic
- A drug (e.g., acetaminophen, an NSAID) that lowers fever by blocking prostaglandin production and resetting the hypothalamic set-point down.
- Chemotaxis
- The directed movement of a cell, such as a phagocyte, toward a chemical signal released at a site of infection.
- Complement
- A cascade of about 30 blood proteins that, when activated, cause opsonization, inflammation, and cell lysis.
- Cytokine
- A signaling protein released by cells to communicate; includes interleukins, interferons, and TNF.
- Diapedesis
- The squeezing of white blood cells between the cells of a vessel wall to enter infected tissue; also called extravasation.
- Fever (pyrexia)
- A regulated rise in core body temperature caused by pyrogens raising the hypothalamic set-point.
- Inflammation
- The tissue response to injury or infection, marked by redness, heat, swelling, and pain.
- Innate immunity
- The non-specific defenses present from birth that respond rapidly and without memory.
- Interferon (IFN)
- An antiviral cytokine; a virus-infected cell releases type I IFN to put neighboring cells into an antiviral state.
- Lysozyme
- An enzyme in tears, saliva, and mucus that digests bacterial cell walls.
- Macrophage
- A large, long-lived phagocyte derived from a monocyte; cleans up microbes and debris and signals other immune cells.
- Membrane attack complex (MAC)
- The ring of terminal complement proteins (C5b–C9) that forms pores and lyses a target cell.
- Neutrophil
- The most abundant white blood cell and the first phagocyte to arrive at an infection.
- Opsonization
- The coating of a microbe with tags (antibody or C3b) that make phagocytosis faster and easier.
- PAMP
- Pathogen-associated molecular pattern — a molecular signature (e.g., LPS) shared by many microbes and recognized by innate receptors.
- Pattern-recognition receptor (PRR)
- A receptor on innate immune cells that binds PAMPs to detect microbes.
- Phagocytosis
- The engulfment and destruction of a microbe by a phagocyte inside a phagolysosome.
- Pyrogen
- A fever-inducing substance; exogenous (e.g., LPS) or endogenous (cytokines such as IL-1, IL-6, TNF).
- Sepsis
- A dysregulated, body-wide inflammatory response to infection that can cause dangerously low blood pressure and organ failure.
- Vasodilation
- Widening of blood vessels; in inflammation it increases blood flow, causing redness and heat.