Digestive: GI, Liver & Pancreas
The digestive tract is one long tube with a few powerful helper organs beside it. Trouble anywhere along that tube shows up fast. This chapter starts with the reflux and ulcers of the upper GI tract. It moves down through inflammatory bowel disease and blockages. Then it turns to the liver, gallbladder, and pancreas, and the jaundice that warns you something is backing up.
By the end of this chapter you can
- Explain GERD and peptic ulcer disease, and why each one is risky.
- Tell Crohn disease apart from ulcerative colitis.
- Spot a bowel blockage, and tell an upper GI bleed from a lower one.
- Describe cirrhosis and what follows it: portal hypertension, varices, ascites, and encephalopathy.
- Explain gallstones, pancreatitis, and the three types of jaundice.
Section 1Upper GI: GERD & peptic ulcers
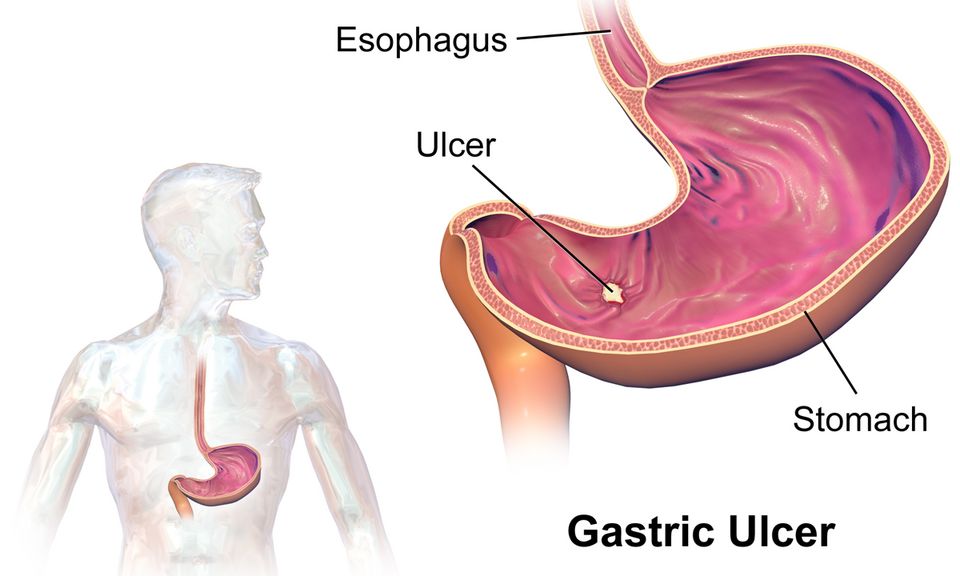
Your stomach makes acid on purpose. Parietal cells in the stomach lining pump out hydrochloric acid (HCl). That acid starts to break down food. It also kills germs you swallow. It is strong enough to burn skin, so the body has to guard itself. It does that in two ways. First, a ring of muscle sits at the bottom of the esophagus. It is called the lower esophageal sphincter (LES), and it stays shut tight. That keeps acid down in the stomach where it belongs. Second, the stomach and duodenum wear a thick coat of mucus and bicarbonate. Think of it as a chemical raincoat. It keeps acid off the soft cells below. Almost every upper GI problem starts when one of these two guards fails.
GERD: when the sphincter leaks
Gastroesophageal reflux disease (GERD) is stomach acid washing backward into the esophagus. It happens when the LES is weak or opens at the wrong time. The esophagus has no mucus raincoat, so the acid stings its lining. That is why the classic symptom is heartburn (pyrosis), a burning behind the breastbone. It is often worse after big meals or when lying down, since lying flat takes gravity out of the fight. Patients may also bring up sour fluid, which is called regurgitation. Some have a cough that will not quit, or a hoarse voice when acid reaches the throat.
A little reflux now and then is normal. GERD is reflux often enough to cause symptoms or damage. The long-term worry is what repeated acid does to the lining. Over years, the normal flat squamous cells can turn into gut-type columnar cells. That change is called Barrett esophagus. The body is adapting so the lining can survive the acid. But this kind of cell swap is a form of metaplasia, and it raises the risk of esophageal adenocarcinoma, a cancer of the esophagus. That is why long-term GERD is watched, not just medicated.
Peptic ulcer disease: when the raincoat wears through
A peptic ulcer is an open sore. It eats through the protective mucosa and into the wall of the stomach or duodenum. Two causes do most of the damage, and both attack the mucus guard. The first is Helicobacter pylori, a spiral-shaped bacterium. It burrows into the mucus layer and sets off inflammation that weakens it. The second is long-term use of NSAIDs, such as ibuprofen and aspirin. NSAIDs block prostaglandins. Those are the very chemicals that tell the stomach to make protective mucus and bicarbonate. Take away the prostaglandins and you take away the raincoat. Then acid digests the tissue itself. Together, H. pylori and NSAIDs cause the large majority of peptic ulcers.
Gastric vs. duodenal: read the pain
Where the ulcer sits changes when the pain comes, and exams love this point. The trick is to think about where the food goes.
| Feature | Gastric ulcer | Duodenal ulcer |
|---|---|---|
| Location | In the stomach lining | In the first part of the small intestine |
| Pain timing | Often worse with food (usually 30 min after eating) | Often eased by food, then back 2-3 hours later |
| Classic clue | May skip meals, can lose weight | Night pain that food settles; may gain weight |
| Usual cause | More often from NSAIDs | More often from H. pylori |
Here is the logic. With a gastric ulcer, food makes the stomach pour out more acid right on top of the sore. So eating hurts. With a duodenal ulcer, food soaks up acid. It also makes the stomach shut its outlet for a while. So eating soothes the pain until the meal moves through.
When an ulcer turns dangerous
Ulcers matter because they can dig deeper. Two problems are emergencies. Bleeding starts when the ulcer eats into a blood vessel. Watch for hematemesis, which means vomiting blood. It can look like coffee grounds once acid has worked on it. Watch for melena too, which is black, tarry, foul stool. That is blood that has traveled the whole gut. Slow, steady bleeding shows up as iron-deficiency anemia and fatigue. The second problem is perforation. The ulcer bores all the way through the wall and spills acid and gut contents into the belly. Pain comes on hard and fast, and the abdomen turns rigid, a board-like abdomen. That is a sign of peritonitis, and it needs surgery right away.
Take a look at the interactive figure below. It shows how a weak sphincter lets acid climb back into the esophagus.
- GERD is acid washing back past a weak LES. Years of acid can lead to Barrett esophagus and raise the risk of esophageal cancer.
- Peptic ulcers form when the mucus guard fails. The usual causes are H. pylori and NSAIDs, which block protective prostaglandins.
- Gastric ulcer pain is often worse with food. Duodenal ulcer pain is often eased by food and returns hours later.
- The dangerous problems are bleeding (hematemesis, melena, anemia) and perforation (sudden pain, rigid board-like belly, peritonitis).
Section 2Inflammatory bowel disease
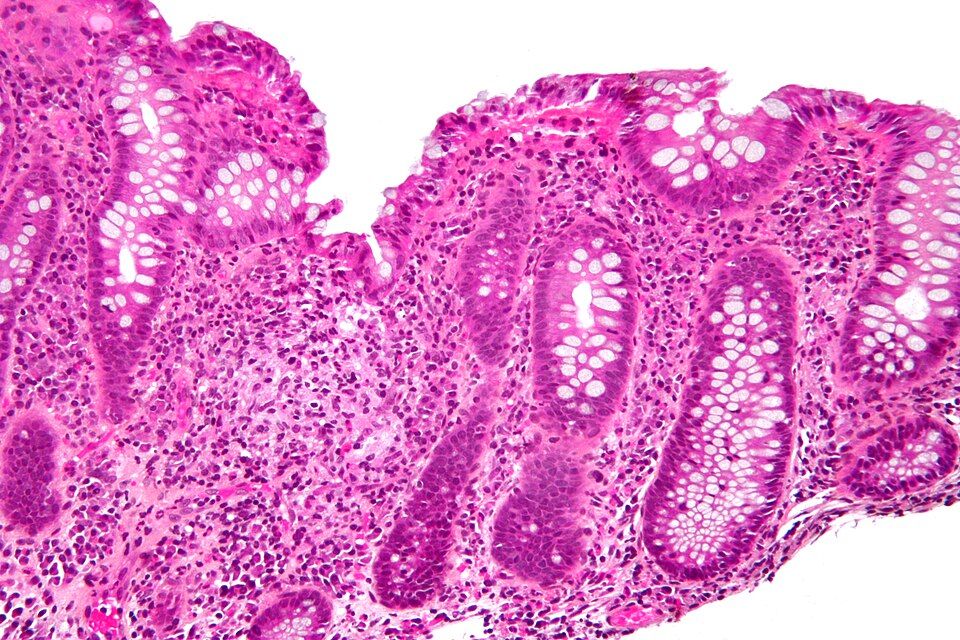
Your gut is a long tube that runs from your mouth to your anus. Its inner lining has a hard job. It has to pull nutrients out of food. At the same time it has to keep trillions of bacteria inside the tube and out of your blood. That lining is the mucosa. It sits on top of your immune system like a screen door. Good things pass through, and invaders are held back. Normally your immune cells and your gut bacteria keep a quiet truce. In inflammatory bowel disease (IBD), that truce breaks down. The immune system starts attacking the bowel wall itself. The result is immune-mediated inflammation, which means the body's own defenses drive it. It flares and settles, flares and settles, for the rest of a person's life.
Two diseases, one family
IBD is an umbrella term for two related conditions. They are Crohn disease and ulcerative colitis (UC), and they share a lot. Both are chronic, which means long-lasting. Both are relapsing, so they cycle between flares of active inflammation and misery, and remission, when things calm down. In both, the immune system overreacts to a normal gut. Genes and triggers in the world around us both play a part. Both can also make the whole body feel sick, not just the belly. Fatigue, weight loss, and a low fever are common, since wide inflammation is a whole-body event. What sets them apart is where they attack and how deep they go.
Crohn disease: patchy and deep
Crohn can strike anywhere from the mouth to the anus. It favors the terminal ileum, the tail end of the small intestine, and the colon. Its signature is skip lesions. Patches of angry, swollen bowel sit right next to healthy tissue, so the pattern looks moth-eaten. The inflammation is also transmural. That means it burrows through all the layers of the bowel wall, not just the surface.
That depth explains Crohn's worst problems. When inflammation tunnels through the wall, it can carve an odd passage between two structures. That passage is a fistula. It may run from bowel to skin, or from bowel to bladder. Long-term transmural damage also scars the tube and narrows it. Those tight spots are strictures, and they can block the bowel. The small intestine does most of the work of soaking up nutrients. So Crohn often causes malabsorption, which means poor nutrient uptake, along with weight loss and vitamin shortfalls. The diarrhea is often not bloody. Patients may have pain in the right lower belly that looks a lot like appendicitis.
Ulcerative colitis: shallow but continuous
UC follows a steadier map. It is limited to the colon only. It almost always starts in the rectum. From there it spreads continuously upward, one unbroken zone of inflammation, with no skip areas. It is also shallow. The damage stays in the mucosa and submucosa, and it spares the deeper muscle layers. Because it does not go transmural, UC rarely causes fistulas or strictures.
But that swollen, ulcerated surface bleeds easily. So the hallmark symptom is bloody diarrhea mixed with mucus. Patients often have crampy pain low in the belly and a constant urge to go, which is called tenesmus. Losing blood and fluid stool many times a day can leave them anemic and dried out. A feared emergency is toxic megacolon. The colon balloons out and can burst. Long-standing UC also raises the risk of colorectal cancer, so these patients need regular colonoscopy checks.
Side by side
| Feature | Crohn disease | Ulcerative colitis |
|---|---|---|
| Location | Mouth to anus (often terminal ileum) | Colon only, starts in rectum |
| Pattern | Skip lesions (patchy) | Continuous |
| Depth | Transmural (all layers) | Mucosa/submucosa only |
| Classic stool | Diarrhea, often not bloody | Bloody diarrhea with mucus |
| Complications | Fistulas, strictures, malabsorption | Toxic megacolon, higher colon cancer risk |
IBD is not IBS
One last split trips people up, because the letters look so much alike. IBD is structural. The inflammation and tissue damage are real, and you can see them on a scope and a biopsy. IBS (irritable bowel syndrome) is functional. The gut hurts and acts up, but the tissue itself looks normal. Explore the interactive figure below to compare the Crohn and UC patterns side by side.
- IBD is long-term, immune-mediated inflammation of the bowel. It relapses in flares and settles into remission, and it splits into Crohn disease and ulcerative colitis.
- Crohn can hit anywhere from mouth to anus, with skip lesions and transmural inflammation. That is why it causes fistulas, strictures, and malabsorption.
- Ulcerative colitis stays in the colon only, spreads continuously from the rectum, and stays mucosal. Its hallmark is bloody diarrhea.
- Deep versus shallow explains the problems. Crohn tunnels through the wall and makes fistulas. UC ulcers the surface, so it bleeds and risks toxic megacolon and cancer.
- Do not mix up IBD (real inflammation with visible damage) and IBS (a functional disorder with normal-looking tissue).
Section 3Bowel obstruction & GI bleeding
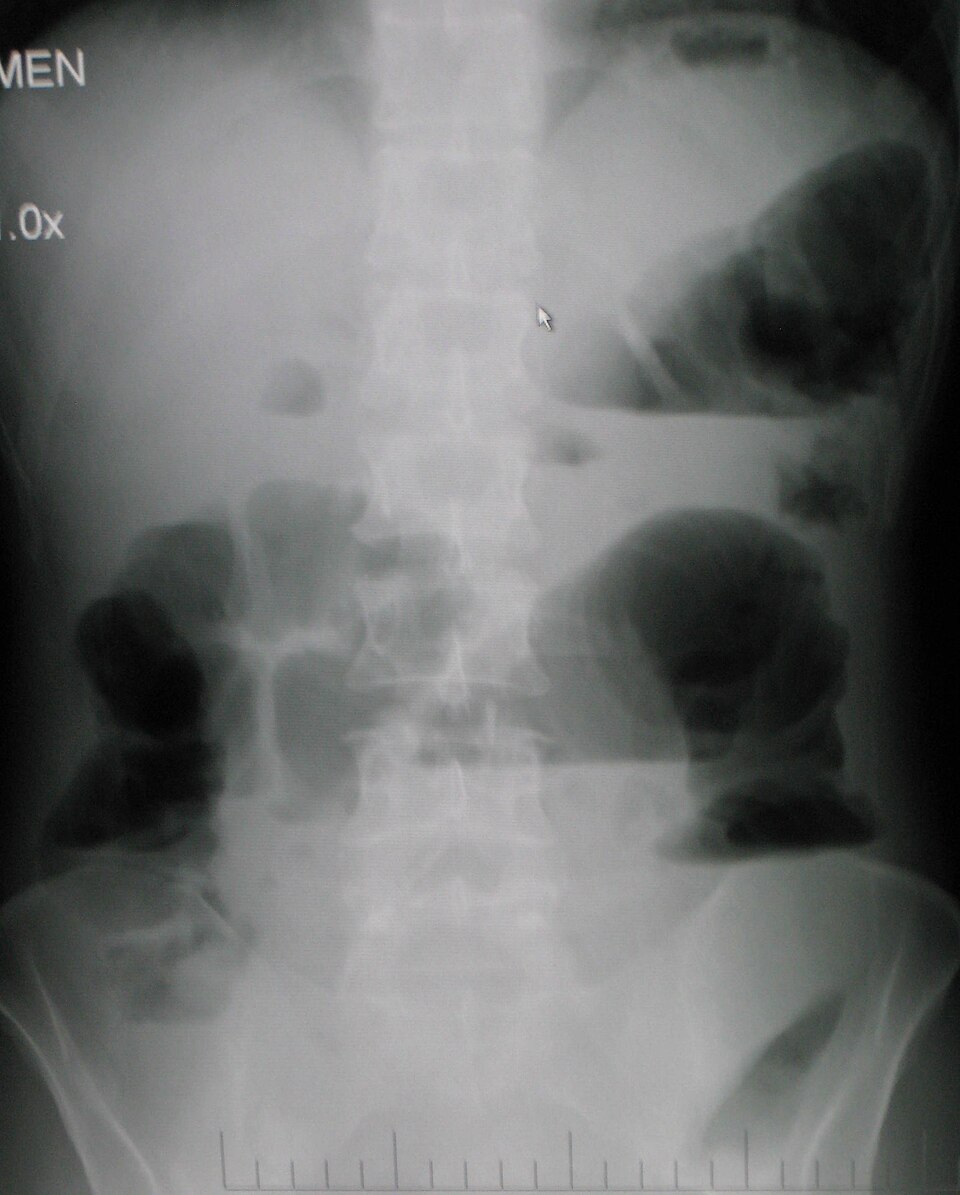
Picture your intestines as a long, muscular hose. There are roughly 20 feet of it, and it never stops working. The gut moves its contents forward with waves of squeezing called peristalsis. Smooth muscle does the squeezing. The enteric nervous system, the gut's own built-in wiring, keeps the rhythm. Food, fluid, gas, and in the end stool all travel one way: down and out. When that forward flow stops, everything piles up behind the block. That is when the trouble begins.
Mechanical obstruction vs paralytic ileus
Two very different things can shut the highway down. In a mechanical obstruction, something plugs the lumen, which is the open space inside the tube. The top cause is adhesions, bands of scar tissue inside the belly, usually from past surgery. Next come a hernia, where a loop of bowel gets trapped as it pokes through the belly wall, and tumors, most often in the colon. The muscle still wants to push. So early on it squeezes harder against a wall it cannot get past.
In a paralytic ileus, nothing is plugging the tube. The muscle simply stops moving. Peristalsis goes quiet. This shows up after belly surgery, when the gut is famously slow for a day or two. It also comes with peritonitis and with electrolyte trouble, especially hypokalemia, which means low potassium. Smooth muscle needs potassium to contract. Opioids do it too, since they slow the gut down. The difference matters a lot. A mechanical block often needs a procedure to open it. An ileus usually needs the cause fixed and the bowel rested.
| Feature | Mechanical obstruction | Paralytic ileus |
|---|---|---|
| Problem | Something plugs the lumen | Gut muscle stops squeezing |
| Common causes | Adhesions, hernia, tumor | After surgery, low potassium, opioids, peritonitis |
| Bowel sounds (early) | High-pitched, overactive, tinkling | Faint to absent from the start |
| Pain pattern | Crampy, wave-like (colicky) | Steady, spread-out ache |
| Usual fix | Often surgery or decompression | Treat the cause, rest the bowel |
The cardinal signs and why they happen
Whatever the cause, obstruction brings a classic set of four. Abdominal distension comes because fluid and swallowed air pile up behind the block, and the bowel balloons outward. Vomiting follows, since the backed-up contents have nowhere to go but up. A low (distal) block often brings foul, feculent vomiting, which smells like stool. A high (proximal) small-bowel block causes earlier, more forceful vomiting. Obstipation is the third sign. It means no stool and no gas passes at all, and it tells you nothing is getting through.
Bowel sounds are the fourth sign, and they tell a story over time. Early in a mechanical obstruction, listen for high-pitched, hyperactive, tinkling sounds as the muscle strains against the block. After hours the muscle tires out, or an ileus sets in. Then those sounds fade to absent. The classic teaching: sounds go high-pitched, then silent.
Why obstruction is an emergency
Trapped bowel does not just hurt. It dies. Fluid pours into the swollen loop, a shift called third-spacing. That drops the volume of blood in circulation. Now the patient risks hypovolemic shock plus metabolic trouble from all the lost fluid and electrolytes. Worse, the swelling can pinch off the bowel's own blood supply. Then the tissue is strangulated, it turns ischemic, which means starved of blood, and it can perforate. Gut contents spill into the belly and set off peritonitis and sepsis, both of which can kill. Fever, a rising heart rate, and sudden severe pain mean a simple block has become a surgical emergency.
GI bleeding: upper vs lower
Bleeding in the digestive tract is sorted by where it starts, because the look of the blood is a built-in clue. An upper GI bleed comes from above the ligament of Treitz. That means the esophagus, stomach, or duodenum. It is often caused by peptic ulcers or esophageal varices, which are swollen veins near the bottom of the esophagus. It shows up as hematemesis, or vomited blood. The blood may look like coffee grounds once stomach acid has partly digested it. It also shows up as melena, which is black, tarry, sticky stool. The stool is black because hemoglobin gets broken down on its long trip through the gut.
A lower GI bleed starts in the jejunum, ileum, or colon. Common causes are diverticulosis, angiodysplasia, hemorrhoids, and colorectal cancer. The blood leaves fast, with no time to be digested. So it shows up as hematochezia: bright red or maroon blood mixed with the stool or coating it.
Why a major bleed is an emergency
A big GI bleed can quietly drain enough blood to cause hypovolemic shock before anyone finds the source. Watch for tachycardia, a fast heart rate, and falling blood pressure. Watch for orthostatic dizziness on standing, pallor, and a dropping hemoglobin and hematocrit. Vital signs often change before the labs do. So trending them and getting IV access in place is the priority.
- Mechanical obstruction (adhesions, hernia, tumor) plugs the bowel. In paralytic ileus the gut muscle simply stops moving.
- The cardinal signs are distension, vomiting, obstipation (no stool or gas), and bowel sounds that go high-pitched then absent.
- Upper GI bleed = hematemesis and melena (black, tarry, digested blood). Lower GI bleed = hematochezia (bright red or maroon).
- A blockage can lead to strangulation, perforation, and peritonitis. A major bleed can cause hypovolemic shock. Both are true emergencies.
- Trend the vital signs, look for tachycardia and low blood pressure, and watch for third-spacing and lost electrolytes.
Section 4The liver: hepatitis & cirrhosis
Think of your liver as the body's busiest chemistry lab. It sits under your right ribs and quietly runs hundreds of jobs at once. Three of those jobs explain most of what goes wrong. First, the liver is the body's detox center. It filters drugs, alcohol, and waste out of the blood. It also turns toxic ammonia, a waste product of protein breakdown, into urea so the kidneys can flush it out. Second, the liver is a factory. It builds most of the body's clotting factors and albumin, the protein that holds fluid inside blood vessels. Third, it handles bilirubin, the yellow-orange pigment left over when old red blood cells are recycled. The liver packs it up so it can leave the body in bile and stool. Hold on to those three jobs. Nearly every sign of liver disease traces back to one of them failing.
Hepatitis: when the liver gets inflamed
Hepatitis simply means the liver is inflamed. Viruses cause most cases. Alcohol and some drugs do the same damage, and acetaminophen in overdose is a big one. The three viral players act in different ways, and that difference drives treatment.
| Feature | Hepatitis A | Hepatitis B & C |
|---|---|---|
| How it spreads | Fecal-oral (food or water with stool in it) | Blood & body fluids (needles, sex, birth) |
| Course | Sudden, then clears on its own; usually full recovery | Often turns chronic; can smolder for years |
| Long-term risk | Rarely leaves lasting damage | Cirrhosis & liver cancer |
| Prevention | Vaccine; clean hands | Hep B vaccine; no Hep C vaccine yet |
During acute hepatitis, patients often feel worn out and sick to the stomach. Many turn jaundiced, with yellow skin and eyes, because the inflamed liver cannot keep up with bilirubin. Alcoholic and drug-induced hepatitis follow the same theme. The toxin harms liver cells, called hepatocytes, faster than they can heal.
Cirrhosis: scarring that does not undo
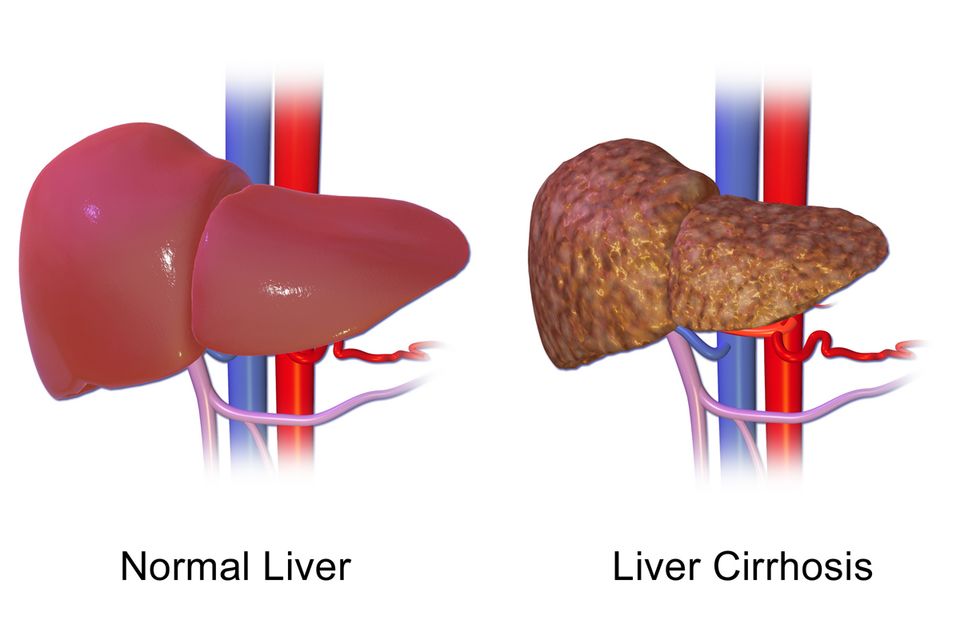
When injury to the liver goes on long enough, the healing itself becomes the problem. The liver stops rebuilding normal tissue. Instead it lays down fibrosis, which is scar tissue. Cirrhosis is the end-stage result. The once-soft organ turns hard, lumpy, and shrunken. Scar tissue cannot do liver work. It also will not let blood flow through the way it should. Those two facts explain the chain of problems that follows.
Portal hypertension and its downstream chaos
Normally, blood from the intestines drains through the portal vein into the liver. Cirrhotic scar tissue squeezes those channels, so pressure backs up. That state is called portal hypertension. The high pressure pushes blood into detours through smaller veins that were never built for the load. Where those veins swell, problems show up:
- Esophageal varices are ballooned, fragile veins at the base of the esophagus. They can burst and bleed fast enough to kill.
- Ascites is fluid pooling in the belly. Two forces drive it. The high portal pressure pushes fluid out of the vessels. And the failing liver makes too little albumin to hold fluid in. Low albumin means low oncotic pressure, the inward pull that keeps water in vessels. So water leaks into the belly.
Why liver failure causes bleeding and jaundice
Remember the factory job. A failing liver stops making enough clotting factors. Patients bruise and bleed easily, and lab tests show a long PT/INR. Pair that with fragile varices, and bleeding becomes a true emergency. Remember the bilirubin job too. As the liver fades, bilirubin builds up in the blood. It stains the skin and the sclera, the white of the eye, yellow. That is the classic jaundice.
Hepatic encephalopathy: the toxin job fails
When the detox center goes down, ammonia from protein digestion is no longer turned into urea. It builds up and crosses into the brain. The result is hepatic encephalopathy: confusion, changes in personality, and a flapping tremor of the hands called asterixis. Early confusion is an important warning sign. The drug lactulose is given to trap ammonia in the gut and pull it out in the stool.
- The liver detoxifies, turning ammonia into urea. It builds clotting factors and albumin, and it processes bilirubin. Remember these jobs and the symptoms make sense.
- Hepatitis is liver inflammation. Hep A spreads fecal-oral and clears up. Hep B and C spread through blood, often turn chronic, and lead to cirrhosis.
- Cirrhosis is scarring that cannot be undone. The scar tissue blocks blood flow and causes portal hypertension, which drives esophageal varices and ascites.
- Liver failure causes bleeding (too few clotting factors, high PT/INR) and jaundice (bilirubin building up).
- Rising ammonia causes hepatic encephalopathy (confusion, asterixis), usually treated with lactulose.
Section 5Gallbladder & pancreas

Your gallbladder and pancreas are two quiet helpers. They sit just under your liver and stomach. The gallbladder is a small green sac that stores bile. Bile is a soap-like fluid the liver makes to break up fat. When you eat a greasy meal, a hormone called cholecystokinin (CCK) tells the gallbladder to squeeze. Bile then runs down the common bile duct into the small intestine. The pancreas pours strong digestive enzymes down its own pancreatic duct. That duct usually joins the bile duct right before both empty into the duodenum. Those enzymes are supposed to stay switched off until they reach the gut. Trouble starts when a stone plugs the plumbing, or when the enzymes switch on too early.
Gallstones and cholecystitis
Bile with too much cholesterol can harden into gallstones. So can bile that sits too long. The medical name is cholelithiasis. Many stones are silent. But a stone can lodge in the neck of the gallbladder or in the cystic duct. Then the gallbladder keeps squeezing against a locked door. It becomes trapped, inflamed, and infected. That is acute cholecystitis. Fatty food is what makes the gallbladder squeeze. So the classic story is right-upper-quadrant (RUQ) pain 30 minutes to a few hours after a fatty meal. The pain often spreads to the right shoulder or shoulder blade, with nausea and vomiting. It can be severe and cramping, which is called biliary colic.
One useful clue is Murphy's sign. Place your hand under the right rib margin. Ask the patient to take a deep breath. The inflamed gallbladder drops onto your fingers. The patient catches their breath and stops from the pain. A positive Murphy's sign points strongly to cholecystitis. For the classic risk profile, think of the 4 F's: female, forty, fertile, and overweight.
When a stone blocks the ducts
A stone that escapes the gallbladder can travel and wedge in deeper. If it blocks the common bile duct, bile backs up. The name for that stone is choledocholithiasis. Bilirubin spills into the blood, so the skin and eyes turn yellow. That is jaundice. The urine darkens, and stools turn clay-pale, because bile pigment no longer reaches the gut. Trapped, still bile invites infection of the whole bile duct system, which is called cholangitis.
Here is the dangerous overlap. The bile duct and the pancreatic duct usually share one final channel. So one stone can dam both. If it blocks the spot where the pancreatic duct drains, enzymes cannot escape. Pressure rises. Now the pancreas is set up to attack itself.
Acute pancreatitis: the organ that digests itself
Acute pancreatitis happens when those digestive enzymes switch on inside the pancreas instead of the intestine. Trypsin turns on too early and wakes up the rest. The gland then starts to digest its own tissue. That self-digestion is called autodigestion. The result is fierce inflammation, swelling, and sometimes bleeding.
The hallmark is severe, constant epigastric pain that bores straight through to the back. Epigastric means the upper middle belly. Patients often feel worse lying flat and better leaning forward. Nausea and vomiting are common, and the belly may be tender and swollen. On labs, lipase rises sharply, usually more than three times the upper normal limit. It also stays up longer than amylase. That makes lipase the more specific marker.
What causes it
Two causes lead by a wide margin: gallstones and alcohol. A handy memory hook is "I GET SMASHED," in which the first culprits are Idiopathic, Gallstones, and Ethanol. Gallstones block the shared duct. Alcohol is directly toxic to pancreatic cells and thickens their secretions.
| Feature | Cholecystitis | Acute pancreatitis |
|---|---|---|
| Core problem | Blocked, inflamed gallbladder | Pancreas digesting itself |
| Pain location | Right upper quadrant, to right shoulder | Epigastric, boring to the back |
| Trigger | Fatty meal | Alcohol or a gallstone |
| Key exam/lab | Positive Murphy's sign | High lipase |
- Gallstones can block bile flow. If the neck or cystic duct is blocked, the gallbladder inflames (cholecystitis), with RUQ pain after fatty meals and a positive Murphy's sign.
- A stone in the common bile duct causes jaundice, dark urine, and pale stools. Because the ducts share a channel, one stone can block the pancreatic duct too.
- Acute pancreatitis is autodigestion. Enzymes switch on early and the pancreas attacks itself, causing severe epigastric pain that bores to the back.
- Lipase is the key lab. It is usually more than triple the upper limit, and it is more specific than amylase.
- The top two causes of pancreatitis are gallstones and alcohol.
Section 6Jaundice & bilirubin
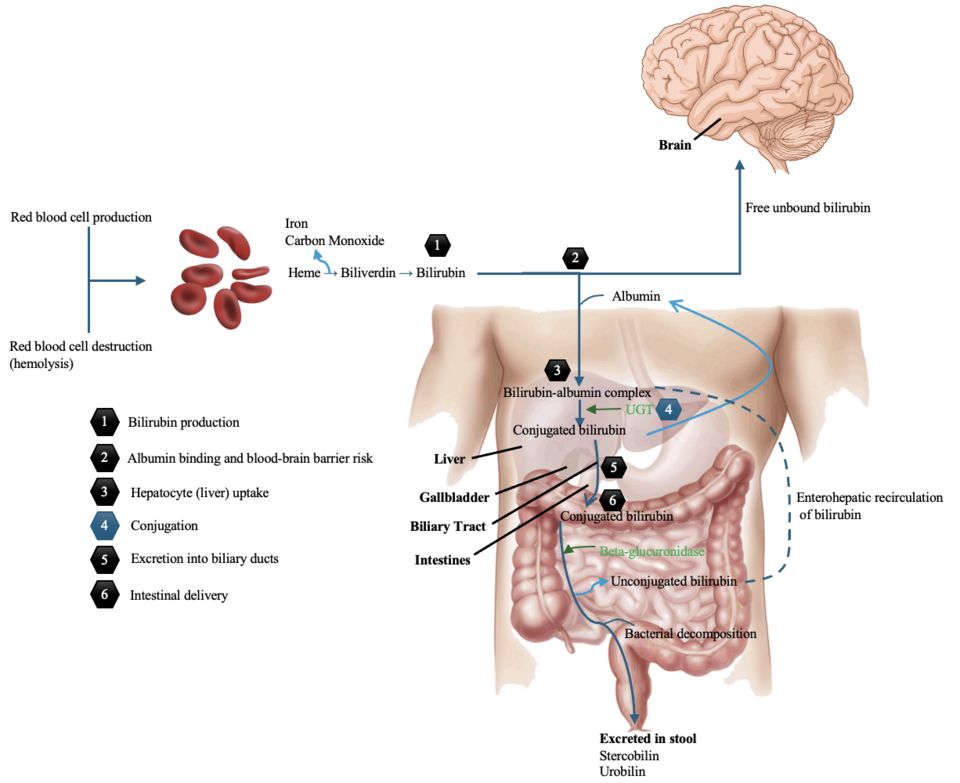
Every day, your body quietly retires about 1% of its red blood cells. Most have simply worn out after roughly 120 days in circulation. When a red cell breaks down, the hemoglobin inside it is taken apart. The heme part becomes a yellow-orange pigment called bilirubin. This first form is unconjugated (indirect) bilirubin, and it has a problem. It is fat-loving and does not dissolve in water. So it cannot simply be flushed out in urine. Instead it rides through the blood stuck to albumin, and it is dropped off at the liver.
How the liver handles bilirubin
The liver is the cleanup station. Liver cells, or hepatocytes, take in unconjugated bilirubin. They attach sugar molecules to it using an enzyme called UDP-glucuronyl transferase. This step is conjugation. It turns the pigment into conjugated (direct) bilirubin, which now dissolves in water. The liver sends conjugated bilirubin into bile. Bile drains through the bile ducts into the small intestine. There, gut bacteria change it into urobilinogen and then stercobilin. Stercobilin is the pigment that gives stool its normal brown color. A small amount is taken back up and leaves in urine as urobilin, which gives urine its yellow tint.
Jaundice, also called icterus, is the yellowing of skin, mucous membranes, and the sclera of the eyes. It appears when serum bilirubin rises above roughly 2 to 3 mg/dL. Bilirubin loves fatty tissue and tissue rich in elastin. That is why the sclera and skin show it first. Jaundice is never a disease by itself. It is a signal that one of the steps above has broken down. To find the break, jaundice is sorted by where in the pathway the problem sits.
The three types of jaundice
Prehepatic (hemolytic) jaundice starts before the liver. Red cells are destroyed faster than the liver can keep up. Causes include hemolytic anemias, sickle cell crisis, and transfusion reactions. The liver is healthy but swamped. So unconjugated bilirubin piles up in the blood.
Hepatic (intrahepatic) jaundice comes from the liver itself being sick. In hepatitis, cirrhosis, or drug injury, damaged hepatocytes cannot conjugate and clear bilirubin well. Both unconjugated and conjugated forms often rise.
Posthepatic (obstructive) jaundice starts after the liver, when bile cannot drain. A gallstone in the common bile duct can block the flow, and so can a tumor in the head of the pancreas. Conjugated bilirubin already dissolves in water, so it backs up and spills into the blood.
| Feature | Prehepatic (hemolytic) | Posthepatic (obstructive) |
|---|---|---|
| Problem | Too many red cells breaking down | Bile cannot drain |
| Main bilirubin type | Unconjugated (indirect) | Conjugated (direct) |
| Urine color | Usually normal | Dark (tea-colored) |
| Stool color | Normal or dark | Pale/clay-colored |
| Itching (pruritus) | Not common | Common |
Why urine darkens and stool turns pale
This clue is one of the most useful of all, and it makes sense once you follow the plumbing. In obstruction, conjugated bilirubin cannot reach the intestine. No stercobilin is made, so stool loses its brown pigment and turns pale or clay-colored. Meanwhile the water-soluble conjugated bilirubin backs up into the blood. The kidneys can filter this water-soluble form. So it shows up in urine, turning it dark, tea-colored. Bile salts also build up under the skin, which often causes intense pruritus, or itching.
Newborn jaundice in one line
Physiologic jaundice of the newborn is common and usually harmless. A baby's young liver has not yet made enough UDP-glucuronyl transferase to conjugate bilirubin quickly. So unconjugated bilirubin rises for a few days. It is often treated with phototherapy, a special light that breaks the pigment down.
An interactive figure below lets you explore how rising bilirubin turns tissues yellow.
- Bilirubin is a pigment from broken-down red cells. The liver conjugates it, which makes it dissolve in water, and sends it out in bile.
- Jaundice shows up when serum bilirubin passes about 2 to 3 mg/dL. It is sorted as prehepatic (hemolysis, unconjugated), hepatic (liver disease, both), or posthepatic (blocked bile, conjugated).
- Blocked bile causes dark urine, since water-soluble conjugated bilirubin spills into urine. It also causes pale stool, since no stercobilin reaches the gut. Itching is common.
- Hemolytic jaundice usually leaves urine and stool color normal, because the extra bilirubin is unconjugated and cannot enter urine.
- Newborn physiologic jaundice comes from a young liver enzyme system and is often treated with phototherapy. Severe cases risk kernicterus.
The chapter in one breath
- GERD happens when a weak lower esophageal sphincter lets acid stomach contents wash back up. The acid burns the esophageal lining and causes heartburn and regurgitation. Over time it can drive Barrett esophagus.
- Peptic ulcers are breaks in the stomach or duodenal wall. Most come from H. pylori infection or NSAIDs stripping the protective mucus barrier, so acid digests the tissue itself. Watch for coffee-ground emesis or melena, which signal a bleed.
- Crohn disease causes patchy, full-thickness (transmural) inflammation anywhere from mouth to anus, with skip lesions and fistulas. Ulcerative colitis is continuous, mucosa-only inflammation limited to the colon, with bloody diarrhea.
- A bowel obstruction blocks flow through the intestine. Gas and fluid back up, causing distension, vomiting, and bowel sounds that go high-pitched then absent. Strangulation cuts off the blood supply and threatens ischemic necrosis, meaning tissue death.
- A GI bleed from an upper source shows as black tarry melena or hematemesis. A lower source shows bright red hematochezia. Either one can drop hemoglobin and push the patient toward hypovolemic shock.
- Hepatitis is liver inflammation from viruses (A-E), alcohol, or toxins, and it blocks the liver's jobs. Repeated injury drives scarring into cirrhosis, where fibrosis raises portal hypertension and causes ascites, esophageal varices, and bleeding from lost clotting factors.
- Gallstones form when bile holds too much cholesterol. A stone stuck in the cystic duct triggers cholecystitis, with RUQ pain that worsens after fatty meals. A stone blocking the common duct can back bile into the pancreas.
- Pancreatitis is the pancreas digesting itself with its own switched-on enzymes, usually after gallstones or alcohol. It causes severe epigastric pain that spreads to the back, with sharply raised lipase and amylase.
- Jaundice is yellow skin and sclera from bilirubin building up, and its type points to the problem. Unconjugated comes from too much hemolysis or a young or failing liver. Conjugated comes from blocked bile flow, which also gives dark urine and clay-colored stools.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Ascites
- Protein-rich fluid building up inside the peritoneal cavity, which is the belly. Portal hypertension and low blood albumin usually drive it. The abdomen swells and feels tight.
- Barrett esophagus
- A change in the lower esophageal lining after years of acid reflux. Normal squamous cells turn into gut-type columnar cells, a change called metaplasia. It raises the risk of esophageal cancer.
- Bilirubin
- The yellow pigment made when the body breaks down old red blood cells. When it builds up in the blood it causes jaundice and turns the skin and the whites of the eyes yellow.
- Cholecystitis
- Inflammation of the gallbladder, usually because a gallstone blocks the cystic duct. It causes right-upper-quadrant pain, fever, and often a positive Murphy sign.
- Cirrhosis
- Lasting scarring, or fibrosis, of the liver. Hard nodules replace working tissue, so the liver slowly loses its ability to filter blood, make proteins, and clear toxins.
- Crohn disease
- A long-term inflammatory bowel disease that can inflame any part of the GI tract from mouth to anus in patchy skip lesions. The inflammation goes through the full thickness of the bowel wall, which is called transmural.
- GERD
- Gastroesophageal reflux disease. Stomach acid flows back into the esophagus again and again, because the lower esophageal sphincter is weak or opens too easily. It causes heartburn and regurgitation.
- Hematochezia
- Bright red or maroon blood passing through the rectum. It usually means bleeding low in the GI tract, in the colon, rectum, or anus. A very fast upper GI bleed can look the same.
- Hepatic encephalopathy
- A drop in brain function, from confusion all the way to coma. It happens when a failing liver can no longer clear ammonia and other toxins from the blood, so they reach the brain.
- H. pylori
- Helicobacter pylori, a spiral-shaped bacterium that burrows into the stomach's protective mucus layer. It is the leading cause of peptic ulcers and long-term gastritis.
- Ileus
- A short-term loss of the normal muscle waves, or peristalsis, of the intestine. It often follows belly surgery. Contents stop moving even though nothing is physically blocking them.
- Melena
- Black, tarry, foul-smelling stool. It forms when blood from an upper GI bleed is digested on its way through the gut, which turns the hemoglobin dark.
- Pancreatitis
- Inflammation of the pancreas. Its digestive enzymes switch on too early and begin to digest the organ itself. Gallstones or alcohol usually trigger it, and it causes severe epigastric pain that spreads to the back.
- Peptic ulcer
- An open sore in the lining of the stomach or duodenum, where acid and pepsin have eaten through the protective mucosa. H. pylori or NSAID use causes most of them.
- Portal hypertension
- Blood pressure that is too high in the portal venous system feeding the liver, usually because cirrhosis backs up blood flow. It drives ascites, esophageal varices, and an enlarged spleen.
- Ulcerative colitis
- A long-term inflammatory bowel disease limited to the colon and rectum. It inflames only the innermost lining, the mucosa, in one continuous stretch. It causes bloody diarrhea and urgency.
DrillFlashcards for this unit
These are the Week 13 cards, the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track how well you know the whole deck, open the full flashcards page.