The Endocrine System
The endocrine system is the body’s chemical messaging service. It works more slowly than nerves. But its effects last for hours or even days. When one gland makes too much or too little of a hormone, the ripples show up everywhere. Blood sugar, heart rate, blood pressure, mood, growth, and water balance all shift. This chapter hands you the one idea that unlocks all of it. That idea is feedback. Then we walk each major gland from healthy to broken, mechanism by mechanism.
By the end of this chapter you can
- Trace how the hypothalamus and pituitary give orders to the other glands. Tell a tropic hormone from a direct one.
- Use negative feedback to predict a lab. Then use a stimulating-hormone level to place a problem as primary (the gland) or secondary (the pituitary).
- Contrast the too-much state with the too-little state for the adrenal (Cushing’s and Addison’s), the thyroid, and ADH (SIADH and DI).
- Read the electrolyte shifts that give a disorder away. Watch potassium in Addison’s, and sodium in SIADH and DI.
- Explain why Type 1 and Type 2 diabetes are different diseases. Name the diagnostic numbers. Tell DKA from HHS.
- Spot growth-hormone excess by its timing. Gigantism comes before the growth plates close. Acromegaly comes after.
- Flag the endocrine emergencies: Addisonian crisis, thyroid storm, myxedema coma, DKA, HHS, and severe hyponatremia.
Section 1The chain of command
The normal wiring: how orders travel down
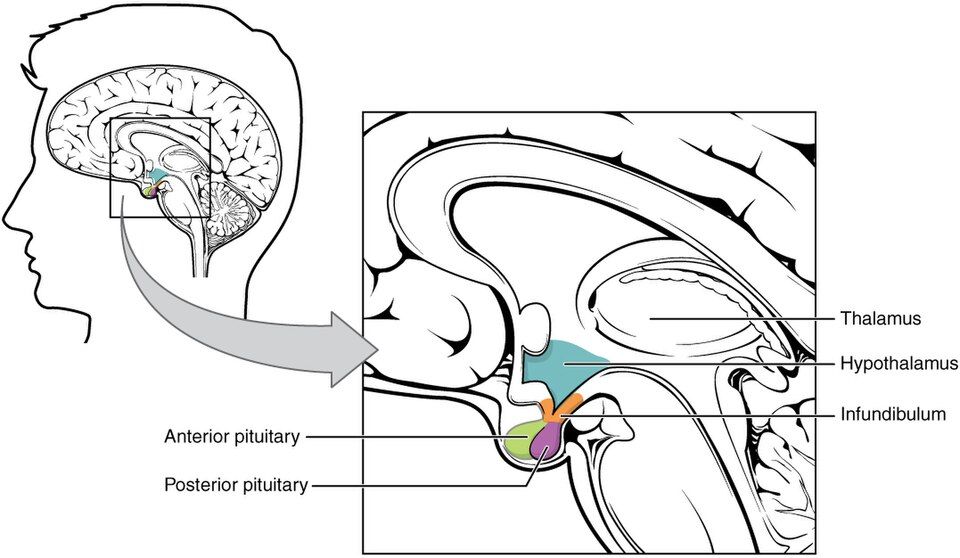
Picture the endocrine system as a company. The hypothalamus is the boss on the top floor. It reads the body's status all day long. It checks temperature, blood pressure, stress, and hunger. It also checks the hormones already moving in the blood. Then it decides what needs to change. Just below it sits its manager, the pituitary gland. The pituitary rests in a bony pocket at the base of the brain. That pocket is the sella turcica. A short stalk joins the two, called the infundibulum. How they talk depends on which half of the pituitary you mean.
The front half gets no nerve signals. It gets chemical notes instead. The hypothalamus makes tiny releasing hormones and inhibiting hormones. These include TRH, CRH, GnRH, GHRH, and the blocker somatostatin. It drips them into a private set of blood vessels inside the stalk. That set is the hypophyseal portal system. Think of a mail tube running between two offices. This small bed of vessels carries the note straight to the anterior pituitary. The note never gets watered down in the rest of the blood first.
The anterior pituitary: a six-product factory
The anterior pituitary is a real factory. It builds six hormones. Several of them are tropic. That word comes from a Greek root meaning to turn toward. A tropic hormone does not act on body tissue. It turns on another gland. The others are direct hormones. They act on the body's own tissues. One way to recall them is FLAT PiG. FLAT is the tropic four: FSH, LH, ACTH, and TSH. PiG is the two direct ones: Prolactin and GH.
| Hormone | Target | Type |
|---|---|---|
| TSH | The thyroid gland | Tropic |
| ACTH | The adrenal cortex | Tropic |
| FSH & LH | The gonads (ovaries and testes) | Tropic |
| GH | The whole body, plus the liver (through IGF-1) | Direct |
| Prolactin | The breast | Direct |
Notice that GH works partly through a helper. It tells the liver to release IGF-1 (insulin-like growth factor-1). IGF-1 then does much of the real growth work in bone and muscle.
The posterior pituitary: a storage locker, not a factory
The back half is different, and it is easy to mix up. The posterior pituitary makes nothing. It is a storage locker. It releases two hormones. One is ADH (antidiuretic hormone, also called vasopressin). ADH tells the kidneys to hold on to water. The other is oxytocin. Oxytocin squeezes the uterus in labor and lets milk flow. Both are built up in the hypothalamus. The parent nerve cells send long axons down the stalk. The hormone rides down the nerve and waits in the tip. It sits there until a signal says release. So the front lobe gets chemical notes through blood vessels. The back lobe gets the finished product down a nerve.
Negative feedback: the body's thermostat
The whole system governs itself with negative feedback. It works just like a home thermostat. Set the dial to 70 degrees. When the room warms past that point, the furnace shuts off. When the room cools, the furnace fires back up. Hormones do the same thing. Walk the thyroid axis and watch. The hypothalamus puts out TRH. TRH tells the pituitary to put out TSH. TSH tells the thyroid to put out T4 (and T3). When T4 in the blood climbs high enough, it loops back. It switches off both TRH and TSH. The furnace turns off. If T4 falls, the pituitary senses the shortage. It cranks TSH up to push the thyroid harder. So here is the most useful line in endocrine care: low thyroid hormone usually means high TSH.
Positive feedback: the rare exception
Now and then the body wants the opposite. It wants a signal that builds on itself until a job is done. That is positive feedback. It is rare for a good reason. It is explosive. Two classic cases stand out. The first is the oxytocin surge in labor. Stretch of the cervix drives more oxytocin. More oxytocin drives stronger contractions. Stronger contractions stretch the cervix even more. The loop runs until the baby is born. The second is the LH surge at mid-cycle. That surge sets off ovulation. Both loops shut off once the goal is met.
The master skill: primary vs secondary vs tertiary
Here is the reasoning trick that cracks most of these cases. When a hormone level is off, ask where the fault lives. Let the tropic hormone point you to it. A primary problem sits in the target gland itself. That means the thyroid, the adrenal, or a gonad. A secondary problem sits in the pituitary. A tertiary problem sits up in the hypothalamus.
| Level | Broken part | Thyroid example (low T4) |
|---|---|---|
| Primary | The target gland | Low T4, high TSH (the pituitary is shouting) |
| Secondary | The pituitary | Low T4, low TSH (no one is shouting) |
| Tertiary | The hypothalamus | Low T4, low TSH, low TRH |
Once the chain of command sinks in, endocrine disease stops being memory work. It turns into detective work. Explore the wiring below.
- The hypothalamus sends releasing and inhibiting hormones through the hypophyseal portal blood vessels to the anterior pituitary. That lobe builds six hormones: TSH, ACTH, FSH, LH, GH, and prolactin.
- The posterior pituitary makes nothing. It only stores and releases ADH and oxytocin. The hypothalamus builds those two and sends them down the nerve.
- Tropic hormones (TSH, ACTH, FSH, LH) act on other glands. Direct hormones (GH, prolactin) act on body tissue.
- Negative feedback works like a thermostat. When the final hormone rises, it shuts off its own signals. So low thyroid hormone usually drives TSH up. Positive feedback is the rare kind that builds on itself, as in labor oxytocin and the LH surge.
- Use the tropic hormone level to place the lesion. Primary is the target gland. Secondary is the pituitary. Tertiary is the hypothalamus.
Section 2Adrenal glands: the cortisol problem
The normal adrenal gland: two organs stacked in one
The adrenal glands sit like small caps on top of each kidney. Each one is really two organs fused together. The outer cortex builds steroid hormones out of cholesterol. The inner medulla makes the fight-or-flight catecholamines. Those are epinephrine and norepinephrine. The cortex has three layers. A handy way to recall them is salt, sugar, sex as you travel inward. The outer zona glomerulosa makes aldosterone. Aldosterone is the mineralocorticoid that holds on to salt and water. The middle zona fasciculata makes cortisol. Cortisol is the glucocorticoid that handles sugar and stress. The inner zona reticularis makes weak androgens, which are the sex steroids.
What cortisol actually does
Cortisol is your built-in stress hormone. It rises and falls on a daily rhythm. It surges whenever you are sick, hurt, or scared. It raises blood glucose by driving gluconeogenesis. That is the liver building brand new glucose. Your brain and muscles then have fuel in a crisis. Cortisol is also strongly anti-inflammatory and immunosuppressive. It calms swelling and quiets the immune system. That is exactly why we bottle it as drugs like prednisone. Cortisol helps maintain blood pressure too. It keeps blood vessels able to answer catecholamines. Control runs through the HPA axis. The pituitary puts out ACTH. ACTH tells the cortex to make cortisol. Rising cortisol then shuts ACTH back off, which is negative feedback. Hold on to that loop. It is the key to telling these diseases apart.
Cushing: too much cortisol
Start with the words. Cushing syndrome is the umbrella term. It covers any cause of too much cortisol. Cushing disease means one thing only. It is a pituitary ACTH-secreting adenoma that drives the adrenals. But the single most common cause overall is neither of those. It is exogenous steroid medication taken for a long time. People take it for asthma, autoimmune disease, or a transplant. Adrenal tumors that make cortisol on their own are a third route.
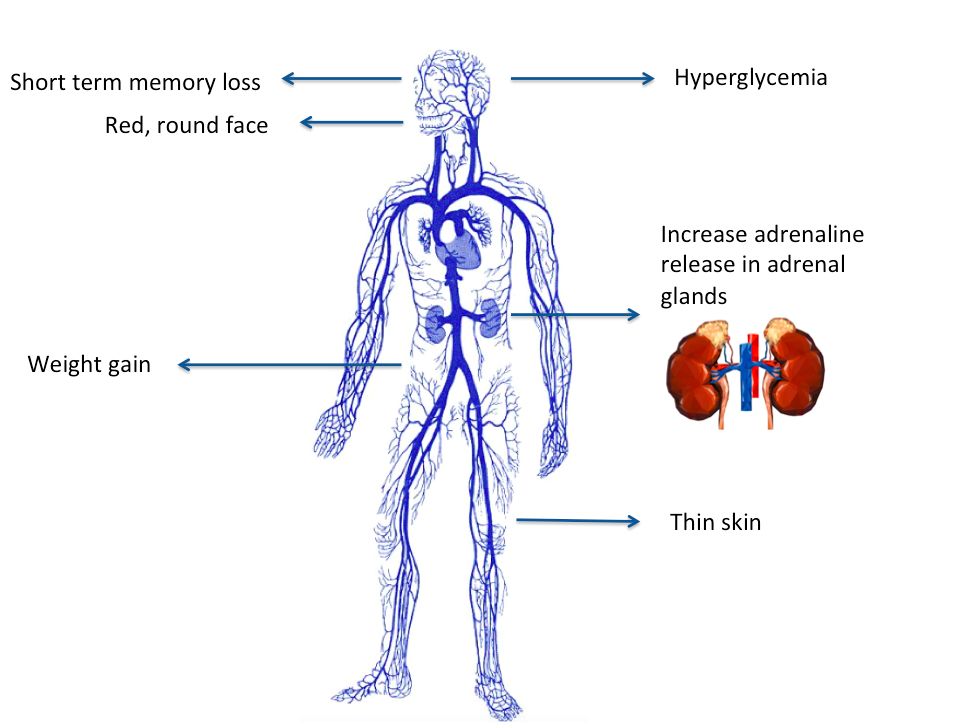
Every classic sign traces back to too much cortisol. Cortisol moves fat to the center of the body. So patients get a round moon face and a buffalo hump between the shoulders. They also get truncal obesity with thin arms and legs. Fat piles up in the middle while cortisol breaks down limb muscle. Cortisol thins the skin and weakens collagen. So you see thin, fragile, easily-bruised skin. You also see stretched purple striae across a belly that outgrew its weakened skin. Nonstop gluconeogenesis causes hyperglycemia, also called steroid-induced diabetes. Cortisol spills over onto mineralocorticoid receptors and holds sodium and water. That causes hypertension and drops the potassium. Aldosterone itself is normal or low in Cushing, so the sodium usually sits normal or only slightly high. It is the cortisol doing the mineralocorticoid job. Bone breakdown leads to osteoporosis. The quieted immune system brings poor wound healing and infection risk. Mood swings, a short temper, and even psychosis round out the picture.
Addison: too little cortisol (primary insufficiency)
Addison disease is primary adrenal insufficiency. The gland itself is destroyed. Most often an autoimmune attack does it. The whole cortex fails, so the patient loses all three outputs. Those are cortisol, aldosterone, and adrenal androgens. Low aldosterone lets sodium and water leak out while potassium builds up. So expect hyponatremia, HYPERkalemia, hypotension, and a strong salt craving. Low cortisol brings hypoglycemia, deep weakness and fatigue, and weight loss. The giveaway finding is bronze hyperpigmentation. With cortisol gone, feedback is lost. The pituitary floods the body with ACTH. ACTH also stirs up melanocytes, the pigment cells in the skin.
Secondary insufficiency: a pituitary problem
Now say the pituitary fails instead. Then ACTH is low. Two clues follow. There is no hyperpigmentation, since no extra ACTH darkens the skin. And aldosterone is largely spared. Aldosterone is driven mainly by the renin-angiotensin system, not by ACTH. So these patients have low cortisol. But their sodium and potassium usually stay closer to normal.
Pheochromocytoma: the medulla's turn
A pheochromocytoma is a tumor of the adrenal medulla. It dumps catecholamines in sudden surges you cannot predict. Recall the 5 P's. Pressure means bursts of high blood pressure, often severe. Pain means a pounding headache. The rest are Palpitations, Perspiration, and Pallor. Between surges the patient may feel completely normal. That is what makes it sneaky.
Putting it together
The fastest way to keep Cushing and Addison straight is a side-by-side look. Explore the interactive figure below, too.
| Feature | Cushing (excess) | Addison (deficiency) |
|---|---|---|
| Cortisol | High | Low |
| Blood glucose | High | Low |
| Blood pressure | High | Low |
| Sodium / Potassium | Na normal to slightly high / K low | Na low / K high |
| Weight & fat | Gain in the middle, moon face | Loss and wasting |
| Skin | Thin, bruises, striae | Bronze hyperpigmentation |
One last feedback check ties it all together. An adrenal tumor making its own cortisol pushes ACTH down, because feedback shuts the pituitary off. A failed adrenal gland lets ACTH climb up. The way ACTH moves tells you where the problem lives.
- The cortex makes salt (aldosterone), sugar (cortisol), and sex steroids (androgens). The medulla makes catecholamines. Cortisol raises glucose, calms inflammation, and props up blood pressure.
- Cushing is too much cortisol only, with aldosterone normal or low. Most often it comes from steroid medication. Look for central obesity, moon face, striae, hyperglycemia, hypertension, hypokalemia, a normal or slightly high sodium, thin skin, and infection risk.
- Addison (primary) destroys the whole cortex. Cortisol AND aldosterone fall, so you get hypotension, hyponatremia, HYPERkalemia, hypoglycemia, salt craving, and bronze skin from high ACTH.
- Secondary insufficiency (pituitary) means low ACTH. There is no hyperpigmentation and aldosterone is spared. Never stop long-term steroids all at once. Taper to avoid an Addisonian crisis.
- Pheochromocytoma is a medulla tumor with catecholamine surges (the 5 P's). Low ACTH points to an adrenal tumor. High ACTH points to a failed adrenal gland.
Section 3Thyroid: the metabolic thermostat
Think of your thyroid as the body's metabolic thermostat. It is a small gland shaped like a butterfly. It sits at the front of your neck. It decides how fast every cell runs its engine. Turn the setting up and your heart beats faster. You burn more fuel and you feel warm. Turn it down and everything slows. Heart, gut, brain, and body heat all ease off. Almost every confusing thyroid symptom makes sense from that one idea. This gland sets the pace of your metabolism.
The normal axis: a three-station relay
Control starts up in the brain. The hypothalamus puts out TRH (thyrotropin-releasing hormone). TRH travels a short way to the anterior pituitary. It tells that lobe to put out TSH (thyroid-stimulating hormone). TSH then rides the blood to the thyroid and says, make hormone. The thyroid answers with mostly T4 (thyroxine), the bulk of its output. It also makes a smaller amount of T3 (triiodothyronine). T3 is the more active form. Much of the T4 is changed into T3 out in the tissues. So think of T4 as the storage and delivery form. T3 is the one that actually revs the cell.
Two more facts anchor the whole system. First, the thyroid cannot build these hormones without iodine. Iodine is a required raw ingredient. That is exactly why iodized salt exists. Second, the thyroid has a side job that has nothing to do with metabolism. Its C-cells release calcitonin. Calcitonin gently lowers blood calcium by tucking it back into bone. It is a minor player in people. Still, it is worth knowing it comes from the thyroid.
Hypothyroidism: the thermostat turned down
When the thyroid makes too little hormone, metabolism idles. Every symptom is that slowdown showing up in a different organ. In countries with enough iodine, the number-one cause is Hashimoto's thyroiditis. That is an autoimmune attack that slowly destroys thyroid tissue. Worldwide, iodine deficiency is still the leading cause. Other causes come after treatment. Those include surgery to remove the thyroid and radioactive iodine ablation. Some drugs do it too, such as lithium and amiodarone.
Trace the mechanism and the signs write themselves. A slow metabolism burns less fuel. So patients feel fatigued. They gain weight even with a normal appetite. They cannot make heat well, which gives cold intolerance. A slowed cardiac pace gives bradycardia. Skin turns over slowly and sweats less, so skin is dry and hair gets coarse and thin. A slow gut means constipation. Reproductive hormones drift, which brings menstrual changes. Periods are often heavier or irregular. Even the nervous system lags. That gives the classic slowed, delayed deep-tendon reflexes. Severe, long-standing disease is called myxedema. That is a puffy, non-pitting swelling from mucin building up in the skin. Its life-threatening extreme is myxedema coma. Look for low body temperature, low blood pressure, and a dulled level of consciousness. That is a true emergency.
Hyperthyroidism: the thermostat cranked up
Too much hormone and metabolism races. The leading cause is Graves' disease. In Graves', antibodies attack the TSH receptor. We call them TSH-receptor antibodies, or TRAb. The stimulating kind are TSI (thyroid-stimulating immunoglobulins). They bind that receptor and switch it on. The gas pedal stays floored no matter what the pituitary wants. Other causes include a toxic multinodular goiter. Those are nodules that make hormone on their own. Thyroiditis can do it too, when an inflamed gland leaks stored hormone.
The signs mirror hypothyroidism in reverse. Burning fuel too fast causes weight loss despite a big appetite. It also causes heat intolerance. The heart speeds up into tachycardia and palpitations, and sometimes atrial fibrillation. The overdriven nervous system brings anxiety, a fine tremor, and brisk hyperreflexia. A fast gut causes diarrhea. Graves' adds two things of its own, both from the antibody attack. One is bulging eyes, or exophthalmos, from tissue swelling behind the eye. The other is pretibial myxedema, a thickened patch of skin over the shins. The emergency here is thyroid storm. Look for a dangerous fever, extreme tachycardia, and agitation or delirium.
Reading the labs: let TSH tell the story
Negative feedback means the TSH and T4 pattern tells you two things. It says whether there is a problem. It also says where the problem lives. In a primary problem the thyroid itself is the culprit. In a secondary problem the pituitary fails to give proper orders. That flips the relationship you expect.
| Pattern | TSH | T4 |
|---|---|---|
| Primary hypothyroid | High | Low |
| Primary hyperthyroid | Low | High |
| Secondary (pituitary) hypothyroid | Low, or normal when it should be high | Low |
Here is the tell for a secondary problem. A low T4 should drive TSH up. So a low T4 paired with a TSH that is low or normal does not fit. The pituitary is not doing its job.
Hypo vs hyper at a glance
| Feature | Hypothyroid | Hyperthyroid |
|---|---|---|
| Heart rate | Slow (bradycardia) | Fast (tachycardia, AFib) |
| Weight | Goes up | Goes down |
| Temperature | Cold intolerance | Heat intolerance |
| GI | Constipation | Diarrhea |
| Mood | Sluggish and low | Anxious and restless |
| Skin | Dry and coarse | Warm and moist |
Keep that one thermostat image in mind and the whole gland makes sense. Explore the interactive figure below to see the axis and its feedback in motion.
- The thyroid sets metabolic speed. Hypothyroid slows everything, with fatigue, weight gain, cold, bradycardia, and constipation. Hyperthyroid speeds everything, with weight loss, heat, tachycardia, anxiety, and diarrhea.
- The axis runs TRH (hypothalamus) → TSH (pituitary) → T4 and active T3 (thyroid), and it needs iodine. Negative feedback makes TSH the key lab.
- Hashimoto's is the top cause of hypothyroidism where iodine is plentiful. Graves', through TSI and TRAb antibodies, is the top cause of hyperthyroidism, and it can add exophthalmos.
- Labs: primary hypothyroid is high TSH with low T4. Primary hyperthyroid is low TSH with high T4. A low T4 with a TSH that is low or wrongly normal points to a secondary (pituitary) cause.
- The emergencies are myxedema coma (hypo) and thyroid storm (hyper). After thyroid surgery, watch for hypocalcemia with the Trousseau and Chvostek signs.
Section 4Diabetes mellitus
Before we talk about what breaks in diabetes, look at how the body normally handles fuel. Picture your bloodstream as a delivery highway. Glucose (blood sugar) is the cargo every cell wants for energy. The traffic controller is your pancreas. More exactly, it is tiny clusters of cells inside it called the islets of Langerhans.
Normal fuel control: the fed state and the fasting state
Inside those islets, beta cells make insulin and alpha cells make glucagon. These two hormones pull in opposite directions. That tug-of-war keeps blood sugar in a safe range. After a meal you are in the fed state. Glucose rises, beta cells release insulin, and insulin acts like a key. It unlocks cells so glucose can move in to be burned or stored. It also tells the liver to bank extra glucose as glycogen. Between meals or overnight you are in the fasting state. Glucose falls, so alpha cells release glucagon. Glucagon tells the liver to break glycogen back down and release glucose. Your brain never runs dry. In short, insulin stores fuel and lets glucose into cells. Glucagon raises blood sugar. Diabetes is what happens when the insulin side of that system fails.
Type 1: an absolute insulin deficiency
In type 1 diabetes, the immune system attacks the beta cells by mistake and destroys them. This is an autoimmune process. We can often find islet autoantibodies in the blood. The beta cells are gone, so there is essentially no insulin at all. We call that an absolute insulin deficiency. It usually shows up in younger, leaner people. The body cannot make insulin, so these patients always require insulin shots to live. Without insulin, glucose cannot get into cells. It piles up in the blood while the cells starve.
Type 2: insulin resistance plus a relative shortfall
In type 2 diabetes, insulin is present. But the cells stop answering it well. That is insulin resistance. The pancreas makes up for it by pumping out extra insulin. Over time it cannot keep up. That leaves a relative insulin deficiency. Type 2 comes on slowly and is often silent for years. It is strongly tied to obesity, metabolic syndrome, and older age. One physical clue is acanthosis nigricans. Those are velvety dark patches in skin folds like the neck and armpits. They signal long-standing high insulin.
Why the three P's happen: osmotic diuresis
Either type can do this. Once blood glucose climbs high enough, the kidneys cannot soak it all back up. Glucose spills into the urine. Sugar in the urine acts like a sponge and drags water out with it. That is osmotic diuresis. It explains the classic three P's. Polyuria means passing large amounts of urine. That causes dehydration, which sets off polydipsia, or intense thirst. Starving cells drive polyphagia, or constant hunger. Weight loss and blurry vision often ride along.
How we diagnose it
Diagnosis rests on standard numbers. Any one of these makes the diagnosis, and we usually confirm it on a repeat test:
- Fasting plasma glucose ≥ 126 mg/dL
- Random glucose ≥ 200 mg/dL along with classic symptoms
- A1c ≥ 6.5 percent (an average of blood sugar over about 3 months)
- 2-hour OGTT ≥ 200 mg/dL (the oral glucose tolerance test)
The long game: chronic complications
Years of high glucose damage blood vessels in two patterns. Microvascular damage hits the small vessels. It causes retinopathy (vision loss), nephropathy (kidney failure), and neuropathy (nerve damage, often numb, tingling feet). Macrovascular damage hits the large vessels. It speeds up coronary artery disease, stroke, and peripheral arterial disease. Put numb feet together with poor blood flow and you get the feared diabetic foot ulcers. Wounds heal slowly and badly.
Gestational diabetes
Pregnancy hormones cause some insulin resistance on their own. When the pancreas cannot keep up, gestational diabetes results. It is often silent, so we screen every pregnant patient. Screening usually happens around 24 to 28 weeks. Extra sugar in the mother's blood crosses to the baby. The baby makes too much insulin and grows too large. That is called macrosomia. After delivery that sugar supply vanishes. But the baby's high insulin keeps going, which causes neonatal hypoglycemia.
The two emergencies: DKA vs HHS
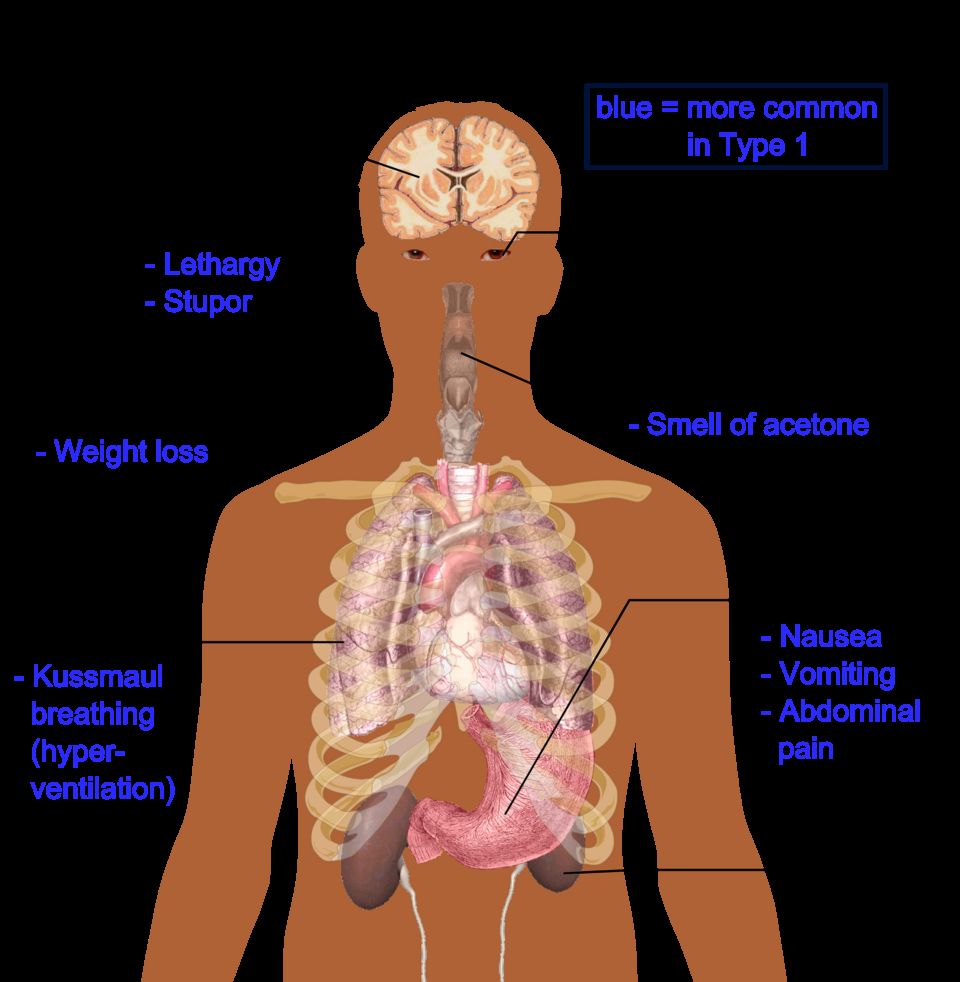
In type 1 there is no insulin at all. The body burns fat for fuel and makes acidic ketones. That tips into diabetic ketoacidosis (DKA). In type 2 there is usually just enough insulin to block ketones. But sugar and dehydration climb to extremes. That is hyperosmolar hyperglycemic state (HHS).
| Feature | DKA | HHS |
|---|---|---|
| Usual type | Type 1 | Type 2 |
| Glucose | Usually > 250 mg/dL | Often > 600 mg/dL |
| Ketones | Present | Little or none |
| Blood pH | Acidotic (low) | Near normal |
| Breathing | Kussmaul (deep and rapid) | Not Kussmaul |
| Onset | Fast (hours) | Slow (days) |
| Core treatment | IV fluids, insulin, careful potassium | IV fluids, insulin, careful potassium |
Both get the same core plan. Rehydrate with IV fluids. Give insulin to lower glucose and shut off ketone production. Replace potassium with care, because insulin drives potassium into cells and levels can crash. Explore the comparison figure below.
- Insulin, from beta cells, lets glucose into cells and stores fuel. Glucagon, from alpha cells, raises blood sugar between meals.
- Type 1 is autoimmune. It is an absolute insulin deficiency that always needs insulin, and it is prone to DKA. Type 2 is insulin resistance plus a relative deficiency, tied to obesity, and it is prone to HHS.
- High glucose spills into urine and drags water with it. That is osmotic diuresis, and it produces the three P's: polyuria, polydipsia, and polyphagia.
- Diagnose with fasting glucose ≥ 126 mg/dL, random ≥ 200 mg/dL with symptoms, A1c ≥ 6.5 percent, or a 2-hour OGTT ≥ 200 mg/dL. Long-term highs cause microvascular and macrovascular damage.
- DKA (type 1) has ketones, acidosis, and Kussmaul breathing. HHS (type 2) has very high glucose with little ketosis. Both need IV fluids, insulin, and careful potassium. Cold and clammy means give sugar fast.
Section 5Growth hormone: timing is everything
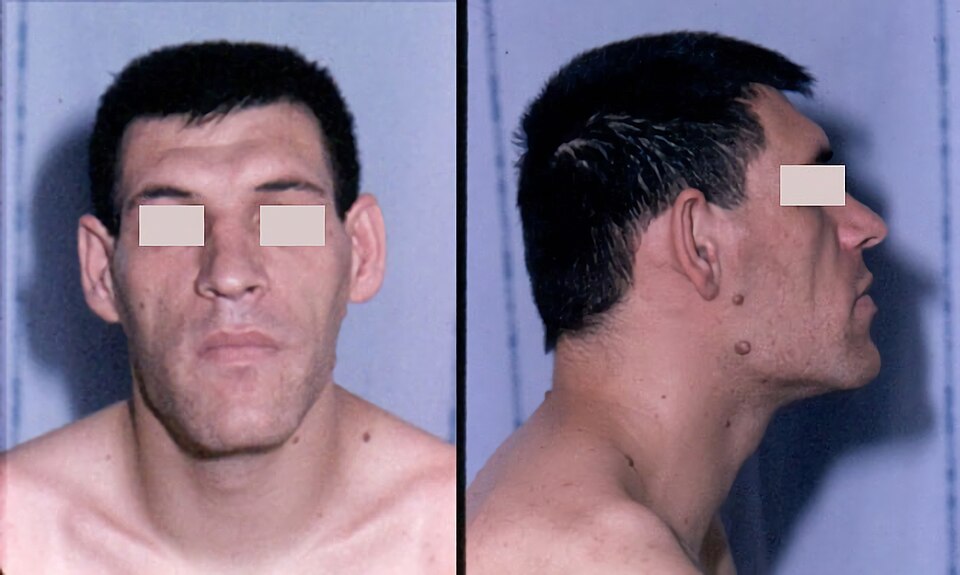
Near the base of your brain sits a gland the size of a pea. It is the anterior pituitary. It releases growth hormone (GH, somatotropin) in bursts, mostly overnight. GH is the body's build order. It tells bone, muscle, and soft tissue to grow. Like most hormones, it runs on a push-pull system. The hypothalamus sends down GHRH (growth hormone-releasing hormone) to press the gas. It sends somatostatin to press the brake. The balance of those two decides how much GH gets out. Sleep, stress, exercise, and low blood sugar all have a say.
How GH actually builds you
GH works two ways at once. It acts directly on tissues. It also acts indirectly. It travels to the liver and tells the liver to make IGF-1 (insulin-like growth factor 1). IGF-1 is the messenger that does much of the real growth work at bone and muscle. That is why we lean on it for testing later. Together they lengthen and thicken bone at the growth zones. They add muscle. They support organs and connective tissue. GH also nudges metabolism. It pushes the body to burn fat. And it tends to raise blood glucose by working against insulin. Hold on to that last fact. It explains a lot of what goes wrong when there is too much GH.
When there is too little GH
In a child, too little GH means the skeleton grows slowly but proportionally. You see a smaller child who is still nicely in proportion, head to limbs to trunk. That is proportional short stature. It differs from conditions where the limbs and trunk do not match. In an adult, growth is already done. So GH deficiency shows up more quietly. Look for fatigue, less muscle and strength, more fat around the middle, and low vitality. These are changes in body composition rather than height.
Too much GH: why timing decides everything
Here is the single most important idea. It is all about the epiphyseal (growth) plates. Those are the cartilage zones at the ends of long bones. New bone is laid down there to make you taller. While those plates are open, bone can still get longer. That covers childhood and adolescence. Once they fuse after puberty, that door closes for good.
So extra GH lands very differently depending on when it strikes. Before the plates close, extra GH lets the whole skeleton keep lengthening. The child grows abnormally tall all over. That is gigantism. After the plates fuse, bone can no longer get longer. The growth signal has nowhere to go but outward. Bone and soft tissue thicken instead. That is acromegaly.
Acromegaly, sign by sign, and why
Acromegaly builds outward. So the clues are about things getting bigger and coarser over years. It is often so slow the patient does not notice. Bone and soft tissue in the hands and feet expand. Patients report a rising ring and shoe size. The face coarsens. The brow and jaw thicken, which gives a jutting jaw called prognathism. The teeth may spread apart as the jaw enlarges. The tongue enlarges (macroglossia) and the voice may deepen. Inside the body, organs enlarge too, which is organomegaly. Soft-tissue swelling in the wrist squeezes the median nerve. That gives carpal tunnel syndrome, with numbness and tingling in the hand. GH works against insulin, so many patients develop glucose intolerance or frank diabetes. Overactive sweat glands cause heavy sweating, or hyperhidrosis.
The usual culprit, and its neighbors
Both conditions almost always come from a GH-secreting pituitary adenoma. That is a benign tumor of the anterior pituitary. The tumor sits in a tight bony pocket near important structures. So as it grows it can press on them. We call those mass effects. One is headache from local pressure. The classic one is bitemporal hemianopsia. The patient loses the outer (temporal) half of each visual field. It happens when the tumor presses upward on the optic chiasm. That is where the nasal retinal fibers cross.
| Feature | Gigantism | Acromegaly |
|---|---|---|
| Timing of GH excess | Before the growth plates close (childhood) | After the growth plates fuse (adulthood) |
| Growth plates | Still open | Fused |
| What changes | The whole skeleton gets longer | Bone and tissue get thicker |
| Main result | Abnormally tall height | Bigger hands, feet, and face (thickness) |
| Usual cause | A GH-secreting pituitary adenoma | A GH-secreting pituitary adenoma |
Picture a growth plate opening and closing and it all clicks into place. Explore it below.
- GH comes from the anterior pituitary. GHRH stimulates it and somatostatin blocks it. GH acts partly through liver-made IGF-1, and it tends to raise blood glucose.
- For GH excess, the deciding factor is whether the epiphyseal growth plates are open. Open plates give gigantism, which is tall all over. Fused plates give acromegaly, where bones thicken.
- Acromegaly shows bigger hands and feet, prognathism with spreading teeth, macroglossia, carpal tunnel syndrome, glucose intolerance, and sweating. All of it comes from outward growth.
- The usual cause is a GH-secreting pituitary adenoma. It can also cause headache and bitemporal hemianopsia by pressing on the optic chiasm.
- Diagnose with an elevated IGF-1 plus a GH that fails to drop after an oral glucose load.
Section 6ADH: the body’s water valve
The normal setup: one hormone, one job
Antidiuretic hormone (ADH) is also called vasopressin. It really does have a single mission. It tells the kidneys to hang on to water. To learn its disorders, start with how the body decides when to hold water. Tucked in the hypothalamus are tiny sensors called osmoreceptors. Their whole job is to taste the blood. They do not check for sugar or salt by itself. They check how concentrated the blood is. That is its osmolality. Sweat on a hot day, or forget to drink, and the blood gets saltier and more concentrated. The osmoreceptors feel that and sound the alarm.
Here is a detail worth holding on to. The hypothalamus makes ADH. But it does not release it. It sends the hormone down to the posterior pituitary. That lobe is the storage tank and the release valve. When the osmoreceptors fire, the posterior pituitary squirts stored ADH into the blood. ADH then travels to the kidney and lands on the collecting duct. That is the last stretch of tubing before urine leaves the kidney. There ADH puts little water doorways into the tubule wall. Those doorways are aquaporins. Water slips out of the forming urine and back into the blood. The blood is thinned again. Only a small amount of concentrated urine leaves the body. When you are well hydrated, ADH switches off. The aquaporins pull back. You pass lots of pale, dilute urine. That is the water valve, opening and closing all day.
Now the two disorders. They are near-perfect mirror images. Learn one and you almost get the other for free.
SIADH: too much ADH (the body is soaked)
SIADH stands for syndrome of inappropriate antidiuretic hormone. The key word is inappropriate. ADH is being released when the body does not need it. The valve is jammed open. Common culprits include central nervous system injury. That covers head trauma, stroke, brain surgery, and meningitis. Small-cell lung cancer is another, since the tumor makes its own ADH. Certain medications do it too, such as SSRIs, carbamazepine, and some chemo drugs. So do the stress states of surgery, pain, and nausea. All of those nudge ADH upward.
With ADH stuck on, the kidneys take back too much water. That extra water thins everything in the blood. So the serum sodium falls. We call it a dilutional hyponatremia. Notice this is a water problem, not a salt-loss problem. Total body sodium is about normal. It is just swimming in too much fluid. The retained water spreads through the whole body instead of pooling as obvious swelling. So patients usually look euvolemic. They may gain a little weight, but often have no clear edema. Meanwhile the urine is the opposite of the blood. It is small in volume and highly concentrated, because the kidney is clinging to water.
The danger is neurologic. Sodium keeps the fluid balance around brain cells steady. When sodium drops, water shifts into the neurons and the brain swells. Expect headache, confusion, lethargy. If the drop is severe or fast, expect seizures. The core fix is simple in concept. Use fluid restriction. Take away the extra water and the sodium drifts back up.
Diabetes insipidus: too little ADH (the body cannot hold water)
Diabetes insipidus (DI) is the flip side. Either the brain does not make or release enough ADH. That is central DI, often after head injury, pituitary surgery, or a tumor. Or the kidney simply cannot respond to the ADH it receives. That is nephrogenic DI, from kidney disease or drugs like lithium. Either way, the aquaporins never open. Water pours straight through into the urine.
The picture is dramatic. You see huge volumes of dilute, pale urine, sometimes many liters a day. The patient slides into dehydration. The serum sodium rises, which is hypernatremia. Water is leaving while sodium stays behind and gets concentrated. The body fights back with intense, unrelenting thirst. Central DI is treated by replacing the missing hormone. We use desmopressin (DDAVP), a synthetic ADH.
A quick word on the name
Do not let the word diabetes fool you. DI has nothing to do with blood sugar. The word diabetes just means a large flow of urine. The second word tells you the type. Insipidus means tasteless. The old test was to taste the dilute urine. Mellitus means sweet, from the sugar spilling over in diabetes mellitus. Same big-urine complaint, completely different cause.
SIADH vs DI side by side
| Feature | SIADH (too much ADH) | DI (too little ADH, or no response) |
|---|---|---|
| ADH level / action | High, so the valve is stuck open | Low or useless, so the valve is stuck shut |
| Serum sodium | Low (hyponatremia) | High (hypernatremia) |
| Urine concentration | Concentrated | Dilute |
| Urine volume | Low | Very high |
| Volume status | Euvolemic or fluid-overloaded | Dehydrated (volume depleted) |
| Core treatment | Fluid restriction | Desmopressin (central DI) |
These two live at opposite ends of the same dial. That dial is the ADH water valve. Picture it opening and closing on the kidney tubule, then explore it below.
- ADH is made in the hypothalamus and stored and released by the posterior pituitary. It tells the kidney collecting duct to take water back by adding aquaporins. Osmoreceptors trigger it when blood is too concentrated.
- SIADH means too much ADH. You get water retention, a dilutional euvolemic hyponatremia, low-volume concentrated urine, and neuro symptoms. Treat it with fluid restriction. Remember: Soaked, Sodium low.
- DI means too little ADH (central) or a kidney that cannot respond (nephrogenic). You get large volumes of dilute urine, dehydration, hypernatremia, and intense thirst. Central DI is treated with desmopressin.
- SIADH and DI are exact opposites on sodium, urine, and volume status. Learn one and flip it for the other.
- Diabetes insipidus has nothing to do with blood sugar. Insipidus means tasteless urine, and mellitus means sweet.
The chapter in one breath
- Negative feedback is the master key. A low target hormone drives its pituitary signal up, so low T4 means high TSH. A high target hormone shuts the signal off.
- Cushing's is too much cortisol, with moon face, central obesity, hyperglycemia, thin easily-bruised skin, and hypertension. Addison's is too little, with hypotension, weight loss, hyperkalemia, and bronze hyperpigmentation.
- Thyroid logic is simple. Hypo runs slow, with fatigue, cold, and weight gain. Hyper runs fast, with tachycardia, heat, and weight loss. A goiter can come with either one.
- Type 1 diabetes is an absolute insulin deficiency prone to DKA, which brings ketones, acidosis, and Kussmaul breathing. Type 2 is insulin resistance prone to HHS, which brings extreme hyperglycemia, deep dehydration, and few ketones.
- Growth hormone excess before the growth plates fuse causes gigantism. The same excess after they fuse causes acromegaly.
- ADH extremes mirror each other. Too much is SIADH, with water retention and dilutional hyponatremia. Too little is diabetes insipidus, with massive water loss and hypernatremia.
- Never stop steroids all at once. Taper corticosteroids to prevent an adrenal crisis, and raise the dose during illness or surgery.
- After a thyroidectomy, stay alert. Watch for hypocalcemia from parathyroid injury, with Chvostek and Trousseau signs, tingling, and tetany. Watch the airway too, since neck swelling can block it.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Aldosterone
- A mineralocorticoid hormone from the adrenal cortex. It tells the kidneys to take back sodium and water and to dump potassium, which raises blood volume and blood pressure.
- Aquaporin
- A water-channel protein. Antidiuretic hormone puts it into kidney tubule walls so water can be taken back, which concentrates the urine.
- Catecholamines
- The fight-or-flight hormones epinephrine and norepinephrine, released by the adrenal medulla. They raise heart rate, blood pressure, and blood glucose.
- Cortisol
- The main glucocorticoid from the adrenal cortex. It raises blood glucose, pulls fat and protein out of storage, and calms inflammation as part of the stress response.
- Exophthalmos
- Eyeballs that bulge forward abnormally. It is classic in Graves disease, where immune-driven tissue swelling pushes the eyes out.
- Goiter
- A visibly enlarged thyroid gland. It can happen whether thyroid hormone output is high, low, or normal.
- Hyperpigmentation
- Darkening of the skin. It happens in primary adrenal insufficiency because high ACTH also stirs up the cells that make melanin.
- IGF-1
- Insulin-like growth factor 1. The liver makes most of it in answer to growth hormone, and it carries out most of growth hormone's effects on tissue growth.
- Insulin resistance
- A state in which body cells answer insulin poorly. The pancreas must then put out more insulin to keep blood glucose in range.
- Ketoacidosis
- A dangerous metabolic state, typical of type 1 diabetes. A severe lack of insulin forces fat breakdown into acidic ketones, and those ketones lower blood pH.
- Myxedema
- The severe, advanced form of hypothyroidism. The face and tissues swell without pitting, from mucopolysaccharide buildup. In crisis, body functions slow down profoundly.
- Negative feedback
- A self-correcting loop. A rising hormone level signals its own source to stop releasing more, which keeps the hormone in a steady range.
- Osmotic diuresis
- Heavy urine output that happens when high blood glucose spills into the urine and pulls water along with it. The result is dehydration.
- Primary vs secondary endocrine disorder
- A primary disorder starts with a fault in the hormone-making gland itself. A secondary disorder starts in the pituitary, which sends too little stimulating hormone. A tertiary disorder starts in the hypothalamus above it, and many texts group both of those under secondary.
- Thyroid storm
- A life-threatening surge of thyroid hormone activity. It brings high fever, a racing heart, agitation, and possible cardiovascular collapse.
- Tropic hormone
- A hormone, usually from the pituitary, whose target is another endocrine gland. It stimulates that gland to release its own hormone.
DrillFlashcards for this unit
These are the Week 6 cards. They are the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.
Check yourself
| Feature | Cushing | Addison |
|---|---|---|
| Cortisol | High | Low |
| Blood glucose | High | Low |
| Blood pressure | High | Low |
| Serum sodium | Normal to slightly high | Low |
| Serum potassium | Low | High |
| Weight | Gain in the middle | Loss |
| Feature | Type 1 | Type 2 |
|---|---|---|
| Core defect | Autoimmune beta-cell loss | Insulin resistance |
| Insulin level | Absent | Normal to high early on |
| Typical onset | Young and lean | Adult, often obese |
| Ketosis risk | High (DKA) | Low (HHS instead) |
Growth hormone excess
Gigantism is GH excess before the growth plates close, so the patient grows very tall. Acromegaly is GH excess after they close, so the hands, feet, jaw, and facial features enlarge instead of height.
Posterior pituitary and ADH
SIADH is too much ADH. Water is held back, urine is concentrated, and serum sodium falls. That is a dilutional hyponatremia. DI (diabetes insipidus) is too little ADH, or a kidney that will not respond. You get huge volumes of dilute urine, thirst, and a rising serum sodium.
| Feature | SIADH | DI |
|---|---|---|
| ADH effect | Too much | Too little |
| Urine output | Low and concentrated | High and dilute |
| Serum sodium | Low | High |
| Volume status | Water held back | Dehydration |