Hematology: The Blood
Blood is a liquid organ. It carries oxygen, stops leaks, and defends the body. So when blood goes wrong, the whole body feels it. This chapter shows how blood cells are made. It covers the anemias that starve tissues of oxygen. It covers bleeding and clotting disorders. It covers the rules of blood typing and transfusion. And it covers the cancers of the blood itself.
By the end of this chapter you can
- Describe how blood cells are made (hematopoiesis) and what erythropoietin does.
- Sort the common anemias and match each one to its cause.
- Explain hemostasis and the main bleeding and clotting disorders.
- Use ABO/Rh matching rules and act on a transfusion reaction.
- Tell leukemia, lymphoma, and multiple myeloma apart.
Section 1Blood, marrow & how cells are made
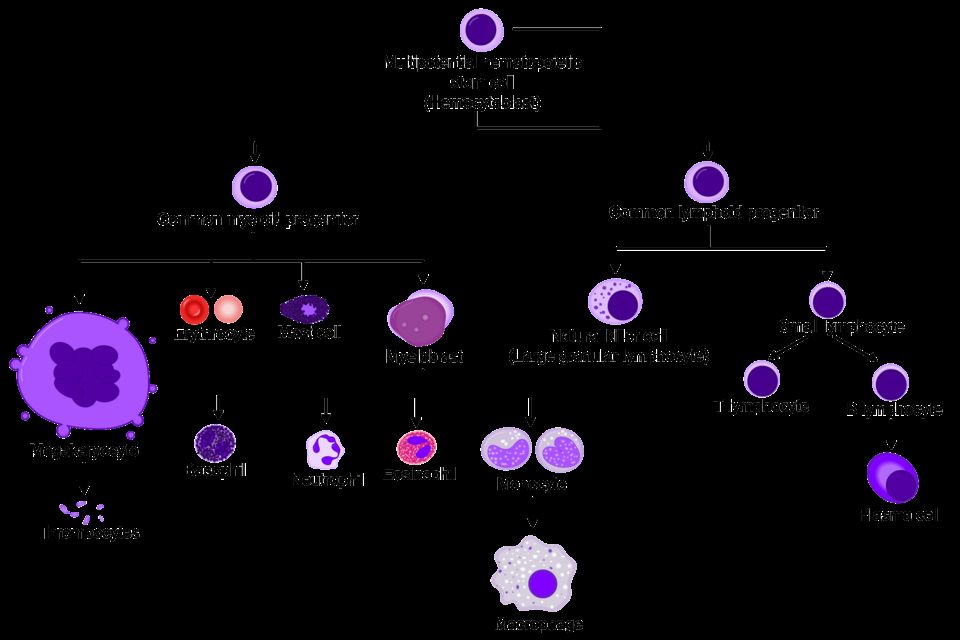
Think of blood as a river that touches every cell you own. It looks like a simple red liquid. It is really a connective tissue, which means living cells floating in fluid. Blood brings oxygen and nutrients to cells. It hauls away carbon dioxide and waste. It moves hormones and immune defenders around. It helps clot a wound. It even steadies your temperature and your pH. So when something goes wrong with blood, the effects show up everywhere at once. Everything depends on it.
What blood is made of
Spin a tube of blood in a centrifuge and it splits into layers. The top ~55% is plasma, a straw-colored fluid that is mostly water. Plasma also carries proteins, electrolytes, glucose, and wastes. The key proteins are albumin, which holds fluid inside vessels, plus clotting factors and antibodies. The bottom ~45% is packed red cells. That percentage is the hematocrit. A thin middle layer, the buffy coat, holds white cells and platelets.
- Red blood cells (erythrocytes) - carry oxygen. There are far more of these than any other blood cell.
- White blood cells (leukocytes) - the immune army. They include neutrophils, lymphocytes, monocytes, eosinophils, and basophils.
- Platelets (thrombocytes) - bits of cells that plug leaks and start clotting.
| Feature | Red cells | Platelets |
|---|---|---|
| Main job | Carry oxygen | Stop bleeding (hemostasis) |
| Has a nucleus? | No (mature RBCs) | No - they are pieces of cells |
| Typical lifespan | About 120 days | About 8 to 10 days |
| Made from | Bone marrow stem cells | Megakaryocytes in marrow |
Hematopoiesis - where blood cells are born
Every blood cell traces back to one ancestor. It is the hematopoietic stem cell (HSC), and it lives in the red bone marrow. In adults that marrow sits mainly in the pelvis, sternum, vertebrae, and the ends of long bones. The whole building process is called hematopoiesis. A stem cell is pluripotent, so it can turn into any blood cell. It also copies itself, so the factory never runs out. As daughter cells grow up, they commit to one of two big lines. The myeloid line makes red cells, platelets, and most white cells. The lymphoid line makes B and T lymphocytes. The marrow replaces worn-out cells all day long. So anything that harms the marrow can drop all the cell lines at once. Chemotherapy, radiation, leukemia crowding it out, and aplastic anemia all do that. Low counts in every line is called pancytopenia.
Erythropoietin - the kidney's oxygen alarm
How does the body know to make more red cells? The kidneys work as oxygen sensors. They notice when too little oxygen reaches their own tissue. That low-oxygen state is hypoxia. It can come from blood loss, high altitude, or lung disease. The kidneys then release a hormone called erythropoietin (EPO). EPO travels to the bone marrow and tells it to ramp up red cell production. This is a beautiful negative-feedback loop. More red cells means more oxygen delivered. That quiets the alarm, so EPO drops again.
This explains a classic clinical picture. In chronic kidney disease, the damaged kidneys stop making enough EPO. The marrow never gets the signal. So the patient gets anemia of chronic kidney disease, even though the marrow itself is healthy. That is why these patients are often treated with man-made EPO. The same loop explains why athletes and people living high in the mountains run higher red cell counts.
Hemoglobin - how red cells carry oxygen
A red cell is basically a bag stuffed with hemoglobin (Hgb). Hemoglobin is the iron-containing protein that actually binds oxygen. Each hemoglobin molecule has four heme groups. Each heme holds one iron atom, and each iron grabs one oxygen molecule. So one hemoglobin carries up to four oxygen molecules. The red cell is a bendy biconcave disc, dented on both sides. That shape gives it lots of surface area. It also lets the cell squeeze through tiny capillaries.
This is why the pieces all have to line up. You need enough iron to build heme. You need enough vitamin B12 and folate to build the cell. And you need a healthy marrow that answers EPO. Take away any one of these and oxygen delivery falls. Low hemoglobin is anemia, and its symptoms flow straight from the mechanism. Tissues are starved of oxygen, so you see fatigue and pallor, which means pale skin. The heart speeds up to move the oxygen that is left. That brings tachycardia, a fast heart rate, plus shortness of breath. The hemoglobin and hematocrit are usually watched together. That pair is the fastest read on how much oxygen a patient's blood can carry.
Explore the loop in the figure below. Watch the spun tube, the kidney, and the marrow move together.
- Blood is a connective tissue. About 55% is plasma (water plus albumin, clotting factors, antibodies). About 45% is cells: red cells, white cells, and platelets.
- Hematopoiesis makes all blood cells from pluripotent stem cells in the red bone marrow. The cells split into myeloid and lymphoid lines. Marrow damage can cause pancytopenia.
- The kidneys sense low oxygen and release erythropoietin to drive red cell production. So chronic kidney disease causes anemia from lost EPO.
- Hemoglobin is the iron-based protein that binds oxygen. Each molecule carries up to four O2. Building it needs iron, B12, and folate.
- Low hemoglobin (anemia) starves tissues of oxygen. That brings fatigue, pallor, and a fast heart rate. Watch Hgb and hematocrit together.
Section 2Anemias
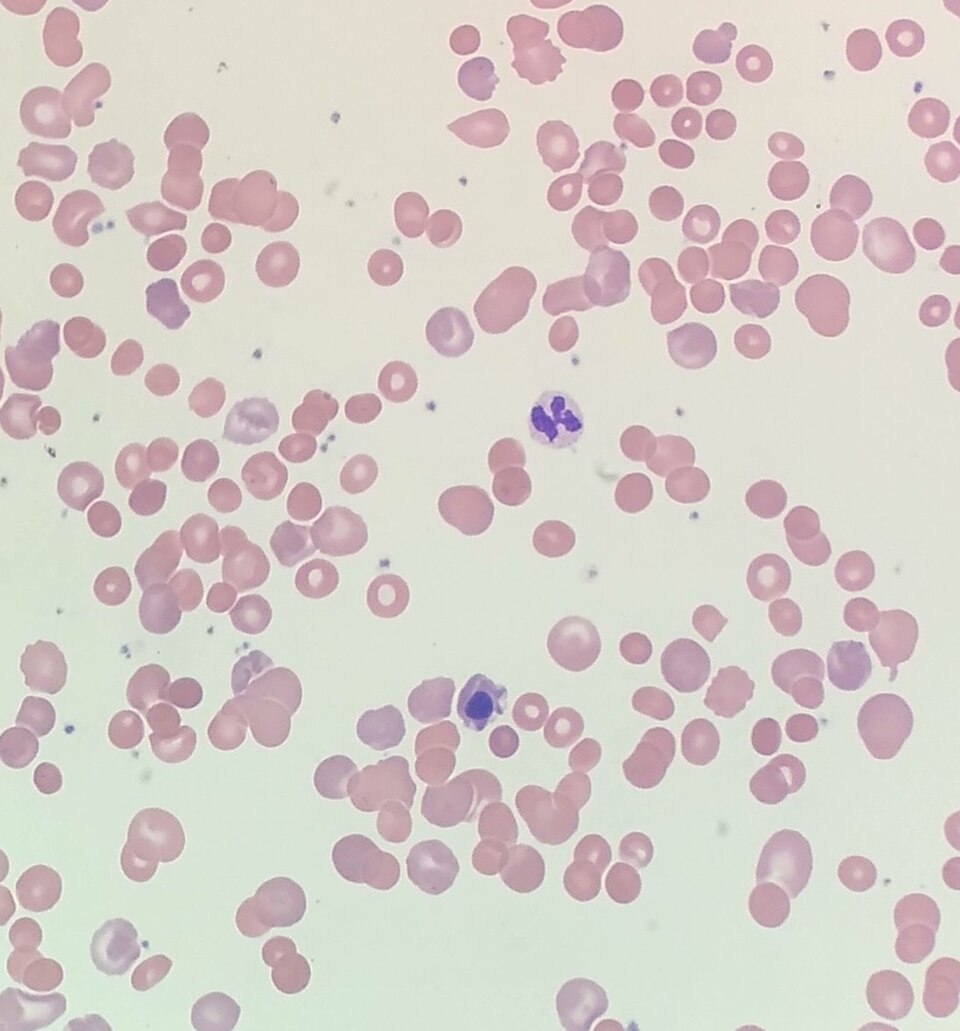
Every one of your cells needs a steady supply of oxygen to make energy. Oxygen does not travel through blood on its own. It rides on hemoglobin, the iron-rich protein packed inside your red blood cells (RBCs). Healthy bone marrow builds new RBCs all the time. It stuffs them with hemoglobin and sends them out to circulate for about 120 days. Anemia means there is not enough working hemoglobin to carry the oxygen your tissues need. Notice the wording. Anemia is not simply "low blood." It is low oxygen-carrying power. The cause may be too few RBCs, too little hemoglobin per cell, or hemoglobin that does not work.
The real problem is oxygen delivery to tissue. So the classic symptoms make sense once you trace the mechanism. Tissues starved of oxygen make less energy, so patients feel fatigue and weakness. Fewer red cells means less color showing through skin and mucous membranes. That shows up as pallor: pale skin, conjunctiva, and nail beds. The heart tries to make up for it by pumping faster to move what little oxygen there is. That causes tachycardia. The blood is also oxygen-poor, so patients breathe faster and feel short of breath, especially with effort. That is dyspnea. Almost every anemia shares these signs. The differences lie in why the hemoglobin is missing.
Iron-deficiency anemia (microcytic)
Iron sits at the core of the heme molecule that binds oxygen. Without enough iron, the marrow makes red cells that are small and pale. Small means microcytic, so the MCV is low. Pale means hypochromic. The cells simply cannot fill up with hemoglobin. This is the most common anemia worldwide. The causes fall into three buckets. Blood loss covers heavy menstrual periods, plus slow GI bleeding from ulcers or colon cancer that quietly drains iron. Increased demand covers pregnancy, infancy, and rapid growth. Poor intake or absorption covers diets low in iron and gut conditions. Lab clues include a low ferritin and a low serum iron. Ferritin is the body's storage form of iron.
B12 and folate deficiency (macrocytic)
Vitamin B12 and folate are both needed to build DNA. When they run short, developing red cells cannot divide properly. They grow large and fragile instead. That gives macrocytic (high MCV) megaloblastic anemia. Folate deficiency comes from a poor diet with few leafy greens, from alcohol use, or from the demands of pregnancy. B12 deficiency has one special cause worth memorizing: pernicious anemia. Absorbing B12 from food takes intrinsic factor, a protein made by the stomach's parietal cells. In pernicious anemia an autoimmune attack destroys those cells. Intrinsic factor disappears, so B12 cannot be absorbed no matter how much is eaten. It must be replaced by injection. One key distinction: B12 also maintains the nervous system. So its deficiency adds neurologic signs like numbness, tingling, and balance problems. Folate deficiency does not.
| Feature | Iron deficiency | B12 / folate deficiency |
|---|---|---|
| Cell size (MCV) | Small (microcytic) | Large (macrocytic) |
| Core problem | Too little hemoglobin | DNA and cell division fail |
| Typical cause | Blood loss, low intake | Poor diet, pernicious anemia |
| Neuro symptoms | No | Yes (B12 only) |
Hemolytic anemias and sickle cell disease
Hemolytic anemias happen when red cells are destroyed faster than the marrow can replace them. Hemolysis means RBC breakdown. Dying cells spill their contents, so you often see jaundice from the bilirubin released. The classic inherited example is sickle cell disease. A single genetic change makes abnormal hemoglobin called HbS. HbS molecules stick together when oxygen levels drop. Dehydration, infection, and cold can set that off too. The soft round RBC then warps into a rigid crescent, or sickle, shape. These stiff cells jam small vessels and block blood flow. That event is a vaso-occlusive crisis: sudden, severe pain as tissue downstream is starved of oxygen. Sickled cells are also fragile and are destroyed early. That drives long-term anemia.
Finally, aplastic anemia is a marrow-failure state. The bone marrow stops making blood cells at all. So RBCs, white cells, and platelets all fall together (pancytopenia). Explore the different anemia types in the figure below.
- Anemia is low working hemoglobin, so less oxygen reaches tissue. The shared signs are fatigue, pallor, fast heart rate, and shortness of breath. They all come from tissue hypoxia and the heart working harder.
- Iron-deficiency anemia is microcytic and the most common kind. A new case in an older adult means rule out GI bleeding.
- B12 and folate deficiencies are macrocytic. Only B12 deficiency causes nerve signs. Pernicious anemia is loss of intrinsic factor, which blocks B12 absorption.
- Sickle cell disease (HbS) sickles when oxygen is low, which causes painful vaso-occlusive crises. Manage with oxygen, fluids, and pain control.
- Aplastic anemia is bone marrow failure, and it produces pancytopenia.
Section 3Bleeding & clotting disorders
Every time you get a paper cut, a well-rehearsed emergency crew goes to work. The bleeding stops within minutes. This process is called hemostasis, which literally means "blood standing still." It runs in steps that overlap. Learn the normal order and you can see exactly what breaks in bleeding and clotting disorders.
Normal hemostasis: how the body plugs a leak
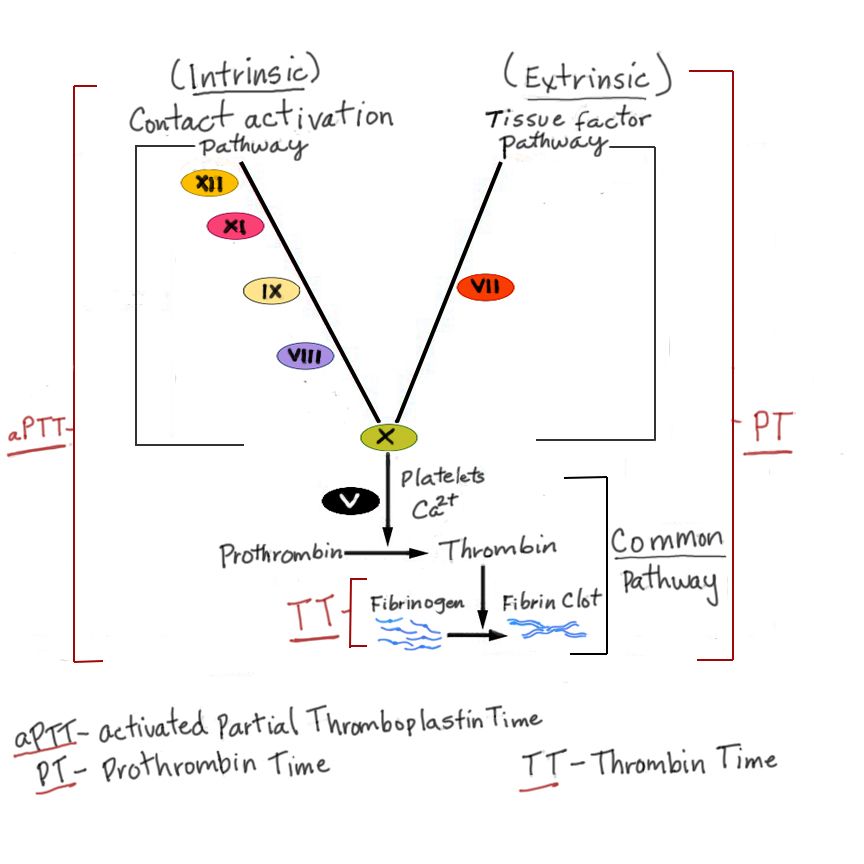
Three things happen fast the moment a blood vessel is injured. First comes vasoconstriction. The vessel clamps down to slow blood flow to the area. Second, the platelet plug forms. Platelets are tiny cell fragments that normally glide past smooth vessel walls. At an injury they touch exposed collagen. Then they stick, switch on, change shape, and clump together. A bridging protein called von Willebrand factor (vWF) helps them hold on. This soft plug is a quick fix. Third comes the coagulation cascade. It is a chain reaction of clotting proteins, called factors, that switch one another on in order. The cascade has an intrinsic and an extrinsic pathway, and the two meet. They turn prothrombin into thrombin. Thrombin then turns fibrinogen into fibrin, tough protein threads. Fibrin weaves through the platelet plug like rebar in concrete and makes the clot stable. Later, once healing is under way, fibrinolysis dissolves the clot.
Thrombocytopenia and ITP: too few platelets
Thrombocytopenia means a low platelet count. That usually means below 150,000/mm3. Serious bleeding risk often starts under 20,000. With too few platelets, the first plug is weak. Patients show petechiae, which are pinpoint red spots. They also show purpura, easy bruising, nosebleeds, and gum bleeding. In immune thrombocytopenic purpura (ITP), the immune system makes antibodies that tag the patient's own platelets. The spleen then destroys them. In children it often follows a viral illness. In adults it tends to be more long-lasting. Treatment targets the immune attack. Options are corticosteroids, IVIG, and sometimes removing the spleen (splenectomy).
Hemophilia and von Willebrand disease: the factor problems
Hemophilia is an inherited shortage of a clotting factor. The platelet plug forms fine, but the fibrin mesh never sets properly. Both common types are X-linked recessive. That is why they classically affect males, whose mothers are carriers. Hemophilia A is a lack of factor VIII. Hemophilia B (Christmas disease) is a lack of factor IX. The two look identical. You see hemarthrosis, which is deep bleeding into joints. You also see muscle bleeds and long bleeding after surgery or trauma. Lab work shows a prolonged aPTT with a normal platelet count. Treatment is to replace the missing factor.
Von Willebrand disease is the most common inherited bleeding disorder. It is usually autosomal, so it affects both sexes equally. vWF is missing or faulty, so platelets cannot stick well. vWF also carries factor VIII, so that factor drops too. The result blends both worlds. You get mucosal, platelet-type bleeding such as heavy menstrual periods and nosebleeds. You also get a mild factor picture.
| Feature | ITP | Hemophilia A/B | von Willebrand |
|---|---|---|---|
| Core defect | Platelets destroyed | Factor VIII or IX missing | vWF missing or faulty |
| Inheritance | Acquired (autoimmune) | X-linked recessive | Usually autosomal |
| Bleeding type | Petechiae, mucosal | Deep joints, muscles | Mucosal, menstrual |
| Key lab | Low platelet count | Prolonged aPTT | Low vWF antigen and activity (ristocetin cofactor assay), sometimes low VIII |
DIC and DVT: when clotting itself becomes the disease
Disseminated intravascular coagulation (DIC) is a dangerous paradox. Sepsis, trauma, childbirth problems, or cancer can trigger it. The cascade fires everywhere at once and throws tiny clots all through the smallest vessels. This consumes platelets and clotting factors faster than the body can replace them. The result is a patient who clots and bleeds at the same time. The microclots damage organs. The used-up supply leaves the patient oozing from IV sites, gums, and incisions. Labs show low platelets, prolonged PT and aPTT, low fibrinogen, and a high D-dimer. DIC is always secondary to something else. So treatment means fixing the underlying cause.
Clotting can also go wrong in a single vessel. A deep vein thrombosis (DVT) is a clot in a deep vein, usually in the leg. Virchow's triad names the three ingredients that promote it. Venous stasis is slow blood flow from not moving. Endothelial injury is damage to the vessel wall. Hypercoagulability is blood that clots too readily. The feared complication is a piece breaking off. It then travels to the lungs as a pulmonary embolism.
You can explore hemostasis, bleeding, and clotting in the interactive figure below.
- Hemostasis runs in order: vasoconstriction, then the platelet plug (which needs vWF), then the coagulation cascade making thrombin and fibrin.
- Platelet or vWF problems cause immediate, superficial bleeding such as petechiae and mucosal ooze. Factor problems cause delayed, deep bleeding into joints and muscles.
- ITP is autoimmune platelet destruction. Hemophilia A (factor VIII) and B (factor IX) are X-linked. Von Willebrand disease is the most common inherited bleeding disorder.
- DIC consumes platelets and factors, so the patient clots AND bleeds at once. The D-dimer is high. DIC is always secondary to another problem.
- A DVT forms through Virchow's triad: stasis, endothelial injury, and easy clotting. It can embolize to the lungs.
Section 4Blood types & transfusion
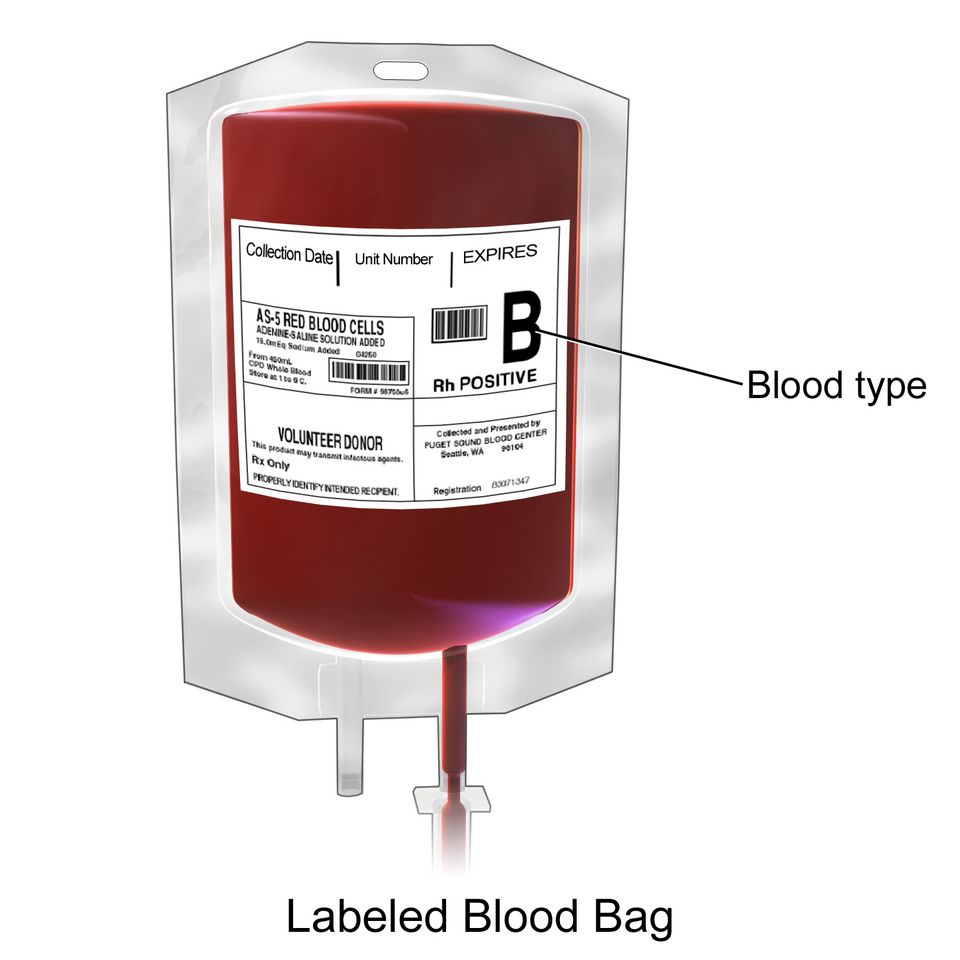
Every drop of blood carries a kind of ID badge. Tiny protein and sugar markers called antigens sit on the surface of your red blood cells. Floating in your plasma are antibodies, immune proteins that attack any antigen your body does not know as its own. Early in life your immune system learns to leave your own red cells alone. It stays armed against foreign ones. This self-versus-nonself check is the whole reason transfusions must be matched. Give someone blood carrying an antigen their plasma has antibodies against, and those antibodies clamp onto the donor cells and destroy them. Sometimes that happens fast enough to threaten life.
The ABO system
The ABO system sorts blood into four types. The sorting depends on which antigens sit on the red cells. Type A cells carry the A antigen. Type B cells carry B. Type AB cells carry both. Type O cells carry neither. Here is the elegant part, and it feels backward at first. Your plasma automatically makes antibodies against whatever antigen you lack. So type A blood has anti-B antibodies. Type B has anti-A. Type O has both anti-A and anti-B. Type AB has neither.
Type O cells carry no A or B antigen. So there is nothing on them for a recipient's antibodies to attack. That is why O-negative is called the universal donor. It is the go-to unit in a trauma emergency, before typing is done. Type AB plasma carries no anti-A or anti-B antibodies. So an AB person can receive any ABO type. That makes AB-positive the universal recipient.
| Blood type | Antigen on red cell | Antibody in plasma |
|---|---|---|
| A | A | anti-B |
| B | B | anti-A |
| AB | A and B | none |
| O | none | anti-A and anti-B |
The Rh factor and hemolytic disease of the newborn
A second marker sits on top of ABO. It is the Rh factor, also called the D antigen. If your red cells carry it, you are Rh-positive. If not, you are Rh-negative. Rh differs from ABO in one way. Rh-negative people do not come with ready-made anti-Rh antibodies. They build them only after they are exposed to Rh-positive blood. That build-up is called sensitization.
This matters most in pregnancy. Say an Rh-negative mother carries an Rh-positive baby. A small leak of fetal blood, often during delivery, can sensitize her. The first baby is usually fine. But in a later Rh-positive pregnancy her anti-Rh antibodies can cross the placenta. They then destroy the fetal red cells. This is hemolytic disease of the newborn (HDN), also called erythroblastosis fetalis. It causes fetal anemia, jaundice, and heart failure.
The fix is RhoGAM (Rh immune globulin). It is given around 28 weeks and again within 72 hours of delivery. RhoGAM mops up any stray Rh-positive fetal cells. It does this before the mother's immune system can notice them and start making its own permanent antibodies. So sensitization never happens.
Type, screen, and crossmatch
Before any transfusion the lab does three things. It types the blood, which means finding the ABO and Rh. It screens the plasma for unexpected antibodies. And it crossmatches, mixing donor cells with recipient plasma to confirm they do not clump. Clumping is called agglutination. It is the visible warning that antibodies are attacking, and it means that unit is unsafe. This careful matching is why transfusion is normally so safe.
When a transfusion goes wrong
Reactions still happen, and telling them apart guides your response.
- Acute hemolytic reaction is the feared one. It usually comes from an ABO mismatch, often a clerical or ID error. Recipient antibodies destroy the donor cells and release hemoglobin. That can trigger fever, chills, flank or back pain, dark urine, hypotension (low blood pressure), and kidney failure.
- Febrile non-hemolytic reaction is the most common one. The recipient reacts to donor white blood cells and gets fever and chills. It is uncomfortable but usually not dangerous.
- Allergic reaction is a response to donor plasma proteins. It ranges from hives and itching up to anaphylaxis.
For any suspected reaction the priority is the same. Stop the transfusion immediately. Keep the IV line open with normal saline, using fresh tubing so no more blood enters. Then check vital signs. Notify the provider and the blood bank. Send the blood bag and tubing back for analysis.
Work through a reaction in the figure below. See what stopping the unit early saves.
Explore the ABO and Rh types in the figure below.
- ABO type is set by antigens on the red cells. Plasma carries antibodies against the antigens you lack. So O-negative is the universal donor and AB-positive is the universal recipient.
- Rh-negative people make anti-Rh antibodies only after exposure. RhoGAM prevents maternal sensitization and hemolytic disease of the newborn.
- Blood is typed, screened, and crossmatched to catch agglutination before it reaches the patient.
- Acute hemolytic reactions from an ABO mismatch are the most dangerous. Febrile and allergic reactions are more common but usually milder.
- For any suspected transfusion reaction, stop the transfusion first. Then keep the line open with saline and notify the provider and blood bank.
Section 5Blood cancers
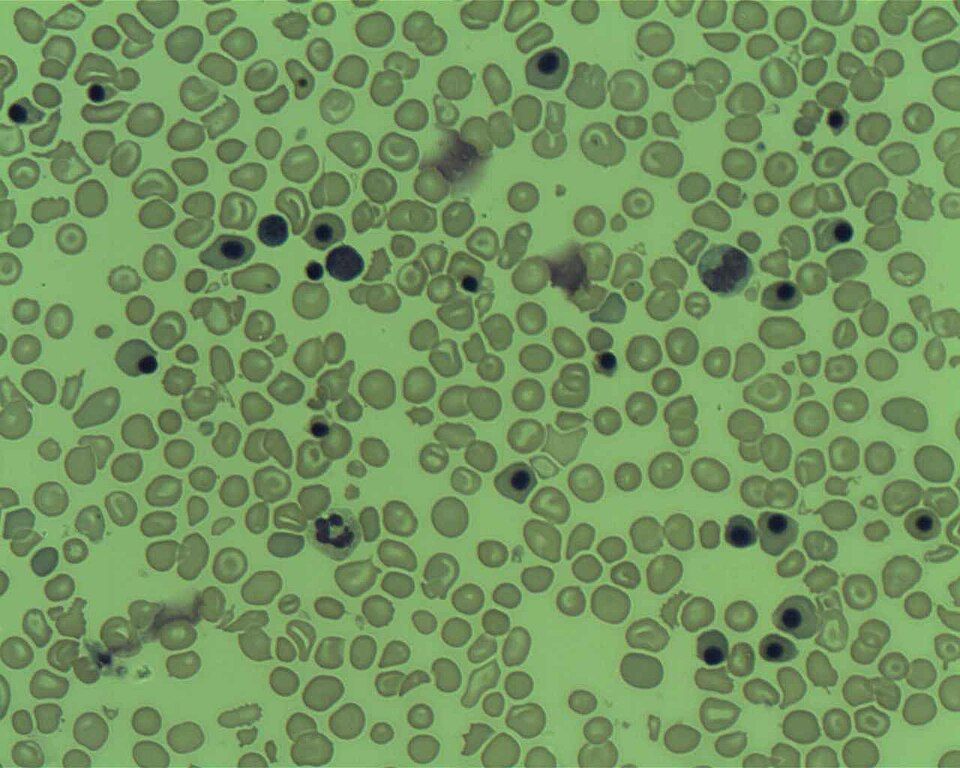
Your bone marrow is a busy blood factory. Deep inside your big bones, hematopoietic stem cells divide and mature. They become three great families of blood cells. Red cells carry oxygen. Platelets plug leaks. White cells fight infection. Normally this factory is tightly controlled. Every cell knows when to grow, when to stop, and when to die. Blood cancers happen when one line of blood cells loses that control. The cells then multiply with no brake. The trouble is not just the abnormal cells themselves. They also take up space, resources, and jobs that healthy cells need. Work out which cell went rogue and where it piles up. That explains almost every symptom your patient will have.
Leukemia: the marrow gets crowded out
Leukemia is cancer of the white-cell-forming lines in the bone marrow. Immature, useless white cells, often called blasts, reproduce so fast that they physically crowd out normal production. Picture a factory floor jammed with defective units, so nothing else can be built. That single mechanism explains the classic triad. Too few red cells means anemia, with fatigue, pallor, and shortness of breath. Too few platelets means thrombocytopenia, with easy bruising, petechiae, and bleeding gums. Too few functional white cells means dangerous infection risk. That risk holds even though the total white count on the lab report may look high.
Leukemias are sorted two ways. Acute versus chronic describes tempo. Acute leukemias explode with immature blasts and make patients sick in days to weeks. Chronic leukemias smolder for months to years, with more mature-looking cells. Myeloid versus lymphocytic describes the parent line. Myeloid cells give rise to red cells, platelets, and granulocytes. Lymphocytic cells give rise to lymphocytes. Combine the two pairs and you get the four big names.
| Type | Who it usually affects | Key feature |
|---|---|---|
| ALL (acute lymphocytic) | Children most often | The most common cancer in childhood; responds well to treatment |
| AML (acute myeloid) | Older adults | Blasts may show Auer rods |
| CLL (chronic lymphocytic) | Older adults | Often found by chance on routine bloodwork |
| CML (chronic myeloid) | Middle-aged adults | Linked to the Philadelphia chromosome |
Lymphoma: cancer that builds tumors in lymph tissue
Leukemia floods the marrow and blood. Lymphoma works differently. It is a solid cancer of lymphocytes that grows into masses. Those masses sit inside lymph nodes and lymphoid organs like the spleen. The hallmark sign is painless lymphadenopathy. That means a firm, swollen, non-tender node in the neck, armpit, or groin. Patients often also have B symptoms. That is the textbook name for three findings together: drenching night sweats, fever with no clear cause, and weight loss.
Lymphomas split into two branches. Hodgkin lymphoma is defined by one giant abnormal cell on biopsy, the Reed-Sternberg cell. It usually starts in one node region. It then spreads in an orderly, predictable pattern, which helps make it one of the more curable cancers. Non-Hodgkin lymphoma is a large, diverse group with no Reed-Sternberg cells. It tends to be more scattered and less predictable at diagnosis. It is also far more common overall.
Multiple myeloma: rogue plasma cells attack bone and kidney
Plasma cells are the mature antibody-factory version of B lymphocytes. In multiple myeloma, one plasma cell line turns malignant. It churns out a single useless antibody, called a monoclonal (M) protein, while crowding the marrow. Its damage spells out neatly with the mnemonic CRAB: Calcium elevated, Renal (kidney) injury, Anemia, and Bone lesions.
- Bone lesions: myeloma cells activate osteoclasts that eat away bone. That leaves punched-out lytic lesions, deep bone pain, and pathologic fractures.
- Hypercalcemia: the dissolving bone dumps calcium into the blood. That causes confusion, constipation, and thirst.
- Kidney injury: the flood of M protein and calcium clogs and damages the renal tubules.
- Anemia and infection: the marrow is crowded, and the antibodies made do not actually work.
Explore the interactive figure below to see how leukemia fills the marrow, how lymphoma builds masses in nodes, and how myeloma eats into bone.
- Leukemia crowds the bone marrow with abnormal white cells. That causes anemia, bleeding from low platelets, and infection. It is classified acute versus chronic and myeloid versus lymphocytic (ALL, AML, CLL, CML).
- Lymphoma forms solid masses in lymph nodes. Hodgkin shows Reed-Sternberg cells and spreads in a set pattern. Non-Hodgkin is more common and more scattered. Watch for painless lymphadenopathy plus B symptoms.
- Multiple myeloma is malignant plasma cells. Remember CRAB: hyperCalcemia, Renal injury, Anemia, and Bone lytic lesions. A monoclonal M protein drives it.
- The shared red flags across blood cancers are fatigue, frequent infections, and easy bruising. A high WBC in leukemia still means the patient is immunocompromised.
The chapter in one breath
- Hematopoiesis builds every blood cell from a single kind of bone-marrow stem cell. Erythropoietin from the kidney drives red-cell production, so kidney failure often causes anemia.
- Blood splits into plasma (fluid, proteins, clotting factors) and formed elements. RBCs carry oxygen on hemoglobin. WBCs fight infection. Platelets plug leaks.
- Iron-deficiency anemia makes RBCs small and pale (microcytic, hypochromic) with a low ferritin. It causes fatigue, pallor, and pica.
- Vitamin B12/folate deficiency makes large immature cells (macrocytic, megaloblastic anemia). Only B12 loss adds nerve signs, and B12 needs stomach intrinsic factor to be absorbed.
- Sickle cell anemia is inherited hemoglobin S. It warps RBCs when they lose oxygen and sets off painful vaso-occlusive crises. Hemolytic anemias destroy cells early and raise bilirubin.
- Clotting fails from too few platelets (thrombocytopenia), missing factors (hemophilia), or widespread clotting-then-bleeding (DIC). Watch for petechiae, bruising, and prolonged bleeding.
- Transfusion safety rests on ABO and Rh typing. Type O is the universal RBC donor and AB the universal recipient. A mismatch triggers a life-threatening hemolytic reaction.
- Leukemias flood the marrow with abnormal white cells and crowd out normal lines. Lymphomas grow in lymph nodes (Hodgkin vs non-Hodgkin). Multiple myeloma is malignant plasma cells eating bone.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- ABO system
- The main way red cells are grouped (A, B, AB, O), based on which sugar antigens sit on the red-cell surface. Your plasma carries antibodies against the antigens you lack, so a mismatched transfusion sets off a dangerous hemolytic reaction.
- Anemia
- Too few red blood cells, or too little hemoglobin, so the blood carries less oxygen. It usually brings fatigue, pallor, and shortness of breath.
- DIC (disseminated intravascular coagulation)
- A life-threatening emergency. Clotting switches on all through the small vessels and uses up clotting factors and platelets so fast that the patient both clots and bleeds at the same time.
- Erythropoietin
- A hormone released mainly by the kidneys when oxygen is low. It tells the bone marrow to make more red blood cells.
- Hematopoiesis
- The ongoing process, mostly in red bone marrow, in which stem cells mature into all the formed elements of blood: red cells, white cells, and platelets.
- Hemoglobin
- The iron-containing protein inside red blood cells. It binds oxygen in the lungs and releases it to the tissues. It also gives blood its red color.
- Hemophilia
- An inherited bleeding disorder, usually X-linked, caused by a missing or low clotting factor (factor VIII in type A, factor IX in type B). Bleeding is prolonged and often goes into joints and muscles.
- Hemostasis
- The body's step-by-step way of stopping bleeding. It moves from blood-vessel spasm to a platelet plug and finally to a stable fibrin clot.
- Intrinsic factor
- A protein made by the stomach's parietal cells. It binds vitamin B12 so B12 can be absorbed in the small intestine. Without it, B12 deficiency develops.
- Leukemia
- A cancer of blood-forming tissue. The marrow makes too many abnormal, immature white blood cells, and these crowd out healthy cells. The patient is then prone to infection, bleeding, and anemia.
- Macrocytic
- A word for red blood cells that are abnormally large. This pattern is often seen in vitamin B12 or folate deficiency.
- Microcytic
- A word for red blood cells that are abnormally small. This pattern is classic for iron-deficiency anemia.
- Pernicious anemia
- A macrocytic anemia caused by loss of intrinsic factor, often from autoimmune damage to the stomach lining. Vitamin B12 cannot be absorbed, so red cells do not mature properly.
- Sickle cell disease
- An inherited disorder in which abnormal hemoglobin S makes red cells stiffen into a crescent shape under low-oxygen stress. The rigid cells block small vessels and cause painful crises, hemolysis, and organ damage.
- Thrombocytopenia
- An abnormally low platelet count. It raises the risk of easy bruising and of bleeding that is prolonged or starts on its own.
- Virchow's triad
- The three conditions that together invite an abnormal clot: sluggish blood flow (stasis), vessel-wall injury, and blood that clots too easily (hypercoagulability).
DrillFlashcards for this unit
These are the Week 8 cards. It is the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it. Hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.