Pharmacological Principles & Herbal Supplements
Every drug you will ever give is a bargain. You accept a wanted effect and you accept, in the same breath, the unwanted ones that ride along with it. Pharmacology is the study of that bargain — what the body does to a drug, what the drug does to the body, and how a nurse tips the odds toward benefit and away from harm. This chapter builds the vocabulary and the reasoning you will use for every medication in the rest of the book: how drugs are named and grouped, how they move through a patient, how they act once they arrive, how to give them safely, and why the bottle of ginkgo in your patient's purse belongs on the medication list too.
By the end of this chapter you can
- Distinguish a drug's chemical, generic, and trade names, and explain why nurses work in generic names.
- Define a drug class and a prototype drug, and use a prototype to predict a whole class's effects.
- Describe the four pharmacokinetic processes — absorption, distribution, metabolism, excretion — and the first-pass effect.
- Use half-life to reason about dosing intervals, steady state, and trough levels.
- Explain pharmacodynamics: receptors, agonists and antagonists, dose–response, potency versus efficacy.
- Interpret the therapeutic index and name the common narrow-therapeutic-index drugs.
- Apply the rights of medication administration, match a drug to an appropriate route, and name concrete error-prevention practices.
- Identify common herbal supplements and their clinically important drug interactions.
Section 1Drugs, names & classes
One drug, three names
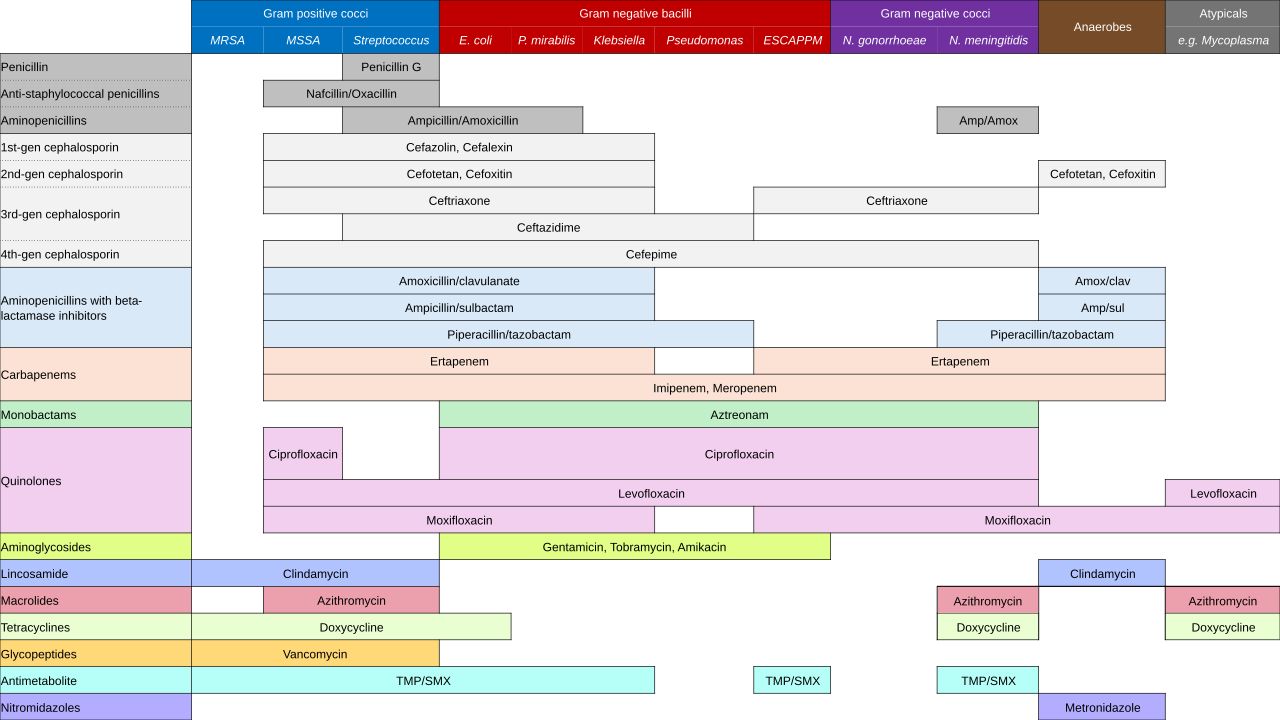
A drug is any chemical that changes the way the body works. Every approved drug carries three names, and confusing them is one of the quiet sources of medication error. The chemical name describes the molecule — N-acetyl-para-aminophenol — and you will essentially never use it. The generic name (also called the nonproprietary or United States Adopted Name) is the drug's one true name: acetaminophen. It belongs to no company, it never changes, and it is what the order, the chart, and the reference book use. The trade name (brand or proprietary name) is the marketing name the manufacturer owns — Tylenol, and a dozen others.
Here is why this matters at the bedside. One generic drug can wear many trade names, and a patient arriving from home may know only the brand. A patient taking Tylenol, Percocet, and a nighttime cold remedy is taking acetaminophen three times and may sail past the maximum daily dose without ever recognizing the drug. Nurses work in generic names precisely because the generic name is the only name that cannot hide a duplicate.
Generic names also carry built-in clues. Most classes share a stem — a fragment of the name that tells you what the drug is before you look it up. If it ends in -olol it is a beta blocker; -pril, an ACE inhibitor; -statin, an HMG-CoA reductase inhibitor; -prazole, a proton pump inhibitor; -cillin, a penicillin; -sartan, an angiotensin II receptor blocker. Learning stems is one of the highest-yield hours you can spend in this book.
Classes: sorting drugs by what they do
A drug class (or pharmacologic class) is a group of drugs that share a mechanism of action, and therefore share effects, adverse effects, and nursing implications. This is the whole reason pharmacology is learnable. There are thousands of drugs and only a few dozen mechanisms that matter. You are not memorizing a list; you are learning a small number of stories and then recognizing which story a new drug belongs to.
Drugs can be grouped two ways, and both appear in practice. A therapeutic classification says what the drug is used for — antihypertensive, anticoagulant, analgesic. A pharmacologic classification says how it works — calcium channel blocker, vitamin K antagonist, opioid receptor agonist. One drug lives in both systems at once: metoprolol is therapeutically an antihypertensive and antianginal, and pharmacologically a beta1-selective adrenergic blocker.
Prototype drugs
Because a class shares a mechanism, each class has a prototype — the well-studied, representative member you learn cold, then use as the template for every other drug in the family. Learn morphine and you have most of hydromorphone, fentanyl, and oxycodone. Learn furosemide and bumetanide and torsemide hold few surprises. When you meet an unfamiliar drug, your first question is not "what does this do?" but "what class is this, and what is the prototype?"
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Beta blockers (-olol) | metoprolol | Blocks beta1 receptors → lower heart rate and blood pressure, less cardiac workload | Hold and notify for HR under 60 or SBP under 90; never stop abruptly (rebound tachycardia, angina, MI); may blunt hypoglycemia warning signs |
| ACE inhibitors (-pril) | lisinopril | Blocks formation of angiotensin II → vasodilation, lower BP, renal protection | Dry hacking cough, hyperkalemia, first-dose hypotension; angioedema is an emergency; contraindicated in pregnancy |
| Loop diuretics | furosemide | Blocks Na-K-2Cl reabsorption in the loop of Henle → brisk diuresis | Watch hypokalemia, hypotension, dehydration; push IV slowly (ototoxicity); daily weight is the best measure of fluid loss |
| Opioid agonists | morphine | Mu-receptor agonist → analgesia, sedation, euphoria | Respiratory depression is the killer — monitor rate and sedation; constipation never resolves, treat it; antidote is naloxone |
| Benzodiazepines (-azepam, -azolam) | lorazepam | Enhances GABAA → sedation, anxiolysis, seizure control | Additive CNS and respiratory depression with opioids and alcohol; fall risk in older adults; antidote is flumazenil (rarely used — it can precipitate seizures) |
| Anticoagulants | warfarin | Inhibits vitamin K epoxide reductase → less synthesis of factors II, VII, IX, X → less clotting | Monitor INR (usual target 2–3); antidote is vitamin K (phytonadione); teach consistent — not zero — leafy-green intake; enormous interaction list. Contrast heparin: acts immediately by potentiating antithrombin, monitored by aPTT (1.5–2.5 times control), reversed by protamine sulfate; watch for HIT (heparin-induced thrombocytopenia) |
| Statins (-statin) | atorvastatin | Inhibits HMG-CoA reductase → lower LDL cholesterol | Report unexplained muscle pain or weakness (myopathy, rhabdomyolysis); avoid grapefruit juice with several agents; monitor liver enzymes |
| Proton pump inhibitors (-prazole) | omeprazole | Irreversibly blocks the gastric H+/K+-ATPase → much less acid | Give before the first meal of the day; long-term use is linked to low magnesium and B12, fractures, and C. difficile; deprescribe when the indication ends |
- Every drug has a chemical, a generic, and one or more trade names; nurses work in generic names.
- Generic stems (-olol, -pril, -statin, -prazole, -sartan) identify the class on sight.
- A drug class shares a mechanism, so it shares effects, adverse effects, and nursing implications.
- Learn the prototype and you have the family; classify an unfamiliar drug before you try to memorize it.
Section 2Pharmacokinetics — what the body does to the drug
The four-step journey
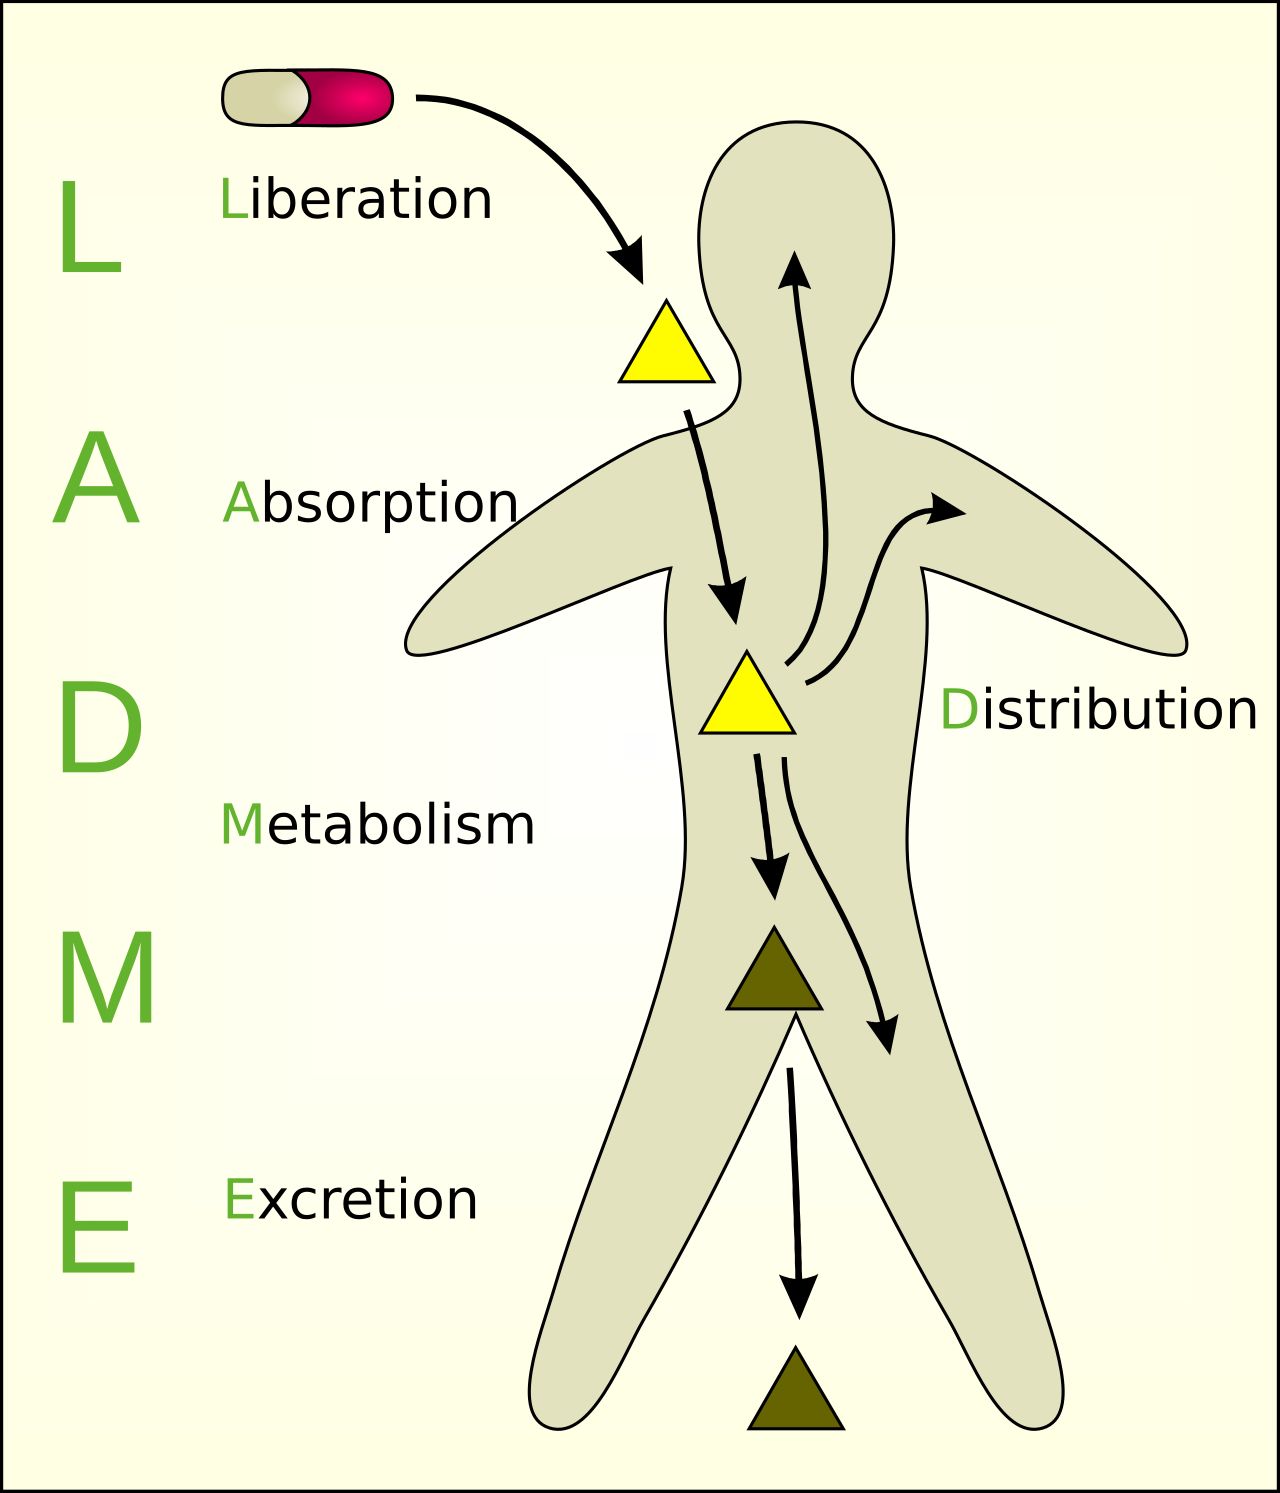
Pharmacokinetics is the study of drug movement: how a drug gets in, where it goes, how it is chemically changed, and how it leaves. Four processes, remembered as ADME, run at once from the moment of administration: Absorption, Distribution, Metabolism, Excretion. Everything that determines how much drug reaches its target and for how long lives in these four steps — which is why the same 5 mg tablet behaves very differently in a young athlete and in an 88-year-old with heart failure and kidney disease.
Absorption is the movement of drug from the site of administration into the bloodstream. It depends on the route (IV is instant and complete; oral is slow and partial), on blood flow to the site (a shocked patient absorbs almost nothing from an intramuscular injection), on the drug's ability to cross membranes (lipid-soluble and un-ionized crosses easily), and on the presence of food. The fraction of a dose that actually reaches the systemic circulation intact is its bioavailability. By definition an IV dose is 100% bioavailable; an oral dose is always less.
Distribution is the drug's travel from blood into tissue. Blood flow decides who gets it first — heart, brain, liver, and kidney are perfused richly; fat and resting muscle far less. Two barriers matter clinically: the blood–brain barrier, which only lipid-soluble drugs cross easily (a reason some antihistamines sedate and others do not), and the placenta, which stops almost nothing. Distribution is also governed by protein binding: many drugs ride on albumin, and only the unbound (free) fraction is active. A patient with low albumin — malnourished, cirrhotic, elderly — has more free drug from the same dose and is at risk for toxicity at a "normal" dose.
Metabolism and the first-pass effect
Metabolism (biotransformation) chemically alters a drug, usually in the liver, usually via the cytochrome P450 (CYP450) enzyme family. Most of the time metabolism inactivates the drug and makes it water-soluble enough to be excreted. Sometimes it does the opposite: a prodrug is given inactive and must be metabolized to work — codeine must be converted to morphine by CYP2D6, and a patient who is a poor metabolizer gets little relief while an ultrarapid metabolizer can be dangerously overdosed.
The CYP450 system is where most drug–drug interactions live. An enzyme inducer (rifampin, phenytoin, carbamazepine, St. John's wort) speeds metabolism, so partner drugs fall to subtherapeutic levels — the classic disaster is an oral contraceptive or warfarin failing. An enzyme inhibitor (many azole antifungals, clarithromycin, amiodarone, grapefruit juice) slows metabolism, so partner drug levels climb toward toxicity.
The first-pass effect is the reason a route change is never a straight swap. Anything absorbed from the stomach or intestine drains into the portal vein and is carried through the liver before it reaches the rest of the body. The liver may destroy most of the dose on that first trip. Oral morphine is the textbook case: roughly three times the IV dose is needed by mouth for the same effect. Routes that bypass the portal circulation — IV, sublingual, transdermal, rectal (partially), inhaled — escape the first pass, which is exactly why nitroglycerin is placed under the tongue and not swallowed.
Excretion, half-life, and steady state
Excretion removes the drug, overwhelmingly through the kidneys. Reduced renal function — from age, dehydration, or kidney disease — means drug accumulates, so renally cleared drugs are dose-adjusted to creatinine clearance or eGFR. Smaller routes matter for specific drugs: bile and feces (some antibiotics), lungs (inhaled anesthetics), and breast milk, which is trivial in quantity but never trivial for the nursing infant.
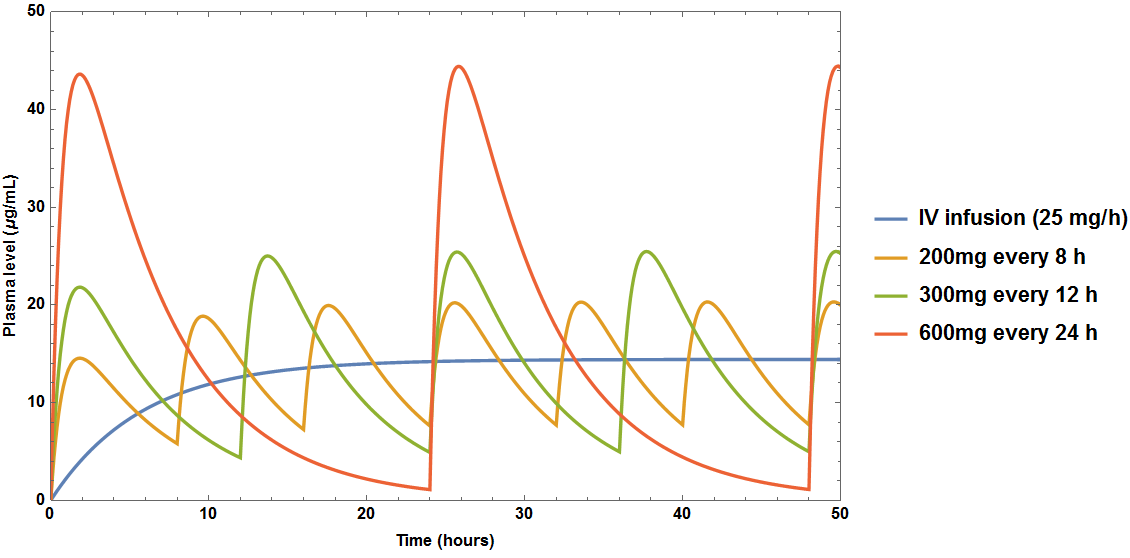
The single most useful number in kinetics is the half-life (t½): the time for plasma concentration to fall by half. Half-life sets the dosing interval, and it drives two rules worth memorizing. It takes about four to five half-lives to reach steady state — the plateau where the amount going in equals the amount coming out, and where the drug is finally doing its full job. It also takes about four to five half-lives to clear a drug after the last dose. That is why a loading dose exists: when a patient cannot wait days for steady state, a large first dose fills the tank immediately, and smaller maintenance doses keep it there.
| Step | What happens | What slows or changes it | What the nurse does |
|---|---|---|---|
| Absorption | Drug enters the bloodstream from the administration site | Route, blood flow to the site, food, gastric pH, lipid solubility | Give on an empty stomach or with food as ordered; recognize that a hypotensive patient absorbs IM and SubQ drugs unreliably |
| Distribution | Drug travels from blood into tissue | Perfusion, protein binding, blood–brain barrier, placenta, body fat | Suspect toxicity at normal doses when albumin is low; assume the drug crosses the placenta and into breast milk |
| Metabolism | Liver enzymes (CYP450) alter the drug; prodrugs are activated | Liver disease, age (neonates and elders), inducers and inhibitors, genetics | Screen for CYP interactions; watch LFTs; know which drugs are prodrugs |
| Excretion | Drug leaves, mostly in urine | Renal function, urine pH, competition for tubular transport | Check creatinine and eGFR before renally cleared drugs; monitor intake and output |
- ADME — absorption, distribution, metabolism, excretion — is what the body does to the drug.
- Bioavailability is the fraction reaching circulation intact; IV is 100%, oral is always less.
- Only the free (unbound) drug is active — low albumin means more free drug and more toxicity risk.
- The first-pass effect destroys much of an oral dose in the liver; sublingual, transdermal, and IV routes bypass it.
- It takes 4–5 half-lives to reach steady state and 4–5 to clear; a loading dose shortcuts the wait.
Section 3Pharmacodynamics — what the drug does to the body
Receptors: the lock and the key
Pharmacodynamics is the other half of the story: once the drug arrives, what does it actually do? Almost always, it binds something. Most drugs act on a receptor — a protein, usually on a cell membrane, that the body built for its own signaling molecule. Drugs do not invent new functions. They borrow existing ones, turning the body's own switches up or down. Albuterol works because your lungs already have beta2 receptors waiting for epinephrine; morphine works because your nervous system already has mu receptors waiting for endorphins.
Two properties describe the fit. Affinity is how tightly a drug binds its receptor. Intrinsic activity is whether binding actually triggers a response. That pair generates the entire vocabulary below — and it explains selectivity, too. A drug is called selective when it prefers one receptor subtype, but selectivity is dose-dependent and never absolute: metoprolol is beta1-selective at ordinary doses, which is why it is the safer choice if a patient with asthma must take a beta blocker at all, but at higher doses it spills onto the beta2 receptors in the airway and can trigger bronchospasm anyway. Nonselective agents such as propranolol block beta2 from the first dose and are avoided in reactive airway disease.
Agonists, antagonists, and everything between
An agonist binds and activates — it mimics the body's own messenger and turns the response on. An antagonist binds and blocks — it has affinity but no intrinsic activity, so it occupies the receptor and prevents the natural messenger (or another drug) from acting. Antagonists have no effect of their own; their entire effect is the absence of someone else's. A partial agonist binds and activates only weakly, producing a submaximal response no matter how high the dose — a ceiling that can be a safety feature.
| Type | What it does at the receptor | Example | What it means at the bedside |
|---|---|---|---|
| Agonist | Binds and activates; mimics the natural ligand | albuterol (beta2), morphine (mu) | Expect the natural signal, amplified — albuterol gives bronchodilation and the tremor and tachycardia that come with it |
| Antagonist | Binds and blocks; affinity, no intrinsic activity | naloxone (mu), metoprolol (beta1) | The classic antidote mechanism; naloxone evicts opioid from the receptor and reverses respiratory depression — but it is shorter-acting than most opioids, so re-sedation is the danger and the patient must be watched |
| Partial agonist | Binds, activates weakly; has a ceiling | buprenorphine (mu) | Less respiratory depression at high doses, but it will displace a full agonist and can precipitate withdrawal |
| Non-receptor action | Works by physical or chemical means, no receptor | antacids, osmotic laxatives, mannitol, chelators | Do not look for a receptor story — the mechanism is chemistry or osmosis |
Dose–response, potency, efficacy, and the therapeutic index
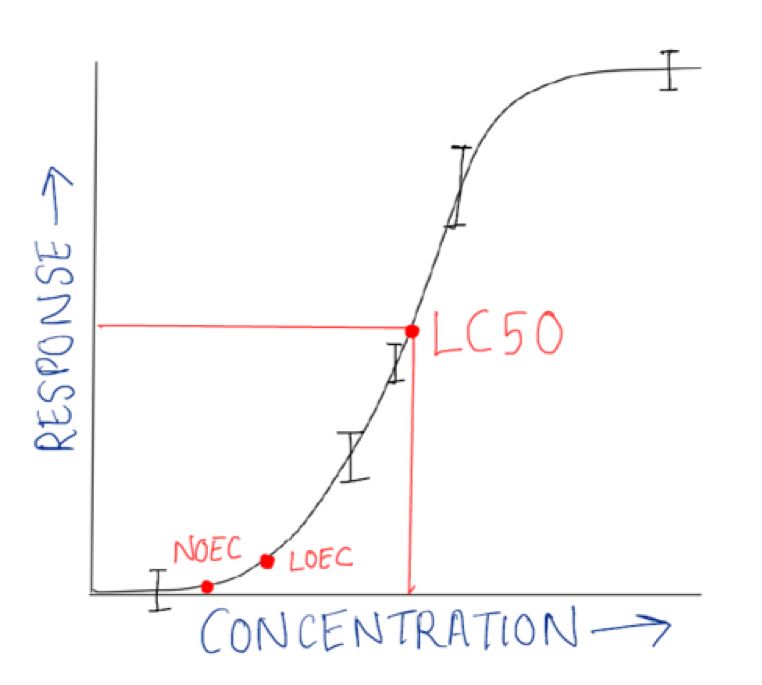
Plot dose against effect and you get the dose–response curve: little happens at the bottom (below threshold), the response rises steeply through the useful middle, then flattens into a plateau where the receptors are saturated and more drug buys no more effect — only more toxicity. That plateau is why "the pain is still there, give more" eventually stops being pharmacology and starts being harm.
Two words students routinely swap. Potency is how much drug it takes to produce a given effect — a more potent drug works at a smaller dose. Efficacy is the maximum effect the drug can produce, no matter the dose. Efficacy is what you want; potency is only a milligram number. Hydromorphone is more potent than morphine (fewer milligrams needed) but not more efficacious. Meanwhile ibuprofen has a hard analgesic ceiling that no dose can escape: for severe pain, an opioid's greater efficacy is the point.
The therapeutic index (TI) compares the dose that poisons to the dose that helps — TD50/ED50, the dose toxic to half the population divided by the dose effective in half of it. A high TI means a wide, forgiving margin. A low (narrow) therapeutic index means the effective dose and the toxic dose are uncomfortably close, and these are the drugs that get serum levels drawn, get double-checked, and land patients in the ED. Learn the list: warfarin, digoxin, lithium, phenytoin, levothyroxine, theophylline, carbamazepine, vancomycin, aminoglycosides (gentamicin), and insulin. The therapeutic range is the concentration window between "not working" and "poisoning" — and for these drugs, that window is a canyon you can fall out of in either direction.
- Drugs act by binding receptors and turning the body's own signals up or down; affinity is the fit, intrinsic activity is whether it fires.
- Agonist activates, antagonist blocks (the antidote mechanism), partial agonist activates weakly with a ceiling.
- Potency = how many milligrams; efficacy = the maximum effect possible. Efficacy is what the patient feels.
- A narrow therapeutic index drug — warfarin, digoxin, lithium, phenytoin, insulin — needs levels, monitoring, and double-checks.
Section 4Safe medication administration
The rights of medication administration
Everything above is theory until you are standing at a bedside with a cup in your hand. The rights of medication administration are the checklist that turns knowledge into safety. The traditional five are right patient, right drug, right dose, right route, right time, and most programs and employers add several more: right documentation, right reason (indication), right response, right to refuse, and right education. Verify them at three points — when you pull the medication, when you prepare it, and again at the bedside before it goes in.
Two of these deserve emphasis because they are the ones most often skipped. Right patient means two identifiers — name and date of birth against the armband, never the room number, and never the patient's nod when you say the wrong name aloud. Right response means the job is not finished when the drug is given: you gave metoprolol, so you recheck the heart rate; you gave morphine, so you reassess pain and respiratory rate and sedation; you gave insulin, so you know when the glucose will bottom out. Documentation comes after administration, never before — charting a drug you have not yet given is how a dose gets given twice.
Routes
The route decides speed, completeness, and reversibility. The single most important safety principle in the table below is this: once it is in, you cannot take it back, and the faster the route, the more absolutely that is true. An oral overdose can sometimes be intercepted; an IV push cannot.
| Route | Onset | First pass? | Nursing notes |
|---|---|---|---|
| Oral (PO) | Slow (30–60 min) | Yes | Safest and cheapest; needs a swallow and a working gut. Never crush extended-release or enteric-coated tablets — crushing an ER product delivers the whole day's dose at once |
| Sublingual / buccal | Fast (1–5 min) | No | Nothing to swallow, nothing to drink; nitroglycerin is the prototype — a tingle suggests the tablet is still potent. Absolutely contraindicated with a PDE-5 inhibitor (sildenafil, tadalafil, vardenafil) — both drugs vasodilate and the combination causes catastrophic hypotension; ask before you give |
| Subcutaneous | Slow, sustained | No | Small volumes (usually 1 mL or less); insulin and heparin; rotate sites; do not massage after heparin (bruising) |
| Intramuscular | Moderate | No | Larger volumes; ventrogluteal is the safest adult site; absorption fails in shock or poor perfusion |
| Intravenous | Immediate | No | 100% bioavailable and irreversible — know the push rate, the compatibility, and the antidote before you start; watch for infiltration and extravasation |
| Transdermal | Slow, steady | No | Remove the old patch before applying the new one (stacked fentanyl patches have killed patients); date and initial; wear gloves; rotate sites |
| Inhaled | Fast, local | No | Local effect with small systemic dose; if both are ordered, bronchodilator before corticosteroid; rinse the mouth after inhaled steroids to prevent thrush |
| Rectal | Variable | Partial | Useful when the patient is vomiting or unconscious; absorption is unpredictable |
Orders and error prevention
A complete medication order names the patient, the date and time, the drug, the dose, the route, the frequency, and the prescriber's signature. If any element is missing, ambiguous, or simply does not make sense for this patient, the order is not valid and you do not give it — you clarify it. "The prescriber wrote it" has never been a defense; the nurse who administers is independently accountable for the drug.
High-alert medications are those that cause disproportionate harm when they go wrong: insulin, anticoagulants (heparin, warfarin), opioids, concentrated electrolytes (especially potassium chloride), chemotherapy, neuromuscular blockers, and sedatives. They earn an independent double-check — a second nurse who verifies the drug, dose, pump settings, and patient without being told what you already calculated. And a permanent rule: concentrated potassium chloride is never given IV push, ever. It must be diluted and infused.
Then there is how the numbers are written. Use a leading zero (0.5 mg, not .5 mg — a missed decimal point becomes a tenfold overdose) and never a trailing zero (5 mg, not 5.0 mg — which reads as 50). Spell out "units" rather than writing "U," which is misread as a zero. Avoid the abbreviations on your facility's do-not-use list. And know your look-alike/sound-alike (LASA) pairs: hydralazine and hydroxyzine, celecoxib and citalopram, metformin and metronidazole, lamotrigine and lamivudine, and — the pair that reaches the ICU — morphine and hydromorphone. Read the label three times — pulling it, preparing it, and returning or discarding it.
- The rights — patient, drug, dose, route, time, plus documentation, reason, response, refusal, education — are checked three times, and right patient means two identifiers.
- Route determines onset and reversibility; IV is immediate and cannot be undone; never crush ER or enteric-coated tablets.
- High-alert drugs (insulin, anticoagulants, opioids, concentrated KCl, chemo) need independent double-checks; KCl is never IV push.
- Use a leading zero, never a trailing zero; spell out "units"; know your LASA pairs.
- An unclear or incomplete order is clarified, not given — the administering nurse is independently accountable.
Section 5Herbal supplements & interactions

Supplements are drugs, whatever the label says
Roughly one in five adults takes an herbal product, and the majority never mention it to a clinician — because in their minds a supplement is food, not medicine. That belief is the hazard. A dietary supplement in the United States is regulated under the Dietary Supplement Health and Education Act (DSHEA) of 1994 as a food, not a drug. It requires no pre-market proof of safety or efficacy, and the FDA can act only after harm appears. Nobody verified the potency, the purity, or the contents of the bottle in your patient's bag.
Meanwhile, the pharmacology is entirely real. Digoxin comes from foxglove, aspirin from willow bark, morphine from the poppy, atropine from belladonna, and paclitaxel from the yew tree. Plants are chemists. "Natural" has never meant safe — hemlock is natural — and a compound potent enough to help is by definition potent enough to interact.
The interactions that actually matter
Herbal interactions cluster into three predictable mechanisms, which means you can reason instead of memorize. First, CYP450 and P-glycoprotein effects: St. John's wort is a powerful inducer and can wreck a drug regimen by driving levels down. Second, bleeding risk: the products with antiplatelet activity stack on top of anticoagulants, antiplatelets, and NSAIDs — the memorable cluster is the four G's plus feverfew (garlic, ginger, ginkgo, ginseng, feverfew). Third, additive pharmacology: kava and valerian pile onto CNS depressants; ginseng pushes glucose down on top of antidiabetics.
| Supplement | Common claimed use | Mechanism / concern | Nursing alert |
|---|---|---|---|
| St. John's wort | Depression, mood | Potent CYP3A4 and P-glycoprotein inducer; serotonergic activity | The most dangerous common supplement. Lowers levels of warfarin, oral contraceptives, cyclosporine, HIV protease inhibitors, digoxin, anticonvulsants — transplant rejection and unintended pregnancy are documented. With an SSRI or triptan, risk of serotonin syndrome |
| Ginkgo biloba | Memory, circulation | Inhibits platelet-activating factor → antiplatelet | Bleeding with warfarin, aspirin, clopidogrel, NSAIDs; lowers seizure threshold; typically stop 1–2 weeks before surgery |
| Garlic | Cholesterol, blood pressure | Antiplatelet; can reduce saquinavir levels | Additive bleeding risk; stop before surgery; may add to antihypertensives |
| Ginger | Nausea, motion sickness | Antiplatelet at higher doses | Reasonably safe in culinary amounts; bleeding risk with anticoagulants at supplement doses |
| Ginseng | Energy, "immune support" | Antiplatelet; lowers blood glucose; may reduce INR | Hypoglycemia with insulin or sulfonylureas; unpredictable warfarin effect; stimulant — insomnia, hypertension; interacts with MAOIs |
| Feverfew | Migraine prevention | Antiplatelet | Bleeding risk; abrupt discontinuation causes rebound headache |
| Kava | Anxiety, insomnia | Hepatotoxicity; CNS depression | Linked to severe liver injury and transplant; additive with benzodiazepines, alcohol, opioids; avoid with any hepatotoxic drug |
| Valerian | Insomnia | CNS depression (GABAergic) | Additive sedation with benzodiazepines, opioids, alcohol, antihistamines; fall risk in older adults |
| Echinacea | Colds, "immune support" | Immune stimulation; possible hepatotoxicity | Avoid in immunosuppression, transplant, autoimmune disease, and HIV; may oppose immunosuppressants |
| Black cohosh | Menopausal symptoms | Hepatotoxicity reports | Monitor liver enzymes; avoid with other hepatotoxic drugs; caution in hormone-sensitive cancer |
| Saw palmetto | Benign prostatic hyperplasia | Mild antiplatelet effect; hormonal activity | Bleeding risk; easing symptoms may mask untreated BPH or prostate cancer — the prescriber must know the patient takes it. Controlled trials have not shown it to lower PSA; the drugs that do are the 5-alpha-reductase inhibitors finasteride and dutasteride, which roughly halve PSA (double the value when interpreting a screen) |
| Milk thistle | Liver support | Generally well tolerated; modest CYP effects | Among the safer products; still verify against the patient's regimen, and it is not a treatment for liver disease |
| Grapefruit juice (not an herb, same problem) | Food | Intestinal CYP3A4 inhibitor | Raises levels of simvastatin, atorvastatin, amiodarone, many calcium channel blockers, some immunosuppressants; a single glass can matter and the effect lasts about 24 hours |
How to ask
The interview technique changes the answer. "Are you taking any medications?" reliably gets a "no" from a patient with three supplement bottles at home, because they do not classify them as medications. Ask instead: "What do you take that you buy without a prescription — vitamins, herbs, teas, powders, protein shakes, anything from the health-food aisle, anything a family member recommends?" Then ask them to bring in the actual bottles. Document each one on the medication list. And teach without judgment: the goal is not to talk the patient out of a supplement, it is to keep them from a bleed, a rejected transplant, or a serotonin crisis they never saw coming. Two teaching points earn their place in nearly every discharge: tell every prescriber about every supplement, and stop most herbal products one to two weeks before surgery.
- Supplements are regulated as food, not drugs — no pre-market proof of safety, efficacy, potency, or purity.
- St. John's wort is the highest-stakes common supplement: a CYP3A4/P-gp inducer that drives warfarin, contraceptives, cyclosporine, and antiretrovirals to failure, plus serotonin syndrome risk.
- The bleeding cluster — garlic, ginger, ginkgo, ginseng, feverfew — stacks with anticoagulants, antiplatelets, and NSAIDs; stop 1–2 weeks before surgery.
- Kava and black cohosh are hepatotoxic; valerian and kava add to CNS depressants; echinacea is a problem in immunosuppression.
- Ask specifically about non-prescription products and put every one on the medication list.
The chapter in one breath
- Every drug has a chemical, generic, and trade name; nurses work in generic names, and stems like -olol and -pril announce the class on sight.
- A class shares a mechanism, so it shares effects and nursing implications — learn the prototype and you own the family.
- Pharmacokinetics (ADME) is what the body does to the drug; bioavailability, protein binding, and the first-pass effect explain why the same dose behaves differently in different patients.
- Half-life drives the dosing interval: about 4–5 half-lives to reach steady state and 4–5 to clear; a loading dose skips the wait.
- Pharmacodynamics is what the drug does to the body: agonists activate, antagonists block (the antidote mechanism), partial agonists have a ceiling.
- Potency is milligrams, efficacy is the maximum effect; a narrow therapeutic index (warfarin, digoxin, lithium, phenytoin, insulin) demands levels and double-checks.
- Safe administration is the rights, two identifiers, the right route, an independent double-check for high-alert drugs, and never IV push potassium.
- Herbal supplements are unregulated drugs: St. John's wort induces CYP3A4 and wrecks regimens, the four G's plus feverfew bleed, kava and black cohosh injure the liver — so ask about the bottles no one prescribed.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Absorption
- Movement of a drug from its administration site into the bloodstream; the first step of pharmacokinetics.
- Adverse drug reaction (ADR)
- A harmful, unintended response to a drug given at a normal dose; broader and more serious than a predictable side effect.
- Agonist
- A drug that binds a receptor and activates it, mimicking the body's own messenger.
- Antagonist
- A drug that binds a receptor and blocks it, producing no effect of its own; the mechanism behind antidotes such as naloxone.
- Bioavailability
- The fraction of an administered dose that reaches the systemic circulation intact; 100% for IV, always less for oral.
- Distribution
- Movement of a drug from the blood into tissues; shaped by perfusion, protein binding, and barriers such as the blood–brain barrier and placenta.
- Efficacy
- The maximum effect a drug can produce regardless of dose — what the drug is capable of.
- Excretion
- Removal of drug and metabolites from the body, chiefly by the kidneys.
- First-pass effect
- Metabolism of an orally absorbed drug by the liver before it reaches systemic circulation; bypassed by IV, sublingual, and transdermal routes.
- Half-life (t½)
- The time required for plasma drug concentration to fall by 50%; sets the dosing interval and predicts steady state and clearance.
- High-alert medication
- A drug that causes disproportionate harm when used in error — insulin, anticoagulants, opioids, concentrated electrolytes, chemotherapy — warranting an independent double-check.
- Loading dose
- A large initial dose given to reach a therapeutic concentration quickly, rather than waiting four to five half-lives.
- Metabolism (biotransformation)
- Chemical alteration of a drug, mostly by hepatic CYP450 enzymes; usually inactivates the drug, but activates a prodrug.
- Pharmacodynamics
- What the drug does to the body — receptor binding, mechanism of action, and the dose–response relationship.
- Pharmacokinetics
- What the body does to the drug — absorption, distribution, metabolism, and excretion.
- Potency
- The amount of drug required to produce a given effect; a more potent drug works at a lower dose. Not the same as efficacy.
- Prodrug
- An inactive drug that must be metabolized into its active form — codeine converted to morphine, for example.
- Prototype drug
- The representative, well-studied member of a class used as the template for the rest of the family.
- Side effect
- A predictable, dose-related effect other than the intended one; often tolerable, sometimes the reason a patient quits the drug.
- Steady state
- The plateau at which drug entering the body equals drug leaving it; reached after roughly four to five half-lives of regular dosing.
- Therapeutic index
- The ratio of the toxic dose to the effective dose; a low (narrow) index means a dangerously small margin for error.
- Trough level
- The lowest drug concentration in a dosing interval, drawn about 30 minutes before the next dose; the level that reveals accumulation.