Endocrine Drugs
The endocrine system runs on chemical messages sent slowly, in tiny amounts, through the bloodstream — and endocrine pharmacology is mostly the art of replacing a message the body has stopped sending, or muffling one it is sending too loudly. That sounds simple until you meet the feedback loop, which quietly turns off the patient's own gland the moment you supply the hormone from outside. Almost every endocrine drug error a nurse will ever see traces back to that one fact, or to a decimal point in an insulin dose. This chapter walks through the pituitary, the thyroid, the adrenal cortex, and the pancreas — the four glands you will medicate most — and the safety habits that keep those drugs from hurting the person you gave them to.
By the end of this chapter you can
- Explain negative feedback and predict what happens to a patient's own gland when you give the hormone from outside.
- Describe the major pituitary agents — including desmopressin and octreotide — and their monitoring.
- Teach a patient how to take levothyroxine correctly and recognize under- and over-replacement.
- Compare methimazole and propylthiouracil and name the adverse effect that must be reported immediately.
- List the major adverse effects of glucocorticoids and explain why long-term therapy must be tapered.
- State the onset, peak, and duration of each insulin class and use peak times to anticipate hypoglycemia.
- Recognize and treat hypoglycemia, including glucagon rescue in an unresponsive patient.
- Describe metformin and the other oral antidiabetic classes, with the nursing alert unique to each.
Section 1Hormone principles and the pituitary
What makes a hormone drug different
A hormone is a chemical messenger released by a gland into the blood, carried to a distant tissue, and recognized there by a receptor built to fit it. Two features of that arrangement matter enormously at the bedside. First, hormones work at vanishingly small concentrations — a therapeutic dose of levothyroxine is measured in micrograms, a thousandth of the milligram doses you are used to — so a misplaced decimal point is a tenfold error, and confusing micrograms with milligrams is a thousandfold one. Second, hormones come in two chemical families that behave completely differently as drugs.
Lipid-soluble hormones (thyroid hormone and the steroid hormones such as cortisol) slip straight through the cell membrane and act on receptors inside the cell, changing which genes get transcribed. Because they work by building new proteins, their effects come on over hours to days and linger after the drug is gone — and because they are fat-soluble, they survive the gut and can be given by mouth. Water-soluble hormones (insulin, growth hormone, glucagon, vasopressin, and the other peptides) cannot cross the membrane; they dock on a receptor on the cell surface and trigger a fast intracellular signaling cascade. They act in minutes — and they are proteins, which means digestive enzymes destroy them. That single chemical fact is why insulin cannot be a pill. It is not a marketing decision or a gap in the science; a swallowed peptide is simply lunch.
Negative feedback: the idea the whole chapter rests on
Endocrine glands are governed by negative feedback, a thermostat arrangement. The hypothalamus signals the anterior pituitary, the pituitary signals the target gland, the target gland releases its hormone — and that circulating hormone travels back and switches off the hypothalamus and pituitary that ordered it. The classic example is the thyroid axis: TRH → TSH → thyroid hormone → suppression of TRH and TSH. The adrenal axis works the same way: CRH → ACTH → cortisol → suppression of CRH and ACTH.
Here is the clinical consequence, and it is worth reading twice. The loop cannot tell the difference between hormone made by the patient and hormone you injected. When you give prednisone daily for two months, the patient's hypothalamus sees plenty of steroid, stops sending CRH, the pituitary stops sending ACTH, and the adrenal cortex — unused, unstimulated — atrophies. Stop the prednisone abruptly and there is no cortisol from either source: the drug is gone and the gland cannot answer. That is adrenal crisis, and it is the reason you will hear "never stop a steroid suddenly" for the rest of your career. The same logic explains why replacement doses are titrated against the pituitary's signal — a TSH level is really the pituitary's opinion of whether your levothyroxine dose is right.
Drugs that act at the pituitary
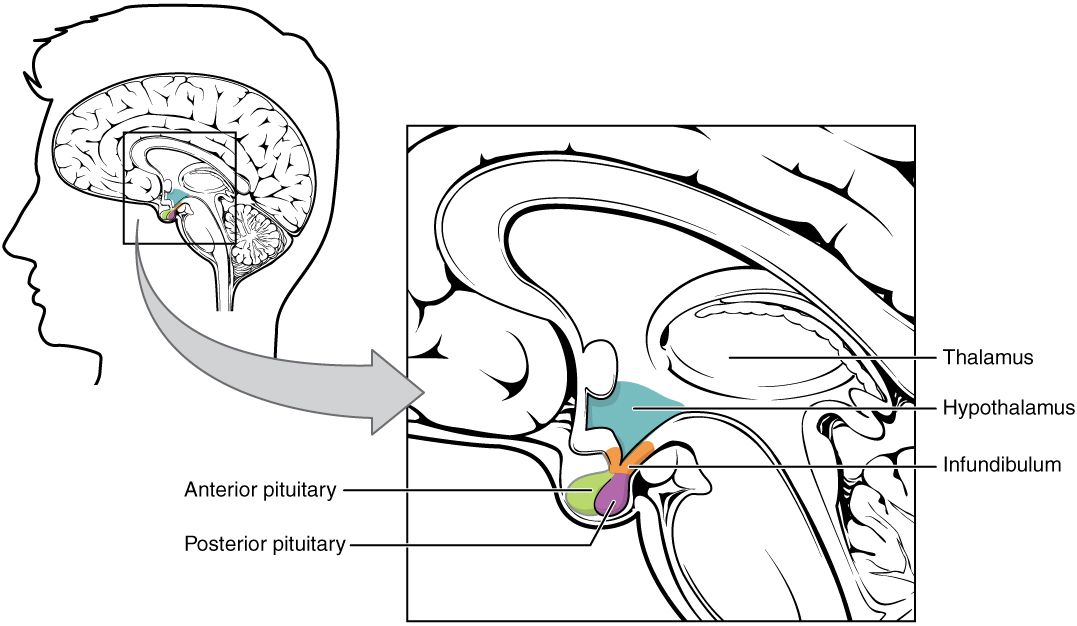
The pituitary is two glands in one coat. The anterior pituitary manufactures its own hormones — growth hormone, TSH, ACTH, prolactin, FSH, LH. The posterior pituitary manufactures nothing; it is a storage tank for two hormones made in the hypothalamus, antidiuretic hormone (ADH, vasopressin) and oxytocin. Pituitary drugs either replace a missing signal or shut down an excessive one.
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Growth hormone | somatropin | Replaces GH in deficiency; promotes linear growth in children | Subcutaneous only; rotate sites. Monitor growth velocity and blood glucose — GH is hyperglycemic. Report limp or hip/knee pain (slipped epiphysis). |
| Somatostatin analog | octreotide | Inhibits GH release; treats acromegaly, carcinoid, variceal bleeding | Monitor glucose (can swing either way), watch for gallstones, bradycardia, steatorrhea/cramping. Check IGF-1 for response. |
| Dopamine agonist | cabergoline, bromocriptine | Dopamine inhibits prolactin, so these lower prolactin and shrink prolactinomas | Orthostatic hypotension — first dose at bedtime, rise slowly. Nausea; take with food. Watch for compulsive behaviors. |
| ADH replacement | desmopressin (DDAVP) | Synthetic ADH; treats diabetes insipidus, nocturnal enuresis, mild hemophilia A/von Willebrand | Water intoxication and hyponatremia. Monitor daily weight, I&O, urine specific gravity, serum sodium. Report headache, confusion, seizure. |
| Vasopressin | vasopressin | ADH plus potent vasoconstriction; used in DI and in shock | IV in critical care; monitor BP, sodium, and the site — extravasation causes tissue necrosis. |
| Oxytocic | oxytocin | Stimulates uterine contraction and milk let-down | High-alert drug. Always on a pump, always titrated; monitor contraction pattern and fetal heart rate. Antidiuretic at high doses — watch sodium. |
Notice the pattern hiding in that table: diabetes insipidus and SIADH are mirror images, and so are their drugs. In diabetes insipidus there is too little ADH, so the kidney cannot hold water — the patient pours out liters of pale, dilute urine, the specific gravity is low, and the serum sodium climbs. You give desmopressin. In SIADH there is too much ADH, water is retained, urine is scant and concentrated, and the sodium falls. Give too much desmopressin and you have simply converted the first problem into the second — which is why the monitoring for desmopressin is not the urine output alone but the sodium.
- Hormones act at microgram concentrations — decimal errors are catastrophic; peptide hormones like insulin are digested, so they cannot be oral.
- Negative feedback cannot distinguish the patient's hormone from yours, so exogenous hormone suppresses and atrophies the patient's own gland.
- The pituitary drugs either replace (somatropin, desmopressin) or suppress (octreotide, cabergoline).
- Desmopressin's danger is water intoxication — monitor serum sodium, daily weight, and neuro status, not just urine output.
Section 2Thyroid drugs
Levothyroxine: replacing what is missing
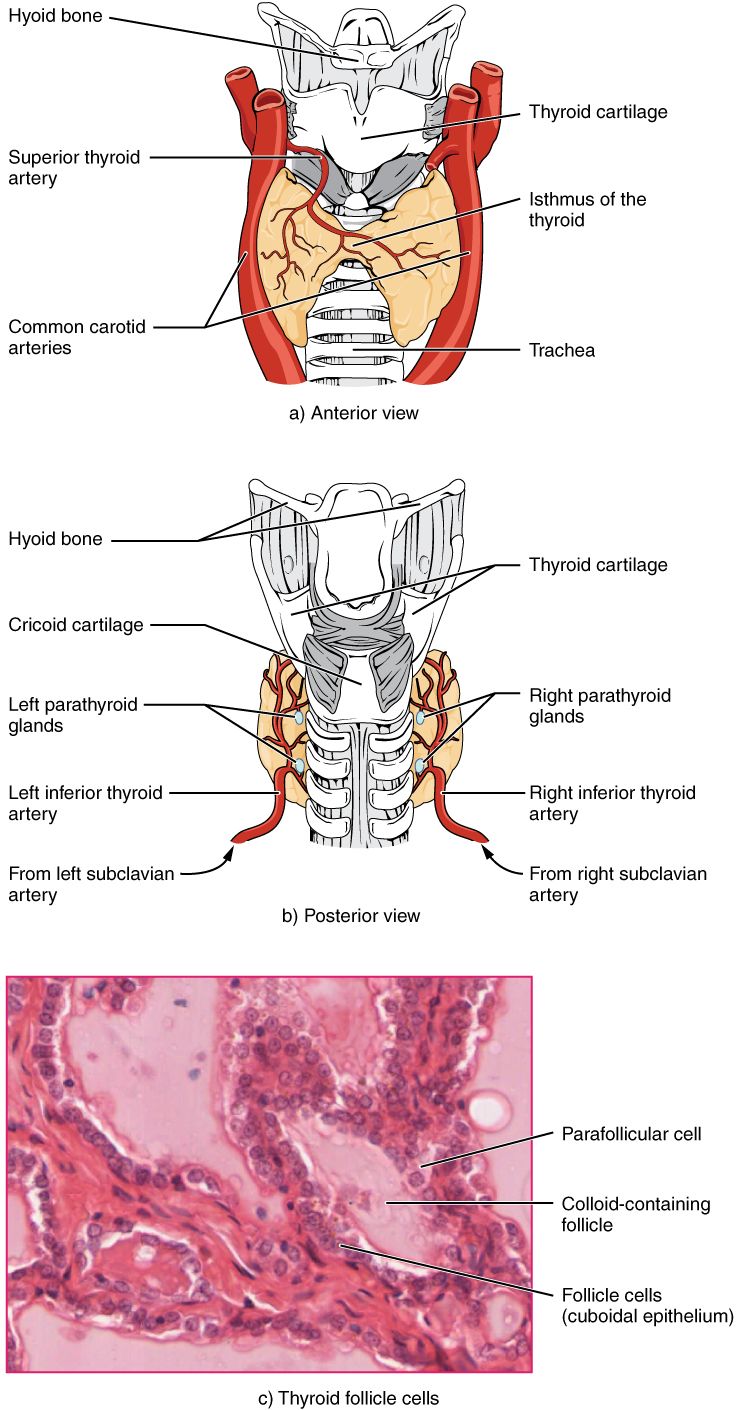
Thyroid hormone sets the body's metabolic idle speed. Too little and everything slows — the patient is cold, constipated, bradycardic, gaining weight, thinking through fog. Levothyroxine (T4) is the synthetic replacement, and it is one of the most-prescribed drugs in the country. It is chemically identical to the T4 the thyroid makes, and the body converts it to the more active T3 at the tissues, which is exactly why T4 is preferred over giving T3 directly: the patient's own tissues decide how much active hormone they need. Levothyroxine has a long half-life (about 7 days), so it is a once-daily drug, effects take weeks to appear, and a single missed dose is not an emergency.
It is also a narrow therapeutic index drug, which drives everything about how it is taken. Give it on an empty stomach with water, 30–60 minutes before breakfast, at the same time every day. Food — especially soy, walnuts, high-fiber meals, and coffee — blunts absorption. Calcium, iron, multivitamins, antacids, sucralfate, and cholestyramine bind it in the gut; separate those by at least 4 hours. Because absorption is so finicky, patients should stay on the same product and not switch brands casually. Dose is titrated against the TSH, rechecked about 6–8 weeks after any change — sooner is just measuring noise, because the hormone has not reached steady state.
Teach the patient what over-replacement feels like, because it looks exactly like hyperthyroidism: tachycardia, palpitations, nervousness, insomnia, heat intolerance, tremor, unintended weight loss. In older adults, an excessive dose brings two real hazards — atrial fibrillation and, over years, osteoporosis. This is why an older patient, or anyone with coronary artery disease, is started on a deliberately low dose and increased slowly: a suddenly faster heart in an already-narrowed coronary artery can precipitate angina or infarction. Two more teaching points that come up constantly: levothyroxine is lifelong — feeling better is evidence it is working, not permission to stop — and requirements increase during pregnancy, so a pregnant patient needs her dose and her TSH revisited early.
Antithyroid agents: turning the gland down
Hyperthyroidism is the opposite picture — racing heart, weight loss despite eating, heat intolerance, tremor, anxiety, diarrhea. The thionamides, methimazole and propylthiouracil (PTU), block the enzyme that builds thyroid hormone. They do not touch hormone already stored in the gland, so the patient does not improve for several weeks — a fact worth telling them up front, or they will decide the drug does not work and quit.
Methimazole is first-line: it is more potent, dosed once daily, and better tolerated. PTU is reserved for three situations — the first trimester of pregnancy (methimazole carries a teratogenic risk in early pregnancy), thyroid storm (PTU has the extra benefit of blocking peripheral T4-to-T3 conversion), and patients who cannot take methimazole — because PTU carries a boxed warning for severe hepatotoxicity, including liver failure. Both drugs share the effect you must burn into memory: agranulocytosis. If a patient on a thionamide reports a sore throat, fever, or mouth ulcers, that is not a cold. Hold the drug, notify the provider, and get a CBC with differential.
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Thyroid replacement | levothyroxine (T4) | Restores metabolic rate; converted to T3 peripherally | Empty stomach, 30–60 min before breakfast; separate calcium/iron/antacids by 4 h. Titrate to TSH q6–8 wk. Report chest pain, palpitations, weight loss. Lifelong. |
| T3 replacement | liothyronine (T3) | Faster onset, shorter half-life; myxedema coma, selected cases | More cardiac stimulation than T4 — monitor HR and rhythm closely. |
| Thionamide | methimazole | Blocks hormone synthesis; first-line for hyperthyroidism | Agranulocytosis — report sore throat/fever at once. Avoid in first trimester. Effect takes weeks. |
| Thionamide | propylthiouracil (PTU) | Blocks synthesis and peripheral T4→T3 conversion | Boxed warning: hepatotoxicity. Report jaundice, dark urine, RUQ pain, anorexia. Reserved for first trimester and thyroid storm. |
| Iodine solution | potassium iodide (SSKI, Lugol's) | High-dose iodine transiently shuts down hormone release; shrinks/firms gland pre-op | Give 1 hour after the thionamide. Dilute in juice, use a straw (stains teeth). Metallic taste. Short-term use only. |
| Radioactive iodine | iodine-131 | Destroys thyroid tissue permanently | Contraindicated in pregnancy/lactation. Radiation precautions; expect eventual hypothyroidism and lifelong levothyroxine. |
| Beta blocker | propranolol | Does not treat the thyroid — blocks the adrenergic symptoms | Symptom relief while thionamides take effect. Monitor HR and BP; caution in asthma. |
- Levothyroxine: empty stomach 30–60 min before breakfast, separate binders by 4 h, titrate to TSH every 6–8 weeks, lifelong, start low in older/cardiac patients.
- Over-replacement mimics hyperthyroidism — tachycardia, weight loss, insomnia; long term it risks atrial fibrillation and osteoporosis.
- Methimazole is first-line; PTU is for the first trimester and thyroid storm and carries a hepatotoxicity boxed warning.
- Both thionamides can cause agranulocytosis — sore throat, fever, or mouth ulcers means hold the drug and draw a CBC.
Section 3Corticosteroids
Two jobs in one gland
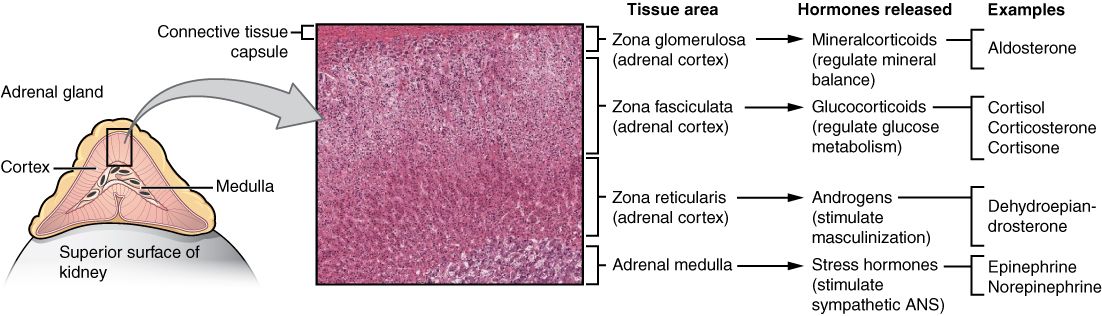
The adrenal cortex makes two kinds of steroid that matter here. Glucocorticoids — cortisol is the natural one — raise blood glucose, suppress inflammation, dampen the immune system, and help the body survive stress. Mineralocorticoids — aldosterone is the natural one — make the kidney retain sodium and water and excrete potassium. Every corticosteroid drug you give is a blend of those two activities, and the blend is the whole reason there are so many of them.
Hydrocortisone is essentially cortisol, with both activities, which makes it the drug of choice when you are replacing a missing adrenal gland. Prednisone and methylprednisolone are mostly glucocorticoid with a little mineralocorticoid — the everyday anti-inflammatories. Dexamethasone is nearly pure glucocorticoid, very potent, long-acting, and carries almost no salt-retaining effect, which is why it is chosen for cerebral edema and for situations where fluid retention would be a problem. Fludrocortisone is the mirror image: chosen for its mineralocorticoid punch, to replace aldosterone. One more thing about prednisone worth knowing: it is a prodrug, activated by the liver into prednisolone, so a patient in liver failure may be given prednisolone directly.
| Agent | Equivalent dose | Glucocorticoid / mineralocorticoid | Typical use & nursing alert |
|---|---|---|---|
| hydrocortisone | 20 mg | Both, roughly balanced | Adrenal insufficiency replacement; IV stress dosing. Short-acting. |
| prednisone | 5 mg | Mostly gluco, some mineralo | Oral workhorse (asthma, RA, IBD). Prodrug — needs a working liver. Give with food. |
| methylprednisolone | 4 mg | Gluco > mineralo | IV equivalent of prednisone; dose packs taper by design — teach the schedule. |
| dexamethasone | 0.75 mg | Almost pure gluco; long-acting | Most potent; cerebral edema, croup, antiemetic. Little salt retention. Big glucose spikes. |
| fludrocortisone | — | Chosen for mineralo | Addison's disease. Monitor BP, weight, edema, and potassium — it drives K+ out. |
The adverse effects: predictable, and all one story
Every classic steroid side effect is just cortisol's normal job, turned up too far and left on too long. Cortisol raises glucose → steroids cause hyperglycemia, and a diabetic patient started on prednisone will need more insulin, not less. Cortisol suppresses immunity → steroids bring infection risk, and worse, they mask the signs: they blunt fever and inflammation, so a serious infection can be well advanced before it announces itself. Cortisol is catabolic → long-term use brings muscle wasting, thin fragile skin, easy bruising, poor wound healing, and osteoporosis. Redistributed fat gives the cushingoid look: moon face, buffalo hump, truncal obesity on thin limbs. Add mood changes (euphoria, agitation, insomnia, occasionally frank psychosis), GI irritation and ulcer risk (worse with concurrent NSAIDs), cataracts and glaucoma, growth suppression in children, and — from the mineralocorticoid side — fluid retention, hypertension, and hypokalemia.
The nursing translation is short and concrete: check blood glucose even in patients who are not diabetic, take daily weights and blood pressures, monitor potassium, give oral doses with food, watch for any infection with a low index of suspicion, and teach the patient to avoid crowds and sick contacts and to report any fever. Live vaccines are generally avoided in patients on immunosuppressive doses. Doses are usually given in the morning, mimicking the body's natural cortisol peak — which both reduces insomnia and disturbs the axis a little less. And every patient on chronic steroids should carry medical identification.
Tapering, and the crisis that follows if you don't
Return to the feedback loop from Section 1. After roughly two to three weeks of systemic steroid at a meaningful dose, the HPA axis is suppressed and the adrenal cortex begins to atrophy. It cannot resume production on demand. So a course of more than about two weeks is tapered — the dose stepped down gradually over days to weeks — giving the hypothalamus, pituitary, and adrenal time to wake up in sequence. Stop abruptly and the patient falls into acute adrenal insufficiency (adrenal crisis): hypotension, shock, weakness, nausea and vomiting, abdominal pain, hypoglycemia, and dilutional hyponatremia. Notice what is not on that list: the potassium is usually normal. The steroid suppressed ACTH only, and aldosterone answers to renin and angiotensin rather than to ACTH, so it keeps working. Hyperkalemia belongs to primary adrenal insufficiency (Addison's disease), where the cortex itself fails and aldosterone is lost too — which is why those patients also need fludrocortisone. Either way it is a genuine emergency treated with IV hydrocortisone and fluids.
The same physiology explains stress dosing. A healthy adrenal gland pumps out extra cortisol during surgery, trauma, or serious infection; a suppressed one cannot. So patients on chronic steroids need increased doses during physiologic stress — and this is exactly when a well-meaning patient with a stomach flu decides to skip their pills because they feel too sick to eat. Teach the reverse: sick days are when the dose matters most, and if they cannot keep it down, they need to be seen.
- Glucocorticoids (cortisol/prednisone) raise glucose and suppress inflammation; mineralocorticoids (aldosterone/fludrocortisone) retain sodium and water and waste potassium.
- Potency ladder: hydrocortisone 20 mg = prednisone 5 mg = methylprednisolone 4 mg = dexamethasone 0.75 mg (most potent, least salt-retaining).
- Adverse effects are cortisol's job overdone: hyperglycemia, infection risk with masked signs, osteoporosis, cushingoid changes, mood swings, GI ulcer, cataracts, fluid retention, hypokalemia.
- Never stop abruptly after >2–3 weeks — taper, and increase the dose during illness, surgery, or trauma to prevent adrenal crisis.
Section 4Insulins
The highest of the high-alert drugs
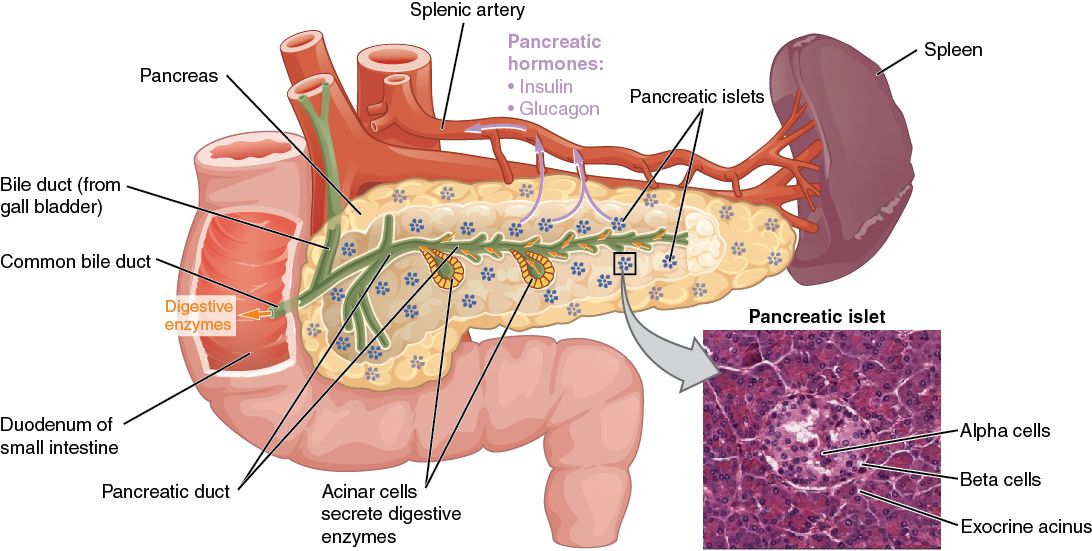
Insulin is the hormone that lets glucose out of the blood and into cells, and it is the drug that appears on every "high-alert" list in every hospital in the country — not because it is unpredictable, but because the consequences of a wrong dose are immediate and can be fatal. The safety practices are non-negotiable and worth stating plainly. Use an insulin syringe (U-100) or an insulin pen — never a tuberculin or general-purpose syringe. Never write or accept the abbreviation "U" for units; a hand-written "10U" reads as "100" often enough that the abbreviation is banned outright. Most facilities require an independent double-check by a second nurse before administration. And because insulin names look and sound alike — glargine, glulisine, lispro, degludec, detemir — read the vial label, not the shelf position.
Insulin is given subcutaneously for routine use; the abdomen absorbs fastest and most predictably, then the arm, thigh, and buttock. Rotate within one anatomic area rather than hopping between areas, so absorption stays consistent, and space injections about an inch apart to prevent lipohypertrophy — the rubbery fatty lumps that form in an overused site and absorb insulin erratically. Do not massage the site, and do not exercise the injected limb right away; both speed absorption and can drop the glucose faster than expected. Unopened vials live in the refrigerator; the in-use vial or pen can stay at room temperature and is generally discarded after 28 days (check the specific product). Never give cold insulin from the fridge if you can help it — it stings.
Onset, peak, duration: the numbers that prevent hypoglycemia
Insulins are not all the same molecule. Regular and NPH are human insulin — NPH being that same insulin complexed with protamine so it dissolves out of the tissue slowly. The rapid- and long-acting products are analogs: amino-acid substitutions (lispro, aspart, glulisine, glargine) or added fatty-acid side chains (detemir, degludec) that change how the molecules clump together, precipitate, and seep into the blood. That structural difference is the whole story — it is why glargine, which precipitates at tissue pH, can never be mixed with anything, and why protamine carried into a regular insulin vial would blunt your fast insulin. The peak is the number that matters clinically, because the peak is when the patient will go low. Learn the peaks and you can predict hypoglycemia instead of discovering it.
| Class | Prototype | Onset / peak / duration | Nursing alert |
|---|---|---|---|
| Rapid-acting | lispro, aspart, glulisine | ~15 min / 1–2 h / 3–5 h | Give with the meal in front of the patient (within 15 min). If the tray does not come, the patient goes low. |
| Short-acting | regular insulin | ~30 min / 2–3 h / 5–8 h | Give 30 min before the meal. The only insulin given IV — DKA drips, hyperkalemia. Clear. |
| Intermediate | NPH (isophane) | 1–2 h / 4–12 h / 14–24 h | The only cloudy insulin — roll gently, never shake. Broad peak means a real risk of nocturnal hypoglycemia. Can be mixed with regular. |
| Long-acting | glargine, detemir | 1–2 h / no true peak / ~24 h | Basal coverage, usually once daily — detemir's duration is dose-dependent and is often given twice daily. Never mix with any other insulin and never give IV. Clear — do not mistake for rapid-acting. |
| Ultra-long | degludec | 1 h / no peak / >42 h | Very flat and forgiving; do not mix. Steady state takes ~3 days. |
| Premixed | 70/30 (NPH/regular), 75/25 | Combines both profiles | Cloudy — roll to resuspend. Convenience at the cost of flexibility; meals must be on time. |
When two insulins are drawn into one syringe — classically NPH plus regular — the sequence is fixed: inject air into the cloudy (NPH) vial, inject air into the clear (regular) vial, withdraw the clear first, then the cloudy. Clear before cloudy — or, as generations of students have said it, regular before NPH. The reason is contamination: a trace of clear regular insulin carried into the NPH vial is harmless, but a trace of NPH's protamine carried into the regular vial would slow the action of your fast insulin, and you would never know it happened.
Hypoglycemia
A blood glucose below 70 mg/dL is hypoglycemia and it is the acute danger of every insulin. The early signs are adrenergic — the body's alarm system firing: shaky, sweaty, tachycardic, anxious, hungry, pale. If it drops further, the brain runs out of fuel and the signs turn neuroglycopenic: confusion, slurred speech, blurred vision, odd behavior, seizure, coma. That second set is often mistaken for intoxication or a stroke, and an unresponsive diabetic patient gets a fingerstick before anything else. Note that a patient on a beta blocker may lose the adrenergic warning entirely — the tremor and tachycardia are blocked — and will present with confusion as the first sign. Diaphoresis usually still comes through.
Treatment is the rule of 15: if the patient is awake and can swallow, give 15 grams of fast-acting carbohydrate — 4 ounces of juice or regular soda, 3–4 glucose tablets, a tablespoon of honey — wait 15 minutes, and recheck. Repeat until above 70, then give a snack with protein and a complex carbohydrate if the next meal is more than an hour away, so the glucose does not simply fall again. If the patient cannot safely swallow, nothing goes in the mouth: give IV dextrose 50% if there is access, or glucagon (IM, SC, or intranasal) if there is not.
- Insulin is a high-alert drug: insulin syringe or pen only, never abbreviate "units," independent double-check, read the label — the names look alike.
- The peak predicts the hypoglycemia. Rapid ~1–2 h, regular 2–3 h, NPH 4–12 h (nocturnal lows), glargine/detemir/degludec have no true peak.
- Regular is the only IV insulin; NPH is the only cloudy one; long-acting insulins are never mixed. Draw clear before cloudy.
- Hypoglycemia <70 mg/dL → rule of 15 if awake; D50 IV or glucagon if not. Beta blockers hide the early adrenergic warning signs.
Section 5Oral antidiabetics and glucagon
Metformin: the one to know cold
Type 2 diabetes is a problem of resistance — there is insulin, but the tissues have stopped listening, and the liver keeps pouring out glucose it does not need to. Metformin, a biguanide, is first-line therapy for almost every newly diagnosed adult, and it is worth knowing better than any other oral agent. It works in three ways: it decreases hepatic glucose production (its main effect), it decreases intestinal glucose absorption, and it increases the sensitivity of muscle and fat to the insulin already present.
Read that list again and notice what is absent: metformin does not squeeze more insulin out of the pancreas. That is why metformin alone does not cause hypoglycemia — a point tested relentlessly and, more importantly, a point that changes how you teach. It is also weight-neutral to modestly weight-reducing, which is a genuine advantage. Its everyday problem is the gut: nausea, diarrhea, cramping, metallic taste, largely solved by taking it with food, starting low, and using the extended-release form. Long-term use can cause vitamin B12 deficiency, so B12 is checked periodically — particularly if a patient develops anemia or neuropathy.
The rare but serious effect is lactic acidosis, which carries a boxed warning. It happens when metformin accumulates, so the risk sits with anything that impairs clearance or oxygenation: renal impairment (metformin is contraindicated at eGFR <30), acute heart failure, hypoxia, sepsis, dehydration, liver disease, and heavy alcohol use. Teach the signs, because they are vague and easy to dismiss: unusual muscle aches, deep or labored breathing, unusual sleepiness, abdominal pain, feeling generally unwell. It is also the reason iodinated contrast keeps coming up on this drug: contrast can injure the kidney, and the kidney is metformin's only exit route. The current rule is narrower than the blanket hold you may still hear on the unit. Metformin is continued through intravenous contrast when the eGFR is 30 mL/min/1.73 m2 or better and there is no acute kidney injury. It is withheld at the time of the study and for 48 hours afterward, pending a repeat creatinine and eGFR, only when the eGFR is under 30, when AKI is present or suspected, or when the contrast is given intra-arterially in a way likely to expose the renal arteries.
The other classes, and the one alert that defines each
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Biguanide | metformin | ↓ hepatic glucose output; ↑ insulin sensitivity | No hypoglycemia alone. Take with food. Avoid at eGFR <30; hold around iodinated contrast only if eGFR <30, AKI, or an intra-arterial study — otherwise it is continued. Watch B12; teach lactic acidosis signs. |
| Sulfonylurea | glipizide, glimepiride, glyburide | Stimulate beta cells to release insulin | Hypoglycemia — the big one, especially glyburide in older adults. Take with breakfast. Weight gain; sulfa allergy caution; alcohol may cause flushing. |
| Meglitinide | repaglinide, nateglinide | Short, fast insulin release for the meal | Take with each meal — skip the meal, skip the dose. Hypoglycemia risk. |
| Thiazolidinedione | pioglitazone | ↑ insulin sensitivity at muscle/fat | Boxed warning: heart failure. Fluid retention — report weight gain, edema, dyspnea. Monitor LFTs. Slow onset (weeks). |
| DPP-4 inhibitor | sitagliptin | Prolongs the body's own incretins → glucose-dependent insulin release | Well tolerated, weight-neutral. Report severe persistent abdominal pain (pancreatitis); joint pain. |
| GLP-1 agonist | semaglutide, liraglutide, dulaglutide | Incretin mimic: ↑ insulin, ↓ glucagon, slows gastric emptying, ↓ appetite | Injectable (some oral). Nausea is dose-limiting; significant weight loss. Boxed warning: thyroid C-cell tumors — avoid with personal/family history of medullary thyroid cancer or MEN 2. Pancreatitis; delayed gastric emptying. |
| SGLT2 inhibitor | empagliflozin, dapagliflozin | Blocks renal glucose reabsorption → glucose out in the urine | Proven heart-failure and kidney benefit. Genital mycotic infections and UTIs — teach hygiene, encourage fluids. Volume depletion/orthostasis. Euglycemic DKA — ketoacidosis with a near-normal glucose. |
| Alpha-glucosidase inhibitor | acarbose, miglitol | Slows carbohydrate digestion → blunts the post-meal spike | Take with the first bite. Flatulence, diarrhea. If hypoglycemic on a combination, treat with glucose tablets, not table sugar or juice — sucrose cannot be broken down. |
A few threads run through that table. The agents that push the pancreas — sulfonylureas and meglitinides — are the oral drugs that cause hypoglycemia; the rest are much safer alone, though any of them can contribute when combined with insulin. Two classes now get prescribed as much for the heart and kidney as for the sugar: SGLT2 inhibitors and GLP-1 agonists both showed cardiovascular and renal benefit in outcome trials, which is why you will find them on the medication list of patients whose A1C is nearly at goal. And the euglycemic DKA of the SGLT2 drugs deserves a moment: because the drug dumps glucose into the urine, a patient can be in genuine ketoacidosis — nauseated, breathing deeply, acidotic — with a glucose of 180. A normal fingerstick does not rule it out.
Glucagon: the rescue
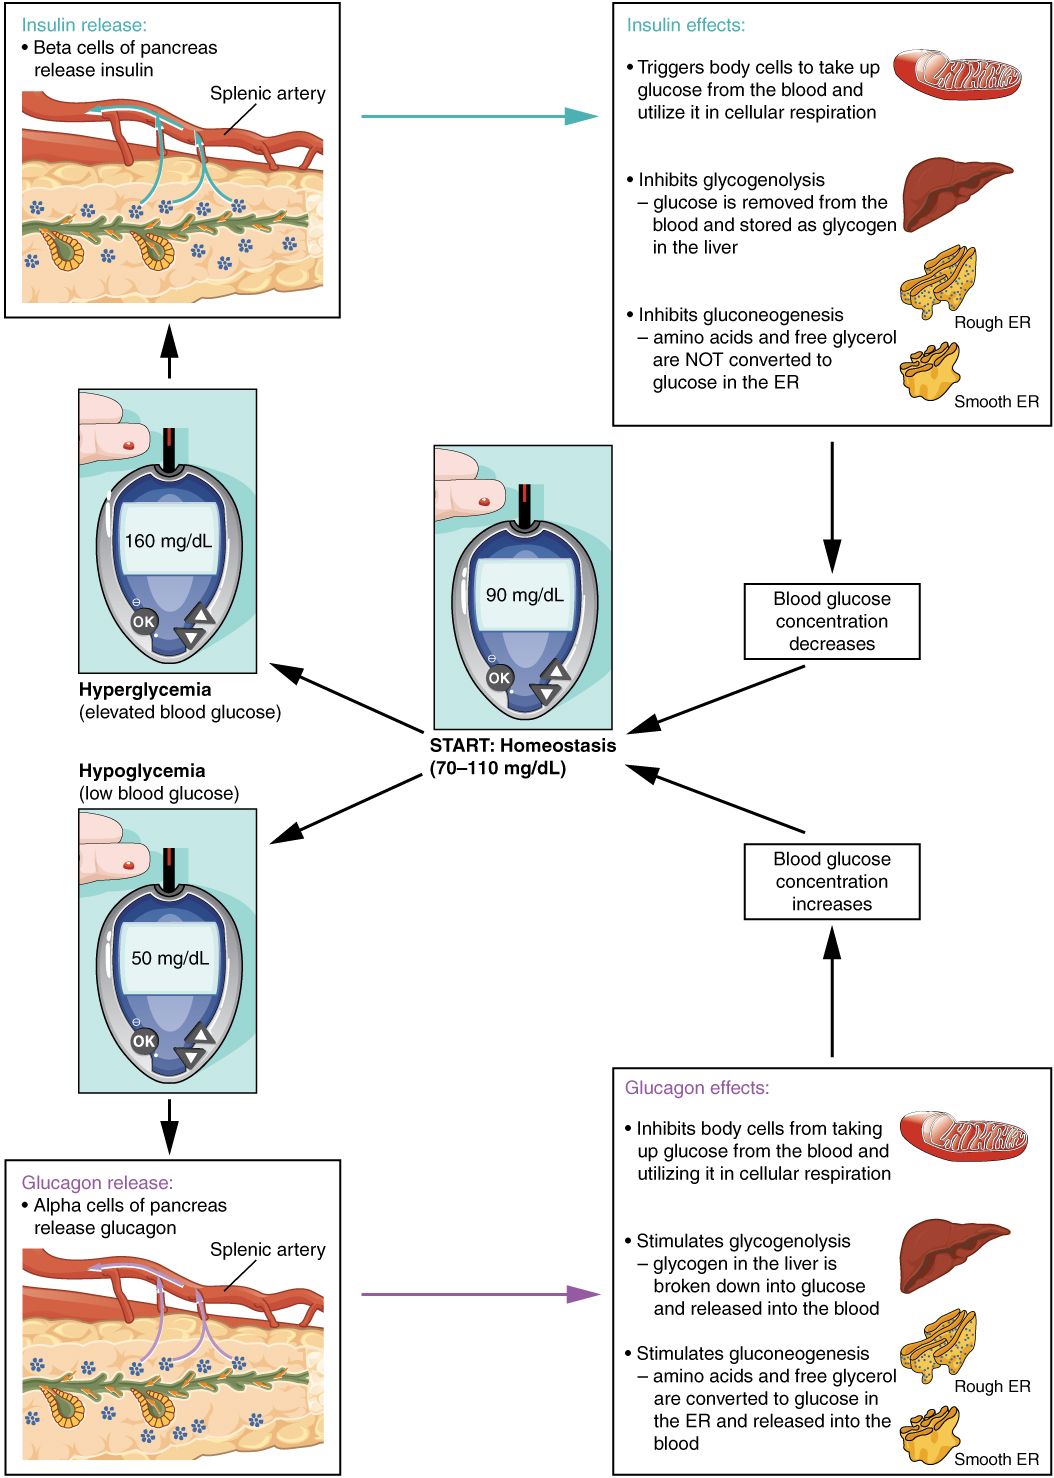
Glucagon is insulin's opposite number, the other hormone of the islets. When glucose falls, alpha cells release it, and it tells the liver to break down stored glycogen into glucose and release it into the blood. As a drug it is the rescue for severe hypoglycemia in a patient who cannot safely swallow and has no IV access — a seizing patient, an unresponsive patient, a child at home. It is given IM, subcutaneously, or intranasally, and it works in roughly 10–15 minutes.
Three things about glucagon must be taught to the family, not just charted. First, it works by emptying the liver's glycogen stores — so it fails or works poorly in a patient with no stores: chronic alcohol use, starvation, prolonged fasting, advanced liver disease. Those patients need IV dextrose. Second, vomiting is common after glucagon, so turn the patient onto their side before it takes effect to protect the airway. Third, the effect is temporary — the liver's stores are finite and the insulin that caused the low is often still working. As soon as the patient is awake and can swallow, they need oral carbohydrate, and they still need to be evaluated. Rescuing someone with glucagon and leaving is how a patient goes low a second time an hour later.
- Metformin is first-line, lowers hepatic glucose output, does not cause hypoglycemia alone, is taken with food, avoided at eGFR <30, held around iodinated contrast only when eGFR is <30, AKI is present, or the study is intra-arterial, and carries a lactic acidosis boxed warning; monitor B12.
- Sulfonylureas and meglitinides squeeze the pancreas — they are the oral agents that cause hypoglycemia; skip the meal, skip the meglitinide.
- Class-defining alerts: pioglitazone → heart failure; GLP-1 agonists → nausea, weight loss, thyroid C-cell boxed warning; SGLT2 inhibitors → genital infections and euglycemic DKA; acarbose → treat lows with glucose only.
- Glucagon mobilizes hepatic glycogen for severe hypoglycemia without IV access; it causes vomiting (turn the patient), is temporary (follow with oral carbs), and fails without glycogen stores.
The chapter in one breath
- Negative feedback is the master idea: hormone given from outside suppresses and atrophies the patient's own gland, which is why steroids are tapered and why a TSH tells you if a levothyroxine dose is right.
- Peptide hormones are digested — insulin can never be a pill; lipid-soluble hormones (thyroid, steroids) act slowly on genes and can be swallowed.
- Pituitary agents replace (somatropin, desmopressin) or suppress (octreotide, cabergoline); desmopressin's hazard is water intoxication and hyponatremia.
- Levothyroxine: empty stomach 30–60 min before breakfast, binders separated by 4 hours, TSH every 6–8 weeks, lifelong, start low in older and cardiac patients.
- Methimazole (first-line) and PTU (first trimester, thyroid storm, hepatotoxicity warning) both risk agranulocytosis — sore throat and fever means hold and draw a CBC.
- Corticosteroid adverse effects are cortisol overdone: hyperglycemia, infection with masked signs, osteoporosis, cushingoid changes, mood, ulcers, fluid retention — and abrupt withdrawal after >2–3 weeks causes adrenal crisis.
- Insulin is high-alert: know the peaks, because the peak is when the patient goes low; regular is the only IV insulin, NPH the only cloudy one, long-acting are never mixed, and hypoglycemia <70 gets the rule of 15 or, if unable to swallow, D50 or glucagon.
- Metformin leads oral therapy and causes no hypoglycemia alone; each other class is defined by one alert — sulfonylurea lows, pioglitazone heart failure, GLP-1 nausea and C-cell warning, SGLT2 euglycemic DKA, acarbose needing pure glucose to treat a low.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Adrenal crisis
- Acute, life-threatening cortisol deficiency — hypotension, shock, weakness, vomiting, hypoglycemia, dilutional hyponatremia — classically triggered by abruptly stopping a chronic steroid or by physiologic stress in a patient with a suppressed axis. Potassium is usually normal in this steroid-withdrawal (secondary) form because aldosterone is preserved; hyperkalemia points to primary (Addison's) disease. Treated with IV hydrocortisone and fluids.
- Agranulocytosis
- A dangerous fall in neutrophils, leaving the patient defenseless against infection; the reason a sore throat, fever, or mouth ulcer on methimazole or PTU is an emergency, not a cold.
- Antidiuretic hormone (ADH, vasopressin)
- The posterior pituitary hormone that makes the kidney conserve water. Too little causes diabetes insipidus; too much causes SIADH.
- Basal insulin
- Long-acting, peakless insulin (glargine, detemir, degludec) that covers the body's constant background need between meals and overnight.
- Biguanide
- The class containing metformin; lowers hepatic glucose production and improves insulin sensitivity without stimulating the pancreas.
- Duration
- How long an insulin continues to lower glucose after it is given.
- Euglycemic DKA
- Diabetic ketoacidosis occurring with a near-normal blood glucose, seen with SGLT2 inhibitors because the drug excretes glucose in the urine; a normal fingerstick does not rule it out.
- Glucagon
- The pancreatic alpha-cell hormone that mobilizes hepatic glycogen to raise blood glucose; used as rescue for severe hypoglycemia when the patient cannot swallow.
- Glucocorticoid
- A steroid whose main actions are raising blood glucose and suppressing inflammation and immunity; cortisol is the natural one, prednisone and dexamethasone the common drugs.
- High-alert medication
- A drug that carries a heightened risk of significant patient harm when used in error — insulin is the archetype — and therefore requires extra safeguards such as an independent double-check.
- Hypoglycemia
- Blood glucose below 70 mg/dL; early adrenergic signs (shaky, sweaty, tachycardic, hungry) give way to neuroglycopenic ones (confusion, slurred speech, seizure, coma).
- Incretin
- A gut hormone (chiefly GLP-1) released with a meal that stimulates insulin, suppresses glucagon, and slows gastric emptying; mimicked by GLP-1 agonists and prolonged by DPP-4 inhibitors.
- Lactic acidosis
- The rare, serious metformin toxicity that occurs when the drug accumulates; suspect it with muscle aches, deep or labored breathing, unusual sleepiness, and abdominal pain.
- Lipohypertrophy
- Rubbery fatty thickening at an overused injection site that absorbs insulin unpredictably; prevented by rotating within an anatomic area.
- Mineralocorticoid
- A steroid whose main action is sodium and water retention with potassium loss; aldosterone is the natural one, fludrocortisone the drug.
- Narrow therapeutic index
- A drug whose effective dose and toxic dose sit uncomfortably close together, demanding precise dosing and monitoring — levothyroxine and insulin both qualify.
- Negative feedback
- The thermostat arrangement in which a hormone shuts off the signals that ordered it; the loop cannot tell exogenous hormone from the patient's own.
- Onset
- How long after administration an insulin begins to lower blood glucose.
- Peak
- When an insulin exerts its maximum effect — and therefore when hypoglycemia is most likely.
- Rule of 15
- Treatment of hypoglycemia in a patient who can swallow: 15 grams of fast-acting carbohydrate, wait 15 minutes, recheck, repeat as needed.
- Taper
- The gradual stepwise dose reduction used to end corticosteroid therapy, allowing the suppressed HPA axis and atrophied adrenal cortex to resume production.
- Thionamide
- The antithyroid class — methimazole and propylthiouracil — that blocks thyroid hormone synthesis; effects take weeks because stored hormone is unaffected.