Fluid, Electrolyte and Acid-Base Balance
Almost every patient on a medical-surgical floor is there because water, salt or acid has moved somewhere it should not be. The vomiting patient, the heart-failure patient, the patient three days post-op who has not eaten, the patient on furosemide and lisinopril, the patient with a nasogastric tube to suction — each of them is a fluid and electrolyte problem wearing a different diagnosis. This chapter teaches you to read the body’s water and its chemistry the way an experienced nurse does: mechanism first, so the manifestations are predictable rather than memorised; then the assessment findings, the labs with real reference ranges, the treatment and the complications. You will learn a ninety-second method for arterial blood gases that works every time, the electrolyte thresholds that mean stop and call, and the administration rules — particularly for potassium — that separate a safe nurse from a headline. Nothing here is abstract. All of it turns up on the NCLEX and in your first month on the floor.
By the end of this chapter you can
- Differentiate the intracellular and extracellular fluid compartments and explain how osmosis, hydrostatic pressure and oncotic pressure move water between them.
- Assess and distinguish fluid volume deficit, fluid volume excess and third spacing using weight, intake and output, vital signs and laboratory data.
- State the reference ranges for sodium, potassium, calcium, magnesium and phosphorus and describe the manifestations of high and low values for each.
- Prioritise nursing actions for hyperkalemia, symptomatic hyponatremia and hypocalcemia, including the drugs used and the monitoring each requires.
- Interpret an arterial blood gas using the ROME and tic-tac-toe methods, identify the degree of compensation and calculate the anion gap.
- Select an appropriate isotonic, hypotonic or hypertonic intravenous solution for a given clinical situation and justify the choice.
- Administer intravenous potassium safely, including dilution, rate limits, monitoring and the absolute prohibition on IV push.
- Identify red-flag findings requiring immediate provider notification and communicate them using SBAR.
- Describe how fluid and electrolyte imbalance presents differently in the older adult and delegate care appropriately to the LPN and the UAP.
Section 1Fluid Compartments, Fluid Movement and Volume Imbalance
Where the water lives and what makes it move
Water is roughly 60 percent of a healthy adult male and about 50 to 55 percent of a healthy adult female, because adipose tissue holds far less water than muscle. Two thirds of that water sits inside cells as intracellular fluid. The remaining third is extracellular fluid, and it is divided again: about three quarters of it bathes the cells as interstitial fluid, and only about one quarter of it is plasma inside blood vessels. Hold on to that last number. The intravascular compartment — the one that carries the blood pressure, the one that perfuses the brain and the kidneys — is a small fraction of total body water. Losing a few litres from it is a catastrophe; losing the same volume slowly from the intracellular space produces thirst and a dry mouth.
Water crosses membranes by osmosis, moving from the side with fewer dissolved particles toward the side with more. The concentration of those particles is osmolality, normally 275 to 295 mOsm/kg in serum, and it is governed almost entirely by sodium, glucose and urea. You can estimate it as twice the serum sodium plus the glucose divided by 18 plus the BUN divided by 2.8. Because sodium dominates that equation, sodium is effectively the body’s water thermostat. Where sodium goes, water follows. This single sentence will get you through most of the sodium content in this chapter.
Inside the capillary bed, two other forces argue with each other. Hydrostatic pressure is the push of blood against the vessel wall, driving fluid out into the interstitium. Oncotic pressure, generated mostly by albumin (normal 3.5 to 5.0 g/dL), is the pull that keeps fluid in. Raise hydrostatic pressure — heart failure, venous obstruction, over-aggressive infusion — and fluid leaks out and becomes edema. Drop the albumin — cirrhosis, nephrotic syndrome, malnutrition, burns — and fluid leaks out for the opposite reason. Both look like swelling at the bedside, but the fix is different, and knowing which force is broken tells you whether the patient needs a diuretic or protein and a different plan entirely.
Regulation is hormonal and quick. Osmoreceptors in the hypothalamus sense a rising osmolality and release antidiuretic hormone, which tells the kidney to reabsorb water and concentrate the urine. Baroreceptors sensing a falling volume activate the renin-angiotensin-aldosterone system; aldosterone reabsorbs sodium (and therefore water) and excretes potassium. Stretched atria release natriuretic peptides that do the reverse. Every one of these systems is blunted in the older adult, which is why an eighty-eight-year-old with two days of diarrhoea arrives in acute kidney injury while a twenty-eight-year-old with the same illness simply feels awful.
Fluid volume deficit
Fluid volume deficit, or hypovolemia, is the isotonic loss of water and electrolytes together: haemorrhage, vomiting, diarrhoea, nasogastric suction, wound and burn exudate, excessive diuresis, fever with insensible loss, and simple failure to drink. This is not the same as dehydration in the strict sense, which is loss of water alone and raises the serum sodium. In practice the two overlap, and the nursing assessment is the same at the start.
The findings follow the physiology. With less volume in the vessels, the heart compensates first: tachycardia is the earliest reliable sign, often before the blood pressure moves at all. Then comes orthostatic hypotension — a drop of 20 mmHg systolic or 10 mmHg diastolic, or a rise in pulse of 20 beats, when the patient sits or stands. Neck veins flatten. Capillary refill lengthens beyond three seconds. Mucous membranes go dry and the tongue develops longitudinal furrows. Skin turgor tents, though in an older adult you must test it over the sternum or forehead rather than the back of the hand, where lost elastin makes it meaningless. Urine output falls below 0.5 mL/kg/hr (about 30 mL/hr in an average adult) and the urine becomes dark and concentrated, with a specific gravity above 1.030 (normal 1.005 to 1.030). Weight falls. Late findings are hypotension, weak thready pulse, cool mottled extremities and altered mental status — by which point you are in hypovolemic shock.
Laboratory work confirms haemoconcentration. Haematocrit rises above the normal 42 to 52 percent in men and 37 to 47 percent in women. BUN rises out of proportion to creatinine, so a BUN-to-creatinine ratio above 20 to 1 (normal 10 to 20 to 1, with BUN 10 to 20 mg/dL and creatinine 0.6 to 1.2 mg/dL) points to a prerenal, volume-responsive cause. Serum osmolality and sodium rise if the loss was mostly water. Urine sodium falls below 20 mEq/L as the kidney clings to salt.
Management is replacement, and the first-line fluid for an isotonic loss is an isotonic crystalloid: 0.9% sodium chloride or lactated Ringer’s. Nursing care is deceptively simple and relentlessly important — strict intake and output, daily weight on the same scale at the same time in the same clothing, vital signs with orthostatics, safety precautions because these patients faint, oral fluids when they can take them, and reassessment of lung sounds every time you increase a rate, because the same patient you are filling can be flooded.
Fluid volume excess and third spacing
Fluid volume excess is isotonic retention of water and sodium, and its causes cluster around three organs: the failing heart, the failing kidney and the failing liver. Add iatrogenic causes — over-resuscitation, excessive normal saline, corticosteroids, hypertonic solutions given too fast — and you have the majority of cases you will see. The signs are the mirror image of deficit: weight gain, bounding pulse, elevated blood pressure, distended neck veins at 45 degrees, an S3 gallop, dependent pitting edema (sacral in the bedbound, pedal in the ambulatory), periorbital puffiness, and the finding that matters most, crackles in the lung bases with dyspnoea and a falling oxygen saturation. Laboratory values show haemodilution: a low haematocrit, a low BUN, a dilute urine with a specific gravity below 1.010.
Third spacing is the awkward middle case, and students routinely miss it. Fluid shifts out of the vascular space into a compartment where it does no useful work — the peritoneum in ascites, the interstitium in burns and sepsis, the bowel wall in obstruction, the retroperitoneum in acute pancreatitis. The patient therefore looks fluid-overloaded (swollen, heavy, weight up) while being functionally hypovolemic (tachycardic, hypotensive, oliguric). Treat the intravascular deficit even though the patient appears wet. In the days that follow, the fluid reabsorbs, and the same patient can flip into overload without a single millilitre being added — which is why they need diuretics later, not sooner.
Management of true excess is sodium and fluid restriction, loop diuretics such as furosemide, positioning with the head of the bed elevated, oxygen, and vigilant monitoring of potassium because loop diuretics waste it. Nursing priorities are respiratory: assess breath sounds and saturation before anything else, then daily weights, then intake and output, then skin care over edematous tissue, which breaks down quickly and heals slowly.
Reading volume status at the bedside
Assemble the picture from several sources rather than trusting any one. Weight trend is first. Intake and output over 24 and 72 hours is second, and you should look at the balance, not the individual numbers. Vital signs including orthostatics are third. Then the focused physical: neck veins, lung bases, dependent edema graded 1 to 4 plus, mucous membranes, capillary refill, skin turgor at a reliable site. Then the labs: sodium, BUN, creatinine, haematocrit, albumin, urine specific gravity. In the critical care setting central venous pressure and dynamic measures such as pulse pressure variation refine the estimate, but on a medical-surgical floor the scale and the stethoscope will carry you.
One caution about mental status. Confusion is not a soft finding in fluid imbalance — it is often the first hard one, especially in the older adult and especially with sodium disorders. A patient who was oriented at 0800 and is picking at the sheets at 1600 has a physiologic cause until proven otherwise, and dehydration, hyponatremia and hypercalcemia are all on that list. Do not chart it as sundowning and move on.
Sodium determines where water goes and weight tells you how much of it there is, so a daily weight plus a serum sodium answers most fluid questions before you touch the patient.
Section 2Sodium and Potassium
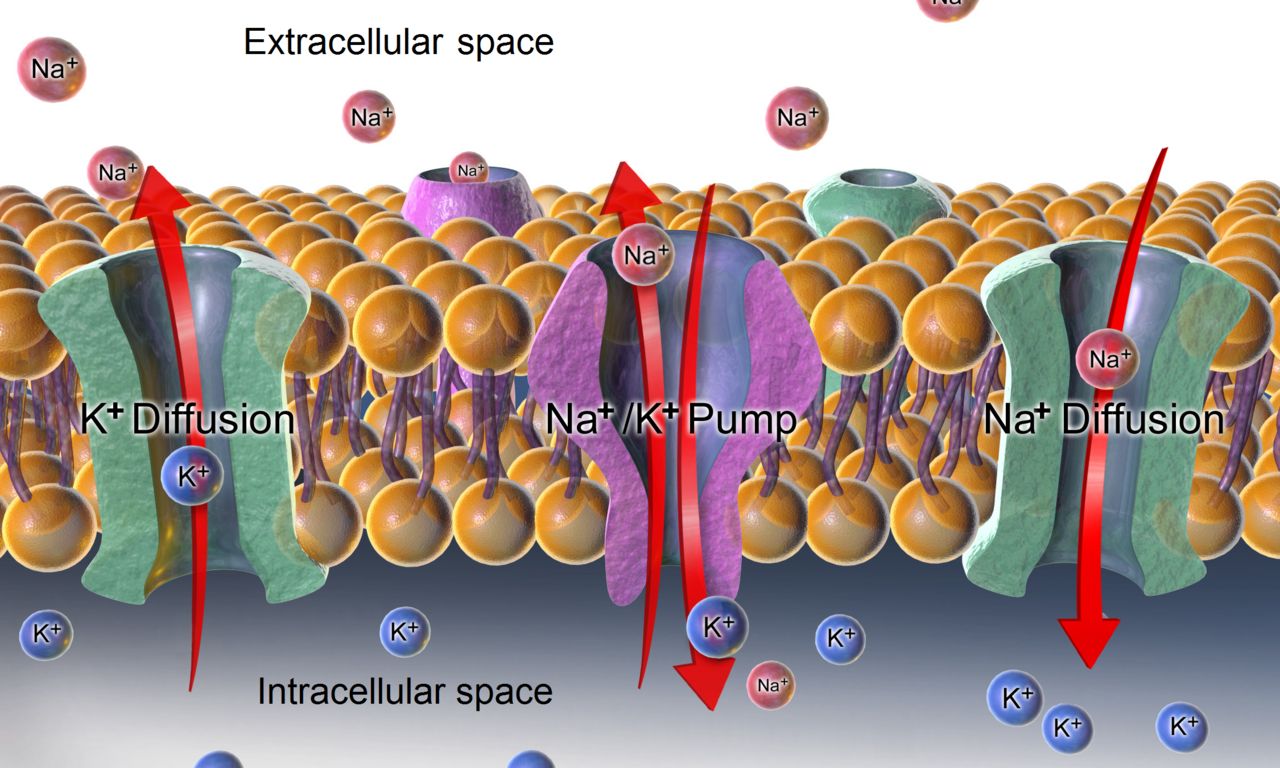
Sodium: a water problem in disguise
Serum sodium is normally 135 to 145 mEq/L. Ninety percent of the time an abnormal sodium is not a sodium problem at all — it is a water problem. Hyponatremia usually means too much water relative to salt; hypernatremia usually means too little water relative to salt. If you fix that idea in place now, the management logic follows without memorisation: dilute sodium is treated by removing water, concentrated sodium is treated by adding water.
Because sodium sets the osmolality of the extracellular fluid, sodium disorders are brain disorders. When serum sodium falls, extracellular fluid becomes hypotonic relative to brain cells, water moves into neurons and the brain swells inside a rigid skull. When sodium rises, water is pulled out of neurons and the brain shrinks, tearing bridging veins in severe cases. Every major manifestation of a sodium disorder — headache, confusion, lethargy, seizure, coma — is a consequence of the size of the brain cell.
Hyponatremia
Hyponatremia is sodium below 135 mEq/L. The common causes on a medical-surgical floor are the syndrome of inappropriate antidiuretic hormone (SIADH, seen with small-cell lung cancer, head injury, pneumonia, and drugs such as SSRIs and carbamazepine), heart failure and cirrhosis (where total body water is high but effective circulating volume is low), excessive hypotonic intravenous fluid, adrenal insufficiency, and gastrointestinal losses replaced with plain water. Thiazide diuretics deserve special mention. They are not a cause of SIADH; they act at the distal tubule and impair the kidney’s ability to dilute urine while causing mild volume depletion, and by that separate mechanism they produce hyponatremia far more often than loop diuretics do.
Symptoms track both the level and the speed of the fall. Above 130 mEq/L most patients are asymptomatic. Between 125 and 130 you see headache, nausea, malaise and muscle cramps. Below 125 you see confusion, lethargy and diminished deep tendon reflexes. Below 120, or with any rapid drop, expect seizures, respiratory arrest and coma. Chronic hyponatremia is far better tolerated than acute, because the brain exports osmoles over days to protect itself — and that adaptation is exactly why correcting it too fast is dangerous.
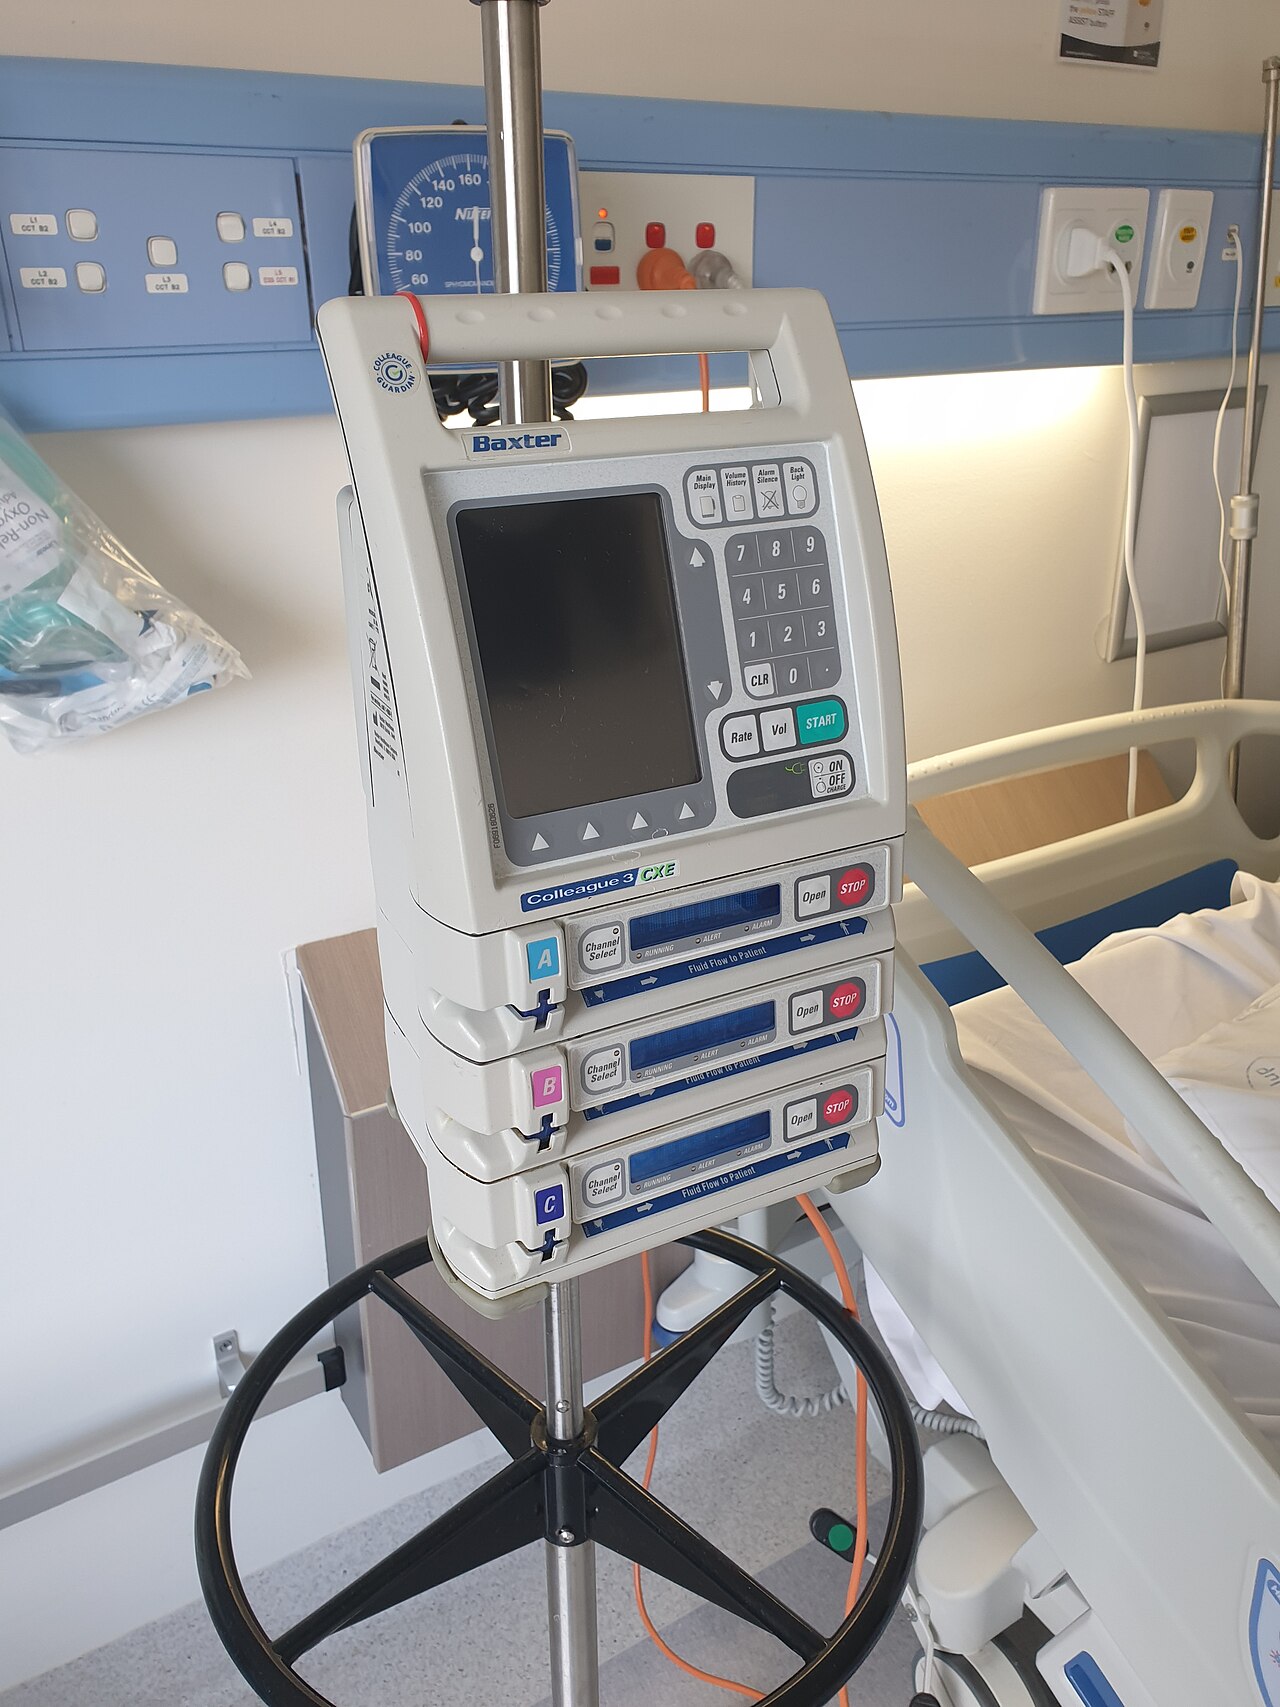
Management depends on volume status and on symptoms. In hypervolemic hyponatremia (heart failure, cirrhosis — edematous, weight up) and in euvolemic hyponatremia (SIADH, where the patient looks neither dry nor overloaded) the treatment is fluid restriction, commonly 800 to 1000 mL per day, with a loop diuretic in the hypervolemic patient or a vasopressin antagonist such as tolvaptan. In hypovolemic hyponatremia the treatment is isotonic 0.9% sodium chloride. For severe symptomatic hyponatremia — seizing, obtunded — the treatment is small-volume 3% hypertonic saline, given through a pump, ideally through a central line, with the patient on continuous monitoring and serum sodium drawn every two to four hours.
The rule that keeps your patient out of a wheelchair: do not raise the serum sodium faster than about 8 to 10 mEq/L in any 24-hour period (many institutions cap it at 8, and lower still in high-risk patients such as those with alcohol use disorder, malnutrition or hypokalemia). Correcting faster causes osmotic demyelination syndrome — formerly central pontine myelinolysis — a delayed, largely irreversible injury producing dysarthria, dysphagia, quadriparesis and locked-in syndrome. Seizure precautions, neurologic checks and hourly documentation of the infusion rate are nursing responsibilities, not the pharmacy’s.
Hypernatremia
Hypernatremia is sodium above 145 mEq/L, and it almost always means a water deficit in a patient who cannot obtain water: the tube-fed patient without free-water flushes, the intubated patient, the patient with dementia, the patient with diabetes insipidus passing litres of dilute urine with a specific gravity below 1.005, the patient on osmotic diuresis from hyperglycaemia, and the patient who received hypertonic saline or excessive sodium bicarbonate.
Manifestations are thirst (if the patient can perceive and express it), dry sticky mucous membranes, a swollen dry tongue, restlessness progressing to agitation, twitching, hyperreflexia, seizures and coma. Note that hypernatremic patients are often agitated rather than lethargic, which fools people into calling for a sedative when they need water. Serum osmolality is high, above 295 mOsm/kg.
Treatment is water, given orally or enterally when possible and as a hypotonic intravenous solution such as 0.45% sodium chloride or D5W when not. The same caution applies in reverse: lower the sodium no faster than about 0.5 mEq/L per hour, or 10 to 12 mEq/L in 24 hours, because a brain that has adapted to a hypertonic environment will swell if you rehydrate it abruptly. Cerebral edema and seizures during correction of hypernatremia are the mirror image of osmotic demyelination. Nursing care includes oral hygiene every two hours, free-water flushes with tube feeds, and offering fluids on a schedule to patients who no longer feel thirst.
| Finding | Hyponatremia (below 135) | Hypernatremia (above 145) |
|---|---|---|
| Mechanism | Water excess relative to sodium; brain cells swell | Water deficit relative to sodium; brain cells shrink |
| Neurologic | Headache, confusion, lethargy, seizure, coma | Thirst, restlessness, agitation, twitching, seizure, coma |
| Reflexes | Diminished | Hyperactive |
| Mucous membranes | Variable; may be moist | Dry, sticky; tongue dry and furrowed |
| Typical cause | SIADH, heart failure, thiazides, hypotonic IV fluid | Inadequate water intake, tube feeds without flushes, diabetes insipidus |
| Treatment | Fluid restriction; 3% saline only if severely symptomatic | Water orally or enterally; 0.45% NaCl or D5W IV |
| Correction limit | Raise no more than 8 to 10 mEq/L in 24 h (osmotic demyelination) | Lower no more than 10 to 12 mEq/L in 24 h (cerebral edema) |
Potassium: the rhythm electrolyte
Serum potassium is normally 3.5 to 5.0 mEq/L, and that narrow window contains only about two percent of the body’s potassium — the rest is intracellular. A small movement across the membrane therefore produces a large change in the serum number and a large change in the resting membrane potential of cardiac muscle. Potassium is the electrolyte that kills quickly, in both directions, and it is the one you will be asked about most.
Hypokalemia (below 3.5 mEq/L) comes from loop and thiazide diuretics, vomiting, nasogastric suction, diarrhoea, laxative abuse, corticosteroids, hyperaldosteronism, poor intake, insulin therapy and alkalosis (which drives potassium into cells). The findings are of a hyperpolarised, sluggish neuromuscular system — a low extracellular potassium makes the resting membrane potential more negative, so the cell sits further from threshold and is harder to excite: fatigue, generalised weakness that starts in the legs, leg cramps, diminished deep tendon reflexes, decreased bowel sounds and paralytic ileus, shallow respirations from weak respiratory muscles, orthostatic hypotension, and on the monitor a flattened or inverted T wave, ST depression and a prominent U wave. Two clinical dangers deserve emphasis: severe hypokalemia can produce respiratory muscle failure, and hypokalemia dramatically potentiates digoxin toxicity even at therapeutic digoxin levels (0.5 to 2.0 ng/mL). Treatment is oral potassium when the patient can swallow and the deficit is mild, and diluted intravenous potassium when it is not. Always check the magnesium: hypokalemia that will not correct is hypomagnesemia until proven otherwise.
Hyperkalemia (above 5.0 mEq/L) comes from kidney injury and chronic kidney disease above all, then from potassium-sparing diuretics such as spironolactone, ACE inhibitors and angiotensin receptor blockers, tissue destruction (crush injury, burns, rhabdomyolysis, tumour lysis, massive haemolysis), acidosis, and iatrogenic over-replacement. A haemolysed specimen is a common false positive — if the value does not fit the patient, redraw before you treat, but do not delay treatment in a patient who looks sick or has ECG changes. Findings are muscle weakness progressing to flaccid paralysis, paraesthesias, hyperactive bowel sounds with diarrhoea and abdominal cramping, and the sequence on the monitor that you must know cold: tall peaked T waves, then a prolonged PR interval with flattened or absent P waves, then a widened QRS, then a sine wave, then ventricular fibrillation or asystole.
Treatment of hyperkalemia is layered, and the order tells you the priority. First, stabilise the myocardium with intravenous calcium gluconate (commonly 10 mL of a 10% solution over 2 to 3 minutes with continuous cardiac monitoring). This does not lower the potassium at all — it raises the threshold potential and buys you thirty to sixty minutes. Second, shift potassium into cells with regular insulin 10 units IV accompanied by 25 g of dextrose (onset 15 to 30 minutes, lasting 4 to 6 hours — check blood glucose hourly), high-dose nebulised albuterol, and sodium bicarbonate if the patient is acidotic. Third, remove potassium from the body with a loop diuretic if the kidneys work, with a gastrointestinal binder such as sodium polystyrene sulfonate, patiromer or sodium zirconium cyclosilicate, or definitively with haemodialysis. Stop all potassium sources — the IV fluid, the salt substitute, the supplement, the lactated Ringer’s.
A sodium disorder is a brain problem corrected slowly, and a potassium disorder is a heart problem corrected immediately — and in hyperkalemia calcium protects the heart without lowering the potassium at all.
Section 3Calcium, Magnesium and Phosphorus
Calcium and neuromuscular excitability
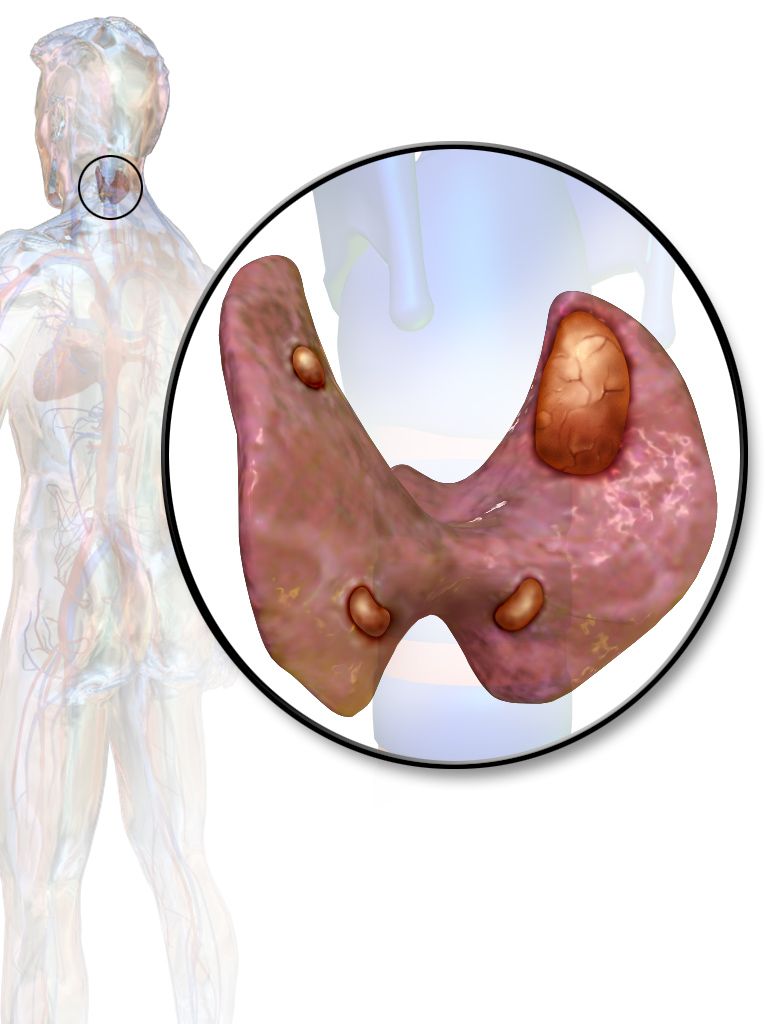
Total serum calcium is normally 8.5 to 10.5 mg/dL, and ionised (free, physiologically active) calcium is 4.5 to 5.6 mg/dL. Roughly half of circulating calcium is bound to albumin, so a hypoalbuminaemic patient will show a low total calcium while the ionised fraction is perfectly normal. Correct it before you panic: add 0.8 mg/dL to the total calcium for every 1 g/dL that albumin sits below 4.0 g/dL. In critically ill patients, order the ionised calcium and skip the arithmetic. Calcium is regulated by parathyroid hormone (which raises it by pulling from bone, reabsorbing it in the kidney and activating vitamin D), by calcitonin (which lowers it), and by vitamin D (which absorbs it from the gut).
Calcium stabilises the neuronal membrane. Less calcium therefore means a twitchier membrane and more calcium means a sleepier one, which is the entire clinical picture in one sentence. Hypocalcemia (below 8.5 mg/dL) causes circumoral and digital numbness and tingling, muscle cramps, hyperactive reflexes, tetany, laryngospasm and stridor, bronchospasm, seizures and a prolonged QT interval that can degenerate into torsades de pointes. Two classic bedside signs: Chvostek sign is a facial twitch when you tap over the facial nerve just anterior to the ear, and Trousseau sign is carpopedal spasm when a blood pressure cuff is inflated 20 mmHg above systolic for three minutes. Trousseau is the more specific of the two.
Causes of hypocalcemia are surgical (thyroidectomy or parathyroidectomy with inadvertent parathyroid injury — watch the first 24 to 48 hours), chronic kidney disease, vitamin D deficiency, acute pancreatitis, massive transfusion with citrated blood, and alkalosis, which increases albumin binding and drops the ionised fraction even when the total is unchanged. That is why a hyperventilating patient gets tingly fingers. Treatment is oral calcium with vitamin D for chronic cases and intravenous calcium gluconate given slowly with continuous cardiac monitoring for acute symptomatic cases. After thyroid surgery keep calcium gluconate and a tracheostomy tray at the bedside and assess the voice and the airway every time you enter the room.
Hypercalcemia (above 10.5 mg/dL) is most often caused by malignancy — bone metastases and paraneoplastic parathyroid hormone-related peptide — or by primary hyperparathyroidism; add thiazides, prolonged immobility, and excessive supplements. Remember it as stones, bones, groans, moans and thrones: renal calculi, bone pain and pathologic fracture, abdominal pain and constipation, lethargy and psychiatric changes, and polyuria from a nephrogenic diabetes insipidus effect. The ECG shows a shortened QT interval. Treatment begins with aggressive isotonic 0.9% sodium chloride to restore volume and promote urinary excretion, then calcitonin for a rapid but short-lived drop, then a bisphosphonate such as zoledronic acid, which works well but takes 48 to 72 hours. Stop thiazides, stop calcium and vitamin D supplements, mobilise the patient, and use dialysis for refractory or renal-failure cases.
Magnesium: the electrolyte nobody checks until it is too late
Serum magnesium is normally 1.5 to 2.5 mEq/L (about 1.8 to 3.0 mg/dL depending on your laboratory’s units — always read the units on the report). Magnesium is a cofactor for hundreds of enzymes and a regulator of both potassium and calcium handling. Its manifestations parallel calcium almost exactly: low magnesium makes membranes irritable, high magnesium makes them sluggish.
Hypomagnesemia (below 1.5 mEq/L) is common in alcohol use disorder, malnutrition and refeeding, prolonged diarrhoea or nasogastric suction, diuretic therapy, proton pump inhibitors and some chemotherapy agents. Findings are tremor, hyperactive reflexes, positive Chvostek and Trousseau signs, muscle cramps, confusion, and dysrhythmias — notably a prolonged QT and torsades de pointes. The critical nursing insight is that hypomagnesemia causes refractory hypokalemia and refractory hypocalcemia. If you have replaced potassium three times and it will not budge, the magnesium is low. Replace magnesium first and the potassium follows.
Hypermagnesemia (above 2.5 mEq/L) is nearly always iatrogenic or renal: magnesium-containing antacids and laxatives in a patient with chronic kidney disease, or magnesium sulfate infusion in obstetric care. The progression is orderly and therefore easy to monitor. First the deep tendon reflexes disappear — check the patellar reflex before and during any magnesium infusion. Then come flushing, warmth, hypotension, bradycardia, lethargy, and finally respiratory depression and cardiac arrest. Any patient on a magnesium infusion needs hourly reflexes, a respiratory rate of at least 12, a urine output of at least 30 mL/hr, and calcium gluconate at the bedside as the antidote. Stop the infusion and call if reflexes are lost.
Phosphorus and the calcium seesaw
Serum phosphorus is normally 2.5 to 4.5 mg/dL, and it moves inversely with calcium: when one rises the other falls. Phosphorus is essential for ATP, for 2,3-DPG in red cells and for the phospholipid membrane, so its deficiency shows up as weakness in every energy-hungry tissue.
Hypophosphatemia (below 2.5 mg/dL) appears in refeeding syndrome, alcohol use disorder, diabetic ketoacidosis treatment, respiratory alkalosis, and with prolonged use of phosphate-binding antacids. Manifestations are muscle weakness including diaphragmatic weakness that can prevent ventilator weaning, bone pain, confusion, and in severe cases haemolysis and cardiomyopathy. Refeeding syndrome is the version you will meet on a medical-surgical floor: a chronically malnourished patient is fed, insulin surges, and phosphorus, potassium and magnesium all plunge into cells within 24 to 72 hours. Advance nutrition slowly and check electrolytes daily.
Hyperphosphatemia (above 4.5 mg/dL) is essentially a marker of chronic kidney disease. Its own symptoms are minimal; the trouble comes from the reciprocal hypocalcemia it produces (tetany) and from calcium-phosphate deposition in soft tissue, vessels and joints. Treatment is dietary phosphorus restriction — dairy, cola, processed meats, nuts — and phosphate binders given with meals, not between them. Calcium acetate, sevelamer and lanthanum all work by binding dietary phosphorus in the gut, so a binder taken an hour after eating has nothing to bind. That timing point is a favourite examination item and a genuine reason for treatment failure.
| Electrolyte | Reference range | Low: hallmark signs | High: hallmark signs |
|---|---|---|---|
| Sodium | 135 to 145 mEq/L | Confusion, seizure, diminished reflexes | Thirst, agitation, dry furrowed tongue |
| Potassium | 3.5 to 5.0 mEq/L | Weakness, ileus, flat T wave, U wave | Weakness, diarrhoea, peaked T wave, wide QRS |
| Calcium (total) | 8.5 to 10.5 mg/dL | Tetany, Chvostek, Trousseau, long QT | Stones, bones, groans, lethargy, short QT |
| Magnesium | 1.5 to 2.5 mEq/L | Tremor, hyperreflexia, torsades de pointes | Loss of deep tendon reflexes, respiratory depression |
| Phosphorus | 2.5 to 4.5 mg/dL | Muscle and diaphragm weakness, confusion | Few direct signs; tetany from reciprocal low calcium |
Low calcium and low magnesium make membranes irritable (tetany, seizures, torsades) and high levels make them sluggish (lethargy, absent reflexes, respiratory depression) — and refractory hypokalemia is a magnesium problem until you prove otherwise.
Section 4Acid-Base Balance and Arterial Blood Gas Interpretation
The buffer, the lung and the kidney
Arterial pH is held between 7.35 and 7.45, a range so narrow that a pH of 7.20 or 7.60 is a medical emergency. Three systems defend it. Chemical buffers — bicarbonate, phosphate, protein and haemoglobin — act in seconds but have limited capacity. The lungs act in minutes by changing the rate and depth of ventilation, blowing off carbon dioxide (an acid) or retaining it. The kidneys act over hours to days by excreting hydrogen ions and reclaiming or generating bicarbonate; they are slow but nearly limitless.
The four numbers you need from an arterial blood gas are pH 7.35 to 7.45, PaCO2 35 to 45 mmHg (the respiratory value, an acid), HCO3 22 to 26 mEq/L (the metabolic value, a base) and PaO2 80 to 100 mmHg with an SaO2 of 95 to 100 percent (oxygenation, which is a separate question from acid-base). Base excess, normally negative 2 to positive 2, is a supporting metabolic number. Draw the specimen from an artery, apply firm pressure for at least five minutes afterward (twenty minutes if the patient is anticoagulated), and get it to the laboratory without air bubbles for analysis within about fifteen minutes. Ice the specimen only if that window cannot be met, because delay and air both falsify the result, and routinely icing a plastic syringe falsely raises the PaO2.
A method you can do in ninety seconds
Use ROME: Respiratory Opposite, Metabolic Equal. In a respiratory disorder, the pH and the PaCO2 move in opposite directions. In a metabolic disorder, the pH and the HCO3 move in the same direction. That is the whole rule.
Run it as three steps. Step one: look at the pH. Below 7.35 is acidosis, above 7.45 is alkalosis, and inside the range is either normal or fully compensated. Step two: look at the PaCO2 and the HCO3, and decide which one is abnormal in the direction that would explain the pH. If the PaCO2 explains it, the disorder is respiratory; if the HCO3 explains it, the disorder is metabolic. Step three: look at the other value to judge compensation — if it has not moved, the disorder is uncompensated; if it has moved in the compensating direction but the pH is still abnormal, it is partially compensated; if the pH has returned to normal while both values remain abnormal, it is fully compensated.
The tic-tac-toe method is the same logic drawn on paper, and it is faster once you have practised it. Draw a grid with three columns labelled ACID, NORMAL and BASE. Down the left side write pH, then CO2, then HCO3. Place each value in the column its own number belongs to: for pH, acid is below 7.35 and base is above 7.45; for CO2, acid is above 45 and base is below 35 (because carbon dioxide is an acid, high is acidic); for HCO3, acid is below 22 and base is above 26 (because bicarbonate is a base, low is acidic). Now look at what lines up. Whichever value shares a column with the pH is the primary disorder. If the third value is in the opposite column, it is compensating. If the third value is in the normal column, there is no compensation yet.
Work an example. A 34-year-old with diabetic ketoacidosis: pH 7.21, PaCO2 26 mmHg, HCO3 10 mEq/L. Step one, pH 7.21 is acidosis. Step two, the PaCO2 of 26 is low, which would be alkalotic, so it cannot be the cause; the HCO3 of 10 is low, which is acidic, and it matches — so this is a metabolic acidosis. Step three, the PaCO2 has dropped well below normal in the opposite direction, which is the lung trying to blow off acid, but the pH is still 7.21, so this is partially compensated metabolic acidosis. The deep rapid breathing you observe at the bedside has a name: Kussmaul respirations. Do not sedate it and do not give this patient an opioid — that respiratory drive is keeping him alive.
Work a second. A 71-year-old with COPD found drowsy: pH 7.30, PaCO2 62 mmHg, HCO3 30 mEq/L. pH is acidotic. The PaCO2 of 62 is high, and high carbon dioxide is acid, so it matches: respiratory acidosis. The HCO3 of 30 is elevated in the compensating alkaline direction, but the pH is still low, so it is partially compensated respiratory acidosis. Now a third, the same patient two days later: pH 7.37, PaCO2 60 mmHg, HCO3 34 mEq/L. The pH is normal but both other values are abnormal, so this is fully compensated respiratory acidosis — and because the pH is on the acidic half of normal (below 7.40), the respiratory value is the primary problem. That last trick — using which half of the normal range the pH sits in — identifies the primary disorder in every fully compensated gas.
The four disorders as you will meet them
Respiratory acidosis is a ventilation failure: retained carbon dioxide from COPD exacerbation, opioid or sedative overdose, neuromuscular disease, chest wall trauma, atelectasis, obesity hypoventilation or an obstructed airway. The patient is dyspnoeic, drowsy, headachy, flushed and eventually somnolent, with a rising PaCO2 and a falling pH. Priority is airway and ventilation: position upright, improve gas exchange, reverse the opioid with naloxone if that is the cause, and support ventilation non-invasively or invasively. Bicarbonate is not the answer — the lung is.
Respiratory alkalosis is over-ventilation: anxiety and panic, pain, fever, early sepsis, pulmonary embolism, high altitude, salicylate toxicity, or a ventilator set too aggressively. The patient reports light-headedness, circumoral and digital tingling, and carpopedal spasm from the fall in ionised calcium. Never assume anxiety. A patient hyperventilating for the first time after hip surgery is having a pulmonary embolism until you rule it out. Treat the cause, coach slow breathing, and reduce the ventilator rate or tidal volume where relevant.
Metabolic acidosis is either acid gained or bicarbonate lost. Acid gained shows a high anion gap: diabetic ketoacidosis, lactic acidosis from shock or sepsis, kidney failure, and toxic ingestions such as methanol, ethylene glycol and salicylates. Bicarbonate lost shows a normal gap: severe diarrhoea, high-output ileostomy, pancreatic fistula, and renal tubular acidosis. Calculate the anion gap as sodium minus the sum of chloride and bicarbonate; normal is 8 to 12 mEq/L (using chloride 98 to 106 mEq/L). Treat the cause — insulin and fluids for ketoacidosis, perfusion for lactic acidosis, dialysis for uraemia — and reserve bicarbonate for severe acidaemia, usually a pH below 7.10, because it generates carbon dioxide and can worsen intracellular acidosis. Watch potassium closely: acidosis pushes potassium out of cells, so the serum potassium looks high even when total body potassium is depleted, and it will fall sharply as you correct the acidosis.
Metabolic alkalosis is either acid lost or base gained: protracted vomiting, prolonged nasogastric suction, loop and thiazide diuretics, hyperaldosteronism, excessive antacid or bicarbonate administration, and massive citrate load from transfusion. The patient shows tingling, tremor, hypertonic reflexes, tetany and dysrhythmias, and there is almost always a coexisting hypokalemia and hypochloremia. Treatment is 0.9% sodium chloride to replace chloride, potassium chloride to replace potassium, and correction of the cause — antiemetics, an appropriate irrigant for the nasogastric tube (isotonic saline, never plain water), and a review of diuretic dosing.
| Disorder | pH | PaCO2 (35 to 45) | HCO3 (22 to 26) | Classic bedside picture |
|---|---|---|---|---|
| Respiratory acidosis | Low | High (primary) | Normal, or high if compensating | COPD exacerbation, opioid overdose, drowsy and dyspnoeic |
| Respiratory alkalosis | High | Low (primary) | Normal, or low if compensating | Anxiety, pain, early sepsis, pulmonary embolism, tingling fingers |
| Metabolic acidosis | Low | Normal, or low if compensating | Low (primary) | DKA with Kussmaul breathing, shock, renal failure, diarrhoea |
| Metabolic alkalosis | High | Normal, or high if compensating | High (primary) | Vomiting, NG suction, diuretics, tremor and tetany |
Respiratory Opposite, Metabolic Equal — find the value that moves with the pH to name the primary disorder, then read the other value to grade compensation, and remember that the lung compensates in minutes while the kidney takes days.
Section 5Intravenous Therapy, Safe Replacement and Nursing Priorities
Choosing the fluid
Intravenous solutions are classified by their tonicity relative to plasma, and that single property determines where the water ends up. Isotonic solutions stay in the extracellular space and expand the intravascular volume without shifting water into or out of cells: 0.9% sodium chloride (308 mOsm/L) and lactated Ringer’s (273 mOsm/L). These two are the fluids of resuscitation, of hypovolemia, of vomiting and diarrhoea, and of the hypotensive post-operative patient. D5W (252 mOsm/L) is the trap here. It is isotonic only inside the bag; the dextrose is metabolised within minutes and what remains is free water that distributes across total body water, so only about a twelfth of the infused volume stays in the vessels. D5W therefore behaves as a hypotonic fluid, does not expand the intravascular space, and must never be given for volume resuscitation or for hypotension — it will fail to restore perfusion and will drop the serum sodium while it fails. Note two further cautions: lactated Ringer’s contains 4 mEq/L of potassium, so avoid it in hyperkalemia and in significant renal failure, and its lactate is converted to bicarbonate by the liver, so it is a poor choice in severe hepatic failure. Only 0.9% sodium chloride may be hung with blood products.
Hypotonic solutions — 0.45% sodium chloride (154 mOsm/L), 0.33% sodium chloride, and D5W once the dextrose is metabolised — have fewer particles than plasma, so water moves out of the vessels and into cells. They treat cellular dehydration and hypernatremia, and they are used after the initial resuscitation phase of diabetic ketoacidosis. They are dangerous in anyone with cerebral edema, head injury or stroke, because they swell the brain, and they can worsen hypotension because they do not stay in the vascular space.
Hypertonic solutions — 3% sodium chloride, 5% sodium chloride, D5 in 0.9% NaCl, D5 in lactated Ringer’s, D10W and parenteral nutrition — pull water out of cells into the vascular space. They are used for severe symptomatic hyponatremia and for cerebral edema, and increasingly concentrated solutions require a central line because of vein damage. Their risks are fluid overload, pulmonary edema and cell shrinkage, so infuse them on a pump, assess lung sounds frequently, and follow serum sodium on the schedule ordered. Colloids raise oncotic pressure and pull fluid in from the interstitium; albumin is used in hypoalbuminaemia, large-volume paracentesis and some burn protocols, and the nurse watches for volume overload and, rarely, allergic reaction. Hydroxyethyl starch appears in older textbooks but is no longer recommended for volume resuscitation, because trials in critically ill and septic patients showed more acute kidney injury, more bleeding and higher mortality.
| Tonicity | Examples | Water moves | Use it for | Watch for |
|---|---|---|---|---|
| Isotonic | 0.9% NaCl, lactated Ringer’s | Stays in extracellular space | Hypovolemia, haemorrhage, vomiting and diarrhoea, blood administration (0.9% only) | Fluid overload; LR has K 4 mEq/L, avoid in hyperkalemia |
| Hypotonic | 0.45% NaCl, 0.33% NaCl, D5W after metabolism | Into the cells | Cellular dehydration, hypernatremia, later phase of DKA | Cerebral edema; never in head injury or stroke; hypotension |
| Hypertonic | 3% NaCl, D5NS, D5LR, D10W, TPN | Out of cells into vessels | Severe symptomatic hyponatremia, cerebral edema, nutrition | Fluid overload, pulmonary edema, phlebitis; pump and frequent sodium levels |
| Colloid | Albumin (hydroxyethyl starch no longer recommended) | Interstitium into vessels | Low oncotic pressure, paracentesis, some burn protocols | Volume overload, allergic reaction, cost; starches cause kidney injury and bleeding |
Giving potassium safely
Potassium chloride is a high-alert medication and the classic source of fatal nursing error. Learn these rules as absolutes.
Never give potassium by IV push, IM or subcutaneously. Undiluted potassium delivered as a bolus stops the heart in asystole. It is not a matter of a slow push or a small dose; there is no safe way to push it. Potassium is always diluted and always infused. Use commercially premixed bags whenever they exist rather than compounding at the bedside, and if a bag ever must be mixed, invert and agitate it thoroughly, because potassium is dense and will pool at the bottom and be delivered as an accidental bolus. Never add potassium to a bag that is already hanging and infusing.
Always use an electronic infusion pump, never gravity. Standard concentration limits are up to 10 mEq per 100 mL for a peripheral line and up to 20 mEq per 100 mL through a central line, per institutional policy. Standard rate limits are no more than 10 mEq per hour peripherally in a patient without continuous cardiac monitoring, and up to 20 mEq per hour only with central access, continuous ECG monitoring and usually an intensive care setting. Know your facility’s policy and do not exceed it because a provider verbally asks you to.
Assess renal function and urine output before you hang it. The kidney is the only meaningful route of potassium excretion, so confirm the patient is producing at least 30 mL/hr or 0.5 mL/kg/hr and check the most recent creatinine. Recheck the serum potassium after the ordered replacement is complete rather than assuming it worked. Place the patient on a cardiac monitor for any rapid or high-dose replacement, and check the magnesium level, because potassium will not correct in a magnesium-depleted patient.
Expect burning and act on it. Potassium irritates veins; pain at the site is common and is not itself an emergency, but it demands a response: assess for infiltration first, then slow the rate, increase the dilution, apply a warm compress, and discuss central access for continued therapy. If the site is cool, swollen, blanched or leaking, stop the infusion, disconnect the tubing while leaving the catheter in place to attempt aspiration, notify the provider, elevate the limb and follow your infiltration protocol. Oral potassium is equally irritating in a different way — give it with a full glass of water or with food, never on an empty stomach, and never crush an extended-release tablet.
Complications of infusion therapy
Infiltration is the leak of a non-vesicant solution into surrounding tissue: swelling, coolness, pallor, discomfort and a sluggish or absent flow. Extravasation is the same event with a vesicant such as a vasopressor, concentrated potassium or many chemotherapy agents, and it causes tissue necrosis. For both, stop the infusion immediately, leave the catheter in place until you have attempted aspiration and considered an antidote, notify the provider, elevate the extremity, and document the site, the volume and the appearance. Phlebitis is inflammation of the vein — redness, warmth, tenderness and a palpable cord along the vein. Discontinue the line, apply warm compresses, and restart in the opposite extremity.
Circulatory overload is the complication that will find you on a busy shift. Signs are dyspnoea, new crackles, a cough that may be productive of frothy sputum, distended neck veins, tachycardia, a rising blood pressure and a falling oxygen saturation. Act in this order: slow the infusion to a keep-vein-open rate rather than stopping it entirely and losing the access, raise the head of the bed, apply oxygen, take a full set of vital signs, and notify the provider — anticipating an order for a loop diuretic. Air embolism presents with sudden dyspnoea, chest pain, hypotension and often a churning murmur; clamp the catheter, place the patient on the left side in Trendelenburg to trap air in the right ventricular apex, give high-flow oxygen and call rapid response. Catheter-related bloodstream infection is prevented by hand hygiene, scrubbing the hub for at least fifteen seconds, aseptic dressing changes and prompt removal of lines nobody needs.
Priorities, delegation, the older adult and teaching
When two problems compete, use the standard hierarchy and use it out loud. Airway, breathing, circulation comes first, so a patient with new crackles and a saturation of 88 percent outranks a patient with a potassium of 3.1. Within circulation, a lethal rhythm risk outranks a stable abnormal value, so a potassium of 6.8 with peaked T waves outranks a sodium of 129 in a comfortable patient. Acute outranks chronic, so a sodium that fell from 138 to 126 overnight outranks a sodium that has been 128 for a year. Unstable outranks stable, and actual outranks potential. When a question asks what you do first and both options are reasonable, ask which patient dies sooner if you get it wrong.
Delegate deliberately. The UAP may obtain and record daily weights, measure and record intake and output, provide oral care, assist with ambulation and toileting, offer scheduled oral fluids, take routine vital signs on a stable patient and report findings to you. The UAP may not assess, interpret, teach or evaluate. The LPN or LVN may, within state scope and facility policy, administer many oral and intramuscular medications, monitor a stable patient receiving an established infusion, perform sterile dressing changes, reinforce teaching you have already provided, and collect focused data. The RN retains the initial and ongoing assessment, the plan of care, all intravenous push medications, the initiation and titration of high-alert infusions including potassium and hypertonic saline, blood product initiation, patient teaching, evaluation of response, and every unstable patient. Delegating a task never delegates the accountability.
The older adult deserves a separate paragraph because the presentation genuinely differs. Total body water falls toward 50 percent or less; thirst sensation blunts, so a dehydrated eighty-year-old may not ask for a drink; the kidney loses concentrating ability and the glomerular filtration rate declines, so both dehydration and overload arrive faster; skin turgor is unreliable and must be checked over the sternum or forehead; and polypharmacy — diuretics, ACE inhibitors, NSAIDs, laxatives, proton pump inhibitors — multiplies risk. Most importantly, the first sign is frequently acute confusion rather than any classic symptom. New delirium in an older patient should prompt a basic metabolic panel, not a sedative. Older adults also tolerate rapid infusion poorly, so the same litre of saline that helps a young adult can put a frail patient into pulmonary edema in an hour.
Teaching closes the loop. Patients on fluid restriction need the daily allowance divided across the day, ice chips counted as half their volume, and hard candy or lemon swabs for thirst. Patients on diuretics need to weigh themselves daily at the same time and call for a gain of 2 to 3 pounds in a day or 5 pounds in a week. Patients on ACE inhibitors, angiotensin receptor blockers or potassium-sparing diuretics need to know that salt substitutes are potassium chloride and are not safe for them. Patients on potassium supplements need to take them with food and water and to report muscle weakness, palpitations or persistent gastrointestinal upset. Patients on phosphate binders need them with meals. Every patient going home on a diuretic should be told the signs of dehydration and the signs of overload, in plain words, before they leave.
| Red flag | Why it matters | What you do first |
|---|---|---|
| Potassium above 6.0, or any level with peaked T waves or wide QRS | Imminent ventricular fibrillation or asystole | Cardiac monitor, stop all potassium sources, call provider by SBAR, anticipate calcium gluconate |
| Potassium below 2.5, or weakness with shallow respirations | Respiratory muscle failure and lethal dysrhythmia | Assess respiratory effort, monitor, notify provider, prepare diluted IV replacement |
| Sodium below 120 or a fall greater than 10 mEq/L in 24 hours | Cerebral edema and seizure | Seizure precautions, neurologic checks, notify provider, prepare 3% saline per order |
| Stridor, hoarseness or tetany after thyroid or neck surgery | Acute hypocalcemia with laryngospasm | Assess airway, apply oxygen, call rapid response, calcium gluconate and trach tray at bedside |
| Absent deep tendon reflexes or respiratory rate below 12 on magnesium | Hypermagnesemia progressing to respiratory arrest | Stop the infusion, support ventilation, call provider, calcium gluconate is the antidote |
| New crackles, dyspnoea and falling SpO2 during an infusion | Circulatory overload and pulmonary edema | Slow to keep-vein-open, sit the patient up, oxygen, vital signs, notify provider |
| pH below 7.20 on an arterial blood gas | Severe acidaemia with myocardial depression | Assess airway and perfusion, notify provider or rapid response immediately |
Tonicity decides where infused water goes, potassium is never pushed and always pumped, and when two problems compete you treat the one that stops breathing or stops the heart first.
The chapter in one breath
Water follows sodium, and sodium is the reason a patient becomes confused rather than merely thirsty. Two thirds of body water is inside cells and only a small fraction is in the vessels, so intravascular losses hurt fast: tachycardia first, then orthostatic hypotension, then oliguria below 0.5 mL/kg/hr, with a rising haematocrit and a BUN-to-creatinine ratio above 20 to 1. Fluid excess announces itself through the stethoscope as crackles, and the scale — one kilogram equals one litre equals 2.2 pounds — is more honest than any intake and output sheet. Learn five ranges by heart: sodium 135 to 145, potassium 3.5 to 5.0, calcium 8.5 to 10.5, magnesium 1.5 to 2.5, phosphorus 2.5 to 4.5. Sodium disorders are brain problems corrected slowly, no more than 8 to 10 mEq/L in 24 hours, because faster correction causes osmotic demyelination. Potassium disorders are heart problems corrected now, and in hyperkalemia calcium stabilises the myocardium while insulin and dextrose shift and binders or dialysis remove. Low calcium and low magnesium make membranes irritable; high levels make them sluggish. For gases, use ROME — Respiratory Opposite, Metabolic Equal — then grade compensation. Choose isotonic fluid to fill the vessels, hypotonic to hydrate cells, hypertonic to pull water in. And potassium is never, under any circumstance, given IV push.
Words worth knowing
| Term | What it means |
|---|---|
| Osmolality | Concentration of dissolved particles in a fluid; serum normal 275 to 295 mOsm/kg, driven mostly by sodium, glucose and urea. |
| Tonicity | The effect a solution has on cell volume; isotonic leaves cells unchanged, hypotonic swells them, hypertonic shrinks them. |
| Hydrostatic pressure | The outward push of blood against the capillary wall that drives fluid into the interstitium; raised in heart failure and fluid overload. |
| Oncotic pressure | The inward pull generated mainly by albumin (3.5 to 5.0 g/dL) that holds fluid inside the vessel; lost in cirrhosis and nephrotic syndrome. |
| Third spacing | Shift of fluid into a non-functional compartment such as the peritoneum or interstitium, producing edema with functional hypovolemia. |
| SIADH | Syndrome of inappropriate antidiuretic hormone; excess ADH causes water retention, dilutional hyponatremia and concentrated urine. |
| Diabetes insipidus | Deficient ADH or renal resistance to it, producing large volumes of dilute urine, hypernatremia and a urine specific gravity below 1.005. |
| Osmotic demyelination syndrome | Irreversible brainstem injury from correcting hyponatremia faster than roughly 8 to 10 mEq/L in 24 hours; formerly central pontine myelinolysis. |
| U wave | A small deflection after the T wave on the ECG, classically prominent in hypokalemia along with a flattened T wave and ST depression. |
| Peaked T wave | The earliest ECG sign of hyperkalemia, followed by loss of the P wave, a widened QRS, sine wave and cardiac arrest. |
| Chvostek sign | Twitching of the facial muscles when the facial nerve is tapped anterior to the ear; suggests hypocalcemia or hypomagnesemia. |
| Trousseau sign | Carpopedal spasm after a blood pressure cuff is inflated 20 mmHg above systolic for three minutes; a more specific sign of hypocalcemia. |
| Tetany | Sustained involuntary muscle contraction from neuromuscular irritability, seen in hypocalcemia, hypomagnesemia and alkalosis. |
| Torsades de pointes | A polymorphic ventricular tachycardia associated with a prolonged QT interval; classically precipitated by hypomagnesemia. |
| Anion gap | Sodium minus the sum of chloride and bicarbonate, normally 8 to 12 mEq/L; a high gap points to added acid such as ketones or lactate. |
| Kussmaul respirations | Deep, rapid, laboured breathing that blows off carbon dioxide to compensate for severe metabolic acidosis, typically in ketoacidosis. |
| Compensation | The opposing system correcting the pH — the lung in minutes, the kidney over days; full compensation returns the pH to normal with both values still abnormal. |
| Refeeding syndrome | Sharp falls in phosphorus, potassium and magnesium within 24 to 72 hours of feeding a chronically malnourished patient; prevented by advancing nutrition slowly. |
| Extravasation | Leakage of a vesicant infusion into surrounding tissue causing necrosis; requires immediate stopping of the infusion and provider notification. |
| SBAR | Situation, Background, Assessment, Recommendation — the structured format for urgent clinical communication. |