Adaptive Immunity & Immunization
Your innate defenses are fast, but they are blunt — they treat every microbe the same and they never learn. Adaptive immunity is the opposite: slow to start, exquisitely precise, and blessed with memory. It is the arm of the immune system that recognizes one specific microbe out of millions, mounts a tailored attack, and then remembers that microbe for years or a lifetime. This chapter follows the two great cell lineages that make it work — T cells and B cells — explains how antibodies are built and what they do, and shows why a second exposure is so much faster than the first. That last fact is the whole reason vaccines work, so we finish where nursing practice lives: the immunizations you will draw up, document, and defend to families.
By the end of this chapter you can
- Contrast innate and adaptive immunity, and name the three hallmarks of the adaptive response: specificity, memory, and self-tolerance.
- Define antigen and epitope, and explain what it means to distinguish self from non-self.
- Distinguish helper (CD4) from cytotoxic (CD8) T cells and describe the role of MHC molecules in showing antigen to them.
- Describe how a B cell becomes a plasma cell, and diagram the basic antibody structure.
- List the five antibody classes and the main jobs antibodies do — neutralization, opsonization, agglutination, and complement activation.
- Compare the primary and secondary antibody responses and explain immunologic memory.
- Classify immunity as active or passive and natural or artificial, and match each to a clinical example.
- Describe the major vaccine types and the nursing implications of live versus non-live vaccines.
Section 1The adaptive response
Two systems, one defense
Your immune system runs on two teams that work together. Innate immunity — skin, mucus, stomach acid, fever, phagocytes, and inflammation — is present from birth, responds within minutes to hours, and reacts the same way to almost any invader. It buys time. Adaptive immunity is the specialist team called in behind it. It takes days to gear up the first time, but it recognizes one particular microbe with extraordinary precision, and once the fight is over it keeps a record so that the next encounter is faster and stronger. Nearly everything protective about a vaccine, a childhood illness you never catch twice, and a positive antibody titer comes from this second system.
Adaptive immunity itself splits into two branches. The humoral (antibody-mediated) response is run by B lymphocytes, which secrete antibodies into blood and body fluids to attack microbes outside of cells — bacteria in the bloodstream, toxins, viruses in transit. The cell-mediated response is run by T lymphocytes, which handle threats inside cells, especially virus-infected cells and cancer cells. Both branches begin when the body detects something foreign.
Antigens, epitopes, and the meaning of “foreign”
An antigen is any molecule the immune system can recognize and respond to — usually a protein or polysaccharide on the surface of a microbe. Adaptive cells do not read the whole antigen at once; each one recognizes a small, specific patch called an epitope. A single bacterium carries many different epitopes, which is why one infection can trigger many different lymphocytes at the same time. The precision here is staggering: your body pre-builds millions of different lymphocytes, each tuned to a different epitope, before it has ever met the microbe. When a matching antigen shows up, the rare lymphocyte that fits it is selected and told to multiply — a process called clonal selection.
Specificity, memory, and tolerance
Three properties define adaptive immunity. Specificity means each response is aimed at one antigen and not its neighbors — measles immunity does nothing for mumps. Memory means the system remembers a past antigen and reacts faster and harder on re-exposure; this is the property vaccines exploit. Self-tolerance means the system learns, during development, to ignore the body's own molecules (self) while attacking foreign ones (non-self). Lymphocytes that would attack self are normally deleted or silenced early on. When that quality-control step fails, the immune system turns on the body — the basis of autoimmune disease such as type 1 diabetes, rheumatoid arthritis, and lupus.
| Feature | Innate immunity | Adaptive immunity |
|---|---|---|
| Present when? | From birth, always ready | Develops after exposure to an antigen |
| Speed | Minutes to hours | Days on first exposure |
| Specificity | Broad — same response to many microbes | Exquisite — one antigen at a time |
| Memory? | No — reacts the same every time | Yes — faster & stronger on re-exposure |
| Key cells | Phagocytes, NK cells, mast cells | T lymphocytes and B lymphocytes |
- Innate immunity is fast and non-specific; adaptive immunity is slower, highly specific, and remembers.
- Adaptive immunity has two arms: humoral (B cells, antibodies, extracellular threats) and cell-mediated (T cells, intracellular threats).
- An antigen is recognized at a small patch called an epitope; clonal selection multiplies the lymphocyte that fits.
- The three hallmarks are specificity, memory, and self-tolerance; loss of tolerance causes autoimmunity.
Section 2T cells

Where T cells come from and how they “see”
T lymphocytes are born in the bone marrow but finish their training in the thymus (the T is for thymus), where the dangerous ones — those that would attack self — are weeded out. A mature T cell cannot recognize a free-floating antigen the way an antibody can. It only reacts to antigen that has been chopped up and displayed on a special surface molecule called MHC (major histocompatibility complex). Think of MHC as a serving tray: a cell holds up a fragment of protein on its MHC, and a passing T cell inspects it. This is called antigen presentation, and it is the reason T cells can tell an infected cell from a healthy one.
There are two classes of tray. MHC class I is found on almost every nucleated cell in the body and displays fragments of whatever is being made inside — so a virus-infected cell involuntarily advertises the virus. MHC class II is found only on professional antigen-presenting cells (dendritic cells, macrophages, and B cells), which deliberately swallow microbes and display their pieces to recruit help.
Helper T cells — the conductors (CD4)
Helper T cells carry a surface marker called CD4 and read antigen presented on MHC class II. They do not kill anything directly; they orchestrate. When a helper T cell recognizes its antigen, it releases chemical messengers (cytokines) that switch on the rest of the response: they push B cells to make antibody, amplify cytotoxic T cells, and rev up macrophages. Because they sit at the center of the network, losing them is catastrophic — which is exactly what makes HIV so devastating.
Cytotoxic T cells — the assassins (CD8)
Cytotoxic T cells carry CD8 and read antigen on MHC class I. When one recognizes a cell displaying foreign (viral or tumor) protein on its class I tray, it delivers the kill: it punches holes in the target and triggers it to self-destruct (apoptosis), taking the virus factory down with it. This is the front line against viral infections and abnormal cells. A handy memory aid is the “rule of eight”: CD4 × MHC II = 8, and CD8 × MHC I = 8 — each T-cell type pairs with the MHC class whose number multiplies to eight.
| Feature | Helper T cell | Cytotoxic T cell |
|---|---|---|
| Surface marker | CD4 | CD8 |
| Reads antigen on | MHC class II | MHC class I |
| Main job | Coordinate & amplify the response via cytokines | Directly kill infected or abnormal cells |
| Best against | Directing all responses (works with B cells too) | Virus-infected cells, tumor cells |
| Clinical note | Target of HIV; count tracks immune status | Key defense in viral illness |
- T cells mature in the thymus and recognize antigen only when it is presented on MHC.
- Helper T cells (CD4) read MHC II and coordinate the response with cytokines; they do not kill directly.
- Cytotoxic T cells (CD8) read MHC I and destroy infected or abnormal cells.
- MHC I is on nearly all cells; MHC II is only on antigen-presenting cells. HIV depletes CD4 cells, crippling adaptive immunity.
Section 3B cells & antibodies
From B cell to antibody factory
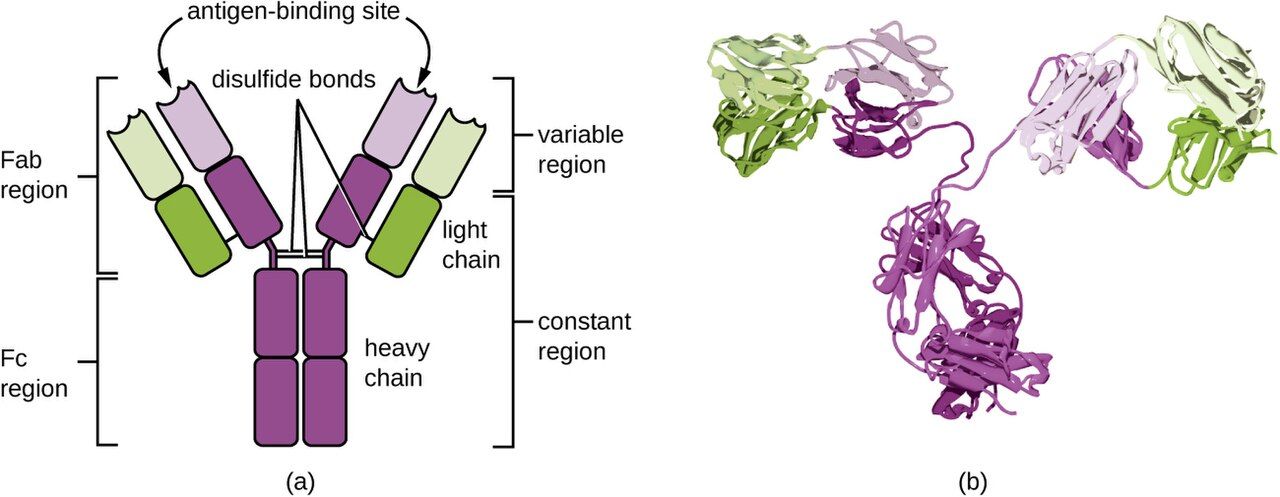
B lymphocytes mature in the bone marrow (a helpful coincidence: B for bone marrow). Each B cell carries a unique receptor on its surface, and when that receptor binds its matching antigen — usually with a push from a helper T cell — the B cell activates and divides. Most of its offspring become plasma cells, short-lived factories that pump out thousands of identical antibodies per second. A smaller share become memory B cells that linger for years, ready for a repeat encounter (the subject of the next section). Antibodies are also called immunoglobulins (Ig), and they are the working product of the humoral response.
Antibody structure: the Y
Every antibody has the same basic shape: a Y built from four protein chains — two identical long heavy chains and two identical short light chains, held together by disulfide bonds. The two tips of the Y are the variable regions: their amino-acid sequence differs from antibody to antibody, giving each its unique antigen-binding site. The stem of the Y is the constant region, which is the same within a class and acts as a handle that other immune components — phagocytes and complement proteins — can grab. So one end of the molecule does the recognizing and the other end does the recruiting.
What antibodies actually do
Antibodies rarely destroy a microbe by themselves. Instead they tag and disable it in four main ways. In neutralization, antibodies coat a virus or toxin so it can no longer attach to host cells — this is how antitoxins and many vaccine antibodies protect. In opsonization, antibodies coat a microbe so phagocytes grab it more easily (the constant stem is the “handle”). In agglutination, antibodies cross-link many microbes into clumps that are easier to clear and can no longer spread. And in complement activation, clustered antibodies trigger the complement cascade, which can punch holes in bacterial membranes. The five classes below differ in their constant stems, and therefore in where they go and what they do.
| Class | Where / role | Clinical pearl |
|---|---|---|
| IgG | Most abundant in blood; long-term protection; crosses the placenta | Signals a past or resolved infection / established immunity; protects the newborn |
| IgM | First antibody made in a new infection; large, stays in blood | A positive IgM suggests a current or recent infection |
| IgA | Guards mucous membranes & secretions; found in breast milk | Passes protection to the breastfeeding infant's gut |
| IgE | Binds mast cells; drives allergy & parasite defense | The antibody behind hay fever and anaphylaxis |
| IgD | On the surface of naive B cells | Helps activate the B cell; least understood clinically |
- B cells mature in bone marrow; activated B cells become antibody-secreting plasma cells and long-lived memory B cells.
- An antibody is a Y: variable tips recognize antigen; the constant stem recruits phagocytes and complement.
- Antibodies work by neutralization, opsonization, agglutination, and complement activation.
- The five classes are IgG, IgM, IgA, IgE, IgD; remember IgM = new infection, IgG = past/lasting, IgA = mucosa/milk, IgE = allergy.
Section 4Primary vs secondary response
The primary response: slow and costly
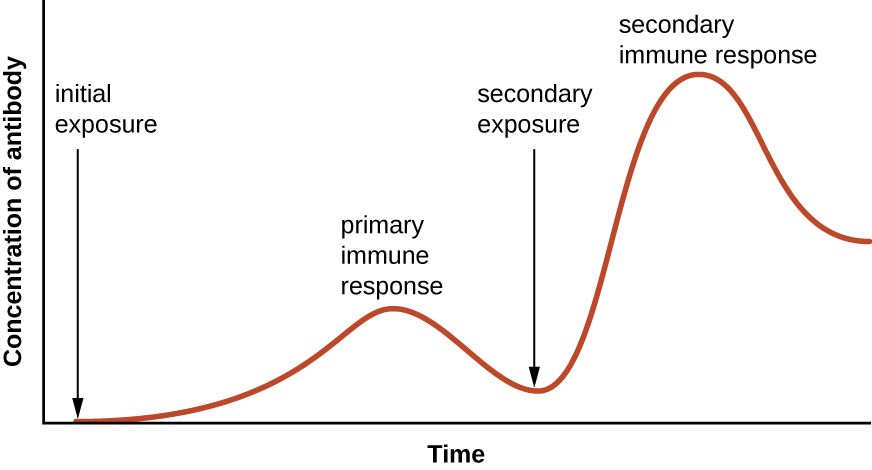
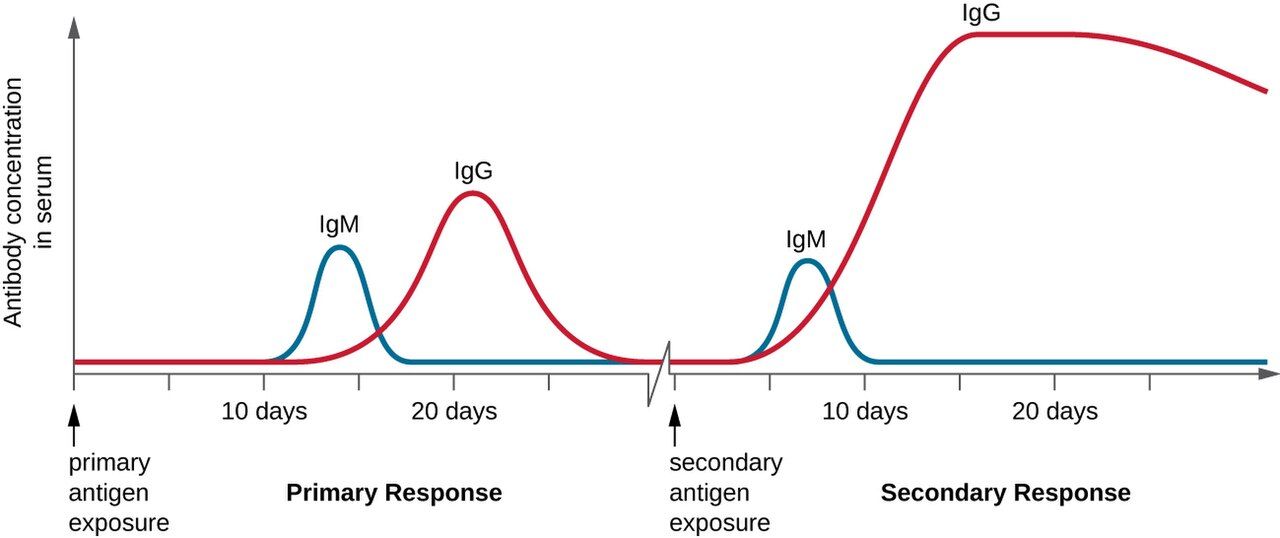
The first time the body meets a new antigen, it must find the one rare lymphocyte that fits, activate it, and let it multiply before any meaningful defense appears. This primary response has a lag of roughly one to two weeks, produces a modest amount of antibody, and is led by IgM, the first-responder class, before IgG builds up. During that lag the patient is often sick — the immune system is fighting from behind. This delay is exactly why a brand-new infection can be dangerous and why an unvaccinated person has no head start.
Memory cells: the immune system's notebook
As the primary response resolves, it does not simply pack up. It leaves behind memory B cells and memory T cells — long-lived cells, sometimes surviving for decades, that carry the receptor for that one antigen. They circulate quietly, primed. Memory is the physical basis of immunity: it is what “having had” a disease or a vaccine actually means at the cellular level.
The secondary response: fast and fierce
When the same antigen returns, memory cells are already waiting, so the body skips most of the search-and-activate delay. The secondary response begins in hours to a few days, produces far more antibody, and is dominated by high-affinity IgG. Often the microbe is cleared before symptoms even appear — which is why you may never know you were re-exposed. Every booster shot deliberately triggers a secondary response to push antibody levels back up and refresh the memory pool.
| Feature | Primary response | Secondary response |
|---|---|---|
| Trigger | First exposure to the antigen | Re-exposure to the same antigen |
| Lag before antibody | ~1–2 weeks | Hours to a few days |
| Amount of antibody | Low | Much higher |
| Dominant class | IgM first, then IgG | Mostly high-affinity IgG |
| Driven by | Naive lymphocytes | Memory B and T cells |
- The primary response is slow (1–2 week lag), small, and IgM-first.
- Memory B and T cells persist for years and are the physical basis of lasting immunity.
- The secondary response is faster, larger, and IgG-dominant — often clearing the microbe before symptoms appear.
- Boosters and titers both work through this memory: one refreshes it, the other measures it.
Section 5Immunization & vaccines

Four kinds of immunity
Clinical immunity is sorted along two axes. The first is active versus passive: in active immunity the person's own immune system makes the antibody and builds memory (long-lasting); in passive immunity ready-made antibody is given to the person, protecting them immediately but only until that borrowed antibody breaks down (no memory). The second axis is natural versus artificial: natural means it happened through ordinary life, artificial means it was delivered deliberately by a clinician. Crossing the two axes gives four categories, and every immunization you handle fits one of them.
| Type | How it happens | Example | Lasting? |
|---|---|---|---|
| Natural active | You catch the illness and recover | Immunity after chickenpox | Yes — memory forms |
| Artificial active | A vaccine teaches your immune system | MMR, hepatitis B, tetanus vaccine | Yes — memory forms |
| Natural passive | Antibody given by nature | Mother's IgG across placenta; IgA in breast milk | No — wears off in months |
| Artificial passive | Pre-made antibody injected | Antivenom, rabies/tetanus immune globulin, RhoGAM | No — temporary |
How vaccines are built
All vaccines do the same job — show the immune system an antigen so it builds memory — but they differ in how they present it, and that difference drives the nursing precautions. Live attenuated vaccines (MMR, varicella, oral polio, intranasal flu) use a weakened but living microbe; they give strong, long-lasting immunity but are generally contraindicated in pregnancy and in immunocompromised patients because even a weakened live microbe can be risky. Inactivated (killed) vaccines (hepatitis A, injectable polio, most flu shots) use a dead microbe — safer, but often needing boosters. Subunit, conjugate, and toxoid vaccines (hepatitis B, Hib, pertussis, tetanus and diphtheria toxoids) use only a purified piece or an inactivated toxin, so they cannot cause the disease at all. mRNA and viral-vector vaccines deliver the genetic instructions for a single antigen so the body makes it briefly and learns to recognize it. None of the non-live types can give the patient the actual infection.
Herd immunity and the nurse's role
When a high enough share of a community is immune, a microbe can no longer find enough susceptible hosts to spread — this is herd immunity, and it shelters the few who cannot be vaccinated (newborns, the immunocompromised, those with true contraindications). Nurses are central to keeping that number high: you administer vaccines by the correct route, observe for the rare immediate reaction, document the lot number and site, and — often most important — you answer families' questions with accurate, calm information. Vaccine hesitancy is met at the bedside far more effectively than in a headline.
- Active immunity = the body makes its own antibody & memory (lasting); passive = borrowed antibody, immediate but temporary.
- Natural vs artificial is simply whether it happened through life or was delivered by a clinician — giving four categories.
- Vaccine types: live attenuated, inactivated, subunit/conjugate/toxoid, and mRNA/vector; only live types carry an infection risk in vulnerable hosts.
- Live vaccines are generally contraindicated in pregnancy and immunocompromise; herd immunity protects those who cannot be vaccinated.
The chapter in one breath
- Adaptive immunity is slow but specific and remembers; its arms are humoral (B cells/antibodies) and cell-mediated (T cells).
- Its hallmarks are specificity, memory, and self-tolerance; lost tolerance causes autoimmunity.
- T cells read antigen on MHC: helper (CD4) cells coordinate via cytokines; cytotoxic (CD8) cells kill infected cells. HIV destroys CD4 cells.
- B cells become plasma cells that secrete antibodies — Y-shaped, with variable tips that recognize and a constant stem that recruits.
- Antibodies work by neutralization, opsonization, agglutination, and complement; classes are IgG, IgM, IgA, IgE, IgD.
- The secondary response is faster and stronger than the primary thanks to memory cells — the basis of boosters and titers.
- Immunity is active/passive and natural/artificial; vaccines create artificial active immunity, and live vaccines are avoided in pregnancy and immunocompromise.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Active immunity
- Protection produced by the person's own immune system making antibody and memory; long-lasting.
- Adaptive immunity
- The specific, memory-forming arm of the immune system, run by T and B lymphocytes.
- Antibody (immunoglobulin)
- A Y-shaped protein made by plasma cells that binds a specific antigen to tag or neutralize it.
- Antigen
- Any molecule the immune system can recognize and respond to; recognized at a small patch called an epitope.
- Antigen-presenting cell (APC)
- A cell (dendritic cell, macrophage, or B cell) that displays antigen on MHC class II to activate helper T cells.
- Attenuated vaccine
- A vaccine using a living but weakened microbe; strong immunity but avoided in pregnancy and immunocompromise.
- CD4 (helper) T cell
- A T cell that reads antigen on MHC II and coordinates the immune response with cytokines; target of HIV.
- CD8 (cytotoxic) T cell
- A T cell that reads antigen on MHC I and kills infected or abnormal cells.
- Clonal selection
- The process by which the one lymphocyte matching an antigen is chosen and multiplied.
- Epitope
- The small, specific portion of an antigen that a lymphocyte or antibody actually binds.
- Herd immunity
- Protection of a whole community, including the non-immune, when enough members are immune to stop spread.
- Humoral immunity
- The antibody-mediated branch of adaptive immunity, driven by B cells; fights extracellular threats.
- Immunologic memory
- The persistence of memory cells that make a repeat response faster and stronger.
- Memory cell
- A long-lived B or T lymphocyte that persists after infection and enables the secondary response.
- MHC (major histocompatibility complex)
- Surface molecules that display antigen fragments to T cells; class I on most cells, class II on APCs.
- Opsonization
- Coating a microbe with antibody so phagocytes engulf it more readily.
- Passive immunity
- Protection from ready-made antibody given to the person; immediate but temporary, with no memory.
- Plasma cell
- An activated B cell that secretes large amounts of antibody.
- Primary response
- The slow, modest, IgM-first reaction to a first exposure to an antigen.
- Secondary response
- The fast, large, IgG-dominant reaction to re-exposure, driven by memory cells.
- Self-tolerance
- The immune system's learned ability to ignore the body's own molecules; its failure causes autoimmunity.
- Toxoid vaccine
- A vaccine made from an inactivated bacterial toxin, e.g., tetanus and diphtheria toxoids.