Vitamins
Vitamins are the smallest thing on your plate that can change everything about how you feel. They supply no energy at all — zero kilocalories per gram, against carbohydrate's 4, protein's 4, fat's 9, and alcohol's 7 — yet without milligram and microgram quantities of thirteen specific organic compounds, blood will not clot, collagen will not hold, nerves will not conduct, and red cells will not mature. That is the paradox worth sitting with: a nutrient can be needed in vanishing amounts and still be non-negotiable. This chapter walks through the two families of vitamins, what each one actually does inside a cell, the classic deficiency syndromes that taught us they existed, and where the evidence for supplementation is strong versus where it is thin. Along the way you will learn to read a Recommended Dietary Allowance properly — which population, which units, and when the number shifts with age, sex, or pregnancy.
By the end of this chapter you can
- Define a vitamin as an organic micronutrient and explain why vitamins yield no energy.
- Separate the fat-soluble (A, D, E, K) from the water-soluble (B complex and C) vitamins and predict how solubility affects absorption, storage, and toxicity risk.
- State the principal function, food sources, deficiency syndrome, and toxicity picture for vitamins A, D, E, and K.
- Describe the coenzyme role of the B vitamins and match each to its classic deficiency disease.
- Explain vitamin C's role in collagen hydroxylation and iron absorption, and recognize scurvy.
- Read an RDA, AI, or UL correctly, naming the population, units, and life-stage adjustments.
- Describe factors that change bioavailability, including food matrix, dietary fat, and cooking method.
- Distinguish strong from preliminary evidence when evaluating a single-nutrient supplement claim.
Section 1What vitamins are
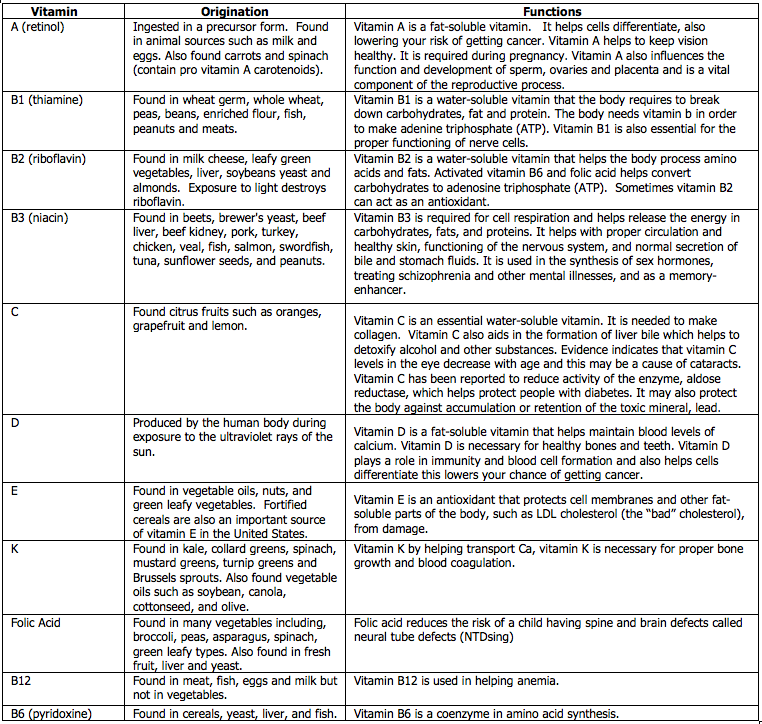
Organic, essential, and needed in tiny amounts
A vitamin is an organic compound — carbon-containing, built by a living thing — that the human body requires in small amounts, cannot make at all (or cannot make enough of), and must therefore obtain from the diet. Each of those clauses does work. Organic separates vitamins from minerals such as calcium, iron, and zinc, which are single elements and cannot be destroyed by heat or light. Small amounts puts them in the micronutrient category: intakes are measured in milligrams (mg) or micrograms (µg) per day, not the tens or hundreds of grams we use for the macronutrients. Essential means that if intake falls low enough for long enough, a specific and reproducible deficiency disease appears — and resolving the deficiency resolves the disease. That last criterion is how each vitamin was discovered.
A common point of confusion: vitamins do not provide energy. Only three macronutrients and one non-nutrient do. Carbohydrate yields about 4 kcal per gram, protein about 4 kcal per gram, fat about 9 kcal per gram, and alcohol about 7 kcal per gram. Vitamins yield 0 kcal per gram. What they do instead is make energy release possible: several B vitamins are built into the coenzymes that run glycolysis, the citric acid cycle, and the electron transport chain. A vitamin does not add fuel to the fire; it is part of the machinery that burns the fuel. That is why "vitamins for energy" is a marketing phrase rather than a physiological one — correcting a genuine deficiency can restore energy dramatically, while adding more vitamin on top of adequacy does not.
Two nuances keep the definition honest. First, humans can make some vitamin D in skin exposed to ultraviolet B radiation, and gut bacteria contribute some vitamin K and biotin — so "cannot be synthesized" is a near-rule rather than an absolute one. Second, a handful of compounds sit at the edge of the category: choline, for example, has an Adequate Intake (550 mg/day for adult men, 425 mg/day for adult women) and is essential, but is usually classed separately because the body synthesizes a meaningful fraction of it.
The two families, and why solubility decides everything
Thirteen compounds are recognized as vitamins for humans, and they divide cleanly by what they dissolve in. The four fat-soluble vitamins — A, D, E, and K — travel with dietary fat, need bile and pancreatic lipase for efficient absorption, get packaged into chylomicrons for transport in lymph, and are stored in the liver and adipose tissue. The nine water-soluble vitamins — the eight B vitamins plus vitamin C — dissolve in the watery interior of foods and of the body, are generally absorbed directly into portal blood, are stored only in small amounts, and are excreted in urine when intake exceeds need.
From that one physical property, a whole set of clinical predictions follows. Fat-soluble vitamins accumulate, so deficiency takes months to years to appear but toxicity (hypervitaminosis) is a real hazard from concentrated supplements. Water-soluble vitamins turn over quickly, so deficiency can develop in weeks to months and intake needs to be regular — but excess is mostly excreted, which makes toxicity less common. "Less common" is not "impossible," and Section 5 covers the important exceptions. One more consequence: anything that impairs fat digestion — cystic fibrosis, cholestatic liver disease, bariatric surgery, untreated celiac disease, some fat-blocking medications — puts the fat-soluble vitamins at risk long before it touches the water-soluble ones.
| Property | Fat-soluble (A, D, E, K) | Water-soluble (B complex, C) |
|---|---|---|
| Absorption | Requires dietary fat, bile, micelle formation | Generally direct; some need carriers (B12 needs intrinsic factor) |
| Transport | Chylomicrons and lipoproteins, via lymph | Free or protein-bound in portal blood |
| Storage | Substantial — liver and adipose tissue | Minimal, except vitamin B12 (liver stores last years) |
| Excretion | Poor; excess accumulates | Readily excreted in urine |
| Deficiency onset | Months to years | Weeks to months |
| Toxicity risk | Higher — A and D especially | Lower, but real for B6, niacin, folic acid, vitamin C |
| Cooking losses | Relatively heat-stable; lost with discarded fat | Leached into cooking water; C and thiamin heat-labile |
Reading the reference values
Vitamin recommendations in North America come from the Dietary Reference Intakes (DRIs), and the labels matter. An RDA (Recommended Dietary Allowance) is the intake estimated to meet the needs of about 97–98% of healthy people in a specified life-stage and sex group — it is deliberately generous, and it is a target for individuals, not a minimum below which harm is certain. An AI (Adequate Intake) is used when the evidence is too thin to set an RDA; vitamins K, B5, and B7 all have AIs rather than RDAs. A UL (Tolerable Upper Intake Level) is the highest chronic daily intake unlikely to cause harm — not a goal, a ceiling. Every one of these numbers is meaningless without its population and units, which is why this chapter always states both.
- A vitamin is an organic micronutrient the body needs in mg or µg amounts and largely cannot synthesize.
- Vitamins supply 0 kcal/g; energy comes from carbohydrate (4), protein (4), fat (9), and alcohol (7) kcal/g.
- Fat-soluble vitamins A, D, E, K are stored and can accumulate to toxicity; water-soluble B vitamins and C turn over fast and need regular intake.
- RDA covers ~97–98% of a specified group, AI is used when evidence is limited, and UL is a ceiling — all three are population-specific.
Section 2Fat-soluble vitamins
Vitamin A: vision, epithelium, and the one with a teratogenic ceiling
Vitamin A arrives in two chemically different forms. Preformed vitamin A (retinol and retinyl esters) comes from animal-source foods — liver above all, plus dairy fat, egg yolk, and fortified foods. Provitamin A carotenoids — principally beta-carotene, plus alpha-carotene and beta-cryptoxanthin — come from deeply colored plants such as sweet potato, carrot, pumpkin, mango, and dark leafy greens, and are converted to retinol in the intestinal wall with modest and variable efficiency. Because the two forms are not interchangeable gram for gram, intakes are expressed in retinol activity equivalents (RAE): 1 µg RAE equals 1 µg of retinol, 12 µg of dietary beta-carotene, or 24 µg of the other provitamin A carotenoids.
Functionally, vitamin A does three big jobs. As 11-cis-retinal bound to opsin it forms rhodopsin, the pigment that lets rod cells detect dim light. As retinoic acid it acts as a hormone-like regulator of gene transcription, directing the differentiation of epithelial tissue — skin, cornea, respiratory and gut lining. And it supports immune competence, partly by keeping those epithelial barriers intact. Deficiency therefore starts with night blindness (nyctalopia), progresses to xerophthalmia with drying of the conjunctiva and cornea, Bitot's spots, and eventually keratomalacia and irreversible blindness; it also raises susceptibility to infection. Globally, vitamin A deficiency remains a leading preventable cause of childhood blindness, and randomized trials of supplementation in deficient populations show reduced child mortality — strong trial-based evidence, though the size of the effect varies across trials and appears smallest where deficiency is least common.
Toxicity is the other half of the story and it is genuinely important. The adult UL is 3,000 µg/day of preformed vitamin A. Chronic excess causes liver injury, bone and joint pain, hair loss, dry cracking skin, and raised intracranial pressure. Most consequentially, preformed vitamin A is a teratogen: high supplemental intakes in early pregnancy are associated with birth defects, which is also why the retinoid medications used for severe acne carry pregnancy-prevention requirements. Carotenoids from food behave differently — they are not converted fast enough to cause hypervitaminosis, and very high intakes produce only carotenodermia, a harmless yellow-orange tint to the skin that fades. The RDA for adults is 900 µg RAE/day for men and 700 µg RAE/day for women, rising to 770 µg RAE in pregnancy and 1,300 µg RAE in lactation.
Vitamin D: a hormone that we happen to call a vitamin
Vitamin D is unusual twice over. It can be synthesized in skin, where UVB radiation converts 7-dehydrocholesterol to cholecalciferol (vitamin D3); and it functions as a steroid hormone rather than a coenzyme. The dietary form from fungi, notably UV-exposed mushrooms, is ergocalciferol (vitamin D2); food sources of D3 include oily fish, cod liver oil, egg yolk, and — the largest contributor in many countries — fortified milk and plant milks. Whichever the source, activation takes two steps: the liver adds a hydroxyl group to make 25-hydroxyvitamin D, the circulating storage form measured on a lab report, and the kidney adds another to make 1,25-dihydroxyvitamin D (calcitriol), the active hormone.
Calcitriol's main job is calcium and phosphate economy: it increases intestinal absorption of both, works with parathyroid hormone to maintain serum calcium, and thereby permits normal bone mineralization. Deficiency produces rickets in children — soft, deforming bone with bowed legs, widened wrists, and a beaded costochondral "rachitic rosary" — and osteomalacia in adults, with bone pain and proximal muscle weakness. Risk rises with limited sun exposure, higher skin melanin (which lengthens the UVB exposure needed), high latitude, clothing coverage, older age, higher body fat (which sequesters vitamin D in adipose tissue), and fat malabsorption; exclusively breastfed infants are routinely given a supplement because human milk is low in vitamin D. The RDA is 15 µg (600 IU)/day for ages 1–70, including pregnancy and lactation, and 20 µg (800 IU)/day for adults over 70; infants have an AI of 10 µg (400 IU)/day. Note the unit conversion, which trips everyone: 1 µg = 40 IU. The adult UL is 100 µg (4,000 IU)/day, and toxicity — hypercalcemia, hypercalciuria, and calcium deposition in kidneys and soft tissue — comes from supplements, never from sunlight, because skin synthesis is self-limiting.
Vitamin D is also a case study in evidence quality. That it prevents and treats rickets and osteomalacia is beyond dispute. The much broader claims — that supplementation in already-replete people prevents cancer, cardiovascular disease, diabetes, or respiratory infection — looked promising in observational studies and then largely failed to hold up in large randomized trials. Treat the skeletal evidence as strong and the extraskeletal evidence as preliminary and mostly negative so far.
Vitamin E and vitamin K
Vitamin E is a family of eight related compounds, but only alpha-tocopherol is retained by the body well enough to meet human requirements, because a hepatic transfer protein selectively loads that form back into circulating lipoproteins. Its role is as the principal lipid-phase antioxidant: it intercepts free radicals inside cell membranes and lipoproteins, protecting polyunsaturated fatty acids from chain-reaction oxidation, and is then regenerated with help from vitamin C. Sources are concentrated in plant fats — sunflower and safflower oil, wheat germ oil, almonds, sunflower seeds, peanuts, avocado, and leafy greens. The adult RDA is 15 mg/day of alpha-tocopherol for both men and women, rising to 19 mg/day in lactation. Dietary deficiency is rare in healthy people and shows up mainly with severe fat malabsorption or specific genetic disorders, producing peripheral neuropathy, ataxia, myopathy, retinopathy, and hemolytic anemia in premature infants. The UL for supplemental alpha-tocopherol is 1,000 mg/day; high-dose supplements can interfere with vitamin K–dependent clotting, and large trials of high-dose vitamin E have found no cardiovascular benefit and some signals of harm.
Vitamin K exists as phylloquinone (K1), abundant in green leafy vegetables such as kale, spinach, collards, and broccoli and in some plant oils, and as the menaquinones (K2) from fermented foods, some animal foods, and colonic bacteria. Its function is precise: it is the cofactor for gamma-glutamyl carboxylase, the enzyme that carboxylates specific glutamate residues so those proteins can bind calcium. The substrates include clotting factors II, VII, IX, and X plus proteins C and S, and also bone proteins such as osteocalcin and the vessel-wall matrix Gla protein. So the deficiency picture is bleeding — easy bruising, mucosal bleeding, prolonged prothrombin time. There is an AI rather than an RDA: 120 µg/day for adult men and 90 µg/day for adult women, and no UL has been set because toxicity from the natural forms has not been demonstrated. Newborns are the classic at-risk group: placental transfer is limited, human milk is low in vitamin K, and the newborn gut is not yet colonized, which is why a single dose at birth is standard practice to prevent vitamin K deficiency bleeding.
| Vitamin | Core function | Food sources | Deficiency | Toxicity / UL (adults) |
|---|---|---|---|---|
| A (retinol, carotenoids) | Rhodopsin for night vision; epithelial differentiation; immunity | Liver, dairy fat, egg yolk; sweet potato, carrot, greens (carotenoids) | Night blindness → xerophthalmia; infection risk | Yes — liver injury, bone pain, teratogenic; UL 3,000 µg preformed |
| D (calciferol) | Calcium and phosphate absorption; bone mineralization | Oily fish, egg yolk, fortified milk; skin synthesis from UVB | Rickets (children), osteomalacia (adults) | Yes — hypercalcemia; UL 100 µg (4,000 IU) |
| E (alpha-tocopherol) | Lipid-phase antioxidant in membranes | Vegetable oils, nuts, seeds, avocado, greens | Rare; neuropathy, ataxia, hemolysis with malabsorption | Bleeding risk at high dose; UL 1,000 mg supplemental |
| K (phylloquinone, menaquinones) | Carboxylation of clotting factors and bone Gla proteins | Leafy greens, plant oils, fermented foods; gut bacteria | Bleeding, prolonged PT; newborn VKDB | No UL set; natural forms not shown to be toxic |
- Vitamin A: night blindness and xerophthalmia when deficient; preformed retinol is teratogenic in excess (UL 3,000 µg/day); food carotenoids are not.
- Vitamin D: activated in liver then kidney; RDA 15 µg (600 IU)/day ages 1–70, 20 µg (800 IU)/day over 70; deficiency causes rickets and osteomalacia.
- Vitamin E: alpha-tocopherol is the active form; RDA 15 mg/day for adults; deficiency is a malabsorption phenomenon, not a dietary one.
- Vitamin K: carboxylates clotting factors II, VII, IX, X; AI 120 µg/day men, 90 µg/day women; newborns are uniquely at risk.
Section 3The B vitamins
One job description, eight employees
The eight B vitamins are chemically unrelated to one another; they were grouped together historically because they were all water-soluble factors isolated from the same yeast and liver extracts. What unites them functionally is that nearly every one becomes a coenzyme — a small non-protein molecule an enzyme must have bound in order to work. Thiamin becomes thiamin pyrophosphate; riboflavin becomes FAD and FMN; niacin becomes NAD+ and NADP+; pantothenic acid becomes coenzyme A; B6 becomes pyridoxal 5'-phosphate; biotin rides on carboxylase enzymes; folate becomes tetrahydrofolate; and B12 becomes methylcobalamin and adenosylcobalamin. Between them they are required for glycolysis, the citric acid cycle, the electron transport chain, fatty acid synthesis and breakdown, amino acid metabolism, heme synthesis, neurotransmitter synthesis, and the one-carbon transfers that build DNA.
Two practical consequences follow. First, because these coenzymes sit in energy pathways, early B-vitamin deficiency tends to present with fatigue and neurological complaints — but so does almost everything else, which is why the specific syndromes below matter for recognition. Second, because they are water-soluble and stored only briefly, intake must be reasonably regular. Vitamin B12 is the great exception: liver stores can supply several years of need, so deficiency develops insidiously and is often well advanced by the time it is noticed.
The classic deficiency diseases
Thiamin (B1) deficiency causes beriberi. The "wet" form is cardiovascular — high-output heart failure with peripheral edema; the "dry" form is a symmetrical peripheral neuropathy with muscle wasting. In the context of chronic heavy alcohol use, which impairs both intake and absorption, thiamin deficiency produces Wernicke encephalopathy — the triad of confusion, eye-movement abnormalities, and ataxia — which can progress to the largely irreversible memory disorder called Korsakoff syndrome. Adult RDA: 1.2 mg/day for men, 1.1 mg/day for women, rising to 1.4 mg/day in pregnancy and lactation. Historically, beriberi followed the milling of white rice, which strips the thiamin-rich bran.
Riboflavin (B2) deficiency (ariboflavinosis) shows up in the mouth and skin: cracking at the corners of the lips (angular cheilitis), a sore magenta-colored tongue, and seborrheic dermatitis. Adult RDA: 1.3 mg/day for men, 1.1 mg/day for women. Riboflavin is notably light-sensitive, which is why milk is sold in opaque containers.
Niacin (B3) deficiency causes pellagra, remembered as the four Ds: dermatitis (a symmetrical, sun-exposed rash, including the collar-like Casal's necklace), diarrhea, dementia, and, untreated, death. Niacin is partly spared by dietary tryptophan — roughly 60 mg of tryptophan yields 1 mg of niacin — so intakes are expressed as niacin equivalents (NE). Adult RDA: 16 mg NE/day for men, 14 mg NE/day for women. Pellagra devastated the American South in the early twentieth century among people eating maize-based diets, until Joseph Goldberger's field studies showed it was a dietary deficiency rather than an infection; traditional nixtamalization of maize with alkali, long practiced in Mesoamerica, releases the bound niacin and prevents it. The UL of 35 mg/day applies to niacin from supplements and fortified foods, where excess produces cutaneous flushing.
Vitamin B6 deficiency causes a microcytic anemia (heme synthesis stalls), dermatitis, and in severe cases seizures and peripheral neuropathy. RDA: 1.3 mg/day for adults aged 19–50, rising to 1.7 mg/day for men and 1.5 mg/day for women over 50; 1.9 mg/day in pregnancy. B6 is also the one water-soluble vitamin with a well-documented toxicity: sustained intakes above the UL of 100 mg/day can cause a sensory peripheral neuropathy.
Folate (B9) and vitamin B12 are best learned as a pair, because both are required for DNA synthesis in rapidly dividing cells and both produce a megaloblastic (macrocytic) anemia when deficient. Folate's RDA is 400 µg DFE/day for adults, 600 µg DFE/day in pregnancy, and 500 µg DFE/day in lactation — DFE meaning dietary folate equivalents, which adjust for the fact that synthetic folic acid is absorbed better than the folate naturally present in leafy greens, legumes, and liver. The single strongest piece of evidence in this whole chapter is that 400 µg/day of folic acid taken before conception and in early pregnancy substantially reduces neural tube defects; randomized trial evidence and the fall in defect rates after national flour fortification both support it, and the recommendation applies to anyone who could become pregnant because the neural tube closes before most pregnancies are recognized.
Vitamin B12 (RDA 2.4 µg/day for adults, 2.6 µg in pregnancy, 2.8 µg in lactation) is found naturally only in animal-source foods and in fortified foods and supplements — a fact of real importance for anyone eating a vegan diet, who needs a reliable fortified or supplemental source. Its absorption is elaborate: stomach acid and pepsin free it from food protein, intrinsic factor from gastric parietal cells binds it, and the complex is taken up in the terminal ileum. Any break in that chain causes deficiency — autoimmune loss of intrinsic factor (pernicious anemia), atrophic gastritis with low acid (common with age), gastric or ileal surgery, or ileal disease. Beyond anemia, B12 deficiency damages the spinal cord and peripheral nerves — subacute combined degeneration — producing numbness, gait unsteadiness, and cognitive change that may not fully reverse. Two smaller members complete the set: pantothenic acid (B5), AI 5 mg/day for adults, and biotin (B7), AI 30 µg/day for adults; deficiency of either is rare outside unusual circumstances.
| B vitamin | Coenzyme form | Adult reference intake | Deficiency syndrome |
|---|---|---|---|
| B1 Thiamin | Thiamin pyrophosphate (TPP) | RDA 1.2 mg/day men, 1.1 mg/day women | Beriberi (wet, dry); Wernicke–Korsakoff |
| B2 Riboflavin | FAD, FMN | RDA 1.3 mg/day men, 1.1 mg/day women | Angular cheilitis, glossitis, dermatitis |
| B3 Niacin | NAD+, NADP+ | RDA 16 mg NE/day men, 14 mg NE/day women | Pellagra — dermatitis, diarrhea, dementia, death |
| B5 Pantothenic acid | Coenzyme A | AI 5 mg/day | Very rare; paresthesias |
| B6 Pyridoxine | Pyridoxal 5'-phosphate (PLP) | RDA 1.3 mg/day (19–50); 1.7 men / 1.5 women (51+) | Microcytic anemia, dermatitis, neuropathy, seizures |
| B7 Biotin | Bound to carboxylases | AI 30 µg/day | Rare; rash, hair loss, neurologic signs |
| B9 Folate | Tetrahydrofolate (THF) | RDA 400 µg DFE/day; 600 µg in pregnancy | Megaloblastic anemia; neural tube defects |
| B12 Cobalamin | Methyl- and adenosylcobalamin | RDA 2.4 µg/day; 2.6 µg in pregnancy | Megaloblastic anemia plus neurologic damage |
- Nearly every B vitamin functions as a coenzyme in energy, amino acid, or DNA metabolism — they enable energy release but supply none.
- Classic pairings: thiamin–beriberi and Wernicke–Korsakoff; niacin–pellagra (4 Ds); folate and B12–megaloblastic anemia.
- 400 µg/day of folic acid periconceptionally prevents neural tube defects — among the strongest single-nutrient findings in nutrition.
- B12 occurs naturally only in animal foods and requires intrinsic factor; deficiency causes anemia plus potentially irreversible neurologic injury.
Section 4Vitamin C
What ascorbate actually does
Vitamin C (ascorbic acid) is a water-soluble vitamin that humans, other primates, guinea pigs, and a few other species must eat because we all carry a broken copy of the gene for L-gulonolactone oxidase, the final enzyme in the synthetic pathway that most mammals still use. Its chemistry is simple — it is a reducing agent, an electron donor — but the consequences are wide.
The best-defined role is in collagen synthesis. The enzymes prolyl hydroxylase and lysyl hydroxylase modify proline and lysine residues in procollagen, and those hydroxyl groups are what allow the triple helix to cross-link and hold tension. Both enzymes need iron in its reduced state, and vitamin C is what keeps it there. Without ascorbate, collagen is made but is structurally weak — which explains almost every sign of scurvy, since collagen is the scaffolding of skin, blood vessel walls, gums, tendon, and bone matrix. Vitamin C is also required for the synthesis of carnitine (which shuttles fatty acids into mitochondria) and of norepinephrine, it acts as a water-phase antioxidant and regenerates oxidized vitamin E, and it markedly enhances absorption of non-heme iron from plant foods by reducing ferric iron to the absorbable ferrous form — a genuinely useful pairing for people relying on beans, lentils, tofu, and fortified grains for iron.
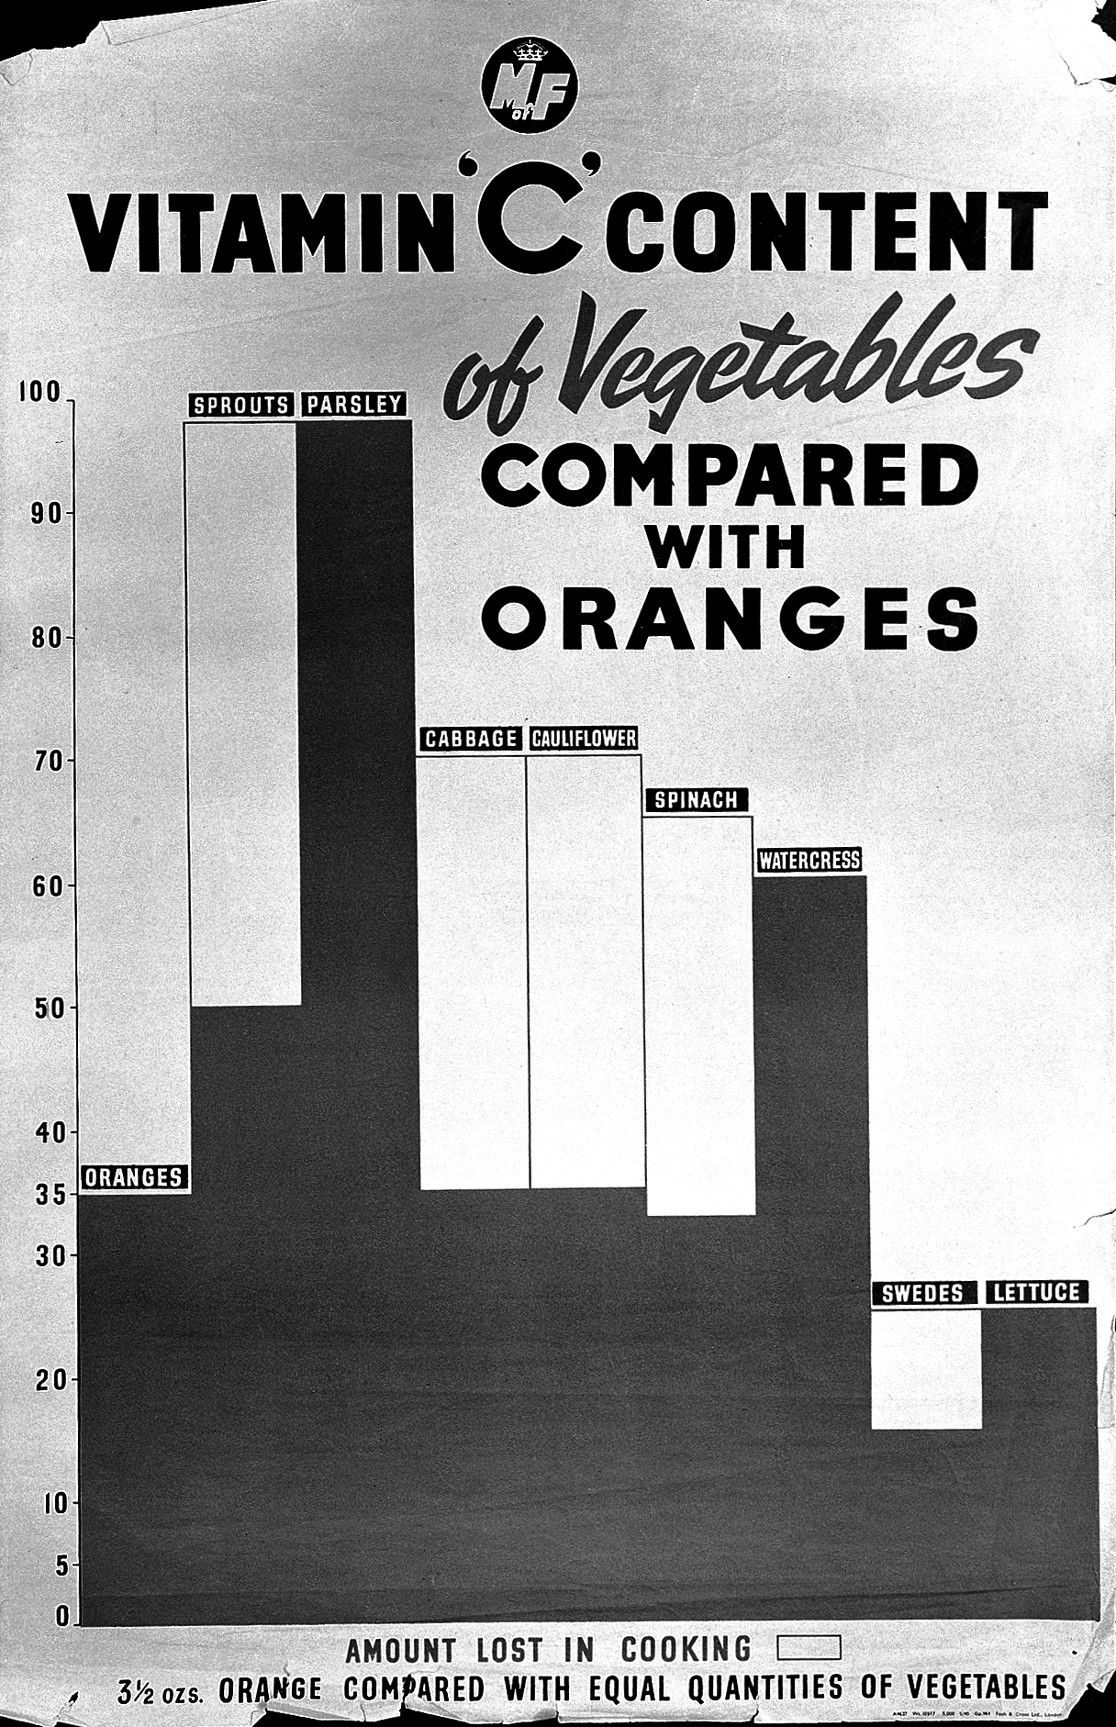
Sources are broader than the citrus stereotype. Per typical serving, sweet peppers, guava, kiwifruit, broccoli, Brussels sprouts, strawberries, papaya, cantaloupe, tomatoes, and potatoes all contribute meaningfully alongside oranges and grapefruit. The adult RDA is 90 mg/day for men and 75 mg/day for women; pregnancy raises it to 85 mg/day and lactation to 120 mg/day, and an additional 35 mg/day is recommended for people who smoke because of higher oxidative turnover. The UL is 2,000 mg/day, above which osmotic diarrhea and gastrointestinal discomfort are common and urinary oxalate rises, which matters for people prone to calcium oxalate kidney stones.
Scurvy, and the first controlled trial
Scurvy is what happens when body ascorbate is depleted, typically after roughly one to three months of near-zero intake. The presentation follows the collagen story exactly: fatigue and irritability first, then perifollicular hemorrhages and distinctive corkscrew-shaped body hairs, swollen bleeding gums with loosening teeth, easy bruising, joint pain and swelling from bleeding into joints, poor wound healing, and the eerie sign of old, long-healed wounds reopening. Anemia is common. In children the growing bone is affected, with painful subperiosteal bleeding. Untreated scurvy was fatal, and repletion reverses it dramatically.
Scurvy is also where clinical nutrition became a science. In 1747, aboard HMS Salisbury, the naval surgeon James Lind took twelve sailors with scurvy, kept their diets otherwise identical, and assigned them in pairs to six different treatments. Only the pair given oranges and lemons recovered. It is one of the first recorded controlled clinical trials, and it worked more than 175 years before the compound responsible was isolated — a reminder that a well-designed comparison can identify a cause long before anyone can explain the mechanism. Scurvy is not merely historical: it still appears today in the context of very restricted eating patterns, severe food insecurity, alcohol use disorder, some psychiatric and neurodevelopmental conditions that narrow food variety, and isolated older adults.
| Feature of scurvy | Underlying mechanism |
|---|---|
| Bleeding, swollen gums; loose teeth | Weak collagen in gingival connective tissue and periodontal ligament |
| Perifollicular hemorrhage; corkscrew hairs | Fragile capillary walls; abnormal keratin and follicle structure |
| Easy bruising, petechiae | Defective collagen in blood vessel basement membrane |
| Poor wound healing; old wounds reopen | New collagen cannot be hydroxylated or cross-linked |
| Joint pain and swelling | Bleeding into joint spaces and periosteum |
| Fatigue; anemia | Impaired carnitine synthesis; blood loss; reduced iron absorption |
- Humans cannot synthesize vitamin C; it is required to hydroxylate proline and lysine in collagen, and for carnitine and norepinephrine synthesis.
- Vitamin C strongly enhances non-heme iron absorption by reducing ferric to ferrous iron.
- RDA 90 mg/day for adult men, 75 mg/day for adult women; +35 mg/day for smokers; UL 2,000 mg/day.
- Scurvy — bleeding gums, perifollicular hemorrhage, poor wound healing — is a collagen failure and still occurs today.
Section 5Vitamins in practice

Bioavailability: what is in the food is not what reaches the cell
Bioavailability is the fraction of an ingested nutrient that is actually absorbed and available for use. A food composition table reports what is in the food; bioavailability determines what you get. Several factors move it. The food matrix matters: carotenoids locked inside intact plant cell walls are poorly released, so chopping, pureeing, and gentle cooking measurably increase carotenoid absorption from carrots and tomatoes — one of the few cases where cooking increases a vitamin's availability rather than decreasing it. Dietary fat matters, as Section 2 covered: A, D, E, and K need it. Chemical form matters: synthetic folic acid is absorbed more completely than natural food folate, which is exactly why intakes are expressed in dietary folate equivalents, and crystalline B12 in fortified foods and supplements does not require stomach acid to release it, which is why fortified sources are more reliable for older adults with reduced acid production. Nutrient interactions matter in both directions: vitamin C boosts non-heme iron uptake, while very high doses of one fat-soluble vitamin can interfere with another.
Losses in storage, prep, and cooking
Vitamins are chemicals, and chemicals degrade. Water-soluble vitamins are lost by two routes — leaching into cooking water and destruction by heat, light, oxygen, or alkaline pH. Vitamin C is the most fragile of all: it is water-soluble, heat-labile, and readily oxidized, so it is often used as the indicator nutrient in cooking studies. Boiling vegetables in a large volume of water and discarding the water causes the largest losses; steaming, microwaving, stir-frying, and roasting retain far more, and any liquid kept and served (as in a soup, stew, or pan sauce) recovers what leached out. Thiamin is destroyed by prolonged heat, by alkaline conditions such as adding baking soda to vegetables or beans, and by sulfite preservatives. Riboflavin is degraded by light. Folate is both heat-sensitive and water-soluble. The fat-soluble vitamins are generally more heat-stable, but they follow the fat — drain the fat and you drain some of the A, D, E, and K with it, and vitamin E is degraded by repeated high-heat frying.
Two practical corrections to common assumptions. First, frozen produce is not nutritionally inferior to fresh. It is typically harvested at peak ripeness and frozen within hours, whereas "fresh" produce may have spent many days in transit and storage losing vitamin C the whole way — frozen often measures equal or higher. Canning involves more heat and more leaching into the packing liquid, though using that liquid recovers some. Second, none of this is a reason to fear cooked food. A cooked vegetable eaten regularly delivers vastly more nutrition than a raw vegetable nobody eats, and cooking improves the availability of carotenoids and the digestibility of many foods. The goal is variety and regularity, not perfection — and no food needs to be described as clean, dirty, or earned.
Supplements: where the evidence is strong, and where it is not
In the United States, dietary supplements are regulated as a category of food rather than as drugs. Manufacturers are responsible for safety and for the truthfulness of their claims, but products are not reviewed or approved for safety or effectiveness before they reach the shelf, and independent testing has repeatedly found products whose contents differ from the label. Voluntary third-party verification programs — USP Verified, NSF Certified for Sport, and similar — test for identity, potency, and contaminants, and a verification mark is a reasonable thing to look for. Note that supplements can interact with medications: high-dose vitamin E with anticoagulants, vitamin K intake variability for someone on warfarin, and high-dose biotin, which interferes with several common laboratory immunoassays (including some troponin and thyroid tests) and can produce misleading results unless the lab is told.
The evidence base is genuinely uneven, and separating its tiers is the most useful thing this section can teach. There are situations where supplementation is strongly supported: folic acid before and during early pregnancy to prevent neural tube defects; vitamin K at birth to prevent hemorrhagic disease of the newborn; vitamin D for exclusively breastfed infants; vitamin B12 from fortified foods or supplements for people eating vegan diets and, commonly, for older adults with reduced gastric acid; vitamin A supplementation for children in populations where deficiency is endemic; and repletion of any diagnosed deficiency. There are also situations where the evidence is preliminary, mixed, or negative: routine multivitamins have not been shown to reduce cardiovascular disease, cancer, or mortality in generally well-nourished adults; large trials of high-dose vitamin E found no cardiovascular benefit; and beta-carotene supplements increased lung cancer incidence in people who smoked or had heavy asbestos exposure, a result replicated in two separate large trials. That last finding is the cautionary tale of the field: an association observed for a food (carotenoid-rich vegetables) did not transfer to an isolated high-dose nutrient, and the isolated nutrient caused harm.
A reasonable summary is that supplements fill gaps; they do not upgrade an already-adequate diet. Whole foods deliver vitamins in the company of fiber, minerals, phytochemicals, and a food matrix that shapes how they are absorbed, and hypervitaminosis from food alone is rare — the notable exception being preformed vitamin A, since liver is concentrated enough that frequent large portions can push intake past the UL. Decisions about whether a specific person needs a specific supplement — and at what amount — belong with a clinician or registered dietitian who knows that person's labs, medications, and circumstances. This chapter describes physiology and evidence; it is general education, not individualized medical or dietary advice.
| Practice | Effect on vitamins | Why |
|---|---|---|
| Boiling and discarding water | Largest losses of vitamin C, thiamin, folate | Water-soluble vitamins leach out and are thrown away |
| Steaming / microwaving | Much better retention | Less contact with water; shorter heating time |
| Adding baking soda to vegetables | Destroys thiamin and vitamin C | Alkaline pH degrades both |
| Chopping and gently cooking carrots, tomatoes | Increases carotenoid availability | Breaks plant cell walls, releasing carotenoids |
| Adding a little oil to a vegetable dish | Improves uptake of A, D, E, K and carotenoids | Fat is required to form absorptive micelles |
| Storing milk in clear glass; produce in bright light | Degrades riboflavin, folate | Both are light-sensitive |
| Freezing at harvest | Retention equal to or better than "fresh" | Vitamin C declines during transport and storage |
| Reusing cooking liquid in soup or sauce | Recovers leached vitamins | The nutrients are in the liquid, not destroyed |
- Bioavailability depends on food matrix, dietary fat, chemical form, and nutrient interactions — not just on what the food table says.
- Water-soluble vitamins are lost by leaching and heat; steaming, microwaving, and using the cooking liquid retain far more than boiling and draining.
- Supplements in the US are not pre-approved for safety or efficacy; third-party verification marks and disclosure to clinicians both matter.
- Strong evidence supports targeted supplementation (periconceptional folic acid, newborn vitamin K, B12 for vegan diets and many older adults); routine multivitamins in well-nourished adults have not shown disease-prevention benefit, and high-dose beta-carotene caused harm in smokers.
The chapter in one breath
- Vitamins are organic micronutrients required in mg or µg amounts; they supply 0 kcal/g, while carbohydrate and protein give 4, fat 9, and alcohol 7 kcal/g.
- Solubility drives everything: fat-soluble A, D, E, K need dietary fat, are stored, and can reach toxicity; water-soluble B and C turn over fast and need regular intake.
- Vitamin A runs night vision and epithelial differentiation — deficiency causes xerophthalmia, and preformed retinol above the 3,000 µg/day UL is teratogenic.
- Vitamin D (RDA 15 µg / 600 IU/day ages 1–70; 20 µg / 800 IU/day over 70) governs calcium absorption; deficiency causes rickets and osteomalacia, and its non-skeletal claims remain unproven.
- Vitamin E is the membrane antioxidant (RDA 15 mg/day); vitamin K carboxylates clotting factors (AI 120 µg/day men, 90 µg/day women) and newborns need a dose at birth.
- The B vitamins are coenzymes: thiamin→beriberi and Wernicke–Korsakoff, niacin→pellagra's four Ds, folate and B12→megaloblastic anemia, with B12 adding irreversible neurologic injury.
- Vitamin C hydroxylates collagen and boosts non-heme iron absorption (RDA 90 mg men, 75 mg women); its absence is scurvy, the subject of Lind's 1747 controlled trial.
- In practice, bioavailability and cooking method change what you actually absorb, and supplement evidence is strong for a few targeted uses and weak or negative for routine high-dose use.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Adequate Intake (AI)
- A reference intake used when evidence is insufficient to set an RDA; vitamins K, B5, and B7 have AIs.
- Ascorbic acid
- Vitamin C; a water-soluble reducing agent required for collagen hydroxylation, carnitine and norepinephrine synthesis, and non-heme iron absorption.
- Beriberi
- Thiamin (B1) deficiency disease; the "wet" form is cardiac with edema, the "dry" form a peripheral neuropathy.
- Bioavailability
- The proportion of an ingested nutrient that is absorbed and available for the body to use.
- Carotenoid
- A plant pigment; the provitamin A carotenoids (beta-carotene, alpha-carotene, beta-cryptoxanthin) are converted to retinol in the body.
- Coenzyme
- A small non-protein molecule an enzyme requires in order to catalyze its reaction; most B vitamins become coenzymes.
- Dietary folate equivalent (DFE)
- The unit for folate intake, adjusting for the higher absorption of synthetic folic acid relative to naturally occurring food folate.
- Fat-soluble vitamin
- Vitamins A, D, E, and K, which require dietary fat and bile for absorption and are stored in liver and adipose tissue.
- Hypervitaminosis
- Vitamin toxicity from excessive intake, most often involving preformed vitamin A or vitamin D from supplements.
- Intrinsic factor
- A protein secreted by gastric parietal cells that is required for vitamin B12 absorption in the terminal ileum.
- Megaloblastic anemia
- Anemia with abnormally large, immature red cells caused by impaired DNA synthesis, classically from folate or vitamin B12 deficiency.
- Micronutrient
- A vitamin or mineral required in milligram or microgram quantities, supplying no energy.
- Niacin equivalent (NE)
- The unit for niacin intake, accounting for niacin synthesized from tryptophan (about 60 mg tryptophan yields 1 mg niacin).
- Osteomalacia
- Softening of adult bone from vitamin D deficiency, with bone pain and proximal muscle weakness; the adult counterpart of rickets.
- Pellagra
- Niacin (B3) deficiency disease, remembered as dermatitis, diarrhea, dementia, and death.
- Recommended Dietary Allowance (RDA)
- The daily intake estimated to meet the needs of about 97–98% of healthy people in a stated age and sex group.
- Retinol activity equivalent (RAE)
- The unit for vitamin A intake: 1 µg RAE equals 1 µg retinol, 12 µg dietary beta-carotene, or 24 µg other provitamin A carotenoids.
- Rickets
- Vitamin D deficiency in children, causing soft, deforming bone with bowed legs and widened growth plates.
- Scurvy
- Vitamin C deficiency disease: bleeding gums, perifollicular hemorrhage, corkscrew hairs, poor wound healing, and joint pain.
- Tolerable Upper Intake Level (UL)
- The highest chronic daily intake unlikely to cause adverse effects in almost all people; a ceiling, not a target.
- Water-soluble vitamin
- The eight B vitamins and vitamin C; minimally stored, readily excreted, and easily lost into cooking water.
- Xerophthalmia
- Progressive drying and damage of the conjunctiva and cornea from vitamin A deficiency; a leading preventable cause of childhood blindness worldwide.