Cardiovascular Drugs II
The first cardiovascular chapter was about pressure and volume. This one is about the heart muscle itself — the plaque that starves it, the pain that warns you, the pump that fails, and the electricity that keeps it honest. These are the drugs that live on your high-alert list: digoxin with its razor-thin therapeutic window, nitroglycerin that can drop a blood pressure through the floor, amiodarone that quietly scars a lung over months, and statins that most of your patients will take for the rest of their lives. What makes a nurse valuable here is not memorizing every drug — it is knowing which number to check before you push, which symptom means stop, and which sentence, said clearly at discharge, keeps a patient out of the emergency department. That is what this chapter teaches.
By the end of this chapter you can
- Explain how statins lower LDL, and describe the muscle and liver monitoring a nurse performs.
- Compare the non-statin lipid agents — ezetimibe, PCSK9 inhibitors, fibrates, niacin, bile acid sequestrants — and their signature adverse effects.
- Teach a patient to use sublingual nitroglycerin safely, including storage, dosing intervals, and when to call 911.
- Identify the drugs in the acute coronary syndrome bundle and the nursing priorities for each.
- Describe the four pillars of heart failure therapy and the monitoring each one demands.
- Recognize digoxin toxicity early, name its antidote, and explain why potassium is the drug's hidden partner.
- Classify antiarrhythmics by Vaughan Williams class and state what each class does to the cardiac action potential.
- Perform and document an apical pulse, and state the parameters that mean hold the dose and call.
Section 1Dyslipidemia drugs
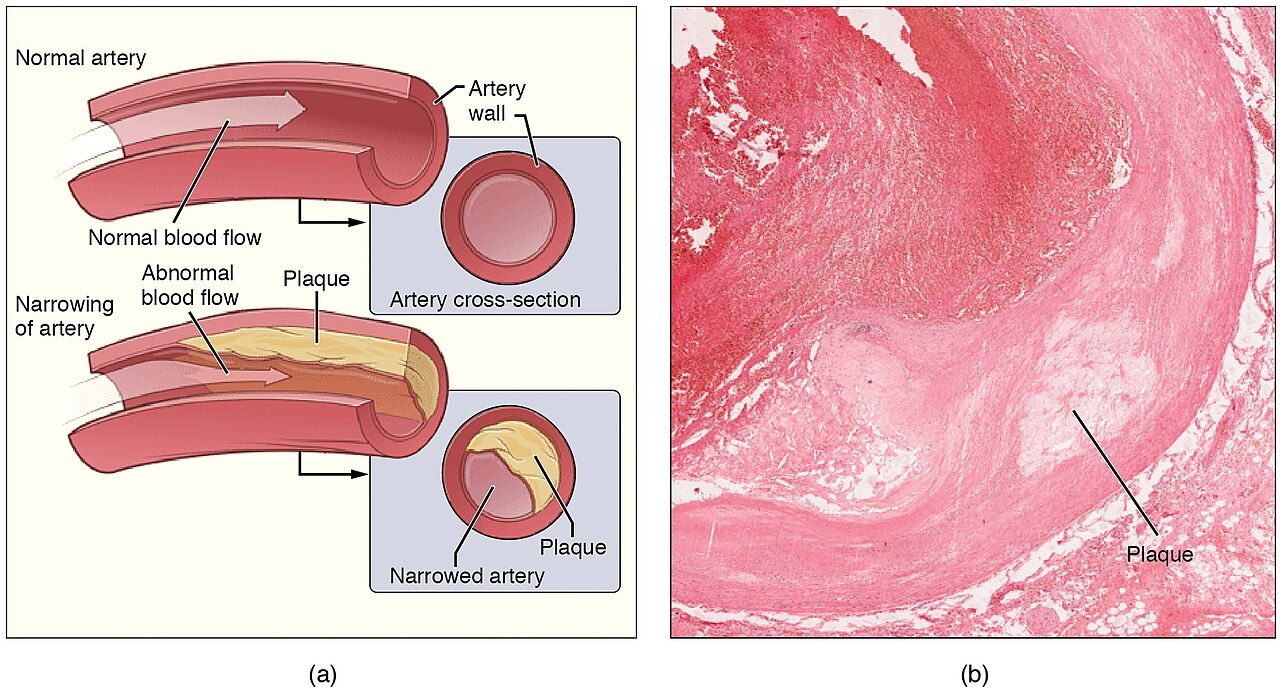
Why we chase a number the patient cannot feel
Dyslipidemia is the quietest diagnosis in the chart. Nobody feels a high LDL. There is no pain, no shortness of breath, no reason to take a pill every night for thirty years — and that is exactly the nursing problem. Low-density lipoprotein (LDL) is the particle that carries cholesterol into the arterial wall, where it oxidizes, recruits inflammatory cells, and builds the plaque you saw in the figure above. High-density lipoprotein (HDL) carries cholesterol back out toward the liver. Triglycerides are a separate problem: at very high levels (roughly above 500 mg/dL) they stop being a cardiac issue and become a pancreatitis issue.
Modern lipid management is not really about hitting a magic number. It is about risk: how likely is this person to have a heart attack or stroke in the next ten years, and how hard should we push? A patient who has already had a myocardial infarction gets high-intensity therapy without much debate. A healthy 45-year-old with a borderline panel gets a conversation. Your job is to make sure that conversation includes the truth: this drug does nothing you will notice, and it works only if you keep taking it.
Statins: the backbone
The HMG-CoA reductase inhibitors — every drug ending in -statin — block the rate-limiting enzyme the liver uses to make cholesterol. Starved of homemade cholesterol, the liver cell puts more LDL receptors on its surface and pulls LDL out of the blood. That is the whole mechanism, and it is remarkably effective: atorvastatin 40–80 mg or rosuvastatin 20–40 mg (the two high-intensity regimens) drop LDL by roughly half. Statins also stabilize existing plaque and damp vascular inflammation, which is why they are started in the hospital during an acute coronary syndrome even when the LDL looks acceptable.
Timing depends on half-life, and students get this backwards constantly. The liver makes most of its cholesterol overnight, so the short-acting statins — simvastatin, lovastatin, fluvastatin — are given in the evening. The long-acting ones — atorvastatin, rosuvastatin, pitavastatin — have half-lives long enough that they can be taken at any consistent hour, which is a gift for adherence.
Statins are metabolized largely by CYP3A4, which is why grapefruit juice matters. Grapefruit inhibits intestinal CYP3A4 and raises drug levels — the effect is real for simvastatin and lovastatin (avoid entirely), modest for atorvastatin (an occasional glass is usually tolerated), and essentially absent for pravastatin, rosuvastatin, and pitavastatin. If a patient loves grapefruit and refuses to give it up, that is a reason to switch statins, not a reason to lose the patient.
Myopathy: the thing you are actually watching for
Muscle complaints are the reason statins get stopped. They sit on a spectrum, and knowing where a patient falls on it is a genuinely useful nursing skill.
Myalgia is muscle aching or weakness with a normal creatine kinase — common, uncomfortable, not dangerous. Myopathy or myositis means symptoms plus a rising creatine kinase (CK). Rhabdomyolysis is the emergency: CK typically more than ten times the upper limit of normal, muscle protein spilling into the blood, and myoglobin clogging the renal tubules into acute kidney injury. The teaching sentence is short and specific: "If your muscles hurt badly, feel weak, and your urine turns the color of cola or tea, stop the drug and call today." Dark urine is the line between an annoyance and a hospitalization.
What do you actually monitor? Less than students expect. Check a lipid panel at baseline and again about 4–12 weeks after starting or changing a dose, then periodically. Check liver enzymes (ALT) at baseline — routine repeat LFTs are no longer recommended, only checked if symptoms of hepatotoxicity appear. Do not draw a routine CK either; get a baseline CK only in high-risk patients (older adults, kidney disease, hypothyroidism, multiple interacting drugs), and draw one whenever a patient reports muscle symptoms. Risk climbs with age, small body frame, renal impairment, untreated hypothyroidism, heavy alcohol use, and CYP3A4 inhibitors like clarithromycin, some azole antifungals, and certain HIV protease inhibitors.
Statins are also traditionally stopped in pregnancy and during breastfeeding. The labeling has been softened to allow individualized use in a narrow group of very-high-risk patients, but the practical bedside expectation remains: a patient who becomes pregnant or is planning pregnancy stops the statin and calls the prescriber. Always ask about pregnancy plans in patients of childbearing potential before discharge.
When a statin is not enough
Statins do the heavy lifting; everything else is an add-on for patients who cannot reach goal, cannot tolerate statins, or have a triglyceride problem instead of an LDL problem.
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| HMG-CoA reductase inhibitor (statin) | atorvastatin, rosuvastatin | LDL down 30–55%; stabilizes plaque | Muscle pain plus dark urine = rhabdomyolysis. Draw CK if symptoms. Short-acting statins at night; avoid grapefruit with simvastatin/lovastatin |
| Cholesterol absorption inhibitor | ezetimibe | Blocks NPC1L1 in gut; adds another 15–25% LDL drop | Very well tolerated; myopathy risk rises slightly when paired with a statin. Give 2 h before or 4 h after a bile acid sequestrant |
| PCSK9 inhibitor (monoclonal antibody) | alirocumab, evolocumab | Frees LDL receptors for recycling; LDL down another ~50% | Subcutaneous every 2–4 weeks. Injection-site reactions; teach self-injection and refrigerated storage (warm to room temperature first) |
| Small interfering RNA | inclisiran | Silences PCSK9 synthesis in the liver | Subcutaneous, given in the office — then only twice a year. A powerful option for the nonadherent patient |
| ATP-citrate lyase inhibitor | bempedoic acid | LDL down ~15–25%; prodrug activated in liver, not muscle | Useful in statin intolerance. Watch uric acid (gout flares) and rare tendon rupture |
| Fibrate | fenofibrate, gemfibrozil | Best triglyceride reduction (~40–50%); modest HDL rise | Never combine gemfibrozil with a statin — severe myopathy. Fenofibrate is the safer partner. Gallstones; monitor renal function |
| Nicotinic acid (niacin) | niacin (extended release) | Raises HDL, lowers TG and LDL | Flushing is near-universal: aspirin 325 mg 30 min before, take with food, avoid alcohol and hot drinks. Also hyperglycemia, hyperuricemia, hepatotoxicity |
| Bile acid sequestrant | cholestyramine, colesevelam | Binds bile acids in the gut; liver burns cholesterol to replace them | Constipation, bloating. Binds other drugs — give other medications 1 h before or 4 h after. Can raise triglycerides |
| Omega-3 fatty acid | icosapent ethyl | Lowers triglycerides; reduces events in select patients | Bleeding risk with anticoagulants; small increase in atrial fibrillation. Fishy aftertaste and burping drive nonadherence |
- Statins inhibit HMG-CoA reductase, forcing the liver to pull LDL out of the blood; they also stabilize plaque.
- Give short-acting statins (simvastatin, lovastatin) in the evening; atorvastatin and rosuvastatin any consistent time.
- Monitor lipids at baseline and 4–12 weeks; ALT at baseline only; draw CK when muscle symptoms appear, not routinely.
- Muscle pain plus cola-colored urine equals rhabdomyolysis — hold the drug and report the same day.
Section 2Angina and acute coronary syndrome
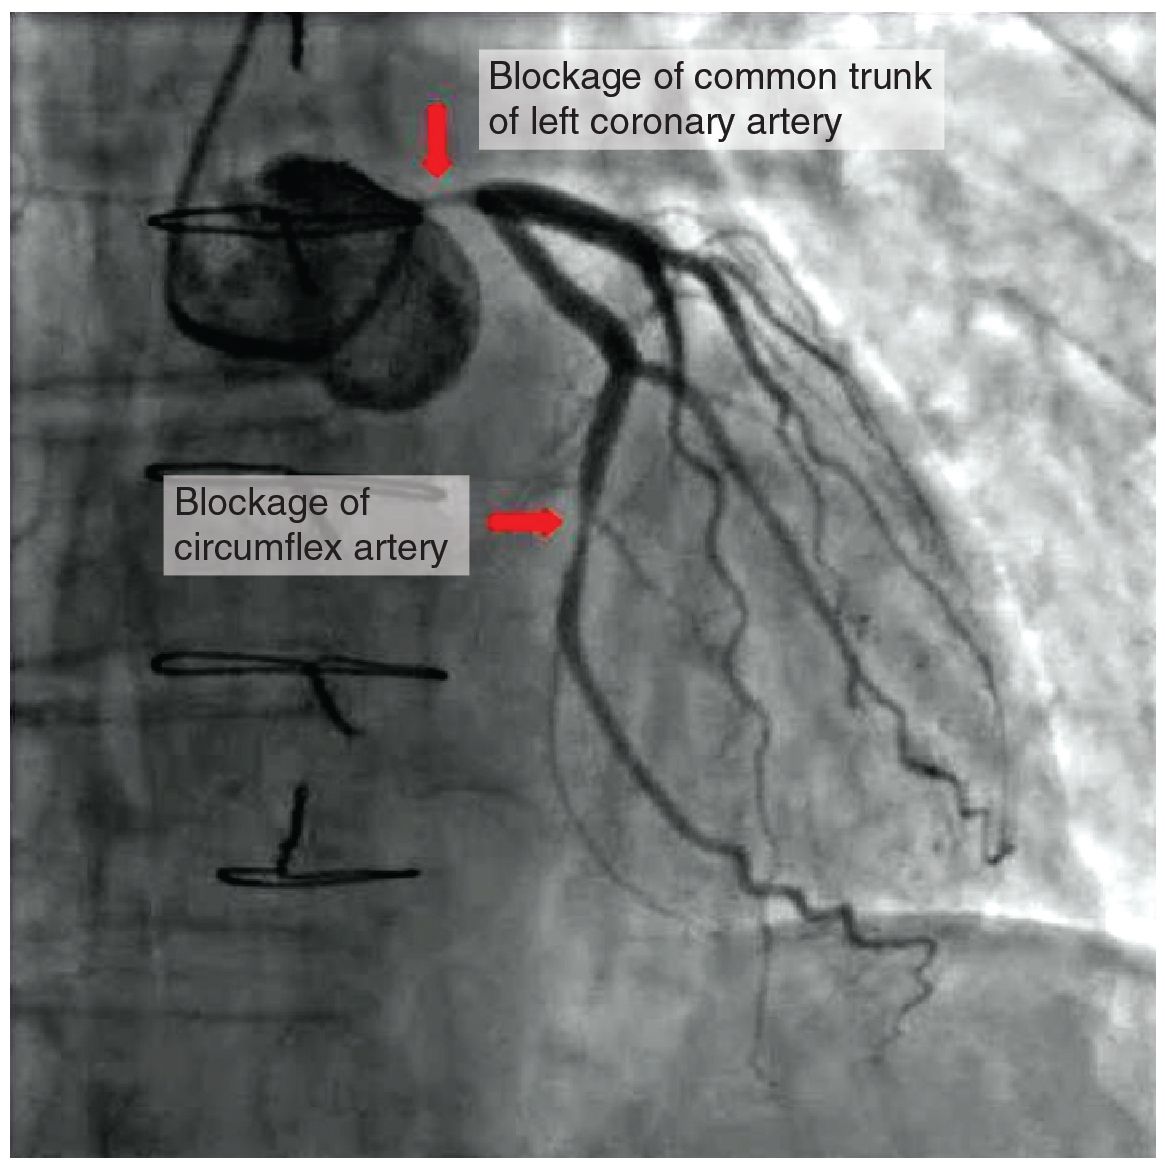
Supply versus demand, and nothing else
Every antianginal drug ever invented does one of two things: it increases the oxygen supply reaching the myocardium, or it lowers the myocardial oxygen demand. That is the entire logic of this section, and if you hold onto it, the drug list organizes itself.
Demand rises with heart rate, contractility, and wall tension (which reflects preload and afterload). So a drug that slows the heart, softens the squeeze, or drains the ventricle before it contracts will lower demand. Supply depends on coronary flow, which happens mostly during diastole — another reason slowing the heart helps, since a slower heart spends proportionally more time in diastole.
Stable angina is predictable: it comes on with exertion or emotion and goes away with rest or nitroglycerin, because a fixed plaque cannot pass enough blood when demand climbs. Unstable angina is new, worsening, or occurs at rest — the plaque has ruptured and a clot is forming. Vasospastic (Prinzmetal) angina is coronary spasm in an artery that may be nearly normal, classically at rest and in the early morning. Acute coronary syndrome (ACS) is the umbrella over unstable angina, NSTEMI, and STEMI — and the distinction between them lives in the troponin and the ST segment, not in how loudly the patient complains.
Nitrates: the drug your patient carries in a pocket
Nitrates are converted to nitric oxide in vascular smooth muscle, which relaxes it. At usual doses the effect is mostly venodilation: blood pools in the veins, less returns to the heart, preload falls, the ventricle wall is under less tension, and demand drops. At higher doses arteries dilate too, lowering afterload, and the coronary arteries themselves relax — which is why nitrates are excellent for vasospastic angina.
Sublingual nitroglycerin teaching is one of the most testable and most genuinely life-saving conversations you will have. Sit or lie down first — this drug drops blood pressure and people faint standing in kitchens. Place one 0.4 mg tablet under the tongue (or one spray onto or under the tongue) and let it dissolve; do not swallow it, do not chew it. A tingling or burning sensation may occur but its absence does not mean the tablet is dead. If the pain is unimproved or worsening 5 minutes after the first dose, call 911 — then continue up to a total of three doses, 5 minutes apart, while help is on the way. That order matters: the old teaching of "three doses, then call" delayed too many people.
Storage sinks a lot of prescriptions. Tablets belong in their original amber glass bottle, tightly capped, away from heat, light, and moisture — not in a pill organizer, not in a pocket against body heat, not in a steamy bathroom cabinet or a hot car. Once the bottle is opened, replace it about every 6 months. The metered spray is more stable and often the better choice for someone who rarely uses it. Expect headache — it is the most common effect, it means the drug is working, and acetaminophen usually handles it. Warn about dizziness and orthostasis.
Other nitrate forms have their own traps. Transdermal patches and long-acting isosorbide mononitrate/dinitrate cause tolerance if given around the clock, so the regimen builds in a nitrate-free interval of 10–12 hours — usually the patch goes on in the morning and comes off in the evening. Remove the old patch before applying a new one, rotate sites, and wear gloves so you do not dose yourself with a headache. Intravenous nitroglycerin is titrated to pain and blood pressure and traditionally requires non-PVC (polyethylene or glass) tubing, because the drug adsorbs to standard PVC.
The rest of the antianginal cabinet
Beta blockers (metoprolol, atenolol, bisoprolol) are first-line for chronic stable angina and reduce mortality after MI: they cut heart rate and contractility, so demand falls and diastolic filling time lengthens. Hold and reassess for bradycardia, hypotension, or acute decompensated heart failure, and never stop them abruptly — rebound tachycardia and angina can trigger an infarct. One classic exception: avoid beta blockers in cocaine-associated chest pain, where unopposed alpha stimulation can worsen coronary spasm; benzodiazepines and nitrates are used instead.
Calcium channel blockers dilate coronary and systemic arteries. Amlodipine and other dihydropyridines mainly vasodilate (ankle edema, reflex tachycardia, flushing). Verapamil and diltiazem also slow the heart and reduce contractility, which makes them useful when a beta blocker is not tolerated — but combining them with a beta blocker risks serious bradycardia and heart block. CCBs are the drugs of choice for vasospastic angina. Ranolazine is a later-line option for chronic angina that inhibits the late sodium current; it barely touches heart rate or blood pressure, which is its selling point, but it prolongs the QT interval and is never used for an acute attack.
The ACS bundle
When a patient with crushing chest pain hits the door, a familiar set of drugs goes in fast. Older courses teach the mnemonic MONA (morphine, oxygen, nitrates, aspirin) — keep the letters, but update the practice: morphine has been deprioritized (it may blunt antiplatelet absorption and can mask ongoing ischemia), and oxygen is given only if the SpO2 is below about 90%, because routine oxygen in a non-hypoxic patient offers no benefit and may cause harm. Aspirin remains the one drug that saves lives in the first minutes.
| Role | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| Antiplatelet (immediate) | aspirin 162–325 mg | Irreversible COX-1 blockade; stops thromboxane A2 | Chewed, not swallowed — faster absorption. Non-enteric-coated. Give first, ask questions second |
| P2Y12 inhibitor | clopidogrel, ticagrelor, prasugrel | Blocks ADP-mediated platelet aggregation | Ticagrelor causes dyspnea (not heart failure) and requires aspirin ≤100 mg/day. Prasugrel is contraindicated with prior stroke/TIA. Hold before CABG |
| Anticoagulant | heparin, enoxaparin, bivalirudin | Stops clot propagation | High-alert. Monitor aPTT (heparin), platelets for HIT, bleeding at all sites. Antidote for heparin: protamine sulfate |
| Nitrate | nitroglycerin SL, then IV | Lowers preload; relieves pain and spasm | Ask about PDE5 inhibitors. Hold for SBP <90 or RV infarction. Continuous BP monitoring on the drip |
| Beta blocker | metoprolol | Lowers demand; reduces mortality and reinfarction | Start within 24 h if stable. Hold for bradycardia, hypotension, decompensated HF, cocaine use |
| High-intensity statin | atorvastatin 80 mg | Stabilizes plaque; reduces recurrent events | Started in hospital regardless of the LDL number. Teach that this is a lifetime drug |
| ACE inhibitor | lisinopril | Limits ventricular remodeling after infarct | Start within 24 h if stable, especially with reduced EF. Watch first-dose hypotension, K+, creatinine, cough |
| Fibrinolytic | alteplase, tenecteplase | Dissolves the clot when PCI is unavailable | Screen hard for bleeding contraindications. Door-to-needle ≤30 min; PCI door-to-balloon ≤90 min |
| Analgesia (selective) | morphine | Pain and anxiety relief; mild venodilation | Now reserved for pain refractory to nitrates. Monitor BP and respirations; naloxone available |
- Every antianginal either raises supply or lowers demand; nitrates work mainly by dropping preload.
- Sublingual nitroglycerin: sit down, one dose, call 911 if unimproved at 5 minutes, up to 3 doses 5 minutes apart. Amber glass, replace every 6 months. Headache is expected.
- Nitrates plus PDE5 inhibitors can kill — ask about sildenafil (24 h) and tadalafil (48 h) before every dose.
- ACS: chewed aspirin immediately, P2Y12 inhibitor, anticoagulant, beta blocker, high-intensity statin; oxygen only if SpO2 <90%; morphine deprioritized.
Section 3Heart failure drugs
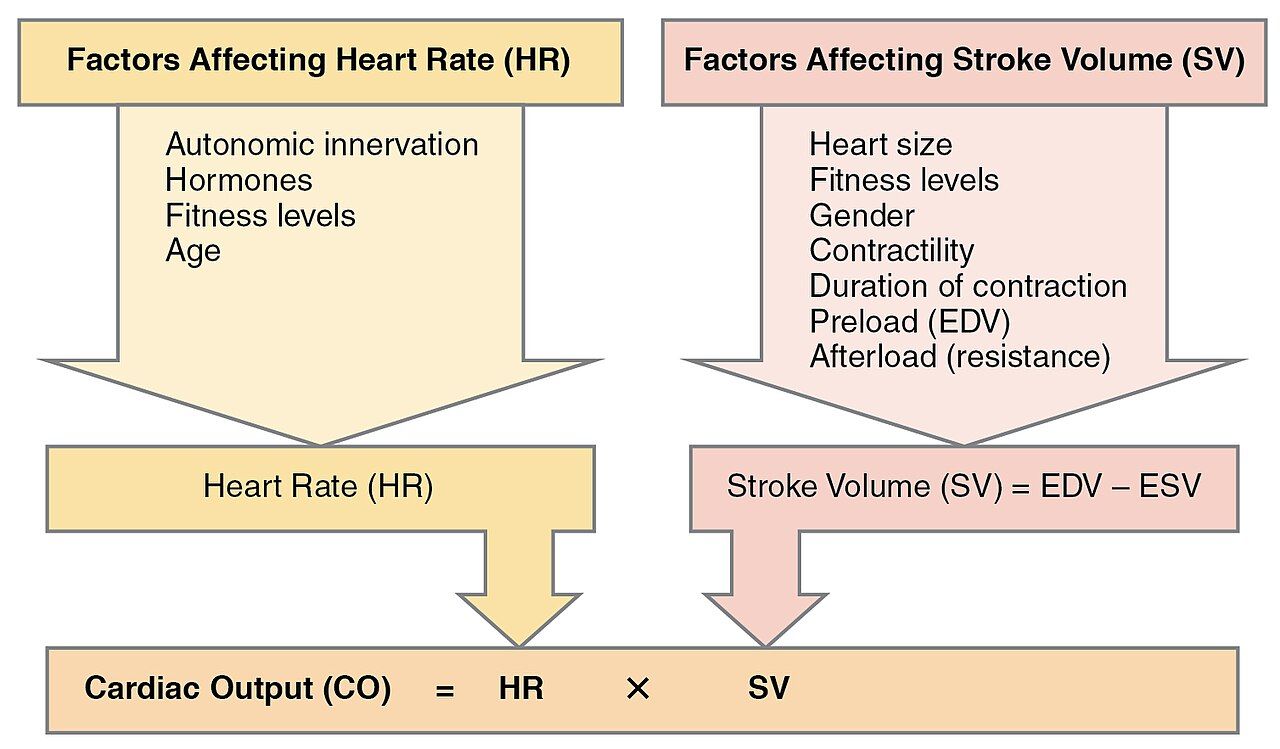
What a failing heart is actually doing
In heart failure with reduced ejection fraction (HFrEF), the ventricle cannot eject enough blood, and the body — sensing what looks like low volume — does exactly the wrong thing. The sympathetic nervous system fires, raising heart rate and afterload. The renin–angiotensin–aldosterone system (RAAS) switches on, retaining sodium and water and driving vasoconstriction. Over months, angiotensin II and aldosterone remodel the ventricle into a dilated, fibrotic, poorly functioning bag. The compensation becomes the disease.
That is why modern heart failure therapy looks strange at first glance: the cornerstone drugs are ones that slow the heart and block the very hormones the body is producing. We are not helping the heart work harder. We are calling off the neurohormonal siege. And the payoff is not just symptom relief — these are mortality drugs, which is why titrating them to target doses matters more than almost anything else on the outpatient side.
The four pillars
Guideline-directed medical therapy for HFrEF now rests on four drug classes, all started early and titrated up as tolerated. Students should be able to name all four cold.
| Pillar | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| ARNI (or ACE inhibitor / ARB) | sacubitril/valsartan; lisinopril; losartan | Blocks RAAS; ARNI also blocks neprilysin, preserving natriuretic peptides | 36-hour washout between an ACE inhibitor and an ARNI — overlapping causes angioedema. Never give both. Monitor BP, K+, creatinine. Fetal toxicity — contraindicated in pregnancy |
| Beta blocker (evidence-based only) | carvedilol, metoprolol succinate, bisoprolol | Blocks sympathetic overdrive; reverses remodeling; lowers mortality | Start low, go slow. Symptoms may worsen for weeks before improving — warn the patient or they will quit. Do not start during acute decompensation. Metoprolol tartrate is not a heart failure drug |
| Mineralocorticoid receptor antagonist | spironolactone, eplerenone | Blocks aldosterone; antifibrotic; potassium-sparing | Hyperkalemia — check K+ and creatinine about 1 week and 1 month after start/titration. Spironolactone causes gynecomastia; eplerenone rarely does. No salt substitutes |
| SGLT2 inhibitor | dapagliflozin, empagliflozin | Improves outcomes in HF with or without diabetes | Genital mycotic infections (teach perineal hygiene), volume depletion, rare euglycemic DKA. Hold with acute illness or prolonged fasting |
Around the pillars sit useful extras. Hydralazine plus isosorbide dinitrate is added for patients who remain symptomatic (with proven benefit in self-identified Black patients) and is a fallback when ACE inhibitors and ARBs cannot be used because of renal function or hyperkalemia. Ivabradine slows the SA node's funny current for patients in sinus rhythm with a heart rate still at or above 70 despite a maximally tolerated beta blocker; it causes luminous visual phenomena (phosphenes) that alarm patients unless you warn them. Vericiguat is an option after a worsening event.
The ACE inhibitor profile deserves its own list, because it recurs everywhere: a persistent dry, hacking cough from bradykinin accumulation (switch to an ARB — ARBs do not cause it), angioedema (a true emergency; airway first; a lifetime contraindication to the whole class and to ARNI), hyperkalemia, first-dose hypotension (give the first dose at bedtime, hold diuretics if possible), a rise in creatinine, and fetal toxicity.
Diuretics: symptom control, not survival
Diuretics are the drugs patients feel working — and they are also the ones that do not, by themselves, prolong life. They exist to pull water off a congested patient who cannot breathe.
Loop diuretics (furosemide, bumetanide, torsemide) block the Na-K-2Cl transporter in the thick ascending limb and are powerful enough to work even when the GFR is poor. Their costs are electrolytic: hypokalemia, hypomagnesemia, hyponatremia, hypocalcemia, metabolic alkalosis, hyperuricemia, hyperglycemia, and dehydration with orthostatic hypotension. Ototoxicity — tinnitus and hearing loss, usually reversible — is linked to rapid IV administration and high doses, which is why IV furosemide is pushed slowly (commonly no faster than about 20 mg/min) and why loop plus aminoglycoside is a bad pairing. Loops are sulfonamide-derived; ethacrynic acid is the alternative for a true sulfa allergy. Give the morning dose early and the second dose by mid-afternoon so the patient is not up all night.
Thiazides (hydrochlorothiazide, chlorthalidone) are weaker and fail below a GFR of roughly 30. Metolazone is the exception used for diuretic resistance: it is given about 30 minutes before the loop dose, and the combination is potent enough to strip potassium dangerously fast — watch the K+ closely. Potassium-sparing agents (spironolactone, eplerenone, triamterene, amiloride) go the other way and retain potassium.
Digoxin and its narrow window
Digoxin is the oldest drug in this chapter and the one most likely to hurt someone. It inhibits the sodium–potassium ATPase in cardiac myocytes. Sodium builds up inside the cell, the sodium–calcium exchanger runs less efficiently, intracellular calcium rises, and the contraction gets stronger — a positive inotropic effect. Separately, digoxin increases vagal tone at the AV node, slowing conduction and heart rate — a negative chronotropic and negative dromotropic effect. That combination is why it is used both for symptomatic HFrEF (fewer hospitalizations, but no mortality benefit) and for rate control in atrial fibrillation, particularly in a hypotensive patient who cannot tolerate a beta blocker.
The therapeutic range is classically 0.5–2.0 ng/mL, but in heart failure the modern target is a narrower 0.5–0.9 ng/mL — higher levels increase mortality without adding benefit. Draw the level as a trough, at least 6–8 hours after the last dose (12 hours or immediately before the next dose is cleanest); a level drawn too early looks alarmingly high and reflects distribution, not toxicity.
The signs of toxicity are famous because they are exam gold and because they are easy to miss at 3 a.m.
| System | What you see | Why it matters |
|---|---|---|
| Gastrointestinal | Anorexia first, then nausea, vomiting, abdominal pain | Loss of appetite is the earliest sign — ask about it every visit |
| Visual | Blurred or yellow-green vision, halos around lights | Nearly pathognomonic; patients rarely mention it unless asked |
| Neurologic | Fatigue, weakness, confusion, delirium | In older adults, new confusion is often the only sign |
| Cardiac | Bradycardia, AV block, any arrhythmia (classically bidirectional VT, or atrial tachycardia with block) | The lethal endpoint. Digoxin can cause the very rhythms it treats |
| Electrolytes | Hypokalemia, hypomagnesemia, hypercalcemia | Each one potentiates toxicity at a normal drug level |
That last row is the concept students most often miss. Potassium and digoxin compete for the same binding site on the Na+/K+ ATPase. When potassium falls — and what drug does your heart failure patient also take? A loop diuretic — digoxin binds more avidly and the patient can become toxic with a "therapeutic" level on the lab report. A normal digoxin level does not rule out digoxin toxicity. Interacting drugs raise levels too: amiodarone, verapamil, quinidine, and clarithromycin all push digoxin up, and the dose is typically cut roughly in half when amiodarone is added.
Treatment of significant toxicity is digoxin immune Fab (DigiFab) — antibody fragments that bind digoxin and pull it out of tissue — used for life-threatening arrhythmia, severe hyperkalemia from acute overdose, or hemodynamic instability. After Fab is given, total serum digoxin levels become uninterpretable (they measure bound drug), so treat the patient, not the number. Correct hypokalemia and hypomagnesemia; in acute overdose with hyperkalemia, calcium is generally avoided.
- Heart failure therapy blocks the body's own compensation: the four pillars are ARNI/ACEi/ARB, an evidence-based beta blocker, an MRA, and an SGLT2 inhibitor.
- Allow a 36-hour washout from an ACE inhibitor before an ARNI; ACE inhibitor cough means switch to an ARB; angioedema means stop the class forever.
- Loop diuretics relieve congestion but waste potassium and magnesium and are ototoxic if pushed fast; MRAs and ACE inhibitors retain potassium — know which way each drug pulls.
- Digoxin: target 0.5–0.9 ng/mL in HF, trough drawn 6–8+ h post-dose; anorexia is the first sign; hypokalemia potentiates toxicity; antidote is digoxin immune Fab.
Section 4Antiarrhythmics
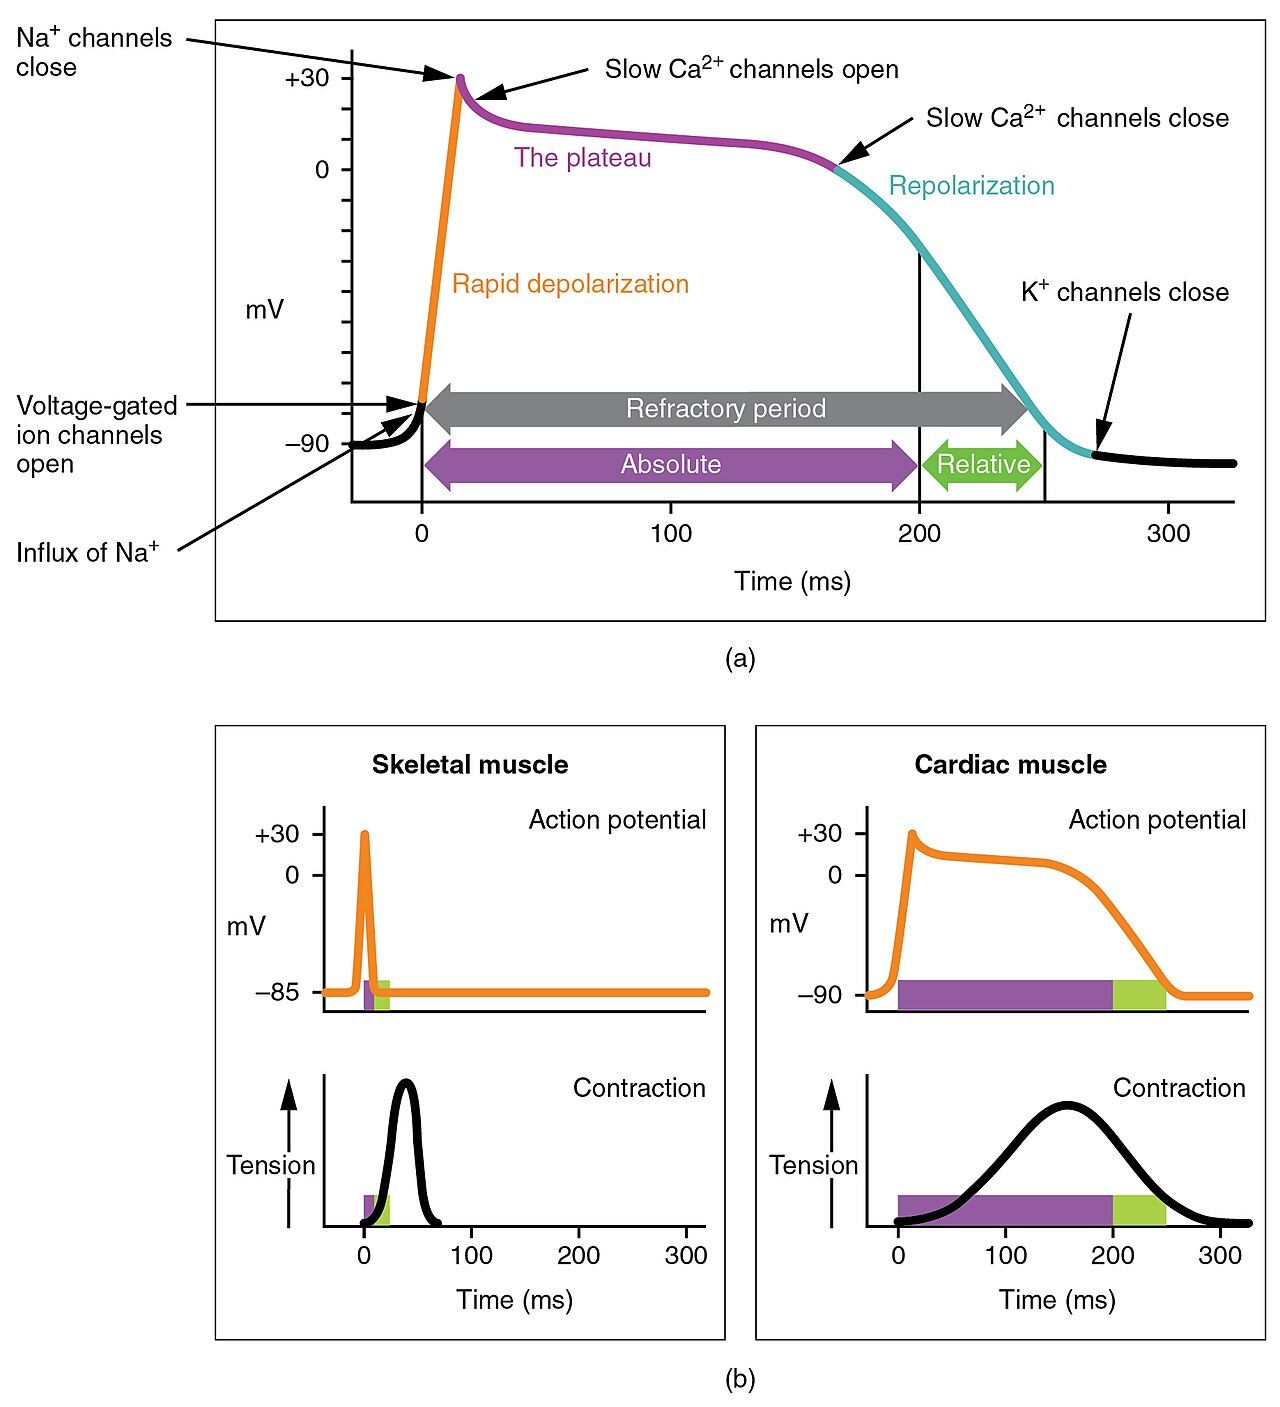
The five phases, and why anyone should care
Antiarrhythmics are frightening to learn because the classification looks arbitrary. It is not. Each class is named for the ion channel it blocks, and each channel owns a phase of the action potential. Learn the phases once and the classes become obvious.
In a working ventricular myocyte: Phase 0 is the rapid upstroke — sodium rushes in and the cell depolarizes. Phase 1 is a brief notch as potassium leaks out. Phase 2 is the long plateau unique to cardiac muscle — calcium enters and drives contraction, and this is what keeps the heart from tetanizing. Phase 3 is repolarization as potassium floods out. Phase 4 is the resting membrane potential — except in pacemaker cells (SA and AV nodes), where phase 4 is a slow spontaneous drift upward (the "funny current") that sets the heart rate, and where phase 0 is driven by calcium, not sodium. That last detail explains why calcium channel blockers act on nodes while sodium channel blockers act on the working muscle.
The Vaughan Williams classes
| Class | Prototype | Key effect | Nursing alert |
|---|---|---|---|
| IA — Na+ block (moderate) | procainamide, quinidine, disopyramide | Slows phase 0; prolongs repolarization → widened QRS and longer QT | Procainamide: drug-induced lupus (arthralgia, butterfly rash — check ANA), agranulocytosis, hypotension on rapid IV. Quinidine: cinchonism (tinnitus, headache, vertigo), diarrhea, raises digoxin. Watch for torsades |
| IB — Na+ block (weak) | lidocaine, mexiletine | Slows phase 0 slightly; shortens repolarization; targets ischemic ventricular tissue | Ventricular arrhythmias only — useless in atrial fibrillation. Toxicity is neurologic: perioral numbness, tinnitus, confusion, twitching, seizures. Never use the lidocaine with epinephrine formulation IV |
| IC — Na+ block (strong) | flecainide, propafenone | Markedly slows phase 0; minimal effect on repolarization | Contraindicated with structural heart disease or prior MI — increases mortality. Used in structurally normal hearts, sometimes as a "pill in the pocket" for AF |
| II — beta blockers | metoprolol, esmolol, atenolol | Blunt sympathetic drive; slow phase 4 in the SA node and slow AV conduction | Rate control workhorses. Hold for bradycardia or hypotension; caution in asthma (use cardioselective); mask hypoglycemia symptoms in diabetes; never stop abruptly |
| III — K+ block | amiodarone, sotalol, dofetilide, ibutilide, dronedarone | Prolong phase 3 repolarization → longer refractory period and longer QT | QT prolongation and torsades. Dofetilide and sotalol require inpatient telemetry initiation. Sotalol is also a beta blocker. Dronedarone carries a boxed warning: it doubles mortality in decompensated heart failure and in permanent AF — contraindicated in NYHA class IV or recently decompensated HF, in permanent AF, and in second- or third-degree block without a pacemaker; also hepatotoxic and raises digoxin levels. See amiodarone below |
| IV — non-dihydropyridine Ca2+ block | verapamil, diltiazem | Slow phase 0 in nodal tissue; slow AV conduction and rate | Bradycardia, heart block, hypotension, constipation (verapamil). Avoid in HFrEF (negative inotropes) and use caution with a beta blocker |
| Unclassified | adenosine, digoxin, magnesium, atropine | Adenosine transiently blocks the AV node; magnesium treats torsades; atropine treats symptomatic bradycardia | See adenosine below. Magnesium is the answer for torsades de pointes. Atropine 1 mg IV for unstable bradycardia |
Two drugs that deserve their own paragraph
Amiodarone is the most useful and most toxic antiarrhythmic in the building. It blocks potassium channels (class III) but also has sodium-blocking, beta-blocking, and calcium-blocking activity — it is all four classes in one molecule, which is why it works on almost anything. It is also lipophilic and stored in fat, giving it a half-life of roughly 40–60 days: side effects can appear months after starting and persist months after stopping. Monitoring is a systems tour — pulmonary fibrosis (the feared one; baseline chest X-ray and pulmonary function, then investigate any new dry cough or dyspnea), thyroid dysfunction in either direction because the molecule is loaded with iodine (baseline and periodic TSH), hepatotoxicity (LFTs), corneal microdeposits (usually benign; annual eye exam; report visual halos), and blue-gray skin discoloration with severe photosensitivity (sunscreen and covering clothing — a real quality-of-life issue patients are not warned about often enough). It raises digoxin and warfarin levels, so both doses come down when amiodarone goes up. IV amiodarone can cause hypotension and phlebitis — use a central line or large vein and an inline filter for continuous infusions.
Adenosine is the drug that makes new nurses gasp. Given for stable SVT, it briefly blocks the AV node and the monitor shows a few seconds of asystole before sinus rhythm resumes. Its half-life is under 10 seconds, so it must be given as a rapid IV push — 6 mg, immediately followed by a 20 mL saline flush, ideally through a proximal large-bore line with the arm elevated (a two-syringe or stopcock technique). Warn the patient first: they will feel chest pressure, flushing, and a sense of doom for a few seconds. Have the defibrillator nearby and a rhythm strip running — the strip is diagnostic even when the drug does not convert.
- Vaughan Williams: I = sodium (phase 0), II = beta blockers (phase 4/AV node), III = potassium (phase 3, QT), IV = calcium (nodal phase 0).
- IA prolongs repolarization (procainamide → lupus-like syndrome), IB shortens it and is ventricular-only (lidocaine → seizures), IC is contraindicated in structural heart disease.
- Amiodarone works on everything and damages everything: lungs, thyroid, liver, cornea, skin. Half-life 40–60 days; cut digoxin and warfarin doses.
- Adenosine is a rapid push with a 20 mL flush — warn the patient, expect a brief asystolic pause. Magnesium is the answer for torsades. Watch the QTc on every class III drug.
Section 5Cardiovascular monitoring and nursing care
The apical pulse: a 60-second skill that prevents harm
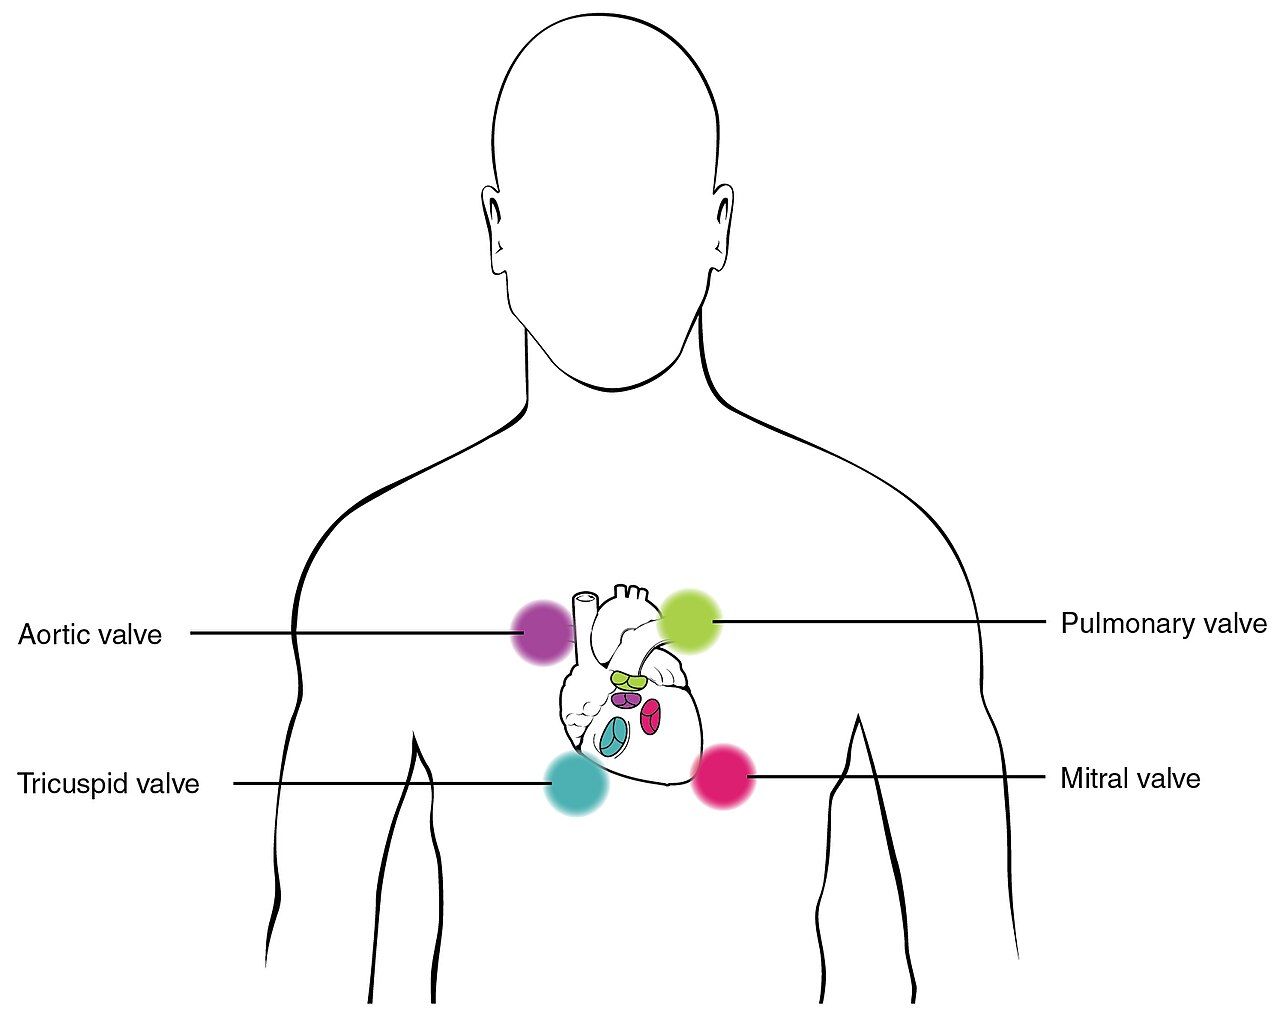
Before digoxin and before beta blockers and non-dihydropyridine calcium channel blockers, you take an apical pulse. Not a radial pulse, not the monitor's number, and not for fifteen seconds times four. Place the diaphragm at the fifth intercostal space, midclavicular line — the point of maximal impulse — and count for a full minute. The full minute is not ritual: these are exactly the patients with irregular rhythms and a pulse deficit, where weak beats generate a heart sound but no radial pulse, and a 15-second sample can be wrong by 20 beats.
Then apply the parameter. Hold digoxin and notify the prescriber if the apical rate is below 60 in an adult (below 70 in a child, below 90–110 in an infant), or if the rate is above 100, or if the rhythm has newly changed. Document the rate, the rhythm, what you held, and who you called. If a patient is discharged on digoxin, they take their own radial pulse for a full minute before every dose — watch them do it, do not just tell them.
Levels, potassium, and the numbers that matter
| What you check | Normal / target | When to check | Nursing alert |
|---|---|---|---|
| Apical pulse | 60–100 bpm | Before every dose of digoxin, beta blocker, verapamil, diltiazem | Hold and call if <60 (adult). Full minute, fifth ICS midclavicular |
| Digoxin level | 0.5–2.0 ng/mL overall; 0.5–0.9 in heart failure | Trough — 6–8+ h after the dose, or just before the next one | A normal level does not rule out toxicity if K+ is low. Antidote: digoxin immune Fab |
| Potassium | 3.5–5.0 mEq/L | Baseline, then with every diuretic, ACEi/ARB/ARNI, or MRA change; ~1 week and 1 month after an MRA start | Low K+ → digoxin toxicity and torsades. High K+ → bradycardia and arrest. Both directions kill |
| Magnesium | 1.5–2.5 mg/dL | With loop diuretics; with any QT-prolonging drug; in refractory hypokalemia | You cannot correct potassium until magnesium is corrected. Magnesium is the treatment for torsades |
| Serum creatinine / eGFR | Baseline-dependent | Before and after starting ACEi/ARB/ARNI/MRA/SGLT2i; with diuretic changes | Digoxin is renally cleared — falling GFR means rising digoxin. A modest early creatinine rise on an ACE inhibitor is often acceptable |
| Blood pressure (with orthostatics) | Individualized | Before nitrates, ACEi/ARNI first doses, and any titration | Hold nitrates for SBP <90. A drop of ≥20 systolic or ≥10 diastolic on standing is orthostatic hypotension — a fall risk |
| QTc interval | <450 ms (men), <460 ms (women) | Baseline and with class IA/III drugs, ranolazine, and dose changes | QTc >500 ms or a rise >60 ms → call. Check K+ and Mg2+ at the same time |
| Daily weight | Patient's dry weight | Every morning at home in heart failure | 2–3 lb in a day or 5 lb in a week → call the clinic. Weight beats edema as an early warning |
| Lipid panel | Risk-based LDL goal | Baseline; 4–12 weeks after a change; then periodically | Fasting is often unnecessary now. Adherence, not the number, is the usual reason a panel disappoints |
| Creatine kinase (CK) | Lab-specific | Only when a statin patient reports muscle symptoms (plus baseline in high-risk patients) | CK >10× ULN with symptoms and dark urine = rhabdomyolysis. Hold the statin |
The potassium row is the one to internalize, because your heart failure patient is often on drugs pulling potassium in both directions at once: a loop diuretic dumping it and an ACE inhibitor plus spironolactone holding it. The net result is unpredictable in any individual, which is why we measure rather than assume. Two teaching points fall out of this. First, salt substitutes are potassium chloride — a patient dutifully avoiding sodium with a shaker of "lite salt" while taking lisinopril and spironolactone can arrive hyperkalemic and bradycardic. Ask specifically. Second, potassium-rich foods (bananas, oranges, potatoes, tomatoes, spinach, avocado) are advice for the patient on a loop diuretic alone, and can be exactly wrong for the patient on an MRA.
What you say before they walk out the door
Cardiovascular drugs fail at home, not in the hospital. These are asymptomatic conditions treated with drugs that cause symptoms — and the patient will do the arithmetic. Discharge teaching is the intervention.
| Drug or class | What the patient must know |
|---|---|
| Statin | Take it forever; it works invisibly. Report muscle pain, weakness, and especially dark urine. Evening dosing for simvastatin/lovastatin. Grapefruit warning where it applies. Stop and call if pregnancy is possible |
| Sublingual nitroglycerin | Sit down. One dose under the tongue; if not better in 5 minutes, call 911, then up to 3 doses total, 5 minutes apart. Amber glass bottle, cool and dark, replace every 6 months. Headache is normal. No erectile dysfunction drugs |
| Nitroglycerin patch | Apply in the morning, remove in the evening for a 10–12 h nitrate-free interval. Remove the old patch first, rotate sites, wash hands |
| Beta blocker | Never stop suddenly — rebound angina, tachycardia, or infarct. Check your pulse before doses. Rise slowly. In diabetes, it can mask the shakiness of hypoglycemia — check glucose, do not rely on feel |
| ACE inhibitor / ARB / ARNI | A dry nagging cough is worth reporting (it is fixable). Any swelling of the lips, tongue, or throat is a 911 emergency. No salt substitutes. Not in pregnancy — call the day you find out |
| Loop diuretic | Morning doses so you can sleep. Weigh yourself daily, same time, same scale, after voiding, before breakfast. 2–3 lb in a day or 5 lb in a week → call. Report ringing in the ears, cramps, or dizziness |
| Spironolactone / eplerenone | No salt substitutes, no potassium supplements unless told. Report breast tenderness or enlargement (there is an alternative). Keep the lab appointments — they are how we catch high potassium before it hurts you |
| Digoxin | Take your pulse for a full minute before every dose; hold and call if under 60. Report loss of appetite, nausea, blurred or yellow-green vision, halos, or new confusion. Never double a missed dose. Keep potassium labs |
| Amiodarone | Report any new cough or shortness of breath right away. Sunscreen and covering clothes — you will burn badly. Keep the thyroid, liver, and eye follow-ups. Tell every prescriber you take it, because it changes other drug levels |
| Antiplatelets / anticoagulants | Soft toothbrush, electric razor, no contact sports. Report black tarry stools, blood in urine, unusual bruising, or a headache after a fall. Never stop a P2Y12 inhibitor after a stent without calling the cardiologist — the stent can clot |
One more layer sits underneath all of it: several drugs in this chapter are formally high-alert medications — IV anticoagulants, IV antiarrhythmics, IV inotropes, and digoxin among them. High-alert does not mean used more often incorrectly; it means when an error happens, the harm is catastrophic. That is what justifies the independent double-check, the smart pump limits, and the habit of saying the dose out loud with another nurse. Use them. Nobody has ever been disciplined for verifying a drip.
- Take an apical pulse for a full minute at the fifth ICS midclavicular line before digoxin, beta blockers, verapamil, and diltiazem; hold and call if <60.
- Draw digoxin levels as a trough ≥6–8 h after the dose; target 0.5–0.9 ng/mL in heart failure. A normal level does not exclude toxicity when potassium is low.
- Potassium is the master variable — loops dump it, MRAs and ACE inhibitors hold it, salt substitutes are potassium chloride, and both extremes are lethal.
- Teach daily weights (2–3 lb/day or 5 lb/week means call), never stopping a beta blocker abruptly, and never combining nitrates with PDE5 inhibitors.
The chapter in one breath
- Statins block HMG-CoA reductase and pull LDL out of the blood; watch for myopathy, draw a CK only when muscles hurt, and treat muscle pain plus dark urine as rhabdomyolysis until proven otherwise.
- Non-statin agents fill gaps: ezetimibe (absorption), PCSK9 inhibitors and inclisiran (receptor recycling), bempedoic acid (statin intolerance), fibrates and icosapent ethyl (triglycerides), niacin (flushing — pretreat with aspirin), sequestrants (separate other drugs by 1–4 hours).
- Antianginals either raise supply or lower demand; nitrates drop preload, cause headache, and are lethal with PDE5 inhibitors — sit down, one dose, call 911 at 5 minutes, three doses maximum, amber glass, replace every 6 months.
- The ACS bundle is chewed aspirin, a P2Y12 inhibitor, an anticoagulant, a beta blocker, a high-intensity statin, and an ACE inhibitor; oxygen only if SpO2 <90%, morphine deprioritized, reperfusion within 30 (needle) or 90 (balloon) minutes.
- Heart failure therapy calls off the body's own neurohormonal siege: the four pillars are ARNI/ACEi/ARB, an evidence-based beta blocker, an MRA, and an SGLT2 inhibitor; diuretics relieve symptoms but do not prolong life.
- Digoxin is a positive inotrope and negative chronotrope with a razor-thin window: anorexia first, then nausea, yellow-green vision, confusion, and arrhythmia; hypokalemia potentiates it; the antidote is digoxin immune Fab.
- Antiarrhythmics are named for the channel they block — I sodium, II beta, III potassium, IV calcium — and every one of them is also proarrhythmic; amiodarone works everywhere and damages lungs, thyroid, liver, cornea, and skin.
- The nursing core is small and it holds: full-minute apical pulse, trough digoxin levels, potassium and magnesium, daily weights, QTc, and the discharge sentences that keep the patient alive at home.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Acute coronary syndrome (ACS)
- The umbrella term for unstable angina, NSTEMI, and STEMI — all caused by plaque rupture and thrombus in a coronary artery.
- Afterload
- The resistance the ventricle must overcome to eject blood; lowering it reduces cardiac workload.
- Angioedema
- Rapid swelling of the lips, tongue, or airway; a rare but life-threatening reaction to ACE inhibitors and ARNIs, and a permanent contraindication to the class.
- Apical pulse
- The heart rate counted with a stethoscope at the fifth intercostal space, midclavicular line, for a full minute — required before digoxin and rate-slowing drugs.
- Chronotropic effect
- An effect on heart rate; digoxin and beta blockers are negative chronotropes.
- Cinchonism
- Quinidine toxicity: tinnitus, headache, vertigo, and visual disturbance.
- Creatine kinase (CK)
- A muscle enzyme that rises with muscle injury; drawn when a statin patient reports muscle symptoms.
- Digoxin immune Fab
- Antibody fragments that bind and inactivate digoxin; the antidote for life-threatening digoxin toxicity.
- Guideline-directed medical therapy (GDMT)
- The evidence-based drug regimen for heart failure, built on four pillars and titrated to target doses.
- High-alert medication
- A drug that causes catastrophic harm when given in error — digoxin, heparin, IV antiarrhythmics — warranting an independent double-check.
- Inotropic effect
- An effect on the force of cardiac contraction; digoxin is a positive inotrope.
- Low-density lipoprotein (LDL)
- The particle that delivers cholesterol into the arterial wall; the primary target of lipid therapy.
- Myopathy
- Muscle pain or weakness accompanied by a rising CK; the middle of the statin muscle spectrum, between benign myalgia and rhabdomyolysis.
- Nitrate tolerance
- Loss of nitrate effect from continuous exposure; prevented by a daily nitrate-free interval of 10–12 hours.
- Preload
- The volume stretching the ventricle at end-diastole; nitrates and diuretics reduce it.
- Proarrhythmia
- A new or worsened arrhythmia caused by an antiarrhythmic drug — a risk of every drug in the class.
- Pulse deficit
- The difference between the apical and radial rates, caused by beats too weak to reach the periphery.
- QT interval (QTc)
- The ECG measure of ventricular repolarization; prolongation predisposes to torsades de pointes.
- Rhabdomyolysis
- Severe muscle breakdown with markedly elevated CK and myoglobinuria (dark, cola-colored urine), risking acute kidney injury.
- Torsades de pointes
- A polymorphic ventricular tachycardia arising from a prolonged QT; treated with intravenous magnesium.
- Vasospastic (Prinzmetal) angina
- Chest pain from coronary artery spasm, often at rest; treated with nitrates and calcium channel blockers, not beta blockers.
- Vaughan Williams classification
- The system that sorts antiarrhythmics by the ion channel they block: I sodium, II beta-adrenergic, III potassium, IV calcium.