Neurologic Disorders: Stroke and Increased Intracranial Pressure
The brain is two percent of body weight and takes twenty percent of the cardiac output, it stores no fuel, and it lives inside a box that cannot expand. Every neurologic emergency in this chapter comes from one of two failures of that arrangement: flow stops, or the box fills. A stroke is flow — a clot that starves tissue or a vessel that ruptures into it — and the clock starts at the moment the patient was last known well, not the moment somebody noticed. Raised intracranial pressure is the box — blood, oedema or cerebrospinal fluid crowding out perfusion until the brainstem is pushed through the tentorium. What makes this content hard for students is that the two conditions share symptoms and share your patient, but the treatments oppose one another: the blood pressure you permit in an ischaemic stroke is the blood pressure that kills in a bleed. Learn the mechanism and the numbers stop being arbitrary.
By the end of this chapter you can
- Differentiate ischaemic from haemorrhagic stroke by mechanism, presentation, imaging and immediate treatment, and explain why only non-contrast CT can tell them apart at the bedside.
- Perform a focused neurologic assessment using level of consciousness, the Glasgow Coma Scale, pupillary response and motor exam, and describe what the NIHSS measures and how its score is used.
- Calculate time from last known well and apply the inclusion and exclusion criteria for intravenous thrombolysis within the 4.5-hour window, including the additional restrictions in the 3–4.5 hour period.
- Explain why blood pressure targets differ between ischaemic stroke (permissive hypertension), post-thrombolysis care, intracerebral haemorrhage and subarachnoid haemorrhage, and name the agents used to reach each target.
- Monitor a patient during and after alteplase or tenecteplase, recognising orolingual angioedema and symptomatic intracranial haemorrhage, and state the nursing actions for each.
- Relate the Monro–Kellie doctrine and cerebral perfusion pressure to every intervention used to lower intracranial pressure, including positioning, hyperosmolar therapy and cerebrospinal fluid drainage.
- Distinguish the early signs of rising intracranial pressure from the late Cushing triad, describe uncal herniation, and explain why prophylactic hyperventilation has been abandoned.
- Prioritise prevention of aspiration pneumonia, venous thromboembolism, pressure injury and shoulder subluxation, and delegate stroke care correctly between the RN, LPN and assistive personnel.
- Teach secondary prevention, escalate red flags using SBAR, and describe how stroke and raised intracranial pressure present differently in the older adult.
Section 1How the Brain Is Perfused and How You Assess It
The arterial map, and what each territory takes away
Two internal carotid arteries carry roughly eighty percent of cerebral blood flow into the anterior circulation; two vertebral arteries join to form the basilar artery and supply the posterior circulation — brainstem, cerebellum, occipital lobes and thalamus. They meet in the circle of Willis, a ring of communicating vessels at the base of the brain. That ring is why some patients occlude a carotid and walk into your unit talking: collateral flow rescued the territory. It is also why the same occlusion in the next patient causes a devastating infarct, because in many people the circle is incomplete. When you hear that a stroke is “bigger than the imaging predicted,” collaterals are usually the reason.
Territory dictates the deficit, and this is the fastest way to make sense of a chaotic first assessment. The middle cerebral artery is the most commonly occluded vessel and supplies the lateral hemisphere, where the face and arm are represented; an MCA stroke produces contralateral face and arm weakness greater than leg weakness, a gaze preference toward the side of the lesion, and, if the dominant hemisphere is involved, aphasia. The anterior cerebral artery supplies the medial surface, where the leg lives; leg weakness out of proportion to the arm, with incontinence and behavioural flatness, suggests ACA. The posterior cerebral artery supplies the occipital lobe and produces a contralateral visual field cut, often with the patient unaware of it.
Posterior circulation strokes are the ones students miss, because the symptoms sound like an inner-ear problem. Dizziness or vertigo, diplopia, dysarthria, dysphagia and dystaxia — the five Ds — plus crossed findings, meaning cranial nerve signs on one side of the face with weakness on the opposite side of the body, are brainstem until proven otherwise. Sudden-onset vertigo with a severe headache and inability to sit unsupported is a cerebellar stroke, and cerebellar strokes swell into the posterior fossa, where there is no room; they obstruct the fourth ventricle and cause hydrocephalus within twenty-four to seventy-two hours. Basilar occlusion can present as fluctuating consciousness and nothing else until the patient is locked in.
Perfusion arithmetic and autoregulation
Two equations carry this entire chapter. Mean arterial pressure is roughly the diastolic pressure plus one third of the pulse pressure, and cerebral perfusion pressure equals mean arterial pressure minus intracranial pressure. Normal intracranial pressure in an adult is 5–15 mmHg; sustained values above 20–22 mmHg are treated. The perfusion target in a patient with an intracranial pressure monitor is a CPP of 60–70 mmHg. Read the equation as a sentence and every intervention becomes obvious: you can raise perfusion by raising the mean arterial pressure or by lowering the intracranial pressure, and every drug, position and drain in this chapter does one of those two things.
Cerebral autoregulation normally holds flow constant across a mean arterial pressure of about 60–150 mmHg by constricting and dilating arterioles. Injured brain loses that ability. In an infarcted or contused region, flow becomes passively dependent on systemic pressure — drop the blood pressure and the tissue is simply less perfused, with no compensatory vasodilation to protect it. This single fact explains permissive hypertension in acute ischaemic stroke, why a hypotensive episode in a stroke patient is corrected urgently rather than tolerated, and why oversedating a head-injured patient can be as harmful as undersedating one.
Carbon dioxide is the most powerful physiologic dilator of cerebral vessels. A rising arterial carbon dioxide level dilates cerebral arterioles, increases cerebral blood volume and raises intracranial pressure; a falling level constricts them and lowers it. That relationship is the mechanism behind hyperventilation therapy, and also behind its abandonment as a routine measure — discussed in Section 4. Oxygen matters too but less linearly: hypoxaemia below a partial pressure of roughly 60 mmHg triggers vasodilation, and hypoxia is directly injurious, so oxygen is titrated to keep saturation above 94 percent and is not given routinely to patients who are already normoxic.
The neurologic assessment that actually changes decisions
Level of consciousness is the earliest and most sensitive indicator of neurologic deterioration — earlier than pupils, earlier than motor changes, far earlier than vital signs. The patient who was oriented at 0800 and is now restless, or who answers correctly but needs you to repeat the question, has changed. Describe what you see rather than labelling it: “opens eyes to name, follows one-step commands, oriented to person only” is documentation another nurse can compare against. Restlessness and agitation in a head-injured patient are neurologic findings, not behavioural problems, and sedating them without assessing is one of the classic errors on this content.
The Glasgow Coma Scale scores eye opening (1–4), verbal response (1–5) and best motor response (1–6) for a total of 3–15. A score of 13–15 is mild injury, 9–12 moderate, and 8 or less is severe — and a GCS of 8 or below is the conventional threshold for intubation, because the patient can no longer protect the airway. Score the best response in the best limb; a hemiplegic patient is scored on the unaffected side. Pupils are the next tier: assess size in millimetres, equality and reaction. Anisocoria greater than 1 mm that is new, a sluggish pupil, or a unilaterally fixed and dilated pupil are all escalation findings, and a fixed dilated pupil in a deteriorating patient is third cranial nerve compression from herniation until proven otherwise. Pinpoint non-reactive pupils suggest a pontine lesion or opioid effect.
Abnormal posturing tells you the level of the injury. Decorticate posturing is flexion of the arms toward the core with extension of the legs and indicates a lesion above the midbrain. Decerebrate posturing is rigid extension and internal rotation of all four limbs and indicates brainstem involvement; it is the worse of the two, and a patient who converts from decorticate to decerebrate is deteriorating. Flaccidity with no response is worse still. Test motor strength by drift — arms out, palms up, eyes closed, ten seconds — because pronator drift catches subtle hemiparesis that a hand squeeze will miss. Never assess “equal hand grips” alone and call it a neuro check.
| Glasgow Coma Scale component | Responses, best score first |
|---|---|
| Eye opening (max 4) | 4 spontaneous · 3 to voice · 2 to pressure · 1 none |
| Verbal response (max 5) | 5 oriented · 4 confused conversation · 3 words only · 2 sounds only · 1 none (record as T if intubated) |
| Motor response (max 6) | 6 obeys commands · 5 localises to pain · 4 withdraws from pain · 3 abnormal flexion (decorticate) · 2 extension (decerebrate) · 1 none |
| Interpretation | 13–15 mild · 9–12 moderate · 8 or less severe; GCS 8 or below generally means intubate |
| Feature | Left (usually dominant) hemisphere stroke | Right hemisphere stroke |
|---|---|---|
| Motor | Right-sided hemiparesis or hemiplegia | Left-sided hemiparesis or hemiplegia |
| Language | Aphasia — expressive (Broca, effortful, non-fluent, aware and frustrated) or receptive (Wernicke, fluent but meaningless, unaware) | Language usually intact; speech may be flat and monotone with poor emotional prosody |
| Perception | Right visual field cut; usually aware of the deficit | Left homonymous hemianopsia and left-sided unilateral neglect; may deny the deficit entirely (anosognosia) |
| Behaviour | Slow, cautious, anxious; high rate of post-stroke depression | Impulsive, distractible, overestimates ability, poor safety judgement |
| Nursing implication | Give time to respond, use yes/no questions and picture boards, never finish sentences for the patient | Highest fall risk on the unit; approach from the unaffected side at first, then teach deliberate visual scanning; never leave unattended in a chair without an alarm and a plan |
Perfusion equals mean arterial pressure minus intracranial pressure, injured brain cannot autoregulate, and a falling level of consciousness is the earliest warning that either side of that equation is going wrong.
Section 2Ischaemic Stroke: The Clock, the Score and the Clot
Mechanism, the penumbra and the transient event
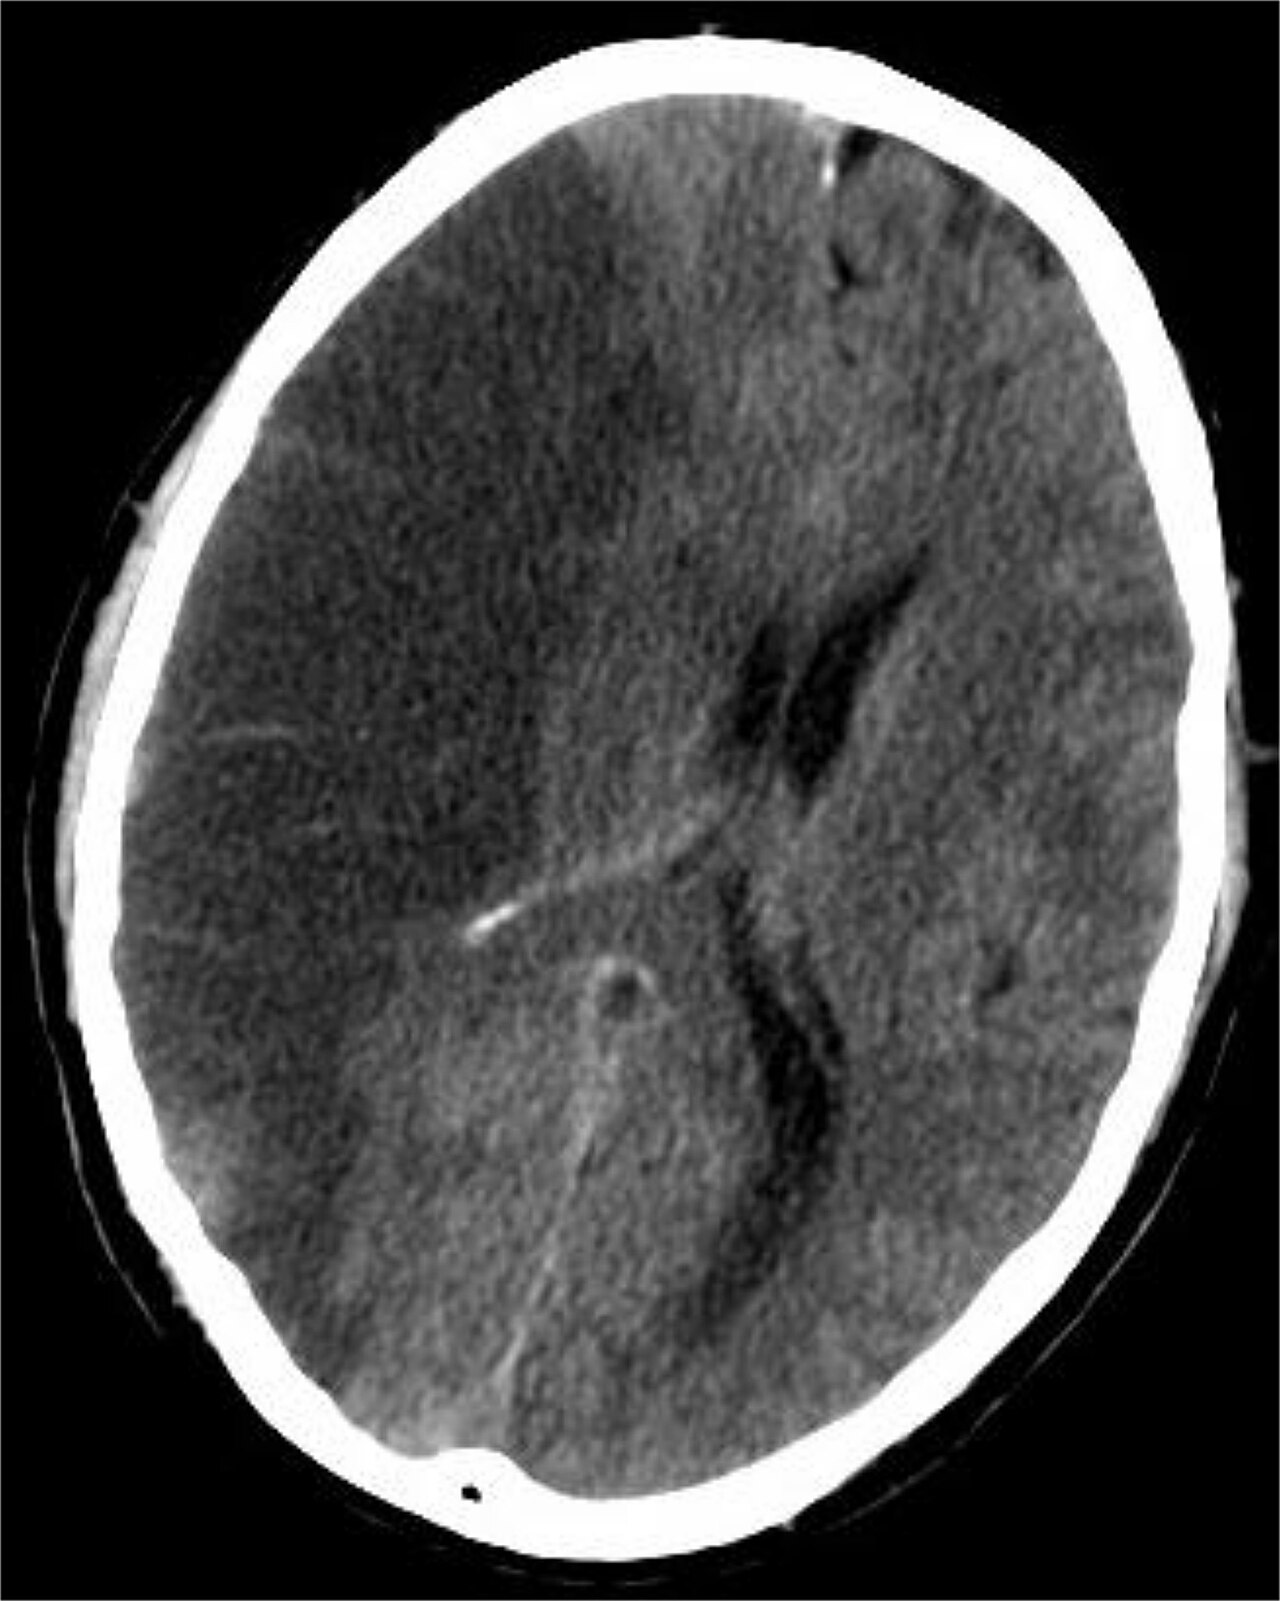
About 87 percent of strokes are ischaemic. The mechanism is either thrombotic — a plaque in a large artery ruptures and clots locally, often producing a stuttering onset that worsens over hours — or embolic, in which a clot travels from elsewhere, most often the left atrium in atrial fibrillation or the carotid bifurcation, and produces a deficit that is maximal at onset. Small-vessel or lacunar strokes occur in the deep penetrating arteries damaged by chronic hypertension and diabetes and produce pure motor or pure sensory syndromes without cortical signs such as aphasia or neglect.
When flow stops, the core of the territory infarcts within minutes. Surrounding it is the ischaemic penumbra — tissue that is electrically silent but structurally alive, kept marginally perfused by collateral vessels. The penumbra is the reason for everything that follows. It is salvageable if flow is restored, and it dies progressively at an estimated rate of roughly 1.9 million neurons per minute. That is the origin of “time is brain,” and it is also why lowering an elevated blood pressure in the first hours can convert penumbra into infarct: those collaterals are pressure-dependent.
A transient ischaemic attack is a focal deficit from ischaemia that resolves — classically within an hour — with no infarction on imaging. It is not a benign event. It is unstable angina for the brain: the risk of completed stroke is highest in the first forty-eight hours and roughly three to five percent in the first two days. A TIA gets the same urgent workup as a stroke: imaging, carotid imaging, echocardiography, prolonged cardiac rhythm monitoring for occult atrial fibrillation, lipids and glucose. Do not let a patient whose symptoms resolved in triage go home without that workup being arranged.
The hyperacute pathway: what happens in the first sixty minutes
The single most important piece of history is last known well — the last moment anyone observed the patient at neurologic baseline, not the time symptoms were discovered. A patient who went to bed at 2200 fine and woke at 0600 with weakness was last known well at 2200, which is eight hours, not one. Get a phone number for the person who saw them last and get it before the patient leaves your area. Ask about anticoagulants, recent surgery, recent stroke or head trauma, and known bleeding disorders, because those are the exclusions you will need in ten minutes.
Concurrent priorities, not sequential ones: airway and breathing, oxygen only if saturation is below about 94 percent, cardiac monitoring, two large-bore intravenous lines, and a point-of-care glucose. Hypoglycaemia is the great stroke mimic and will resolve with dextrose; hyperglycaemia worsens outcome, and glucose is targeted to 140–180 mg/dL. Draw a complete blood count, coagulation studies, basic metabolic panel and troponin, get a twelve-lead ECG, and obtain an emergent non-contrast head CT. The CT is not there to prove infarction — early ischaemia is often invisible — it is there to exclude haemorrhage, because thrombolysis into a bleed is lethal. Do not delay the CT for laboratory results; in a patient with no anticoagulant history and no bleeding history, only the glucose must be back before thrombolysis. CT angiography follows to identify a large-vessel occlusion, and CT perfusion is used to define core and penumbra when the patient is outside the standard window.
The National Institutes of Health Stroke Scale is an eleven-item, 42-point standardised examination that scores consciousness, gaze, visual fields, facial palsy, arm and leg motor strength, limb ataxia, sensation, language, dysarthria and extinction or inattention. Higher is worse. It is not a diagnostic test and it does not decide treatment by itself; it quantifies severity, it standardises handoff between clinicians, it flags large-vessel occlusion when the score is high, and it is repeated so that any change is measurable rather than impressionistic. Note that a posterior circulation stroke can be devastating with a low NIHSS, because the scale is weighted toward hemispheric function. Institutional door-to-needle goals are 60 minutes or less, and many stroke centres now target 30 to 45.
| NIHSS total | Severity band | Practical meaning |
|---|---|---|
| 0 | No stroke symptoms | Deficit resolved or below detection; still work up as TIA |
| 1–4 | Minor | Candidate for short-course dual antiplatelet therapy when the NIHSS is 3 or less and no thrombolytic was given; still disabling if it is the dominant hand or speech |
| 5–15 | Moderate | Typical thrombolysis population |
| 16–20 | Moderate to severe | Strong suspicion of large-vessel occlusion; alert the thrombectomy team |
| 21–42 | Severe | Large territory at risk; anticipate airway compromise and malignant cerebral oedema at 48–72 hours |
Thrombolysis: who gets it, how it is given, and the twenty-four hours after
Alteplase is given at 0.9 mg/kg to a maximum total dose of 90 mg, with ten percent of the dose as an intravenous bolus over one minute and the remainder infused over sixty minutes. Many centres now use tenecteplase at 0.25 mg/kg to a maximum of 25 mg as a single bolus, which is faster to give and simplifies transfer for thrombectomy. The treatment window is within 4.5 hours of last known well; the 0–3 hour period uses the standard criteria, and the 3–4.5 hour period adds further exclusions. Weight matters: get an actual or best-estimate weight, because these are milligram-per-kilogram drugs and an overdose is an intracranial haemorrhage.
Blood pressure must be below 185/110 mmHg before thrombolysis begins and maintained below 180/105 mmHg for the following twenty-four hours. Labetalol 10–20 mg intravenously over one to two minutes, repeated once if needed, or a nicardipine infusion starting at 5 mg/hour and titrated by 2.5 mg/hour every five to fifteen minutes to a maximum of 15 mg/hour, are the standard agents. Nitroprusside and nitroglycerin are avoided as first-line agents because they dilate cerebral vessels and can raise intracranial pressure. If you cannot get the pressure safely under 185/110 and keep it there, the patient is not a thrombolysis candidate.
Nursing care during and after the infusion is where students earn their keep. Monitor blood pressure and perform neurologic checks every 15 minutes during the infusion and for two hours after it starts, then every 30 minutes for six hours, then hourly until twenty-four hours. Give no antiplatelet or anticoagulant for twenty-four hours, and repeat imaging at twenty-four hours before starting any antithrombotic. Avoid arterial punctures at non-compressible sites, avoid intramuscular injections, and defer indwelling urinary catheters and nasogastric tubes where clinically possible. Assess the tongue and lips about twenty minutes into the infusion for orolingual angioedema, which occurs in roughly one to five percent of patients, is more common in those taking an ACE inhibitor, and is often worse on the side opposite the infarct. This is the one thrombolysis complication where imaging is irrelevant and the airway is everything, because the swelling can close it within minutes. Assess the airway immediately and keep assessing it. Swelling confined to the anterior tongue or lip may be observed closely; swelling that is progressing, that involves the posterior tongue, oropharynx or larynx, or that produces stridor or any change in voice means stop the infusion and call for airway support early — anaesthesia or the difficult-airway team at the bedside, awake fibreoptic or nasotracheal intubation preferred, cricothyrotomy equipment ready. Give intravenous methylprednisolone, intravenous diphenhydramine and an H2 blocker such as famotidine, and add intramuscular epinephrine if there is no response and no contraindication. Hold the patient’s ACE inhibitor. A sudden severe headache, acute hypertension, nausea and vomiting, or any new neurologic deterioration means stop the infusion, obtain an emergent non-contrast head CT, and notify the provider — in that order, and you can do the first two while someone else pages. Anticipate a stat fibrinogen level, type and crossmatch, reversal with cryoprecipitate or fibrinogen concentrate, and neurosurgical consultation.
| Category | Criteria for intravenous thrombolysis in acute ischaemic stroke |
|---|---|
| Inclusion | Disabling neurologic deficit consistent with ischaemic stroke; treatment can begin within 4.5 hours of last known well; age 18 or older; non-contrast CT excludes haemorrhage |
| Absolute exclusions | Any intracranial haemorrhage on CT or by history; symptoms suggesting subarachnoid haemorrhage; ischaemic stroke, serious head trauma, or intracranial or intraspinal surgery within 3 months; intracranial neoplasm, arteriovenous malformation or aneurysm; active internal bleeding; suspected aortic arch dissection; infective endocarditis; blood pressure that cannot be lowered below 185/110 mmHg; CT hypodensity involving more than one third of the hemisphere |
| Haematologic exclusions | Platelet count below 100,000/mm³; INR above 1.7 or prothrombin time above 15 seconds; aPTT above 40 seconds or heparin within 48 hours with elevated aPTT; treatment-dose low-molecular-weight heparin within 24 hours; a direct oral anticoagulant within 48 hours unless coagulation testing is normal |
| Correct and reassess | Blood glucose below 50 mg/dL — treat and re-examine; if the deficit resolves it was hypoglycaemia, if it persists the patient may still be eligible |
| Additional exclusions, 3–4.5 hour window | Age over 80 years; NIHSS above 25; use of any oral anticoagulant regardless of INR; history of both diabetes mellitus and prior ischaemic stroke |
| Non-compressible arterial puncture | Within the previous 7 days — relative exclusion, weigh risk against benefit |
Thrombectomy, and the blood pressure question that decides everything
Mechanical thrombectomy retrieves the clot through a femoral or radial catheter and is indicated for large-vessel occlusion of the internal carotid or proximal middle cerebral artery. The standard window is within six hours of last known well; selected patients with favourable perfusion imaging — a small infarct core and a large salvageable penumbra — are treated out to twenty-four hours. Thrombolysis and thrombectomy are not alternatives: an eligible patient gets the drug and goes to the angiography suite. Post-procedure nursing includes groin site and distal pulse checks, bed rest with the affected leg straight per protocol, and neurologic checks at the same frequency as post-thrombolysis care, because reperfusion haemorrhage is the feared complication.
Now the point students most often get wrong. In an acute ischaemic stroke patient who is not receiving thrombolysis, hypertension is largely protective and is permitted — permissive hypertension. Treatment is generally withheld unless the pressure exceeds 220/120 mmHg, and even then the goal is a gentle reduction of about fifteen percent over the first twenty-four hours. The collateral vessels keeping the penumbra alive are pressure-dependent; an aggressive antihypertensive extends the infarct. The exceptions are the patient receiving a thrombolytic, in whom bleeding risk dominates, and the patient with a concurrent problem that demands lower pressure such as aortic dissection, acute coronary syndrome, acute heart failure or hypertensive encephalopathy.
Contrast this with haemorrhage. In an intracerebral bleed the vessel is already open; the pressure that maintains collateral flow in ischaemia instead expands the haematoma. So the target reverses. This is the single most testable comparison in neurologic nursing, and it is worth writing down until it is reflexive.
| Situation | Blood pressure target | Why |
|---|---|---|
| Ischaemic stroke, no thrombolytic | Treat only if above 220/120 mmHg; then lower about 15 percent in 24 hours | Penumbral collateral flow is pressure-dependent; lowering pressure grows the infarct |
| Before thrombolysis | Must be below 185/110 mmHg | Higher pressure plus a fibrinolytic multiplies intracranial haemorrhage risk |
| For 24 hours after thrombolysis | Keep below 180/105 mmHg | Same reason; the drug is still active and the tissue is freshly reperfused |
| Intracerebral haemorrhage, presenting systolic 150–220 mmHg | Lower systolic to approximately 140 mmHg (a 130–150 range); avoid dropping below 130 | Reduces haematoma expansion; excessive lowering risks hypoperfusion |
| Subarachnoid haemorrhage, aneurysm not yet secured | Systolic below 160 mmHg | Rebleeding risk is highest in the first 24 hours and rebleeding is frequently fatal |
| After vasospasm develops in SAH | Induced hypertension with euvolaemia, aneurysm already secured | The problem is now too little flow, not too much pressure |
Establish last known well, exclude haemorrhage with non-contrast CT, treat within 4.5 hours if criteria are met, and remember that blood pressure is permitted high in untreated ischaemic stroke but must be below 185/110 before a thrombolytic and below 180/105 for the next twenty-four hours.
Section 3Haemorrhagic Stroke: Intracerebral and Subarachnoid
Intracerebral haemorrhage: stop the expansion, reverse the anticoagulant
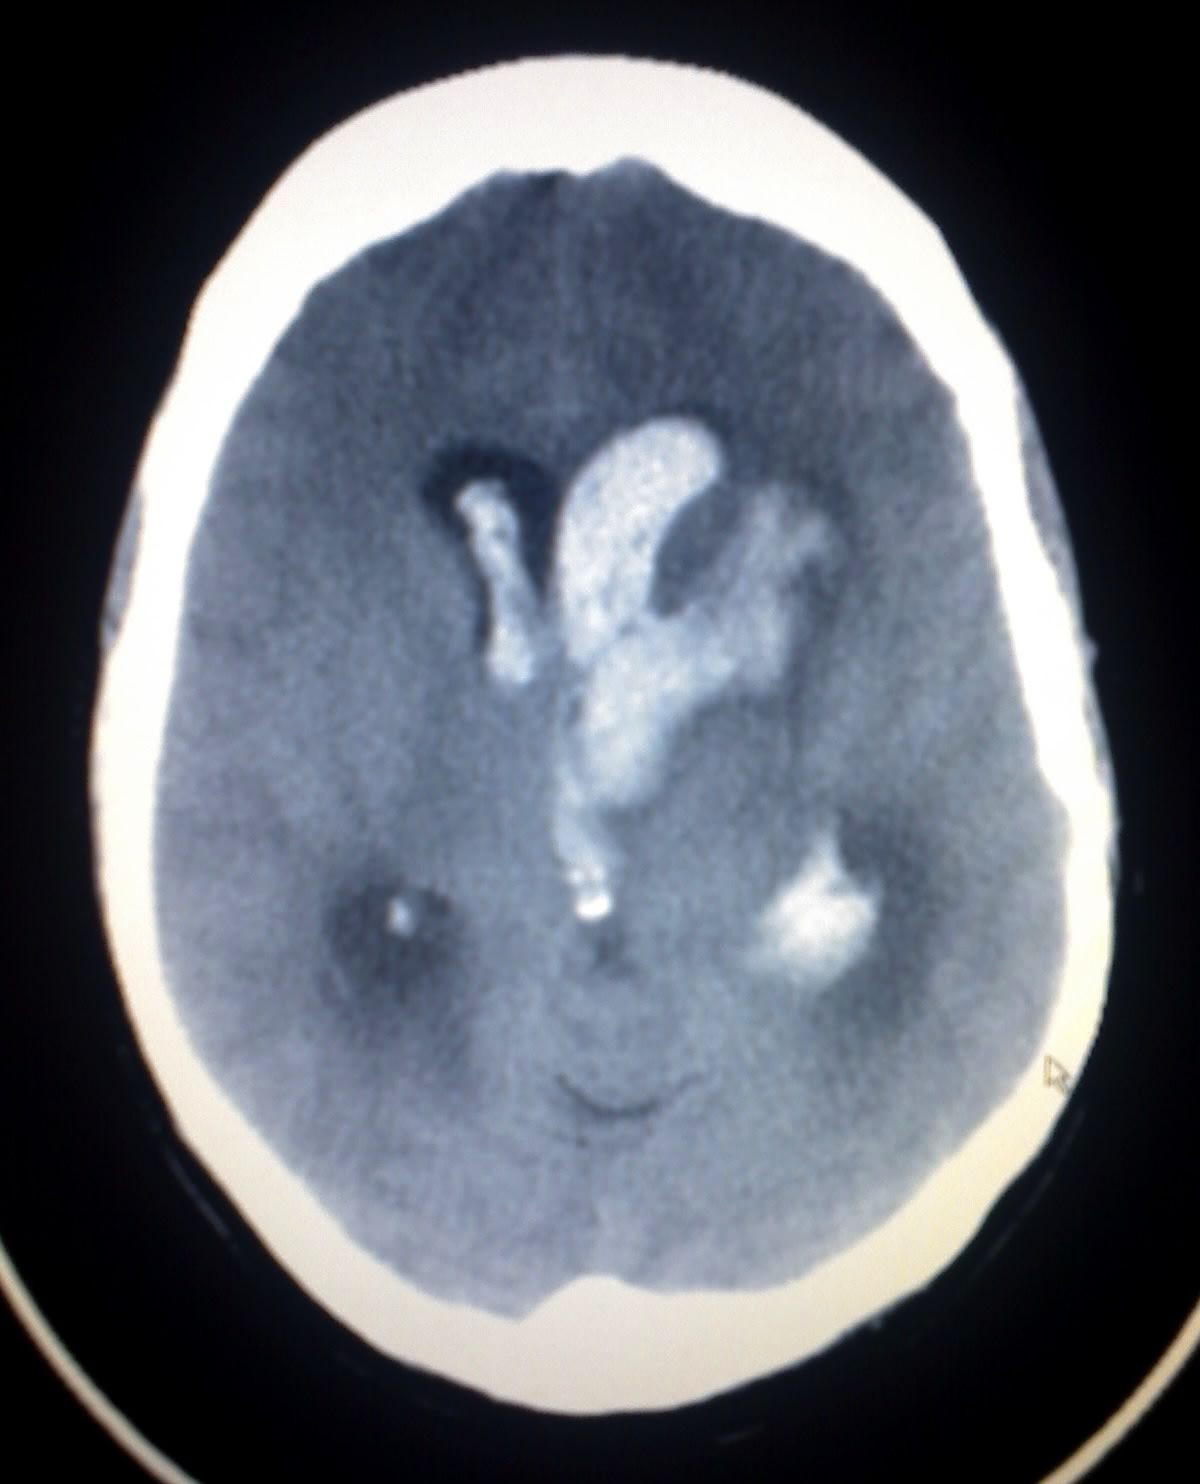
Intracerebral haemorrhage accounts for roughly ten percent of strokes and carries the highest thirty-day mortality of any stroke subtype. The commonest cause is chronic hypertension damaging the small penetrating arteries of the basal ganglia, thalamus, pons and cerebellum; in older adults, cerebral amyloid angiopathy produces lobar bleeds; anticoagulants, arteriovenous malformations, tumours and sympathomimetic drug use account for most of the rest. The presentation differs from ischaemia in tempo and company: a deficit that worsens progressively over minutes to hours, accompanied by severe headache, vomiting, markedly elevated blood pressure and early depression of consciousness, is a bleed until CT says otherwise. But no clinical rule is reliable enough to act on — the CT decides.
The first hours are about preventing haematoma expansion, which occurs in up to a third of patients and independently predicts death and disability. Three actions matter. First, blood pressure: for a patient presenting with systolic pressure between 150 and 220 mmHg, lowering to approximately 140 mmHg is reasonable and safe, using a titratable agent such as nicardipine or clevidipine rather than intermittent boluses that overshoot. Avoid dropping the systolic below 130. Second, reverse anticoagulation immediately and check the medication list yourself rather than trusting the triage note. Warfarin is reversed with four-factor prothrombin complex concentrate plus vitamin K 10 mg intravenously — the vitamin K is essential because the concentrate wears off long before the warfarin does. Dabigatran is reversed with idarucizumab. Apixaban and rivaroxaban are reversed with andexanet alfa where available or four-factor prothrombin complex concentrate. Third, correct any coagulopathy and treat platelet counts below 100,000/mm³; routine platelet transfusion for a patient on aspirin or clopidogrel is not recommended and may worsen outcomes.
Beyond that, care is neurocritical: head of bed at 30 degrees with the head midline, normothermia, glucose 140–180 mg/dL, isotonic fluids only, seizure treatment if seizures occur (prophylactic antiseizure medication is not routine), and serial neurologic examinations with repeat imaging for any change. Surgery is selective. Cerebellar haemorrhage larger than about 3 cm, or any cerebellar bleed causing brainstem compression or hydrocephalus, is a neurosurgical emergency because the posterior fossa has no reserve space. Supratentorial clot evacuation is considered case by case, and an external ventricular drain is placed for intraventricular extension with hydrocephalus.
Subarachnoid haemorrhage: the worst headache, the rebleed and the spasm
Subarachnoid haemorrhage is most often aneurysmal, and the classic history is a thunderclap headache — sudden, maximal within seconds, described as the worst headache of the patient’s life — often with brief loss of consciousness, vomiting, photophobia and nuchal rigidity from meningeal irritation. Up to half of patients report a lesser sentinel headache in the preceding days or weeks, a warning leak that was dismissed as a migraine. Focal deficits may be absent entirely. Non-contrast CT within six hours of onset detects nearly all cases; if the CT is negative and suspicion remains, lumbar puncture looks for xanthochromia and for red cells that do not clear between the first and fourth collection tubes. CT angiography or catheter angiography then defines the aneurysm.
The three killers, in order of appearance, are rebleeding, hydrocephalus and vasospasm. Rebleeding risk is highest in the first twenty-four hours and is frequently fatal, so the aneurysm is secured early by endovascular coiling or surgical clipping, and until it is secured the systolic pressure is kept below 160 mmHg with the patient on strict bed rest, in a quiet dim room, with stool softeners, analgesia and antiemetics — anything that provokes a Valsalva manoeuvre or a pressure surge is removed from the environment. Acute hydrocephalus from blood obstructing cerebrospinal fluid pathways presents as declining consciousness and is treated with an external ventricular drain.
Cerebral vasospasm is the delayed catastrophe, typically beginning on day 3 and peaking between days 4 and 14. Breakdown products of subarachnoid blood irritate the arteries into narrowing, producing delayed cerebral ischaemia. It is detected by a new focal deficit, a new confusion, or rising velocities on transcranial Doppler — and the nurse who notices that a previously alert patient is now inattentive on day 7 is the one who catches it. Every aneurysmal SAH patient receives nimodipine 60 mg orally or by nasogastric tube every 4 hours for 21 days. Three points about nimodipine are non-negotiable. It is a calcium channel blocker but it improves neurologic outcome by mechanisms beyond simple vasodilation, so it is given even if angiography looks fine. It must never be given intravenously — inadvertent intravenous administration of the oral capsule contents has caused cardiac arrest and death. And it lowers blood pressure, so check the pressure before every dose and hold or split the dose per protocol rather than pushing through hypotension. Established vasospasm is treated with euvolaemia and induced hypertension once the aneurysm is secured, and with endovascular angioplasty or intra-arterial vasodilators when medical therapy fails; the old triple-H protocol of hypertension, hypervolaemia and haemodilution has been abandoned because the volume loading caused pulmonary oedema without benefit.
Sodium, the heart and the rest of the body
Hyponatraemia occurs in up to a third of subarachnoid haemorrhage patients and has two very different causes that require opposite treatments. The syndrome of inappropriate antidiuretic hormone retains water; the patient is euvolaemic or slightly hypervolaemic with concentrated urine, and outside the brain-injured patient the treatment is fluid restriction. Cerebral salt wasting dumps sodium and water renally; the patient is hypovolaemic with a negative fluid balance, high urine output and high urine sodium, and treatment is sodium and volume replacement with isotonic or hypertonic saline. In aneurysmal subarachnoid haemorrhage the two cannot be reliably separated at the bedside, and the rule is the same whichever it is: correct the sodium while keeping the patient euvolaemic — isotonic or hypertonic saline, sodium supplementation, and fludrocortisone or hydrocortisone — and do not fluid-restrict. Hypovolaemia and a negative fluid balance are associated with delayed cerebral ischaemia, and the days the sodium falls are exactly the days vasospasm appears, so fluid-restricting a salt-waster in that window drops cerebral perfusion at the worst possible moment. Reserve the fluid-restriction rule for SIADH outside the subarachnoid haemorrhage and vasospasm setting. Assess volume status — intake and output, daily weights, orthostatic changes, central venous pressure if monitored — before assuming SIADH. Correct chronic hyponatraemia no faster than 8 mEq/L in 24 hours to avoid osmotic demyelination.
Neurogenic pulmonary oedema and stress cardiomyopathy occur after severe subarachnoid haemorrhage from a catecholamine surge; expect ST changes, T-wave inversions, prolonged QT and a rising troponin in a patient with normal coronary arteries. Report them, but do not let a positive troponin distract the team from the brain. Fever is common and is often central rather than infectious; treat it anyway, because every degree of fever raises cerebral metabolic demand. Screen for and treat hyperglycaemia. Deep vein thrombosis prophylaxis begins with intermittent pneumatic compression on admission; pharmacologic prophylaxis is added after the bleed is stable and the aneurysm secured, generally after 24 to 48 hours and always by provider order.
Families need honest, repeated, plain-language information here more than in almost any other diagnosis, because a young patient can be neurologically catastrophic within hours of a normal morning. Prepare them for the intensive care environment, for the drains and the monitors, and for the fact that the patient may look stable on day two and deteriorate on day seven from vasospasm. Chapter 14 revisits goals-of-care conversations; the groundwork for them starts on day one.
In haemorrhagic stroke the vessel is already broken, so the systolic pressure is driven down toward 140 mmHg, anticoagulation is reversed immediately, and in aneurysmal subarachnoid haemorrhage nimodipine is given enterally every four hours for twenty-one days to blunt the vasospasm that peaks on days 4 to 14.
Section 4Increased Intracranial Pressure, Herniation and Neurocritical Care
Monro–Kellie, compensation and the cliff
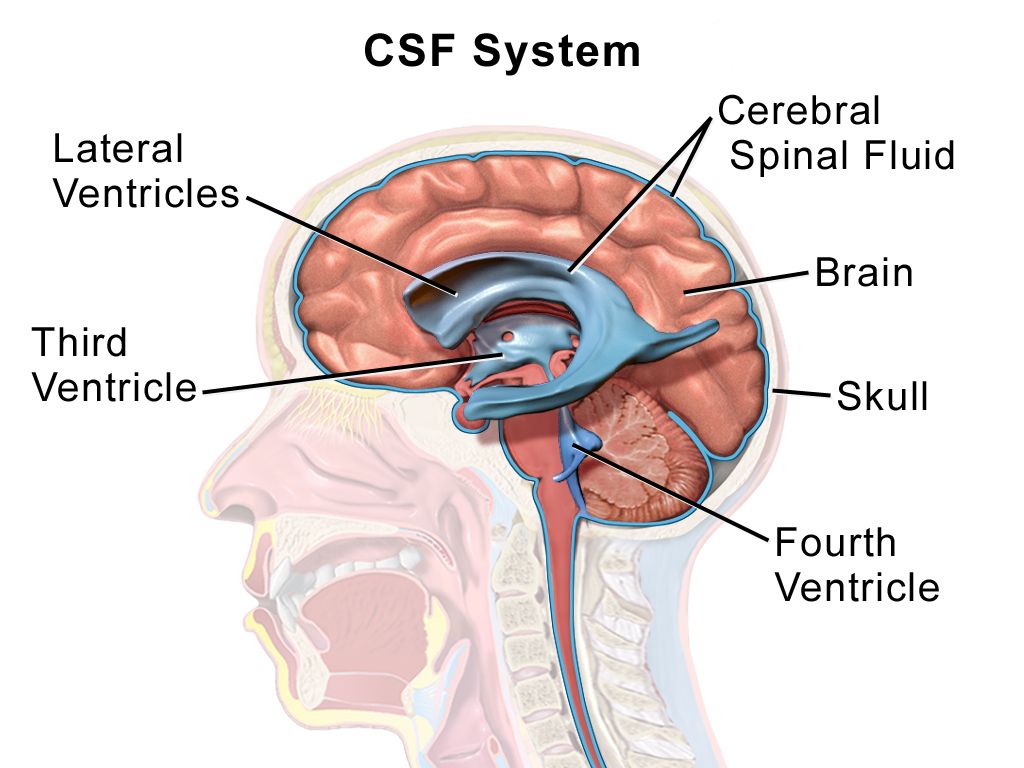
The Monro–Kellie doctrine states that the cranial vault is a fixed volume containing three components: brain tissue at roughly 80 percent, blood at about 10 percent and cerebrospinal fluid at about 10 percent. Because the container cannot expand, an increase in any one component must be matched by a decrease in another or the pressure rises. The brain compensates first by displacing cerebrospinal fluid into the spinal subarachnoid space and increasing its absorption, then by shunting venous blood out of the cranium. These mechanisms buy real time — which is exactly why a patient can look deceptively well while a haematoma grows.
Compensation is finite, and the pressure–volume relationship is not a straight line. Early on, a large added volume raises pressure very little. Once compensation is exhausted, a tiny additional volume — a coughing spell, a poorly timed suction pass, a few more millilitres of clot — produces a steep, sometimes catastrophic rise. That curve explains the clinical experience of a patient who is stable, stable, stable, then suddenly not. It also explains why the interventions in this section look trivial individually: each removes a few millilitres of volume, and near the cliff a few millilitres is the difference.
Causes fall into predictable buckets: mass lesions (haematoma, tumour, abscess), cerebral oedema (cytotoxic oedema after ischaemia and hypoxia, vasogenic oedema around tumours and abscesses), increased cerebrospinal fluid from hydrocephalus, and increased cerebral blood volume from hypercapnia, hypoxia, seizure, fever or venous outflow obstruction. Note that the last bucket is the one nursing care directly controls, which is the point of everything that follows.
Early signs, and why the Cushing triad is too late to be useful as a warning
The earliest sign of rising intracranial pressure is a change in level of consciousness: restlessness, irritability, confusion, needing louder or more repeated stimulation to rouse. Headache, often worse in the morning and worse with coughing or bending, and vomiting that may be projectile and unaccompanied by nausea follow. Pupillary changes come next — a sluggish pupil, then a unilaterally dilated one. Then motor changes: worsening hemiparesis, then abnormal posturing. Papilloedema on funduscopy is a real sign but a late and unreliable one at the bedside.
The Cushing triad — rising systolic pressure with a widening pulse pressure, bradycardia, and irregular or abnormal respirations — is a brainstem reflex to preserve cerebral perfusion when the pressure has already risen dangerously. It is a late sign of impending or ongoing herniation, not an early warning. If you are waiting for the Cushing triad to call the provider, you have waited too long. Be careful how you carry that into an examination question. When the Cushing triad is one of the options it is never the distractor: irregular respirations with bradycardia and a widening pulse pressure mean herniation is happening now, and under airway-breathing-circulation that is the patient you go to first. The teaching point runs the other way. When every option is still subtle, the newly drowsy or newly difficult-to-arouse patient is the one to escalate, because that is the finding that still leaves you time to act before the triad ever appears. Both require action; only one gives you time.
Herniation is displacement of brain across a dural boundary. Uncal (transtentorial) herniation compresses the third cranial nerve, producing an ipsilateral fixed, dilated pupil with contralateral hemiparesis and declining consciousness — the classic “blown pupil.” Central herniation produces progressive rostral-to-caudal deterioration. Tonsillar herniation forces the cerebellar tonsils through the foramen magnum onto the medulla and causes respiratory arrest and death. This is why a lumbar puncture is contraindicated when a mass lesion with raised pressure is suspected: removing fluid from below creates a pressure gradient that pulls the brain downward.
| Timing | Findings | What you do |
|---|---|---|
| Earliest | Restlessness, irritability, confusion, decreased arousal, subtle disorientation | Full neurologic assessment, vital signs, glucose, oxygenation; notify the provider now |
| Early | Headache worse with cough or bending, vomiting without nausea, blurred or double vision | Head of bed 30 degrees, head midline, antiemetic, minimise stimulation, escalate |
| Progressing | Sluggish then unilaterally dilated pupil, worsening hemiparesis, decorticate posturing | Emergent CT, prepare hyperosmolar therapy, alert neurosurgery, prepare for airway management |
| Late | Cushing triad: widening pulse pressure with rising systolic, bradycardia, irregular respirations; decerebrate posturing; fixed dilated pupil | Herniation is occurring — rapid response, airway, hypertonic saline or mannitol, immediate neurosurgical involvement |
| Terminal | Flaccidity, apnoea, bilateral fixed pupils | Full resuscitation per goals of care; outcome is usually determined |
Lowering the pressure: nursing measures, osmotherapy, ventilation and drains
Nursing measures are not filler; they are the first tier of treatment because they reduce cerebral blood volume by improving venous drainage. Keep the head of the bed at 30 degrees, the head in midline neutral alignment, and the neck free of tight tracheostomy ties or cervical collars — head rotation or neck flexion kinks the jugular veins and can raise intracranial pressure measurably. Avoid extreme hip flexion, which raises intra-abdominal and thus intrathoracic pressure. Prevent Valsalva: stool softeners, no straining, no vigorous coughing, and instruct patients not to hold their breath while repositioning. Preoxygenate before suctioning and limit each pass to ten seconds or less; suctioning is a potent pressure spike. Space nursing activities rather than clustering them — unlike most of your care, several stimulating tasks in a row are harmful here. Keep the room quiet and dim, treat pain and agitation (untreated pain raises pressure; oversedation removes your ability to assess), and treat fever aggressively toward normothermia because pyrexia raises cerebral metabolic demand. Use isotonic fluids only. Hypotonic fluids — dextrose 5 percent in water, half-normal saline — move free water into brain tissue and worsen oedema.
Hyperosmolar therapy draws water out of brain tissue across an intact blood–brain barrier. Mannitol 0.25–1 g/kg is infused over 15 to 30 minutes through a filter, because the solution crystallises; inspect every bag and never give one containing visible crystals. Mannitol is an osmotic diuretic, so it causes brisk urine output — an indwelling catheter is generally required — and it can produce hypovolaemia, hypotension, electrolyte disturbance and acute kidney injury. Monitor serum osmolality and hold the dose if it exceeds about 320 mOsm/kg, and watch the sodium, potassium and renal function. Hypertonic saline at 3 percent is infused to a target serum sodium of roughly 145–155 mEq/L with sodium checked every six hours; 23.4 percent hypertonic saline is given as a small bolus for acute herniation and must go through a central line. Hypertonic saline is often preferred in the hypotensive or hypovolaemic patient because it expands rather than depletes intravascular volume. Corticosteroids such as dexamethasone reduce the vasogenic oedema of tumours and abscesses; they are ineffective in ischaemic stroke and harmful in traumatic brain injury, and this distinction is heavily tested.
Hyperventilation is no longer routine. The physiology is real — lowering arterial carbon dioxide constricts cerebral arterioles, reduces cerebral blood volume and drops the pressure within minutes — but the effect is the problem. That vasoconstriction reduces cerebral blood flow to tissue that is already ischaemic, the benefit wanes within hours as bicarbonate buffering equilibrates, and rebound vasodilation follows when the carbon dioxide is allowed to normalise. Prolonged prophylactic hyperventilation worsens outcomes. Current practice keeps the arterial carbon dioxide in the normal 35–45 mmHg range and reserves brief, targeted hyperventilation to 30–35 mmHg as a rescue bridge for acute herniation while definitive therapy — osmotherapy, cerebrospinal fluid drainage, the operating room — is being arranged. Do not hyperventilate a head-injured patient with a bag-valve mask because it feels like doing something.
An external ventricular drain both monitors pressure and treats it by removing cerebrospinal fluid. The transducer and drip chamber are levelled to the foramen of Monro, approximated externally at the tragus of the ear or the outer canthus of the eye, and re-levelled every time the bed height or patient position changes — an unlevelled drain gives you a false number and can over-drain, which collapses ventricles and can cause a subdural haemorrhage. Close the drain before repositioning, before transport, and before any activity that raises pressure, then reopen it and document. Report cloudy drainage, a new fever or a sudden change in output volume. Maintain sterile technique religiously; ventriculitis is a devastating complication. Refractory pressure may require decompressive craniectomy, barbiturate coma with continuous electroencephalographic monitoring, or targeted temperature management.
The skull cannot expand, so a falling level of consciousness is the early warning and the Cushing triad is the late one; treat with midline positioning, venous drainage, hyperosmolar therapy and cerebrospinal fluid drainage, and reserve hyperventilation as a brief rescue rather than a routine.
Section 5From the First Seventy-Two Hours to Discharge
The swallow screen and the complication that kills most stroke patients
Dysphagia affects roughly half of acute stroke patients, and aspiration pneumonia is the leading preventable cause of death in the first weeks. The rule is absolute: keep the patient nil by mouth — no food, no fluids, not even the sip of water used to take a tablet — until a swallow screen has been passed. A validated bedside screen typically checks alertness, ability to sit upright, voice quality, volitional cough and a graded water trial, watching for coughing, throat clearing, a wet or gurgly voice, or a drop in oxygen saturation. Failing the screen means a formal speech-language pathology evaluation and possibly a videofluoroscopic swallow study. Silent aspiration — no cough at all — is common in stroke, so absence of coughing is not reassurance.
Once cleared, position the patient fully upright at 90 degrees for meals and for at least 30 minutes afterward, use the recommended texture and liquid consistency exactly as prescribed, feed slowly with small bites, place food on the unaffected side of the mouth, check for pocketing after every few bites, and perform oral care at least twice a day — oral hygiene measurably reduces pneumonia rates. Avoid straws unless specifically approved, and never rush a meal. If a patient will be unable to swallow safely for more than a few days, enteral feeding is started rather than allowing a week of malnutrition.
Other early complications cluster in a predictable order. Venous thromboembolism prevention begins with intermittent pneumatic compression on admission and early mobilisation. In ischaemic stroke that was not treated with a thrombolytic, prophylactic-dose subcutaneous heparin or low-molecular-weight heparin is started promptly — generally within 24 to 48 hours of admission — once the initial non-contrast CT has excluded haemorrhage, and no repeat scan is required first. It is only after intravenous thrombolysis that every antithrombotic, prophylactic dosing included, is deferred for 24 hours and until follow-up imaging is clear; in haemorrhagic stroke it waits until the haematoma is stable. Malignant cerebral oedema after a large middle cerebral artery infarct peaks between 48 and 72 hours — the patient who deteriorates on hospital day two or three is swelling, not re-stroking. Haemorrhagic transformation of an infarct, urinary retention and infection, pressure injury over the affected heel and sacrum, constipation, seizures and post-stroke depression all belong on the care plan from day one.
Mobility, the affected side and the mind
Protect the hemiplegic shoulder. The affected arm has no muscular support for the glenohumeral joint, and shoulder subluxation with a painful frozen shoulder is common and preventable. Never pull on the affected arm to reposition or transfer, support it on a pillow or lap tray when the patient is sitting, use a sling only as prescribed and not continuously, and perform passive range of motion within the prescribed limits. Position to prevent contracture and foot drop, turn at least every two hours, and inspect skin at every turn — the affected side has impaired sensation and the patient will not report the pain that would normally prompt a shift in position.
Unilateral neglect after a right hemisphere stroke and homonymous hemianopsia are safety issues, not curiosities. A patient who eats half the plate, shaves half the face and walks into the doorframe on the left is at high risk of falls and injury. Initially set up the environment on the unaffected side so the patient can function, then progressively teach deliberate head-turning and visual scanning toward the neglected side; a rehabilitation programme moves toward re-integration rather than permanent accommodation. Approach an impulsive right-hemisphere patient with structure, short instructions and constant supervision; they will attempt to stand and walk without warning and without insight into the deficit.
Post-stroke depression affects roughly a third of survivors and is under-recognised because clinicians attribute flat affect to the stroke itself. Screen for it, treat it, and tell families that emotional lability — sudden crying or laughing disproportionate to the situation — can be a neurologic symptom rather than grief. Communication support matters just as much: with expressive aphasia allow time and use yes/no questions, communication boards and gestures; with receptive aphasia use short simple sentences, one idea at a time, demonstration and consistent word choices. Speak to the patient, not about the patient.
| Task | RN | LPN/LVN | Assistive personnel |
|---|---|---|---|
| Initial and ongoing neurologic assessment, NIHSS, GCS | Yes | No | No |
| Bedside swallow screen before first oral intake | Yes (per policy, RN or SLP) | No | No |
| Administering and monitoring a thrombolytic | Yes | No | No |
| Care of the unstable or deteriorating patient | Yes | No | No |
| Patient and family teaching, evaluation of response | Yes | Reinforce only | No |
| Routine oral and enteral medications on a stable patient | Yes | Yes | No |
| Reinforcing a prescribed swallowing technique on a screened, stable patient | Yes | Yes | Feeding assistance only after the RN has assessed and set up |
| Vital signs on a stable patient, hygiene, turning, transfers, applying compression devices, intake and output, prescribed passive range of motion | Yes | Yes | Yes — with clear reporting parameters |
Secondary prevention, teaching and the older adult
Every ischaemic stroke or TIA patient leaves on antithrombotic therapy matched to the mechanism. For a non-cardioembolic stroke that is aspirin 81–325 mg daily or clopidogrel; after a minor stroke with an NIHSS of 3 or less or a high-risk TIA, dual antiplatelet therapy with aspirin plus clopidogrel is given for about 21 days and then stepped down to a single agent, because continuing both long-term increases bleeding without further benefit. For stroke with atrial fibrillation the answer is anticoagulation, and a direct oral anticoagulant — apixaban, rivaroxaban, edoxaban or dabigatran — is preferred over warfarin except in mechanical heart valves and moderate-to-severe mitral stenosis, where warfarin with an INR of 2.0–3.0 remains standard. High-intensity statin therapy, typically atorvastatin 80 mg, is standard regardless of the baseline cholesterol. Blood pressure control, glycaemic control, smoking cessation, weight and activity, and carotid endarterectomy or stenting for symptomatic stenosis of 70–99 percent complete the package.
Teaching should end with something the family can act on at 0300. Teach BE-FAST — Balance loss, Eyes or vision change, Face drooping, Arm weakness, Speech difficulty, Time to call emergency services — and be explicit that they call an ambulance rather than driving, because prehospital notification starts the stroke pathway before arrival. Teach that symptoms which resolve still require a 911 call. Review each medication by purpose and by the specific thing that would make them call: bleeding on an anticoagulant, muscle pain on a statin, dizziness on an antihypertensive. Confirm follow-up with neurology, primary care and outpatient therapy, arrange home safety modification, and address driving restrictions honestly — visual field cuts and neglect are legal and practical barriers, and the conversation is easier before discharge than after a crash.
Older adults present differently and you must adjust the index of suspicion. Acute confusion or delirium may be the only manifestation of a stroke, and a fall may be the presenting event rather than a consequence. Atrial fibrillation prevalence rises steeply with age, making cardioembolic stroke and anticoagulant-associated haemorrhage both more likely, and polypharmacy makes the medication reconciliation genuinely diagnostic. Age-related cerebral atrophy creates extra space inside the vault, so an older patient tolerates a growing subdural haematoma for far longer before signs appear — the presentation is often insidious confusion weeks after a minor head bump, and the classic pressure signs come late. Reduced renal reserve raises the risk from mannitol, contrast and osmotic shifts, so monitor creatinine and electrolytes closely. Baseline sensory impairment and cognitive decline make assessment harder, which is exactly why obtaining the family’s account of the patient’s true baseline is not optional.
Nothing by mouth until the swallow screen is passed, protect the affected shoulder and skin, mobilise early with the rehabilitation team, and discharge every patient on mechanism-matched antithrombotic therapy, a high-intensity statin, controlled blood pressure and a family who can recognise BE-FAST and call 911.
The chapter in one breath
Cerebral perfusion pressure is mean arterial pressure minus intracranial pressure, and every disorder in this chapter attacks one of those two terms. Ischaemic stroke, about 87 percent of cases, starves a territory and leaves a salvageable penumbra whose collateral flow is pressure-dependent — so blood pressure is permitted up to 220/120 mmHg unless a thrombolytic is being given, in which case it must be below 185/110 before and below 180/105 for twenty-four hours after. Establish last known well, exclude blood with non-contrast CT, quantify with the NIHSS, treat within 4.5 hours, and send large-vessel occlusions for thrombectomy. Haemorrhagic stroke reverses the logic: the vessel is open, so the systolic pressure comes down toward 140 mmHg and anticoagulation is reversed immediately, while aneurysmal subarachnoid haemorrhage adds early aneurysm securing, rigid pressure control until it is secured, and enteral nimodipine every four hours for twenty-one days against vasospasm that peaks on days 4 to 14. Raised intracranial pressure announces itself first as a falling level of consciousness; the Cushing triad is herniation already happening. Treat with midline positioning, venous drainage, osmotherapy and cerebrospinal fluid drainage — not routine hyperventilation. Then keep the patient nil by mouth until the swallow screen is passed, because aspiration pneumonia is what actually kills stroke survivors.
Words worth knowing
| Term | What it means |
|---|---|
| Last known well | The last moment the patient was observed at neurologic baseline; the clock for thrombolysis starts here, not at symptom discovery |
| Ischaemic penumbra | Hypoperfused but still living tissue surrounding an infarct core, salvageable if flow is restored and dependent on collateral perfusion pressure |
| Permissive hypertension | Deliberately tolerating an elevated blood pressure in acute ischaemic stroke, treating only above 220/120 mmHg, to preserve penumbral flow |
| NIHSS | National Institutes of Health Stroke Scale, an eleven-item 0–42 point standardised neurologic examination used to grade stroke severity and track change |
| Alteplase | Recombinant tissue plasminogen activator; 0.9 mg/kg to a maximum of 90 mg, ten percent as a bolus and the rest over 60 minutes, within 4.5 hours of last known well |
| Tenecteplase | A single-bolus fibrinolytic, 0.25 mg/kg to a maximum of 25 mg, increasingly used in place of alteplase for acute ischaemic stroke |
| Orolingual angioedema | Swelling of the tongue and lips occurring in a small percentage of patients receiving alteplase, more common with concurrent ACE inhibitor therapy |
| Mechanical thrombectomy | Catheter-based clot retrieval for large-vessel occlusion, standard within 6 hours and selectively out to 24 hours with favourable perfusion imaging |
| Haematoma expansion | Growth of an intracerebral bleed in the first hours, the main preventable driver of death and disability; limited by blood pressure control and anticoagulant reversal |
| Thunderclap headache | Sudden headache maximal within seconds, classic for subarachnoid haemorrhage and never to be dismissed as migraine |
| Xanthochromia | Yellow discolouration of cerebrospinal fluid from broken-down blood, supporting subarachnoid haemorrhage when the CT is negative |
| Nimodipine | Calcium channel blocker given 60 mg orally or enterally every 4 hours for 21 days after aneurysmal subarachnoid haemorrhage; never given intravenously |
| Cerebral vasospasm | Delayed arterial narrowing after subarachnoid haemorrhage beginning around day 3 and peaking days 4 to 14, causing delayed cerebral ischaemia |
| Cerebral salt wasting | Renal sodium and volume loss after brain injury producing hypovolaemic hyponatraemia; treated with salt and volume, unlike euvolaemic SIADH, which is fluid-restricted — but in aneurysmal subarachnoid haemorrhage neither is fluid-restricted, and hyponatraemia is corrected while maintaining euvolaemia |
| Monro–Kellie doctrine | The principle that brain, blood and cerebrospinal fluid occupy a fixed cranial volume, so an increase in one must be offset or the pressure rises |
| Cerebral perfusion pressure | Mean arterial pressure minus intracranial pressure; target 60–70 mmHg in a monitored patient |
| Cushing triad | Widening pulse pressure with rising systolic pressure, bradycardia and irregular respirations — a late sign of herniation, not an early warning |
| Uncal herniation | Displacement of the temporal lobe compressing the third cranial nerve, producing an ipsilateral fixed dilated pupil with contralateral hemiparesis |
| External ventricular drain | Catheter in a lateral ventricle that measures intracranial pressure and drains cerebrospinal fluid; levelled at the foramen of Monro and clamped before repositioning |
| Unilateral neglect | Failure to attend to one side of the body or environment, typical of right hemisphere stroke and a major fall and injury risk |