Controlling Microbes — Sterilization, Disinfection & Asepsis
Washing your hands, wiping a bedrail, opening a sterile dressing kit, hanging an IV bag: every one of those acts is microbial control. Microbial control is the planned work of killing microbes, or of holding their numbers down so they cannot cause harm. The trouble is the words. In daily speech they are loose. In clinical work they are exact. The gap between "clean," "disinfected," and "sterile" is the gap infections slip through. This chapter sorts the words out. It then walks through the physical and chemical tools that kill microbes. It shows why a kill follows a steady curve instead of an on and off switch. It ends with the two levels of asepsis used in care, many times a day. Learn this well and infection control stops being a list of rules. It starts being something you understand.
By the end of this chapter you can
- Define and rank sterilization, disinfection, antisepsis, and sanitization, and use the -cidal and -static suffixes the right way.
- Compare the main physical methods of control, which are moist heat, dry heat, the autoclave, radiation, and filtration, and match each one to what it can and cannot sterilize.
- Explain how the autoclave reaches sterilization, and how a cycle is proven to have worked.
- Describe the main families of chemical disinfectants and antiseptics, and say how each one kills microbes.
- Read the microbial death curve, explain the D-value, and say why sterility is defined as a statistic.
- List the factors that make a kill faster or slower, and rank microbes by how well they resist control.
- Tell medical (clean) asepsis from surgical (sterile) asepsis, and apply the rules of a sterile field.
Section 1The vocabulary of control
A ladder, not a light switch
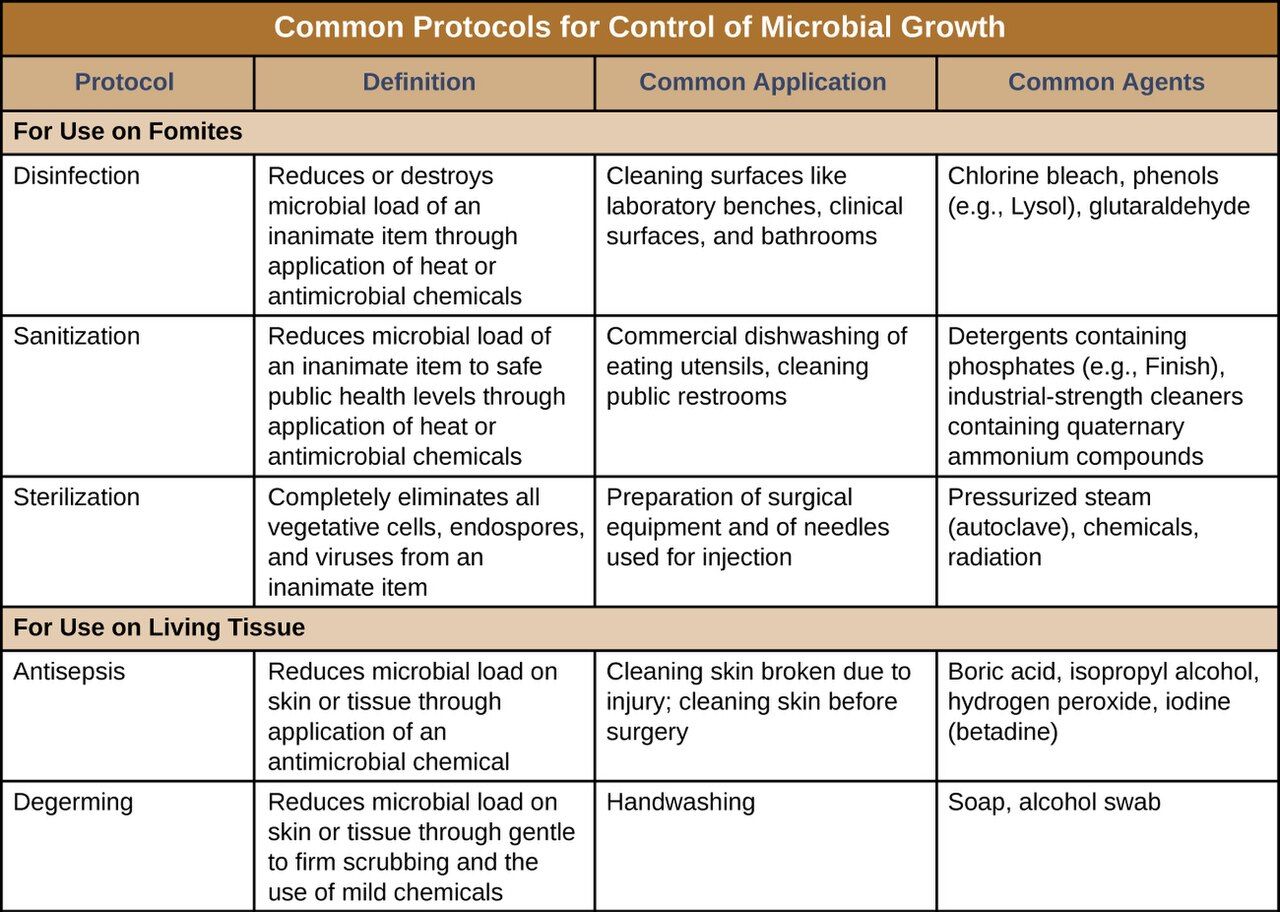
Here is the biggest idea in the chapter. "Getting rid of germs" is not one job. It is a ladder. Each rung strips away more microbial life than the rung below it. Each rung also has an exact name and an exact job. Sterilization sits at the top. It is the complete destruction or removal of all microbial life. That includes the toughest target of all, the bacterial endospore. A sterile object has nothing living on it. Nothing at all. One rung down is disinfection. It destroys most pathogens on a non-living surface. It does not reliably kill endospores. Because it is not absolute, disinfection comes in levels. The levels are high, intermediate, and low, and they rank how much the agent kills. This matters because so much daily work is disinfection and not sterilization. Knowing the difference tells you when a wipe is enough. It also tells you when only a sterile item from central supply will do.
On skin versus on surfaces
The next two words get mixed up constantly. They do similar work in different places. Antisepsis is the removal of microbes from living tissue. That means skin, a mucous membrane, or a surgical site. The chemical used is an antiseptic. It goes on living tissue, so it has to be mild enough to spare that tissue. Disinfection happens on non-living objects instead. The chemical used is a disinfectant. It can be far harsher, because no living cells have to survive it. That is why skin gets prepped with chlorhexidine or an alcohol swab. Both are antiseptics. A counter gets wiped with bleach or a quaternary ammonium solution instead. Both are disinfectants. Pouring a surface disinfectant into a wound is a real mistake, not a shortcut. Two more words finish the set. Degerming is the mechanical scrubbing away of microbes, and the alcohol wipe before an injection does exactly that. Sanitization only lowers microbial counts to a level judged safe for public health. It does not try to remove them. It is the standard for restaurant dishwashers and drinking glasses. It is not the standard for anything that enters the body.
Reading the suffixes
Microbiology labels its weapons with two endings, and you need to read them on sight. An agent ending in -cidal kills the target outright. Bactericidal, virucidal, fungicidal, and sporicidal all work that way. An agent ending in -static only stops the target from multiplying. The microbes are still alive. They are simply held in check. They will grow again if the agent is taken away. They will also grow again if the body's immune defenses fail. That split is not just wording. A bacteriostatic drug leans on a working immune system to finish the job. The same idea returns when we reach antimicrobial drugs and people whose immune defenses are weak.
| Term | What it does | Kills endospores? | Used on |
|---|---|---|---|
| Sterilization | Destroys or removes all microbial life | Yes | Instruments, IV fluids, implants |
| Disinfection | Destroys most pathogens (high/intermediate/low level) | Not reliably | Inanimate surfaces & equipment |
| Antisepsis | Reduces microbes on living tissue | No | Skin, mucous membranes, wounds |
| Degerming | Mechanically removes microbes | No | Skin (e.g., pre-injection swab) |
| Sanitization | Lowers counts to a "safe" public level | No | Dishes, food surfaces, floors |
- Sterilization alone removes all life, endospores included. Disinfection works on surfaces and antisepsis on living tissue, and neither one is reliable against spores.
- A disinfectant is a harsh chemical for objects. An antiseptic is a mild chemical for skin and tissue.
- Sanitization only drops counts to a safe level. Degerming is mechanical removal.
- -cidal kills. -static only halts multiplying, and it leans on host defenses.
Section 2Physical methods — heat, the autoclave, radiation & filtration
Heat: the oldest and most reliable tool
Heat kills in two ways at once. It denatures proteins and enzymes, and it breaks up membranes. It also comes in two forms with very different power. Moist heat means steam and boiling water, and it beats dry heat by a wide margin. Water carries energy well, and it makes proteins clump fast. Think how quickly an egg white sets in boiling water. In a dry oven the same change takes far longer. Dry heat comes from a hot-air oven or an open flame. It works too, but it needs much higher temperatures and much longer times for the same kill. Two old benchmarks describe what heat does. The thermal death point is the lowest temperature that kills all microbes in a suspension in ten minutes. The thermal death time is the time needed to kill them at a set temperature. Now note the key limit. Ordinary boiling at 100°C does not sterilize. It kills vegetative cells and most viruses. It leaves hardy endospores alive. That is the exact problem the autoclave was built to solve. Pasteurization is a gentler cousin of boiling. It uses brief, mild heat, and it does not sterilize. It lowers the count of pathogens and spoilage organisms in milk and other liquids while keeping the flavor.
The autoclave: steam under pressure
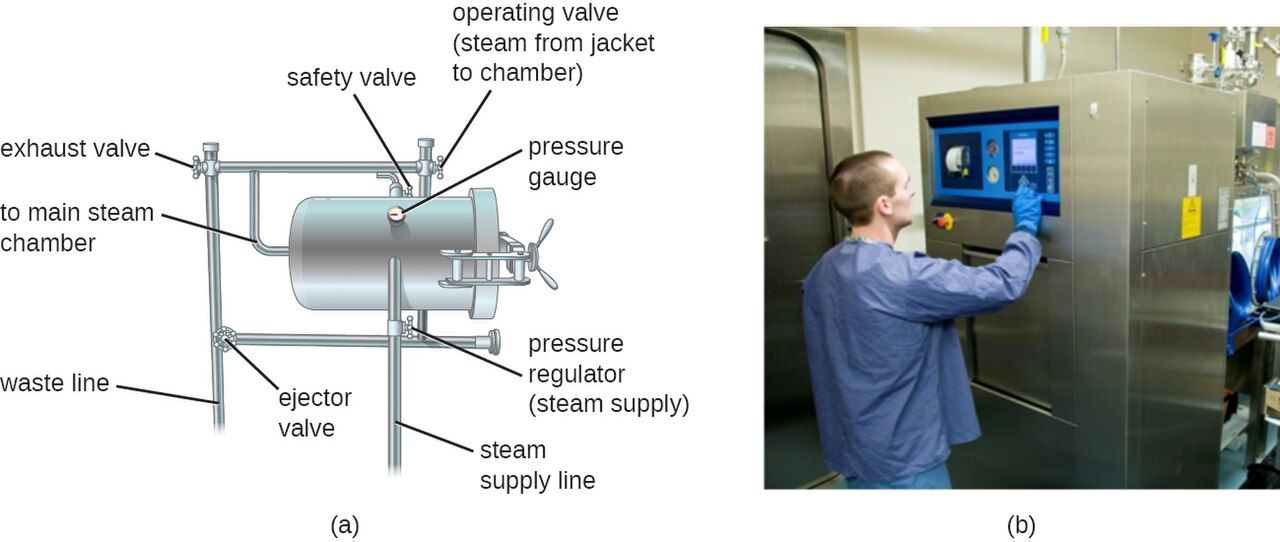
The autoclave is the single most important sterilizing device in health care. It beats the boiling water problem with one simple trick. Raising the pressure raises the boiling point. Steam can then be driven well past 100°C. A standard cycle holds saturated steam at 121°C, at about 15 pounds per square inch (psi) of pressure, for roughly 15 to 20 minutes. Those conditions destroy even endospores. The active ingredient is the moist heat of the steam. The pressure is not the thing that kills. Pressure is only there to make the hotter steam possible. A load counts as sterile only if steam reached every surface, at temperature, for long enough. So autoclaving is always verified and never assumed. Chemical indicators are the striped tape and the pouch dots that change color. They confirm that a load was exposed to heat. The real proof is a biological indicator. That is a sealed vial of Geobacillus stearothermophilus endospores. The vial rides through the cycle and is then incubated. If those famously heat-resistant spores are dead, everything else in the load is dead too.
Radiation and filtration: when heat would ruin the product
Plenty of medical items would be wrecked by an autoclave. Plastic syringes, IV tubing, sutures, and some fluids would melt, warp, or break down. Those get sterilized another way. Radiation splits into two types. Ionizing radiation covers gamma rays, X-rays, and electron beams. It carries enough energy to smash DNA and to spin off destructive free radicals. It goes deep, it works in the cold, and industry uses it for prepackaged disposables and some foods. Nonionizing radiation is mainly ultraviolet (UV) light, and it is much weaker. UV fuses neighboring thymine bases into dimers, and those dimers block DNA copying. UV barely penetrates anything. It cannot pass through glass, plastic, or even a layer of dust. So its use is limited to disinfecting surfaces and air, in biosafety cabinets and empty rooms. It is also a real hazard to the eyes and skin of anyone standing in the room. Filtration is different again. It removes microbes instead of killing them. A fluid or gas is strained through pores too small for cells to pass. A membrane filter with 0.2 µm pores sterilizes heat-sensitive liquids, such as certain antibiotics, vitamins, and IV additives. HEPA filters do the same job for air. They keep operating rooms and protective isolation rooms clean.
| Method | How it kills / removes | Sterilizes? | Typical use |
|---|---|---|---|
| Autoclave (moist heat) | Steam at 121°C, 15 psi denatures proteins | Yes (spores too) | Surgical instruments, glassware, media |
| Dry heat / flame | Oxidation & denaturation at high temp | Yes (long/hot) | Glassware, inoculating loops |
| Boiling (100°C) | Denatures proteins | No — spores survive | Home disinfection of vegetative cells |
| Ionizing radiation | Breaks DNA, forms free radicals | Yes | Disposable plastics, sutures, foods |
| UV (nonionizing) | Thymine dimers block replication | Surface only | Air & surfaces in cabinets/rooms |
| Membrane filtration | Physically strains out cells (0.2 µm) | Yes (fluids) | Heat-labile fluids; HEPA for air |
- Moist heat beats dry heat, and ordinary boiling does not sterilize, because endospores survive it.
- The autoclave holds 121°C at about 15 psi for roughly 15 minutes. It sterilizes with pressurized steam, and a Geobacillus spore biological indicator proves the cycle worked.
- Ionizing radiation sterilizes heat-sensitive disposables. UV only disinfects surfaces and air, because it does not penetrate.
- Filtration with a 0.2 µm membrane or a HEPA filter strips microbes out of heat-labile fluids and out of air.
Section 3Chemical methods — disinfectants & antiseptics
How chemicals kill
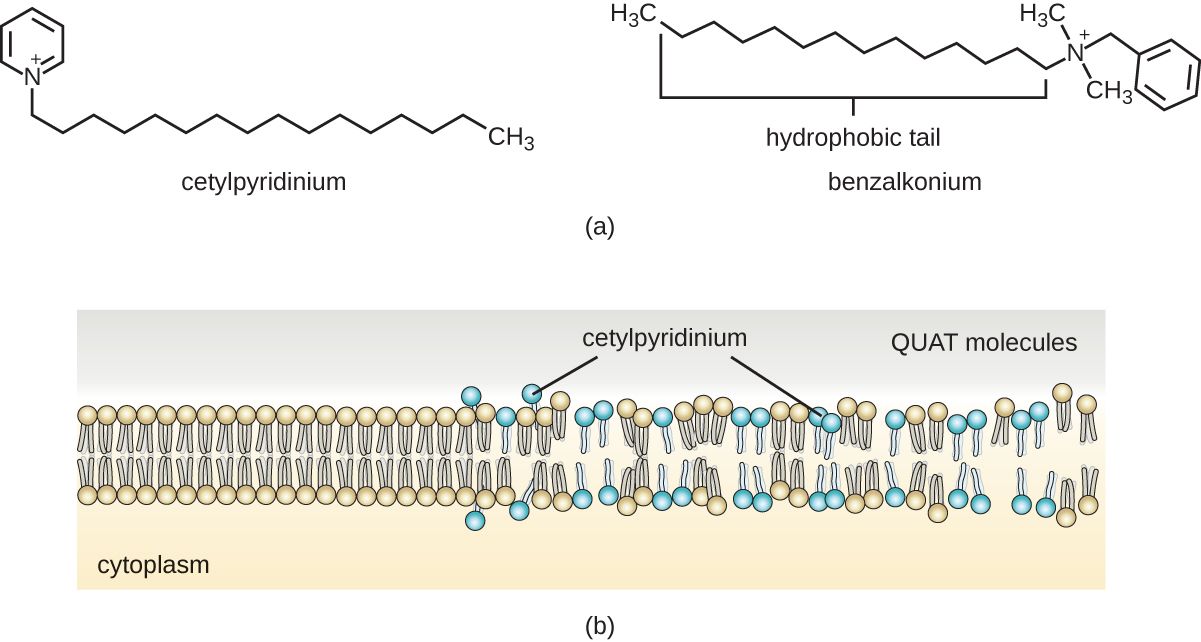
Chemical control agents work in a handful of ways, and most of them fall into two big buckets. Some denature proteins. They unfold the enzymes a microbe needs to stay alive. Others disrupt the plasma membrane. They dissolve its lipids, so the cell leaks and dies. A few go further and damage nucleic acids or oxidize cell parts. Whether a chemical is called a disinfectant or an antiseptic depends on where it is used. It does not depend on the molecule itself. Several agents serve as both at different strengths, and iodine and the quats are good examples. Two practical properties decide whether a chemical is useful in a hospital. The first is its use-dilution, which is the concentration at which it truly works. Stronger is not always better. 70% alcohol kills better than 100% alcohol, because alcohol needs water to denature protein. The second property is how the agent behaves around organic matter such as blood and pus. Organic matter can cancel many agents out on contact.
The chemical families you will meet
You do not need to memorize every compound. You do need to know the major families and where each one shines. Alcohols are isopropyl and ethanol, and they work best at 60% to 90%. They denature proteins and dissolve membranes. They are fast, cheap skin antiseptics and surface wipes. They also dry off quickly and do not kill spores. Chlorhexidine is a mild, long-lasting skin antiseptic. It binds to skin and keeps killing for hours. That is why it is chosen for surgical scrubs and central line site care. Iodophors are iodine held inside a carrier, and povidone-iodine, sold as Betadine, is the common one. They are broad-spectrum skin preps for surgery and for injections. Halogens also include chlorine, which you know as household bleach, or sodium hypochlorite. Bleach is strong and cheap. It is one of the few agents that reliably kills Clostridioides difficile spores on surfaces. Hydrogen peroxide and the other peroxygens oxidize cell parts, and they work well on surfaces and some equipment. Quaternary ammonium compounds (quats) are low-toxicity, detergent-like disinfectants for everyday surface cleaning, though they are weak against some resistant organisms. Glutaraldehyde can sterilize delicate, heat-sensitive equipment when the contact time is long enough. So can the gas ethylene oxide. Both are toxic and both demand strict handling. Ortho-phthalaldehyde (OPA) belongs beside them by chemistry but not by power. It is a fast-acting high-level disinfectant with poor sporicidal activity. It is cleared for high-level disinfection of endoscopes. It is not a sterilant.
Matching the agent to the risk
No single chemical does everything. So hospitals sort items by how much killing each one needs. That scheme is the Spaulding classification. Critical items enter sterile tissue or the bloodstream, and surgical instruments, catheters, and implants all qualify. They must be sterilized. Semicritical items touch mucous membranes but not sterile tissue, and endoscopes and respiratory equipment qualify. They need at least high-level disinfection. Noncritical items touch only intact skin, and blood pressure cuffs, bedrails, and stethoscopes qualify. They need only low-level or intermediate-level disinfection. This one framework quietly governs a huge share of practice, from the bedside to central supply. It is the reason a scope gets a different reprocessing protocol than a bedrail.
| Agent family | Mechanism | Kills spores? | Typical use |
|---|---|---|---|
| Alcohols (60–90%) | Denature protein, dissolve membrane | No | Skin antiseptic, surface wipes, hand rub |
| Chlorhexidine | Disrupts membrane; persists on skin | No | Surgical scrub, line-site antisepsis |
| Iodophors (povidone-iodine) | Oxidize / halogenate cell components | No (routine use) | Pre-op skin prep, injection sites |
| Chlorine (bleach) | Strong oxidizer | Yes (surfaces) | Surface disinfection, C. diff rooms |
| Hydrogen peroxide | Oxidizes cell components | Yes (high conc.) | Surface disinfection, equipment, vaporized room decontamination |
| Quats | Detergent-like membrane disruption | No | Routine surface cleaning |
| Glutaraldehyde / ethylene oxide | Alkylate proteins & DNA | Yes (long contact) | Sterilizing heat-sensitive equipment |
| Ortho-phthalaldehyde (OPA) | Alkylates proteins | No — poor sporicide | High-level disinfection of endoscopes (not sterilization) |
- Chemical agents mostly denature proteins or disrupt membranes, and the same molecule can be a disinfectant on surfaces and an antiseptic on skin.
- Alcohols and chlorhexidine are the workhorse skin antiseptics. Bleach handles spores on surfaces. Glutaraldehyde and ethylene oxide sterilize heat-sensitive equipment, while OPA is a high-level disinfectant only.
- Use-dilution matters, and 70% alcohol out-kills 100% because alcohol needs water.
- The Spaulding classification sorts items as critical, semicritical, or noncritical, and matches the level of killing to how each item is used.
Section 4The microbial death curve & what changes the odds
Death is logarithmic, not all-at-once
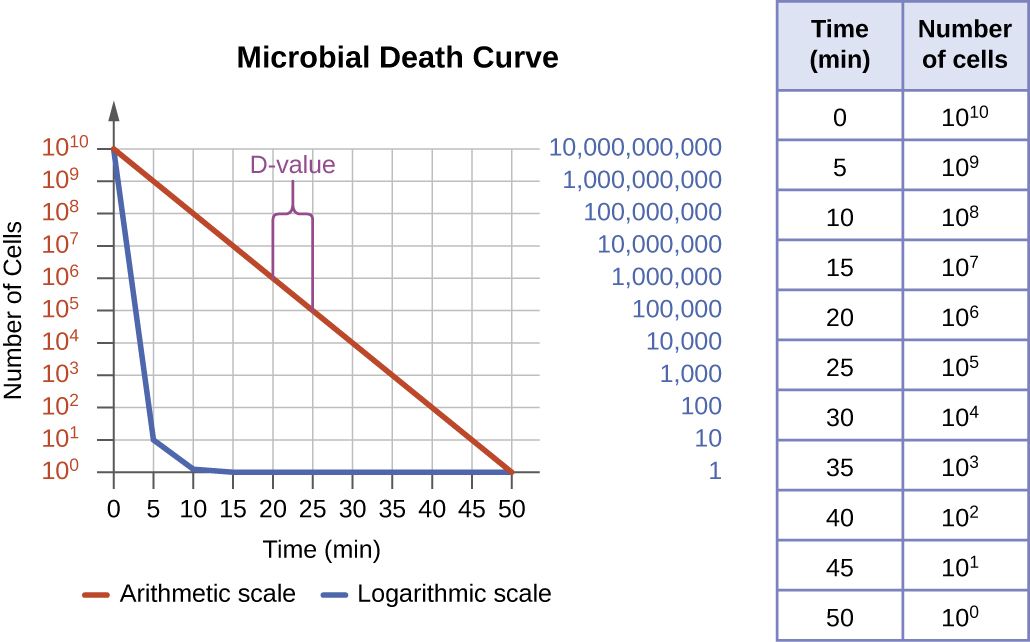
It is tempting to picture a disinfectant killing every microbe the instant it lands. Killing does not work that way. Under a lethal agent, a microbial population dies logarithmically. A constant percentage dies in each equal unit of time. A constant number does not. Say a chemical kills 90% of the cells in the first minute. In the second minute it kills 90% of the survivors. In the third minute it kills 90% of those. Plot that on a log scale and you get a straight line sloping down. That line is the microbial death curve. The consequence runs deep. You are always killing a fraction, and you never pick off the last stubborn cell at once. So you can drive the count vanishingly low, yet you can never reach true zero in a set time. That is why sterility is defined statistically, as a probability. The usual target is a sterility assurance level of one survivor in a million, written 10−6. It is not a promise that nothing is alive.
The D-value
One number captures how steep that line is. It is the decimal reduction time, better known as the D-value. The D-value is the time needed to kill 90% of the population at a given temperature or agent strength. Killing 90% drops the count by one power of ten, and that drop is called one "log". A short D-value means the target dies quickly. A long D-value means a tough target or a weak method. The D-value is the bridge from the curve to real protocols. Start with a known count and a known D-value. You can then work out how long a treatment has to run to reach your target survival level. That is exactly how sterilization cycles and canning times get set.
What speeds up or slows down the kill
The same agent can kill in seconds or fail outright, and the conditions decide which. Knowing the variables lets you spot a control measure being quietly undermined. A kill goes faster with higher temperature. It goes faster with higher concentration or intensity. It goes faster with longer contact time. That last one is why every disinfectant label carries a wet contact time. The surface has to stay visibly wet for that whole time, or the agent never finishes. A kill goes slower, or fails, under several conditions. A huge microbial load takes longer to clear, because the same percentage dies each interval. Some microbes are resistant by nature. A protective biofilm can shield them. And organic matter such as blood, pus, feces, or biofilm both blocks the agent physically and inactivates many agents chemically. Microbes themselves fall into a predictable resistance ranking. Prions sit at the very top and are nearly indestructible. Bacterial endospores come next. Below them sit mycobacteria, whose waxy wall makes tuberculosis hard to kill. Then come non-enveloped viruses, and then fungi such as Candida and the molds. The easiest targets sit at the bottom. Those are ordinary vegetative bacteria and fragile enveloped viruses such as influenza and HIV.
| Factor | Effect on killing | Why |
|---|---|---|
| Time (contact time) | More time → more kill | Each interval removes another fraction (log) |
| Temperature / concentration | Higher → faster kill | Speeds denaturation and reaction rate |
| Number of microbes | More cells → slower to clear | Same % killed each interval — larger start, longer to finish |
| Microbe type | Spores & mycobacteria resist | Endospore coats and waxy walls block agents |
| Organic matter | Present → killing fails | Blood/pus shield and inactivate the agent |
| Biofilm | Present → strong resistance | Matrix blocks penetration; cells shielded |
- Microbes die logarithmically, a constant fraction per unit time, so true zero is never guaranteed and sterility is a probability, set at a 10−6 assurance level.
- The D-value is the time needed to kill 90%, or one log, of a population, and it sets how long a process must run.
- A kill speeds up with more time, heat, and concentration. It slows down with a big microbial load, resistant organisms, biofilm, and organic matter.
- Resistance ranks from prions and endospores at the toughest end, down through mycobacteria, non-enveloped viruses, and fungi, to vegetative bacteria and enveloped viruses at the easiest end.
Section 5Asepsis at the bedside — medical vs surgical
Two kinds of asepsis
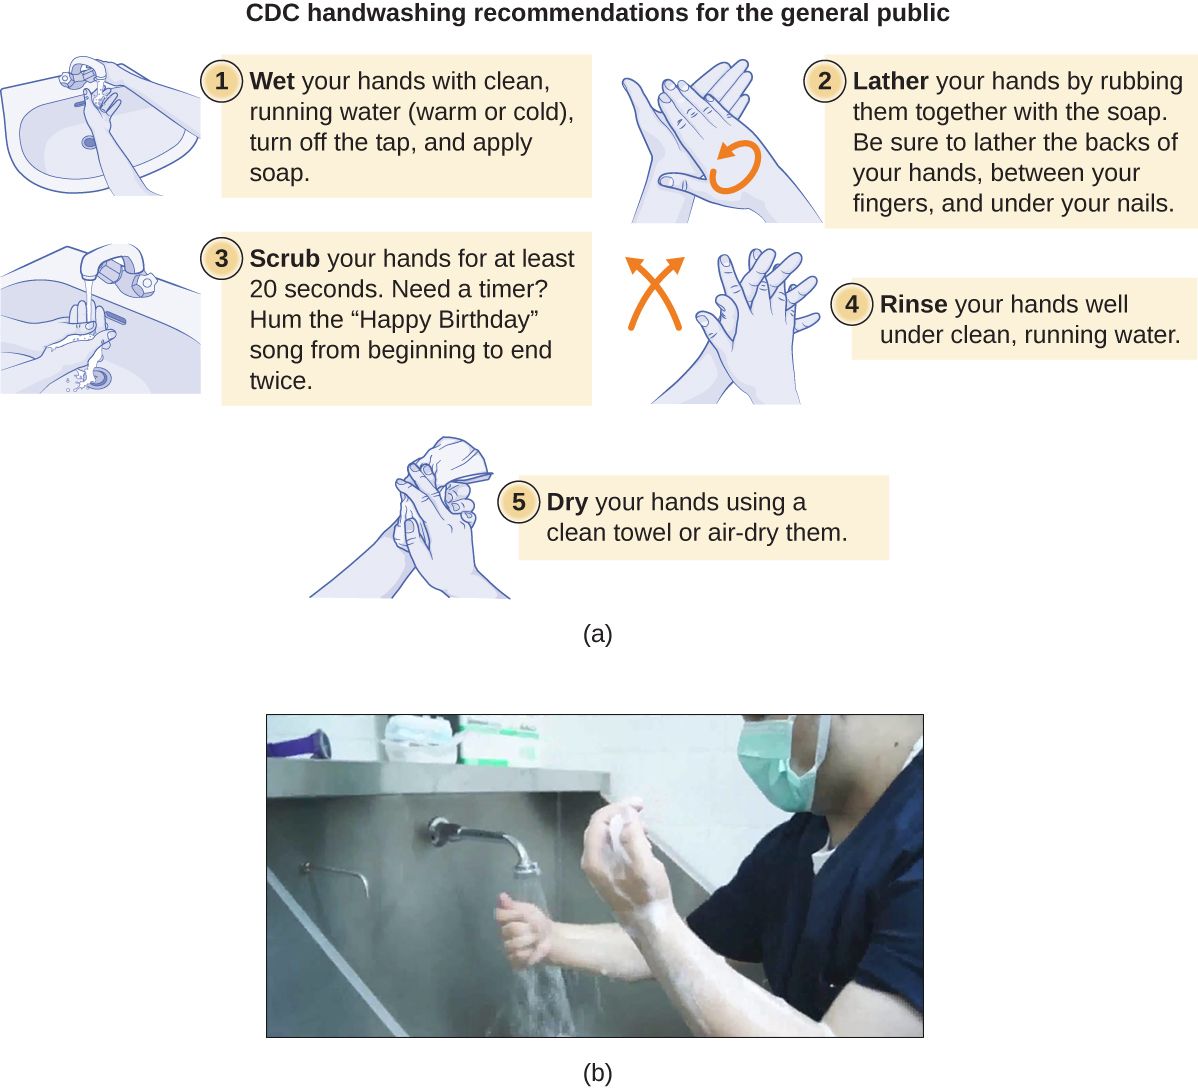
Asepsis means the absence of contamination by pathogens. In care it is practiced at two levels. Medical asepsis is also called clean technique. It aims to reduce the number and spread of microbes, and so to break the chain of transmission. It is the everyday level. It covers hand hygiene, gloves, gowns, cleaning shared equipment, and the standard precautions used with every person, whatever the diagnosis. It does not require sterility. It requires cleanliness and consistency. Surgical asepsis is also called sterile technique. It aims for the total absence of microbes. It is used whenever the body's natural barriers are breached. That covers inserting a urinary or central catheter, changing a sterile dressing on a deep wound, and assisting in the operating room. The shift from clean to sterile is the same ladder you met in Section 1, now applied with gloved hands.
Clean technique: the everyday defense
Medical asepsis rests on a small set of habits. Done reliably, those habits prevent an enormous share of infections. Hand hygiene comes first. It is done before and after every contact with the person being cared for. It is done before a clean task, after exposure to body fluids, and after touching that person's surroundings. Those are the familiar moments of hand hygiene. Alcohol-based hand rub is the default, because it is fast and effective. Soap and water are saved for hands that are visibly soiled. Soap and water are also required for spore-formers like C. diff. Around that core sit gloves and gowns, which guard against splashes. Linens and waste get handled safely. Shared devices get disinfected between uses. Transmission-based precautions are layered on top of standard precautions when a specific organism is in play. None of this is glamorous. All of it works.
Sterile technique: the rules of the field
Surgical asepsis runs on a set of blunt rules. They exist because a sterile field is only sterile until proven otherwise. Once a sterile package is opened, a field is established. From that moment the rules hold. Only sterile items may touch sterile items. A 1-inch border around the drape counts as contaminated. Anything held below waist level counts as contaminated. So does anything out of your line of sight, because you cannot vouch for what you cannot see. You never reach across the field, and you never turn your back on it. Any moisture that wicks through the drape contaminates it. That wicking is called strike-through, and microbes travel along the wet path. Sterile gloves and gowns stretch the field to your hands and your front. The idea behind all of it is honest humility. When you are in doubt about whether something is still sterile, you treat it as contaminated and start over. A fresh drape is cheap. A bloodstream infection is not.
| Feature | Medical asepsis (clean) | Surgical asepsis (sterile) |
|---|---|---|
| Goal | Reduce number & spread of microbes | Eliminate all microbes |
| Standard | Clean | Sterile |
| Typical tasks | Hand hygiene, gloves/gowns, cleaning | Catheter insertion, sterile dressings, OR |
| Hand practice | Handwash or alcohol rub | Surgical hand scrub, sterile gloves |
| If contaminated | Re-clean and continue | Discard field and restart |
- Medical asepsis, or clean technique, reduces and contains microbes through hand hygiene, gloves, gowns, and cleaning, and it is used with every person.
- Surgical asepsis, or sterile technique, aims to eliminate all microbes, and it is used whenever a natural barrier is breached.
- A sterile field is contaminated by anything nonsterile, by a 1-inch border, by items below waist level or out of sight, and by moisture strike-through.
- The governing rule is "when in doubt, it's contaminated", so you discard and restart instead of gambling.
The chapter in one breath
- Microbial control is a ladder: sterilization removes all life including spores, disinfection handles surfaces, antisepsis handles living tissue, and sanitization only drops counts to a safe level.
- -cidal agents kill. -static agents only stop multiplying, and they rely on the host's immune system.
- Physical methods: moist heat beats dry heat, the autoclave at 121°C and 15 psi sterilizes and is verified by a Geobacillus spore indicator, and radiation plus 0.2 µm filtration handle heat-sensitive items.
- Chemical methods denature proteins or disrupt membranes. Alcohols and chlorhexidine prep skin, bleach kills spores on surfaces, and the Spaulding classification matches the killing level to how an item is used.
- Microbes die logarithmically. The D-value is the time to kill 90%, and sterility is a statistical assurance level, never an absolute.
- A kill is slowed by big loads, resistant organisms, biofilm, and above all by organic matter, so you always clean before you disinfect.
- In care, medical asepsis is the everyday clean default and surgical asepsis is the sterile standard whenever a barrier is breached. When in doubt, it's contaminated.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or circle back whenever a word trips you up.
- Antisepsis
- The reduction or removal of microbes from living tissue, using an antiseptic.
- Antiseptic
- A chemical mild enough to apply to living skin or tissue, e.g., alcohol or chlorhexidine.
- Asepsis
- The absence of contamination by pathogens; practiced as medical (clean) or surgical (sterile) technique.
- Autoclave
- A device that sterilizes with pressurized saturated steam, typically 121°C at ~15 psi for ~15 minutes.
- Bactericidal / bacteriostatic
- Agents that respectively kill bacteria (-cidal) or merely stop them multiplying (-static).
- Biological indicator
- A vial of heat-resistant spores run through a cycle to confirm true sterilization.
- D-value (decimal reduction time)
- The time needed to kill 90% (one log) of a microbial population under set conditions.
- Degerming
- The mechanical removal of microbes from skin, e.g., scrubbing before an injection.
- Disinfection
- Destruction of most pathogens on an inanimate surface; does not reliably kill endospores.
- Endospore
- A dormant, extremely resistant bacterial structure that is the toughest living target of microbial control.
- Filtration
- Physical removal of microbes by straining fluid or air through pores too small for cells (e.g., 0.2 µm, HEPA).
- Medical asepsis
- "Clean technique" that reduces the number and spread of microbes; the everyday level of care.
- Microbial death curve
- The logarithmic (straight-line, on a log scale) decline of a population under a lethal agent.
- Pasteurization
- Brief mild heating that lowers pathogen and spoilage counts in liquids without sterilizing.
- Sanitization
- Reduction of microbial counts to a level judged safe for public health, e.g., dishes and food surfaces.
- Spaulding classification
- A scheme rating items critical, semicritical, or noncritical to set the required level of processing.
- Sterility assurance level (SAL)
- The statistical probability of a survivor after sterilization, conventionally one in a million (10−6).
- Sterilization
- The complete destruction or removal of all microbial life, including endospores.
- Strike-through
- Moisture wicking through a sterile drape, which carries microbes along the wet path and contaminates the field.
- Surgical asepsis
- "Sterile technique" aiming for the total absence of microbes; used when barriers are breached.
- Thermal death point / time
- The lowest temperature that kills all microbes in a suspension in ten minutes, and the time a given temperature needs to do it.
- Use-dilution
- The working concentration at which a chemical agent is effective (more is not always better).